
Adaptogens for Libido: Which Support and Which Do Not
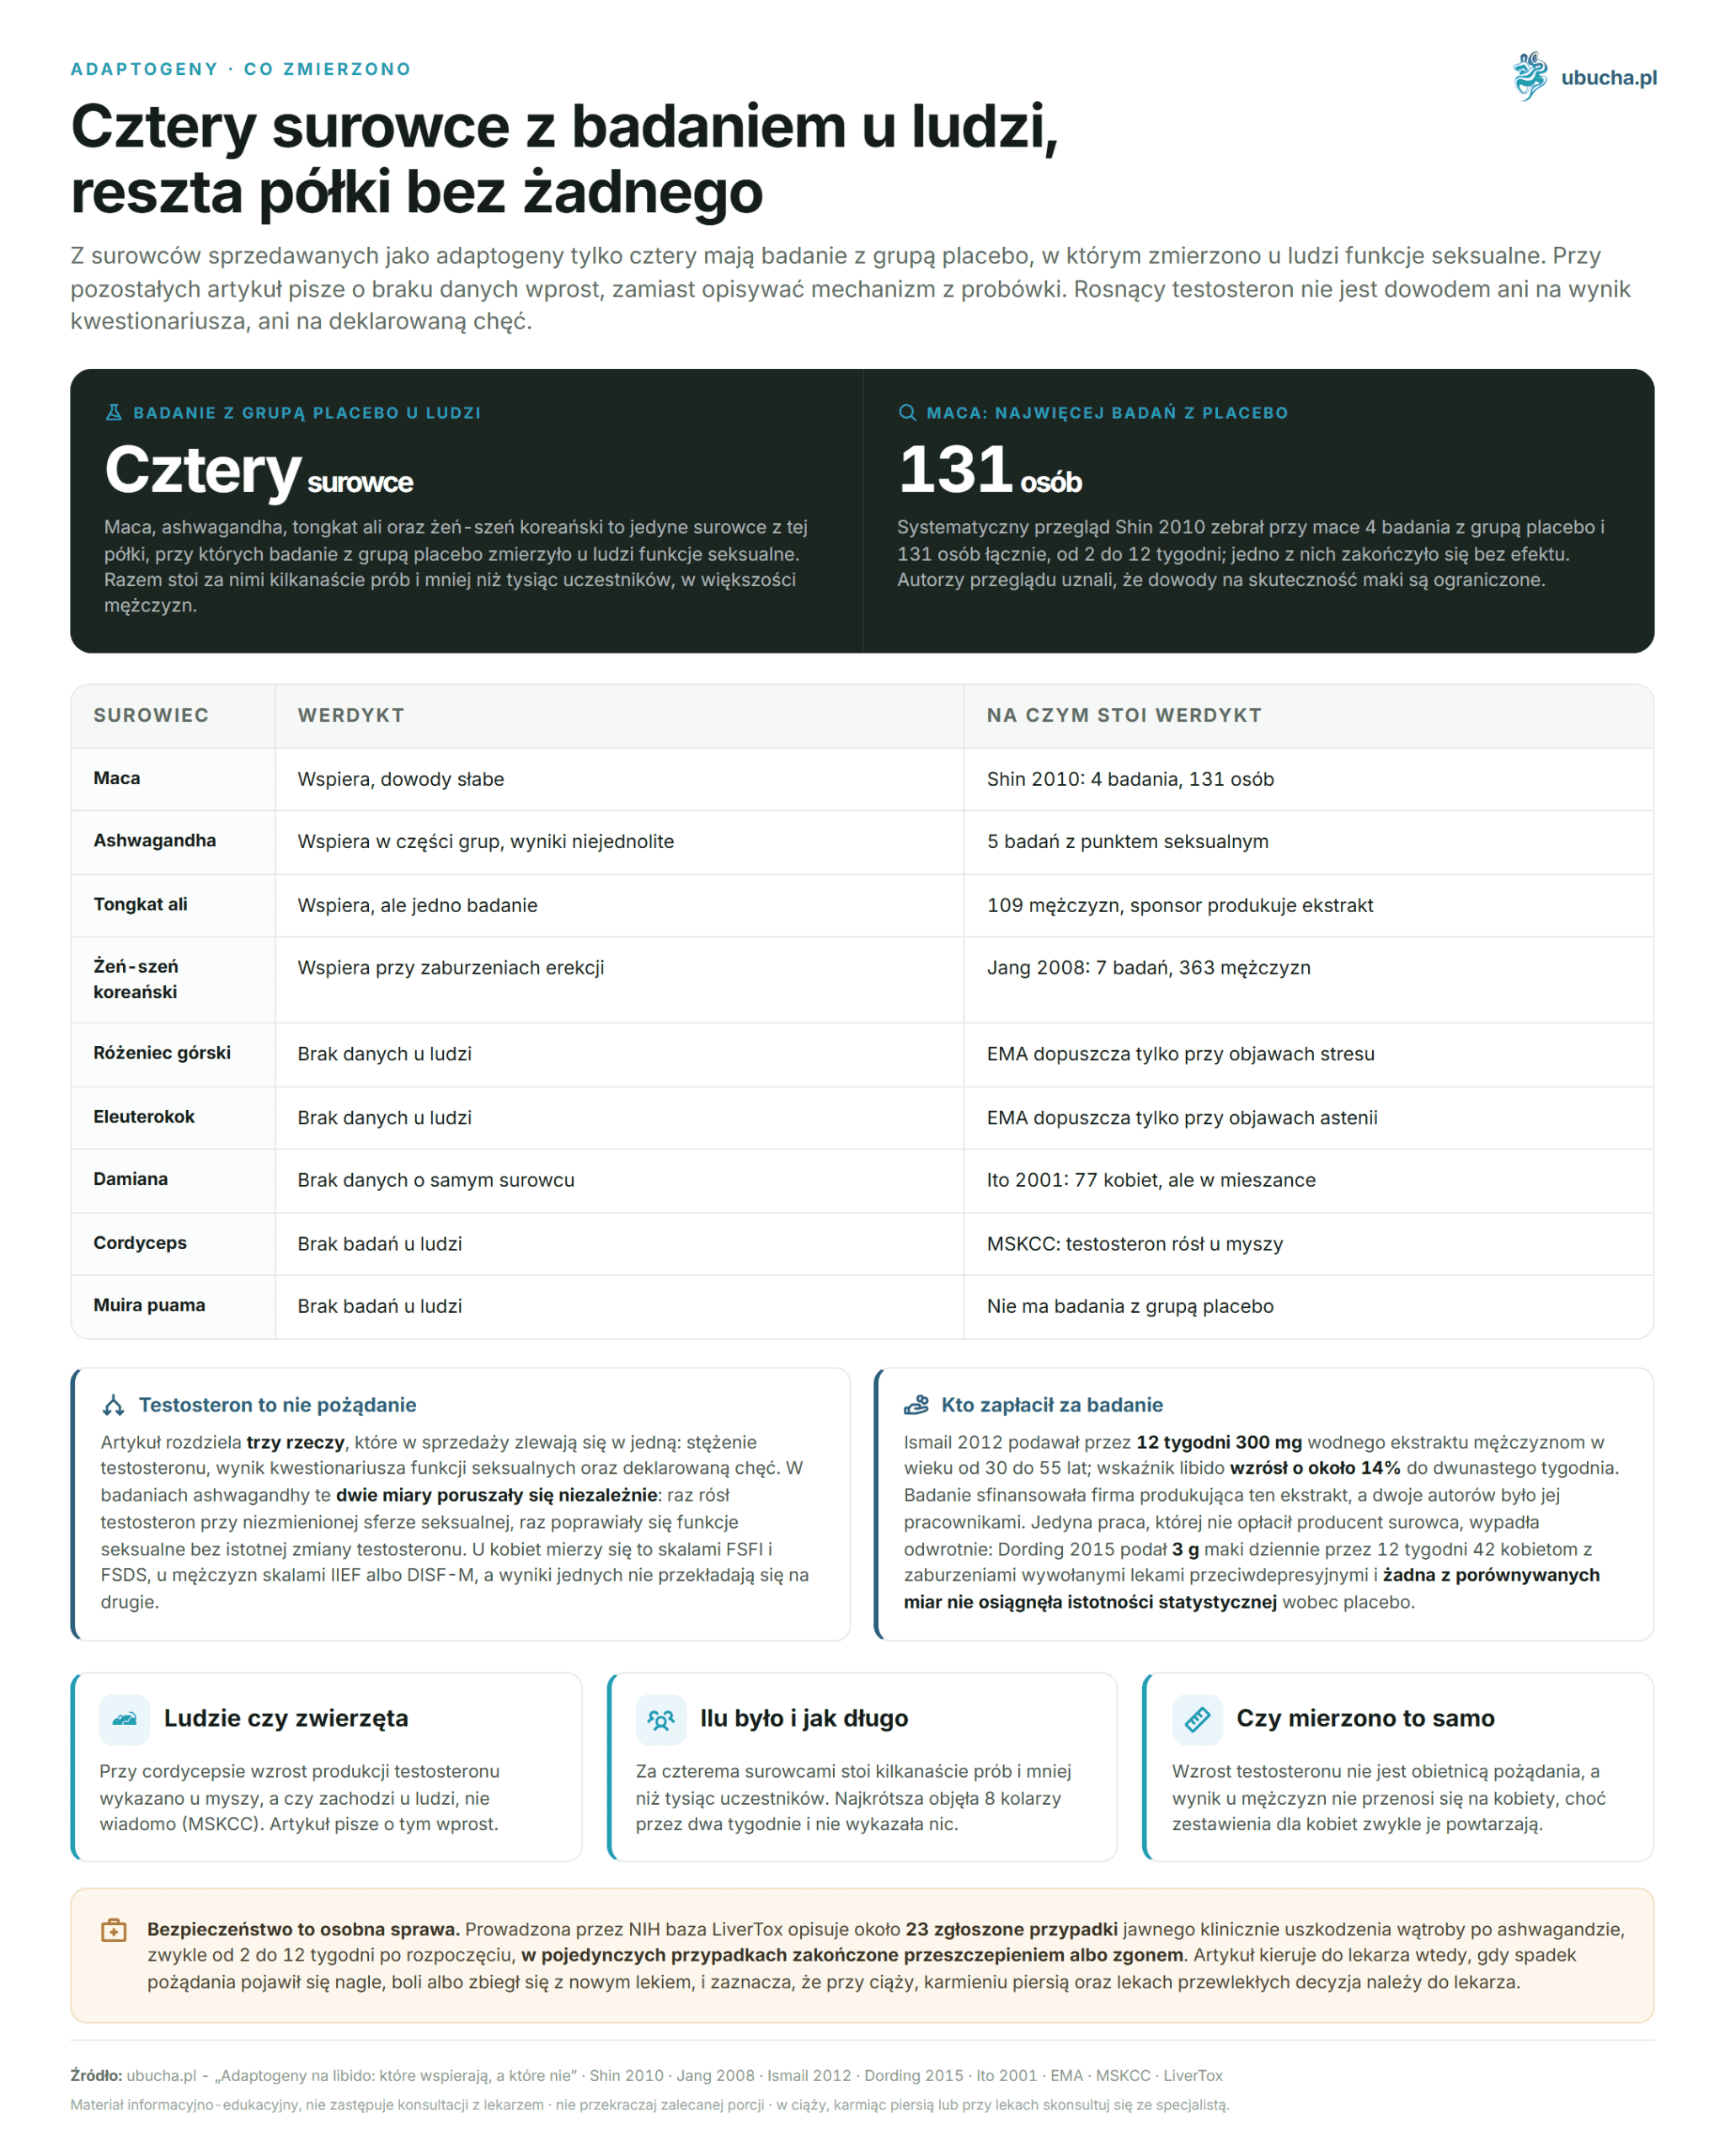
Four adaptogens have placebo studies on sexual functions, the rest have none. A table with the verdict, number of participants, and funding source.
Of the raw materials sold as adaptogens, only four have placebo-controlled studies measuring sexual function in humans: maca, ashwagandha, tongkat ali, and Korean ginseng. The rest of this category, led by Rhodiola rosea, has not a single such trial. Below is a table with the verdict for each raw material and what the verdict is based on: how many people, how long, and who funded the study. We separate three things that blend into one in sales: testosterone levels, sexual function questionnaire results, and declared desire. Increasing testosterone is not evidence of the other two. Where there are no studies in humans, we state this directly instead of describing the mechanism from a test tube.
KEY INFORMATION
• Maca: 4 placebo studies, 131 participants total in the Shin 2010 review, authors’ conclusion: evidence limited
• Tongkat ali: 1 study, 109 men, 12 weeks, libido index increased by 14% (Ismail 2012), sponsor produces extract
• Korean ginseng: 7 studies, 363 men with erectile dysfunction (Jang 2008), authors advise against final conclusions
• Ashwagandha: 5 studies with sexual endpoint, results varied in women and men
• Rhodiola rosea and eleutherococcus: zero studies with such an endpoint, EMA approves them only for fatigue and weakness
• Cordyceps: testosterone increased in mice, not tested in humans (MSKCC)
Which adaptogens have placebo-controlled studies on sexual functions?
Four: maca, ashwagandha, tongkat ali, and Korean ginseng. Together, they are backed by a dozen trials and fewer than a thousand participants, mostly men. The remaining raw materials in this category either have no studies with a sexual endpoint or have been tested only in multi-ingredient mixtures, from which the contribution of a single plant cannot be isolated.
| Raw Material | Verdict | What the verdict is based on |
|---|---|---|
| Maca (Lepidium meyenii) | supports, weak evidence | Shin 2010: 4 studies, 131 people, from 2 to 12 weeks; one of them with no effect |
| Ashwagandha (Withania somnifera) | supports in some groups, results inconsistent | 5 studies with sexual endpoint: in women 2 positive, in men 2 positive and 1 zero |
| Tongkat ali (Eurycoma longifolia) | supports, but one study | Ismail 2012: 109 men, 12 weeks, 300 mg; sponsor produces extract |
| Korean ginseng (Panax ginseng) | supports in erectile dysfunction | Jang 2008: 7 studies, 363 men, from 4 to 12 weeks |
| Rhodiola rosea (Rhodiola rosea) | no data in humans | EMA: approved only for occasional stress symptoms |
| Eleutherococcus (Eleutherococcus senticosus) | no data in humans | EMA: approved only for asthenia symptoms |
| Damiana (Turnera diffusa) | no data on the raw material itself | Ito 2001: 77 women, 4 weeks, but in a mixture with four other ingredients |
| Cordyceps | no studies in humans | MSKCC: testosterone increased in mice, not tested in humans |
Why does maca perform best in this comparison?
Because it has four placebo-controlled studies, not just one, and among them is a trial that ended with zero, which allows us to see the spread of results instead of just successes. The systematic review by Shin 2010 included 131 participants and concludes with the statement that the evidence for the effectiveness of maca is limited.
The distribution of these four trials looks like this. Zenico 2009 administered 2400 mg daily for 12 weeks to 50 men with mild erectile dysfunction and achieved improvement in the IIEF-5 scale. Gonzales 2002 administered 1500 or 3000 mg for 12 weeks to 57 healthy men and noted an increase in reported desire in the eighth and twelfth weeks, although the authors of the review describe this endpoint as poorly documented. Brooks 2003 included 16 postmenopausal women for 6 weeks. Stone 2009 included 8 cyclists for 2 weeks and showed no difference compared to placebo.
Additionally, there is a trial that was not included in the review yet. Dording 2015 administered 3 g of maca daily for 12 weeks to 42 women with sexual disorders caused by antidepressants. None of the compared measures achieved statistical significance compared to placebo. The study was funded by a grant from the US NCCAM, not the raw material producer, and this is the only work in this comparison that can be said. More numbers are available in the text about the properties of maca.
What do studies on tongkat ali and Korean ginseng show?
One study on 109 men and a review of seven studies on 363 men. Both report improvement and both have serious reservations. The first was funded by the company producing the used extract, and the authors of the second state directly that the material is too limited to draw final conclusions.
Ismail 2012 administered 300 mg of aqueous Physta extract to men aged 30 to 55 for 12 weeks. The erectile domain score in the IIEF questionnaire was significantly higher than in placebo, and the libido index increased by about 14% by the twelfth week. The study was funded by Biotropics Malaysia, and two authors were its employees; Physta is its product. Dosage and composition are discussed separately in the text about tongkat ali and testosterone.
Jang 2008 gathered 7 placebo-controlled studies on red ginseng in men with erectile dysfunction, totaling 363 participants aged 24 to 70, treated for 4 to 12 weeks. The meta-analysis of three studies with available IIEF results favored ginseng. The concluding statement of this review is, however, cautious: the number of studies, total number of participants, and methodological quality were too low to settle the matter.
Which popular raw materials have no studies in humans on libido?
Rhodiola rosea, eleutherococcus, cordyceps, and muira puama. None of them has a placebo-controlled trial measuring sexual function in humans. Damiana has such a study, but only as an ingredient in a mixture, so its individual contribution cannot be isolated.
The European Medicines Agency approves the root of Rhodiola rosea only for the occasional relief of stress symptoms, such as fatigue and weakness, and the root of eleutherococcus for alleviating asthenia symptoms. Neither monograph mentions the sexual sphere, and both are based on traditional use, as the quality of clinical studies was deemed insufficient. Regarding cordyceps, Memorial Sloan Kettering states that an increase in testosterone production has been shown in mice, but whether it occurs in humans is unknown.
Damiana was included in the Ito 2001 study as one of five ingredients in a preparation given to 77 women for 4 weeks. Satisfaction with sexual life improved in 73.5% of the active group compared to 37.2% of the placebo group, but the capsule also contained ginseng, ginkgo, L-arginine, and vitamins with minerals. Such a study says nothing about damiana itself. The same applies to muira puama, described in more detail in the post about muira puama and catuaba.
How to read promises on labels and when to give up?
Three questions cover most packages. Was the study done in humans, not animals? How many participants were there and how long did it last? Was what the label promises measured accurately? An increase in testosterone is not a promise of desire, and a result obtained in men does not transfer to women.
Comparisons for women usually repeat results from male trials, although in this category the data diverges the most: in women, they are measured using FSFI and FSDS scales, in men using IIEF or DISF-M scales, and the results of one do not translate to the other. This distinction is described in the context of raw material selection in the text about adaptogens for women.
A separate issue is safety. The NIH-maintained database LiverTox describes about 23 reported cases of clinically evident liver damage after ashwagandha, usually from 2 to 12 weeks after starting, in some cases ending in transplantation or death. A detailed breakdown of studies on this raw material is in a separate text “Ashwagandha and libido: what exactly do scientific studies show”. If a drop in desire appeared suddenly, is painful, or coincided with a new medication, it is a matter for a doctor, not a supplement: the Dording 2015 study shows how little the plant helps with a problem caused by medication. Products from this group have been gathered in the category adaptogens.
Frequently Asked Questions
Which adaptogen has the most research on libido?
Maca. A systematic review by Shin 2010 gathered four placebo-controlled studies involving a total of 131 people, including one with no effect. However, the authors concluded that the number of studies and their quality are too limited to draw firm conclusions.
Do adaptogens increase libido in women?
Data in women is rarer than in men. Ashwagandha has two eight-week studies showing improvement in the FSFI scale, maca has one small study in postmenopausal women and one that ended with no difference compared to placebo in 42 women taking antidepressants.
Does Rhodiola rosea affect libido?
There is no placebo-controlled study measuring sexual function in humans after Rhodiola rosea. The European Medicines Agency approves it only for the occasional relief of stress symptoms, such as fatigue and weakness.
Does an adaptogen that raises testosterone also raise libido?
Not necessarily. In studies of ashwagandha, these two measures moved independently: sometimes testosterone increased with unchanged sexual function, and sometimes sexual functions improved without a significant change in testosterone. These are separate endpoints measured by different tools.
How long did the studies on adaptogens and libido last?
From 2 to 16 weeks. The shortest trial involved 8 cyclists over two weeks and showed no results, while the longest lasted 16 weeks. None checked what happens after discontinuation, so nothing is known about the durability of the effect.
Do damiana and muira puama have studies in humans?
Damiana was included in the Ito 2001 study on 77 women, but as one of five ingredients in the preparation, so its individual contribution cannot be isolated. Muira puama has no placebo-controlled study on sexual functions in humans.
Are adaptogens for libido safe?
Not all and not for everyone. The LiverTox database maintained by NIH describes about 23 cases of liver damage after ashwagandha, usually from 2 to 12 weeks after starting. In pregnancy, breastfeeding, and chronic medications, the decision should be made by a doctor.
When should you see a doctor instead of reaching for a supplement?
When a drop in desire appeared suddenly, is accompanied by pain, or coincided with a new medication. The Dording 2015 study showed that in disorders caused by antidepressants, maca did not show a significant difference compared to placebo.
This article is for informational and educational purposes and does not replace a consultation with a doctor. If you are pregnant, breastfeeding, taking medications, or have chronic conditions, consult the use of supplements or herbs with a specialist.
Author: Michał Waluk · Published: 2026-08-24 · Updated: 2026-08-24