
Supplements for Menopause: What Really Alleviates Symptoms and How to Build a Supplementation Plan
Proven supplements for menopause: sage, vitamin D3+K2, magnesium, ashwagandha, and omega-3. Dosage, evidence from studies, and a ready-made supplementation plan.
Menopause is a natural phase of a woman’s life, but its symptoms can significantly lower quality of life for months, and sometimes years. Hot flashes, night sweats, insomnia, mood swings, dryness of mucous membranes, and accelerated bone loss are the most common complaints during this period. Hormone replacement therapy (HRT) remains the most effective treatment method, but not every woman can or wants to resort to it. Supplements and herbs can be a valuable alternative or complement, but only when choosing those with real clinical evidence, not just a catchy name on the label. Some popular ingredients, such as isoflavones from red clover, have weaker support in studies than their popularity suggests. This article shows what really works, for which symptoms, and in what doses, along with a ready-made supplementation plan.
KEY INFORMATION
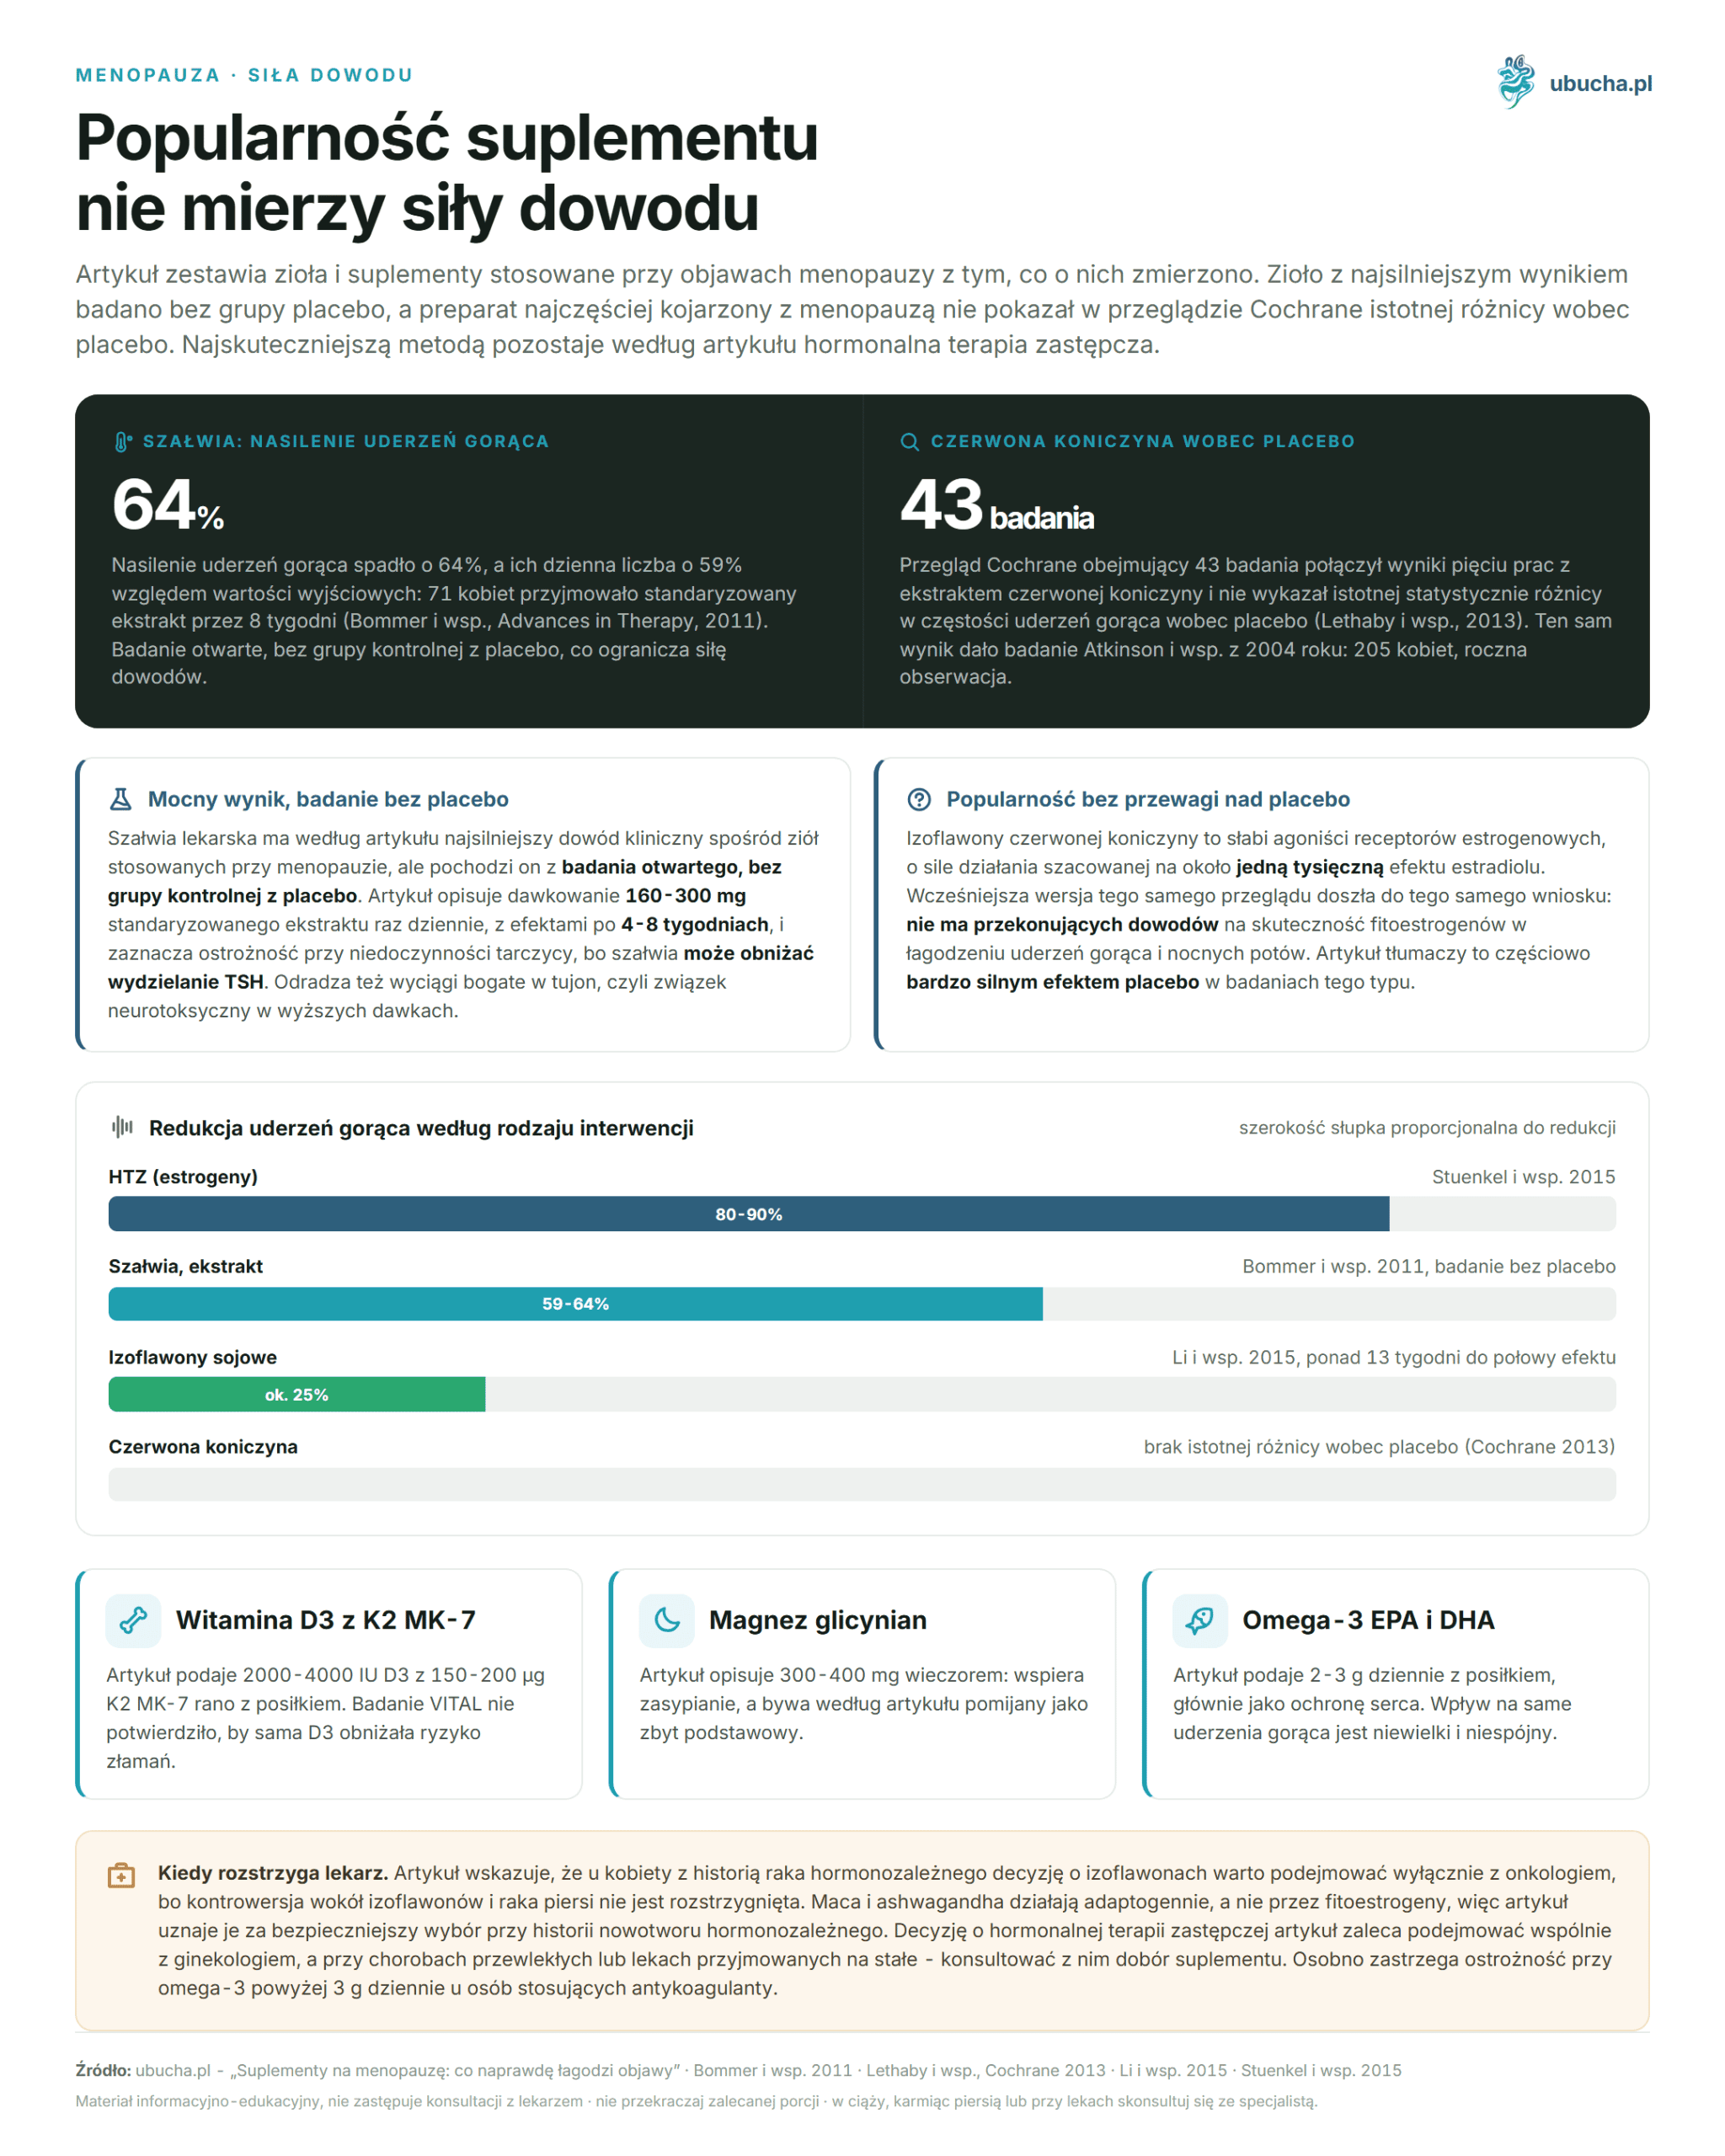
• Sage reduced the intensity of hot flashes by 64% and their daily number by 59% in an 8-week study (Bommer et al., 2011, n=71 women).
• Isoflavones from red clover are popular, but the Cochrane review (Lethaby et al., 2013, 43 studies) found no significant difference in the frequency of hot flashes compared to placebo.
• Vitamin D3+K2, magnesium, and omega-3 form the basis of supplementation, as they support bones, heart, mood, and sleep during menopause.
• Maca and ashwagandha act adaptogenically, not through phytoestrogens, making them a safer choice for women with a history of hormone-dependent cancer.
What Happens to Hormones During Menopause and Why Do Symptoms Occur?
Estrogen levels, mainly estradiol, gradually decrease during the perimenopausal period lasting 4-10 years, and menopause is diagnosed after 12 months without menstruation, usually between the ages of 45 and 55. Estrogens protect bones, blood vessels, and thermoregulation, so their loss triggers most typical symptoms.
Estrogens inhibit excessive activity of osteoclasts responsible for bone loss, limit inflammation of blood vessels, and stabilize thermoregulation. Low estradiol levels disrupt the hypothalamus’s function, leading to sudden dilation of skin blood vessels, i.e., hot flashes. The drop in estrogens causes or exacerbates hot flashes in about 85% of women, night sweats, insomnia in about 60% of women, vaginal dryness, mood swings, depression, accelerated bone loss leading to postmenopausal osteoporosis, and increased risk of cardiovascular diseases.
Supplements do not replace estrogens, but they can support specific mechanisms behind the symptoms. Phytoestrogens, i.e., isoflavones, weakly activate estrogen receptors. Adaptogens, such as maca and ashwagandha, modulate the hypothalamic-pituitary-adrenal axis instead of sex hormone levels. Magnesium, vitamin D3, and K2 protect bones, while omega-3 reduces inflammation of blood vessels. Understanding these mechanisms facilitates the selection of a supplement for a specific symptom.
Does Sage Help with Hot Flashes?
Yes, sage has the strongest clinical evidence among herbs used for menopause. In an eight-week study by Bommer et al. (2011, n=71 women), standardized extract reduced the severity of hot flashes by 64%, and their daily number by 59%.
Sage (Salvia officinalis) has a documented history of use in menopausal symptoms. Bommer et al. (Advances in Therapy, 2011, DOI 10.1007/s12325-011-0027-z) conducted an open study without a placebo group: 71 women took one tablet of standardized sage extract (160 mg) daily for 8 weeks. The severity of hot flashes decreased by 64%, and their daily number by 59% compared to baseline values. The mechanism involves compounds with estrogen-like action, modulating the beta estrogen receptor, as well as anticholinergic action limiting excessive sweating.
The study lacked a placebo control group, which limits the strength of the evidence, but the safety profile of standardized extracts is good. Avoid extracts rich in thujone, a neurotoxic compound in higher doses, although preparations from fresh sage leaves contain little of it. Dosage: 160-300 mg of standardized extract once daily, or 1-2 tablespoons of fresh leaves as tea 2-3 times daily. Effects appear after 4-8 weeks. Exercise caution with hypothyroidism, as sage may lower TSH secretion.
Does Red Clover Alleviate Hot Flashes?
The evidence is weaker than the popularity of this supplement suggests. The Cochrane review (Lethaby et al., 2013, 43 studies) found no statistically significant difference in the frequency of hot flashes between red clover extract and placebo.
Red clover (Trifolium pratense) contains isoflavones: daidzein, genistein, formononetin, and biochanin A. These are phytoestrogens, weak agonists of estrogen receptors, mainly ER-beta, with an estimated strength of action about one thousandth of estradiol’s effect. The updated Cochrane review from 2013 (Lethaby et al., DOI 10.1002/14651858.CD001395.pub4, PMID 24323914) combined the results of five studies with Promensil extract and found no significant difference in the frequency of hot flashes compared to placebo. An earlier version of the same review from 2007 reached the same conclusion, and the authors summarized that there is no convincing evidence for the effectiveness of phytoestrogens in alleviating hot flashes and night sweats.
A similar result was obtained in an independent study by Atkinson et al. (Breast Cancer Research, 2004, n=205 women, one-year observation): supplementation with red clover isoflavones did not yield a statistically significant difference in the frequency of hot flashes compared to placebo, partly because the placebo effect in such studies can be very strong. If you decide to use red clover despite the weak evidence, the typical clinically studied dose is 40-80 mg of isoflavones daily, and any effects appear after 4-8 weeks. The controversy surrounding isoflavones and breast cancer is unresolved: epidemiological data from Asia suggest a protective role of high soy consumption from childhood, but that is a different scenario than a supplement in pill form for a woman with a history of hormone-dependent cancer, for whom the decision should be made only with an oncologist. If you are looking for an alternative with a distinct, complex profile of evidence, it is also worth exploring black cohosh.
How Much Vitamin D3 and K2 is Needed During Menopause?
The recommended dose is 2000-4000 IU of vitamin D3 together with 150-200 µg of vitamin K2 MK-7 daily, taken with a fatty meal. The goal is a level of 25(OH)D3 in the range of 50-80 ng/ml, as during menopause, bone mass loss accelerates even 3-5 times in the first 5-10 years after the last menstruation.
Estrogens inhibited the activity of osteoclasts, so their absence accelerates bone resorption. Vitamin D3 is essential for calcium absorption from the intestine: with a deficiency of D3, absorption drops from about 30-40% to 10-15%. Vitamin K2 MK-7 activates osteocalcin, a protein that mineralizes bones, and the MGP protein, which protects blood vessels from calcification. The combination of D3 and K2 works synergistically: D3 delivers calcium to the blood, and K2 directs it to the bones instead of the arteries. More about this mechanism and dosing is discussed in a separate article on vitamin K2 MK-7.
A combined analysis of data from 11 RCT studies included 31022 people over the age of 65 (Bischoff-Ferrari et al., New England Journal of Medicine, 2012). Only the highest actual intake of vitamin D, with a median of about 800 IU daily, was associated with a significant reduction in hip fracture risk by 30% and non-vertebral fracture risk by 14%, regardless of additional calcium supplementation. However, a newer ancillary analysis of the VITAL study (LeBoff et al., NEJM, 2022, n=25871) did not confirm that 2000 IU of D3 daily reduced fracture risk in the general population, even among those with lower levels of 25(OH)D3 at the start. Practical conclusion: D3 supplementation makes sense as a prevention of deficiency, not as a universal remedy for fractures in every woman. Monitor your 25(OH)D3 levels and consider bone densitometry (DXA) every 2 years after menopause.
Do Ashwagandha and Maca Help with Menopause?
Both act adaptogenically, not through phytoestrogens, so they may be a safer choice for those with a history of hormone-dependent cancer. Ashwagandha has good support in studies regarding psychological symptoms and quality of life, while maca has somewhat weaker support, mainly in terms of libido and mood.
Ashwagandha, in standardized extracts such as KSM-66 or Sensoril, lowers cortisol and modulates the hypothalamic-pituitary-adrenal axis. During menopause, cortisol often rises along with the drop in estrogens, which exacerbates anxiety, insomnia, and mood swings. In a study by Gopal et al. (Journal of Obstetrics and Gynaecology Research, 2021, n=100 women in the perimenopausal period, 91 completed the study), ashwagandha extract at a dose of 300 mg twice daily for 8 weeks significantly reduced the menopause rating scale (MRS) score and improved quality of life measured by the MENQoL scale compared to placebo. Dosage: 300-600 mg daily, in the morning or morning and evening, with effects increasing after 4-8 weeks.
Maca (Lepidium meyenii) is a Peruvian adaptogenic plant that modulates the secretion of LH and FSH by affecting the hypothalamus, without involving phytoestrogens. A systematic review by Lee et al. (Maturitas, 2011, 4 RCT studies) indicated a beneficial effect of maca on psychological symptoms of menopause, such as anxiety and low mood, as well as on libido, but the authors noted that the number and quality of available studies are too small to draw certain conclusions. The effect on hot flashes themselves is less pronounced than with sage. Dosage: 1500-3000 mg of standardized extract daily with a meal. More about dosing and combinations of maca with other adaptogens can be found in the article on the properties of maca.
What Helps with Insomnia During Menopause?
About 60% of women in menopause struggle with sleep disturbances caused by night sweats, elevated cortisol, and a natural decline in melatonin. Magnesium glycinate in the evening and, in selected cases, a low dose of melatonin are the two best-tolerated supplements supporting sleep during this period.
Melatonin can be helpful for sleep disturbances related to menopause, especially in women with delayed sleep onset or frequent awakenings. Dosage: 0.3-1 mg 30-60 minutes before sleep. Short-term it is safe, and with use longer than 3 months, it is worth monitoring whether it disrupts the natural circadian rhythm. Magnesium glycinate at a dose of 300-400 mg in the evening supports GABA-ergic mechanisms responsible for falling asleep, reduces nervous hyperactivity, and may alleviate the intensity of night sweats by affecting the autonomic nervous system.
In our observations of menopausal protocols, magnesium is often overlooked as too basic, which is a mistake. Women in menopause have an increased risk of magnesium deficiency for several reasons: increasing osteoblast activity uses more of it, calorie restriction in the diet provides less, and elevated cortisol increases its renal excretion. Magnesium glycinate in the evening is one of the cheapest and best-tolerated supplements, so it is worth starting with it before reaching for more expensive preparations.
Does Omega-3 Help with Menopause?
Partially. Omega-3 EPA and DHA support heart and mood, but have a small, inconsistent effect on hot flashes themselves. Their greatest value lies in cardiovascular protection, as the risk of heart disease increases after menopause with the loss of the protective effect of estrogens on the endothelial cells.
After the loss of estrogens, the lipid profile and inflammatory state of blood vessels often worsen. Omega-3 lowers triglycerides, reduces inflammatory markers CRP and IL-6, and improves endothelial elasticity. In the REDUCE-IT study (Bhatt et al., NEJM, 2019, n=8179), 4 g of icosapent ethyl, a highly purified EPA, daily reduced the risk of cardiovascular events by 25% in patients with elevated triglycerides despite statin treatment. For menopausal women with developing hypertriglyceridemia, this is significant data. The effect of omega-3 on hot flashes alone is ambiguous in studies and usually small, so do not treat it as the main tool for this specific symptom.
A meta-analysis by Hallahan et al. (British Journal of Psychiatry, 2016, 35 RCT studies) showed that forms with a predominance of EPA, above 50% of the composition, alleviated symptoms of depression, while forms with a predominance of DHA did not provide such an effect. Depression and anxiety increase in up to 40% of women in the perimenopausal period, so the choice of omega-3 form has practical significance. Dosage: 2-3 g of EPA and DHA daily with a meal, in triglyceride form, which has better bioavailability than ethyl esters. With doses above 3 g daily, exercise caution when simultaneously using anticoagulants.
How to Build a Supplementation Plan for Menopause?
Start with the basics that every woman in menopause should have: vitamin D3, K2, magnesium, and omega-3. Only on this basis should you select supplements for specific symptoms, such as hot flashes or sleep problems, and add them one at a time, observing the body’s response.
Level one, mandatory for every woman in menopause: vitamin D3 at a dose of 2000-4000 IU together with K2 MK-7 150-200 µg in the morning with a meal, omega-3 EPA and DHA 2-3 g daily with lunch, and magnesium glycinate 300-400 mg in the evening. The cost of such a set is approximately 100-150 PLN per month, depending on the selected products (price status as of 2026-08-10). Justification: protection of bones and heart and improvement of sleep and mood have the strongest evidence here.
Level two, selected for active symptoms: sage in extract 160-300 mg in the morning for hot flashes and night sweats, ashwagandha KSM-66 300-600 mg daily for stress, sleep problems, and libido, possibly maca 1500-2000 mg with a meal for low mood and energy. Isoflavones from red clover can be considered for hot flashes, but remember that the evidence for their effectiveness is weak. Level three, additional support: melatonin 0.3-1 mg in the evening for sleep disturbances, vitamin C 500 mg for immunity and collagen synthesis, and hydrolyzed collagen for skin and joints. Add each new supplement every 7-14 days, and if you have chronic diseases or take medications regularly, consult your choice with a gynecologist.
Do Soy and Tofu Replace Supplements During Menopause?
Partially, and mainly as a dietary element, not a supplement substitute. In East Asia, where the consumption of fermented soy products has been high since childhood, women report milder menopause symptoms and fewer osteoporotic fractures than in Europe, although this is correlation, not causal evidence.
Epidemiological studies indicate a diet rich in soy phytoestrogens, around 40-200 mg of isoflavones daily, as one of the possible protective factors. A modeling analysis by Li et al. (British Journal of Clinical Pharmacology, 2015, 16 studies, about 1710 participants) showed that soy isoflavones reduced the frequency of hot flashes by a maximum of about 25% after subtracting the placebo effect, but needed more than 13 weeks to achieve half of that effect, significantly longer than estrogens. The effect is therefore real, but slower and weaker than with HRT or sage, so soy should be treated as an element of the daily diet, for example in the form of tofu, edamame, or tempeh, and not as a fast-acting supplement.
Fermentation, as in natto, miso, or tempeh, improves the bioavailability of isoflavones by converting glucosides to aglycones, i.e., daidzein and genistein. Equol, a metabolite of daidzein produced by some gut bacteria, has a stronger estrogenic effect than daidzein itself, but only about 30-40% of the Western population are so-called equol producers, compared to 50-60% of the Asian population. This explains why the effects of soy isoflavones are so variable among women.
What Improves Skin and Joints During Menopause?
Estrogens stimulate collagen production, so their decline accelerates skin aging and weakens joints. Vitamin C as a cofactor in collagen synthesis and hydrolyzed collagen at a dose of 2.5-10 g daily have the best support in clinical studies in this area.
A randomized study by Maheux et al. (1994) showed the scale of this impact from another perspective: one-year estrogen therapy significantly increased skin and dermis thickness in postmenopausal women compared to placebo, confirming how strongly estrogens affect skin collagen. Vitamin C is a cofactor for proline and lysine hydroxylases, essential enzymes for collagen synthesis, and as an antioxidant, it protects against oxidative stress exacerbated by inflammation after menopause. A review by Pullar et al. (Nutrients, 2017) links higher vitamin C intake with better skin elasticity in observational studies. Dosage: 500-1000 mg daily, in the morning or with a meal, well tolerated up to 2 g daily.
Hydrolyzed collagen types I and III have growing evidence for improving skin elasticity and hydration. In a study by Proksch et al. (Skin Pharmacology and Physiology, 2014, n=69 women aged 35-55), 2.5 g of hydrolyzed collagen daily for 8 weeks significantly improved skin elasticity compared to placebo. For joints, type II collagen, UC-II, at a dose of 40 mg daily, or hydrolyzed types I and III at a dose of 10 g daily, may alleviate joint pain, a common symptom of menopause associated with the loss of the anti-inflammatory action of estrogens.
Frequently Asked Questions
Below are answers to the most frequently asked questions regarding supplements for menopause.
What supplements best alleviate hot flashes?
The best-studied is sage: 160-300 mg of extract daily reduced the severity of hot flashes by 64%, and their daily number by 59% (Bommer et al., 2011). Isoflavones from red clover are popular, but a Cochrane review from 2013 (Lethaby et al.) did not show a significant advantage over placebo. The effects of sage increase after 4-8 weeks; do not combine it with antithyroid medications without consultation.
Can supplements replace hormone replacement therapy?
Not fully. HRT remains the most effective method for treating hot flashes, with a reduction of 80-90% (Stuenkel et al., 2015). Supplements work weaker, but can be a sensible option for women who do not want or cannot use HRT, for example after breast cancer. Always make the decision about HRT together with your gynecologist.
What is the recommended dose of vitamin D3 during menopause?
Recommended dose: 2000-4000 IU of D3 with 150-200 µg of K2 MK-7 daily, with a fatty meal, target 25(OH)D3 50-80 ng/ml. D3 supports bones weakened after menopause, although the VITAL study did not confirm that D3 alone reduces fracture risk without confirmed deficiency. Check D3 levels every 6 months.
Does magnesium help with menopause symptoms?
Magnesium supports bone health, reduces anxiety, and improves sleep, which are problems particularly exacerbated during menopause. Magnesium glycinate at a dose of 300-400 mg in the evening is one of the cheapest and best-tolerated supplements during this period. Women in menopause have an increased risk of magnesium deficiency, among other reasons due to increased osteoblast activity and higher renal excretion.
Does maca help with menopause?
A systematic review by Lee et al. (Maturitas, 2011, 4 RCT studies) indicated a beneficial effect of maca on anxiety, low mood, and libido, although the authors noted that there is too little evidence for certain conclusions. The effect on hot flashes themselves is weaker than with sage. Maca does not contain phytoestrogens, so it may be safer than isoflavones in women with a history of hormone-dependent cancer. Dose: 1500-3000 mg daily.
Does omega-3 help with menopause?
Omega-3 EPA and DHA have anti-inflammatory effects, lower CRP and IL-6, and protect the heart, the risk of which increases after menopause. Forms with a predominance of EPA may improve mood (Hallahan et al., 2016). The effect on hot flashes is small and inconsistent, so treat omega-3 mainly as support for heart and mood. Dose: 2-3 g daily.
For supplements from this article, such as vitamin D3, K2, magnesium, or ashwagandha, check the supplements category in the u Bucha store.
This article is for informational and educational purposes and does not constitute medical advice. Before starting supplementation, consult your doctor, especially if you are taking medications regularly, are pregnant or breastfeeding, or have chronic illnesses.
Author: Michał Waluk · Published: 2026-06-02 · Updated: 2026-08-10