
Immune Supplements for Children: Which Are Safe and When Is It Really Worth Giving
Which immune supplements for children have studies, and which do not. Vitamin D, C, zinc, probiotics, elderberry, and echinacea in light of pediatric data.
A preschooler can go through infection after infection from October to March, and the pharmacy shelf suggests that it can be bought. The problem is that a significant portion of “immune” preparations for children is based on studies conducted on adults, and the doses are calculated from a person weighing seventy kilograms. This text separates two things: what has actually been tested on children and on how many of them, and what is sold on faith. We read Cochrane reviews covering ingredients from the pharmacy’s first shelf, current Polish guidelines for vitamin D dosing, and descriptions of poisonings in small children. You will see how many infections per year fit within the developmental norm, when recurrent infections are a signal for immunological diagnostics, and why excess vitamin can be more dangerous for a child than its deficiency.
KEY INFORMATION
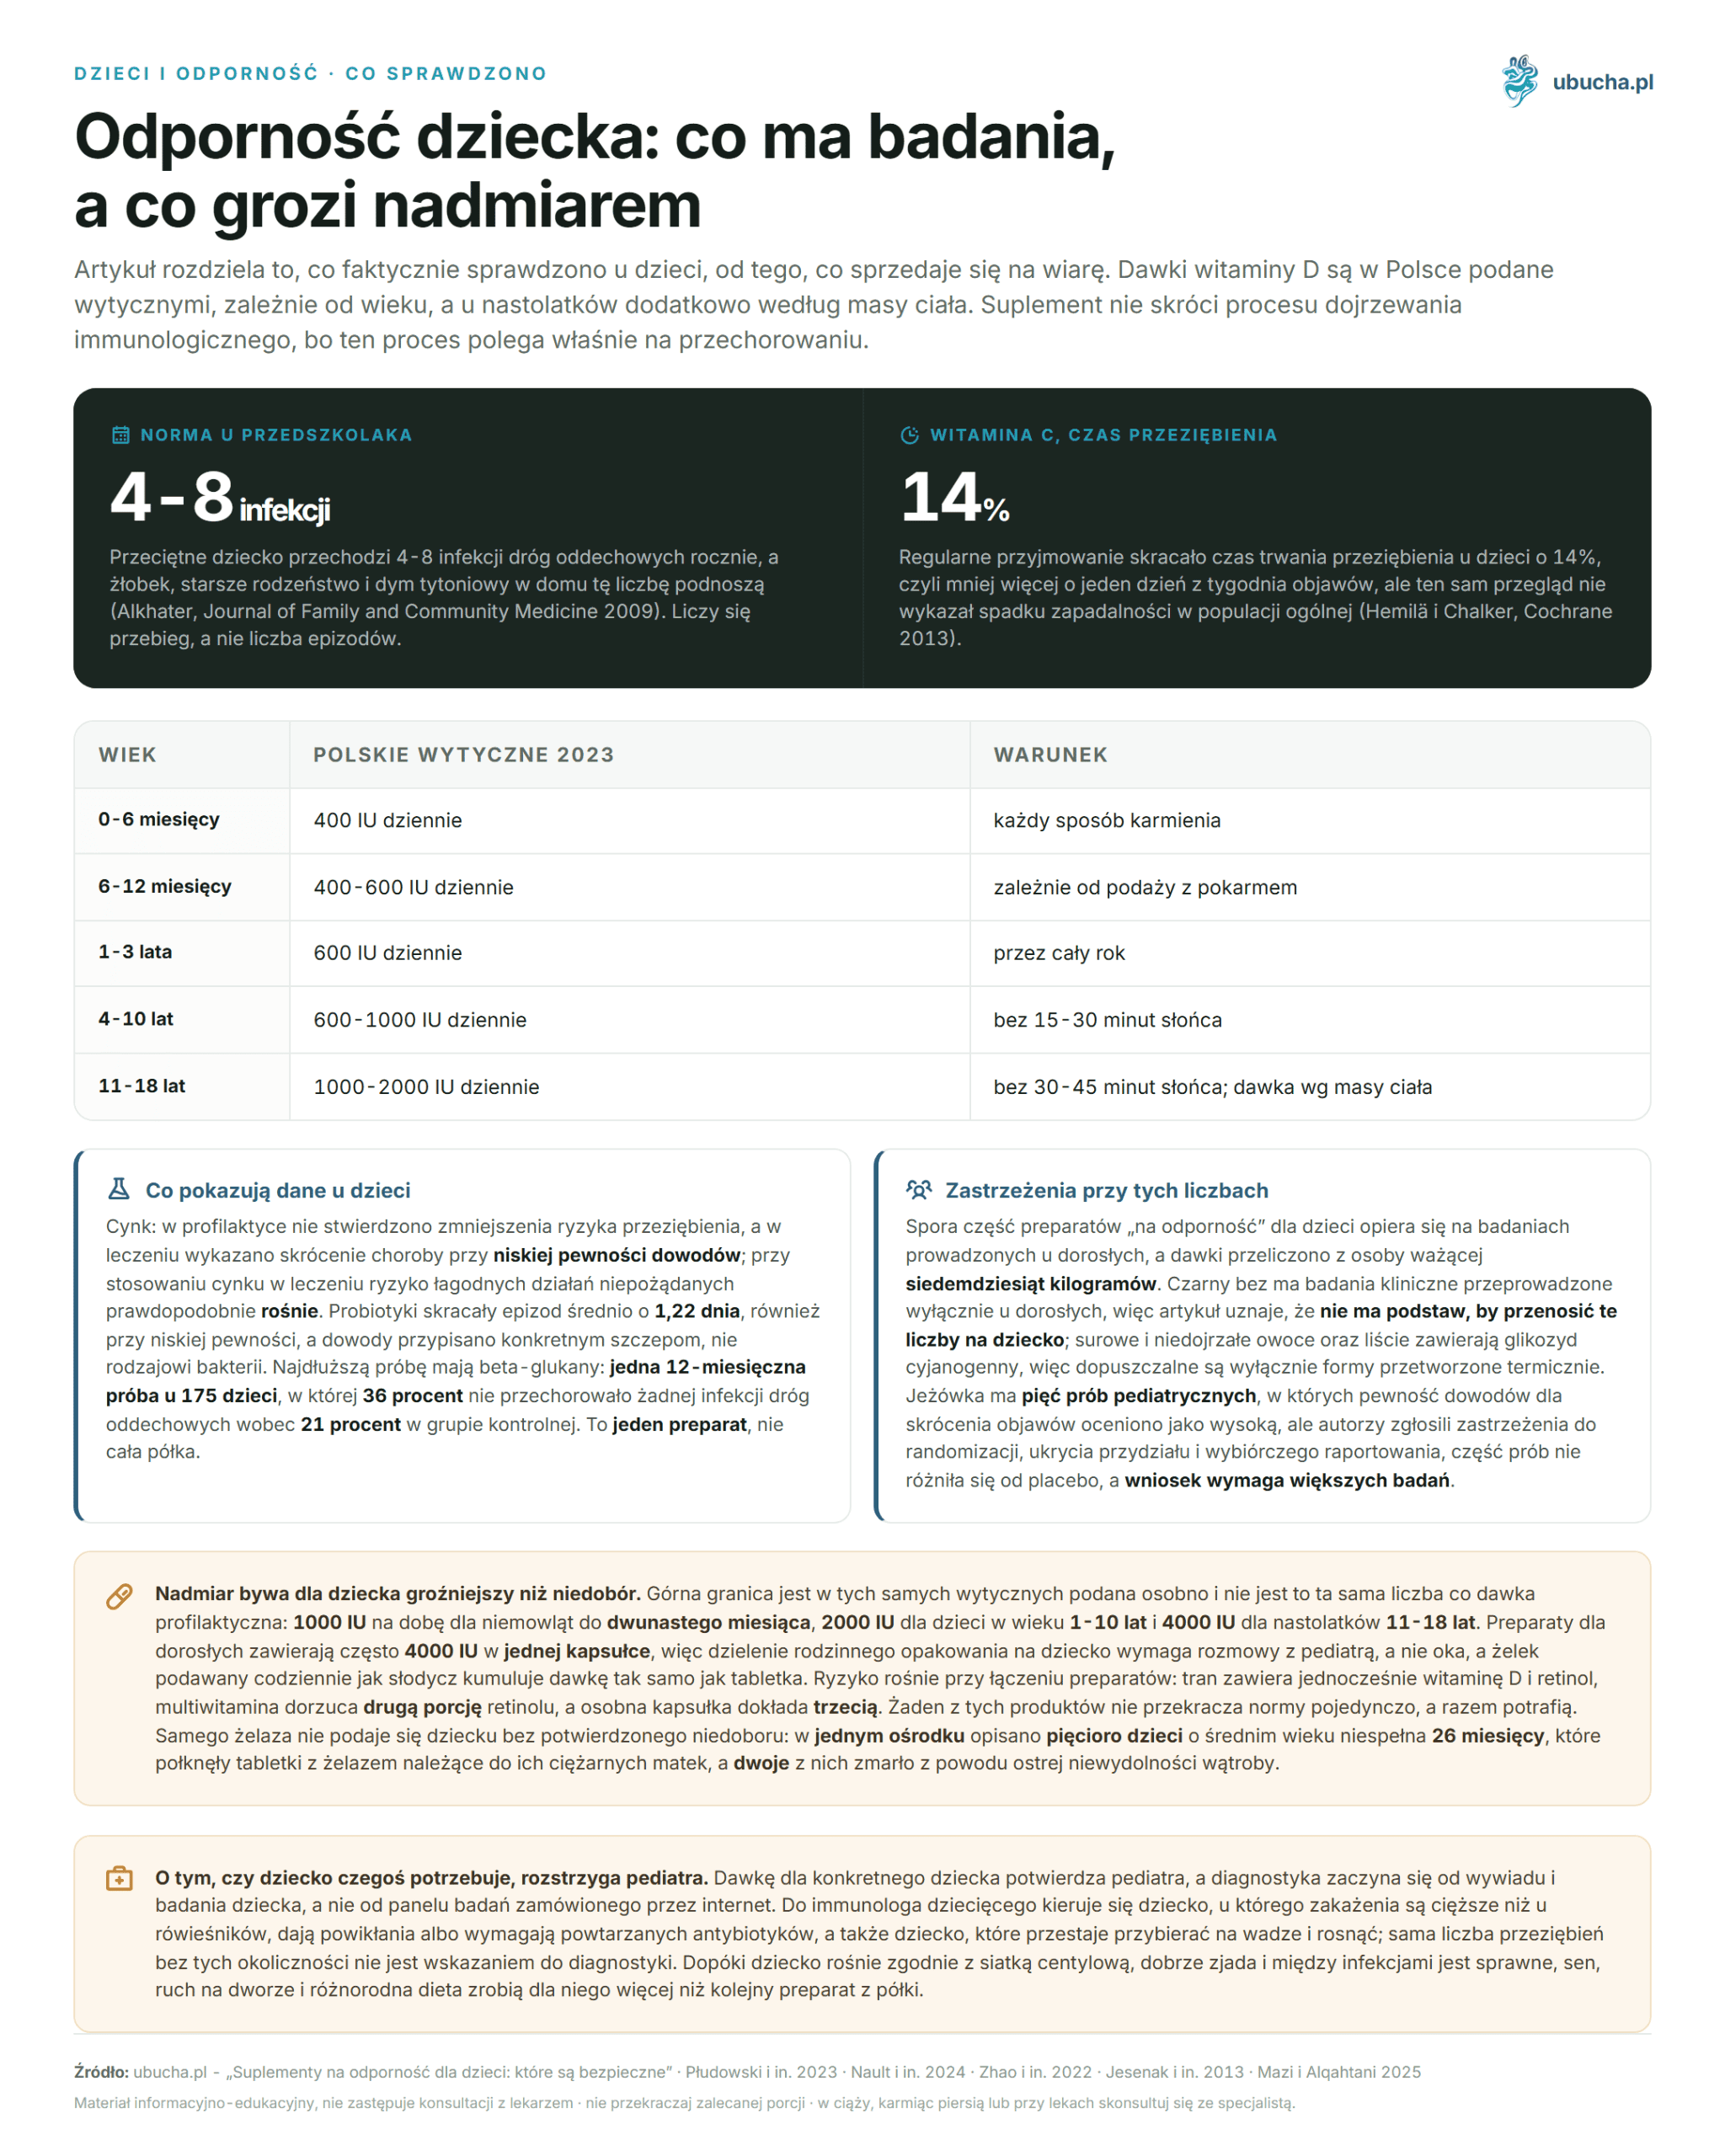
• The average child experiences 4-8 respiratory infections per year, and daycare increases this number (Alkhater, Journal of Family and Community Medicine 2009).
• Vitamin C shortens colds in children by 14%, but does not reduce incidence (Hemilä and Chalker, Cochrane 2013).
• Probiotic evidence is attributed to specific strains, not the type of bacteria.
• Excess retinol, vitamin D, and iron pose real threats to small children, not just theory.
How many infections per year is normal for a preschooler?
The average child experiences four to eight respiratory infections per year, and daycare, older siblings, and tobacco smoke at home increase this number (Alkhater, Journal of Family and Community Medicine 2009). A child with normal immunity grows normally, responds to standard treatment, and looks healthy between infections.
This distinction does more good for the parent than any preparation. A runny nose every three weeks from November to March looks like a series, but spread over twelve months fits within the same range cited by pediatric literature. The first year in a peer group is usually the worst, as the child encounters dozens of viruses they have not seen before. Each of these infections leaves behind an immunological memory, so the second season in the same group usually looks different.
We have noticed in conversations with parents that the pressure to “boost immunity” increases not when the child is sicker, but when they are sick more often than a neighbor’s child who does not attend preschool. This comparison makes no sense, as exposure makes the difference, not the efficiency of the immune system. A supplement will not shorten the process of immunological maturation, as this process is precisely about getting sick.
The conditions under which it is worth stopping counting infections and starting diagnostics are described later in the text. Until then, accept a simple rule: the course matters, not the number of episodes.
How much vitamin D should a child receive in Poland?
Here, an official norm applies, not a parent’s decision. The guidelines from Płudowski and colleagues from 2023 state 400 IU daily for infants up to six months, regardless of feeding method, and 600 IU year-round for children from the first to the third year of life, as there are restrictions on sun exposure at this age (Płudowski et al., Nutrients 2023).
| Age | Polish Guidelines 2023 | Condition |
|---|---|---|
| 0-6 months | 400 IU daily | from the first days of life, any feeding method |
| 6-12 months | 400-600 IU daily | depending on dietary intake |
| 1-3 years | 600 IU daily | year-round |
| 4-10 years | 600-1000 IU daily | when there is no 15-30 minutes of sun on exposed forearms and legs, between 10 and 15, without sunscreen, from May to the end of September |
| 11-18 years | 1000-2000 IU daily | as above, but guidelines require 30-45 minutes; dose according to body weight |
The scale of deficiency in the Polish population is real and strongly seasonal. In a multicenter study of 720 healthy children aged 9-13 years, the concentration of 25(OH)D was measured twice: after winter in March and after summer in October. In March, deficiency was found in 64 percent of participants, and severe deficiency in another 20.2 percent, meaning over four-fifths of children. In October, these figures were 25.9 and 0.1 percent respectively (Chlebna-Sokół et al., European Journal of Nutrition 2019). The authors conclude that supplementation should occur year-round, not just in winter.
The upper limit is given separately in the same guidelines and is not the same number as the preventive dose. The table of tolerable upper intake of cholecalciferol states 1000 IU per day for infants up to twelve months, 2000 IU for children aged 1-10 years, and 4000 IU for teenagers aged 11-18 years (Płudowski et al., Nutrients 2023, table 2). Adult preparations often contain 4000 IU in one capsule, so dividing a family package for a child requires a conversation with a pediatrician, not just a glance.
Does vitamin C shorten a child’s cold?
It shortens it, but less than the label promises, and does not prevent illness. A Cochrane review from 2013, involving over 11,000 participants, found no reduction in cold incidence in the general population. Regular intake, however, shortened the duration of colds in children by 14 percent, compared to 8 percent in adults (Hemilä and Chalker, Cochrane Database of Systematic Reviews 2013).
It is worth translating that 14 percent into days. If a cold lasts for a child for seven days, a 14 percent reduction means about one day less. This is an honest and real result, just not corresponding to the promise of “the child will stop getting sick” suggested by the packaging. The effect applied to regular intake throughout the season, not just taking the preparation on the first day of a runny nose. In therapeutic studies, which started after symptoms appeared, there was no consistent effect.
Another matter is the dose. The Cochrane review included trials using at least 0.2 grams daily, and some studies in children reached 1-2 grams. This is multiple times the amount a child gets from food, and it is not a recommendation to replicate at home. A child’s need for vitamin C is covered by a diet with fruits and vegetables, and the amount of the supplement, if it is to be given at all, is determined by a pediatrician. Excess vitamin C does not accumulate like fat-soluble vitamins, but in larger amounts can cause diarrhea and stomach pain.
Does zinc help a child with a cold?
Data in children are weak and partly directly negative. A Cochrane review from 2024 included 34 studies and 8526 participants, including 12 studies in children. No reduction in cold risk was found in prevention, and treatment showed a shortening of illness with low certainty of evidence and great heterogeneity of results (Nault et al., Cochrane Database of Systematic Reviews 2024). The same review notes on the cost side that using zinc in treatment likely increases the risk of mild adverse effects.
The most telling is a pediatric study from 1998. Macknin and colleagues gave 249 students zinc gluconate lozenges five or six times a day. The time to symptom resolution was nine days in both groups, and there was no difference for any of the nine assessed symptoms. An unpleasant taste was reported by 60 percent of children taking zinc compared to 38 percent in the placebo group (Macknin et al., JAMA 1998). A lozenge requires dissolving in the mouth for several minutes, which a small child will not do, and in infants, this poses an additional choking risk.
There is one situation where zinc in children has stronger foundations. A Cochrane review from 2016 included six studies and 5193 children aged 2 to 59 months, and the incidence of pneumonia was lower in the zinc groups by 13 percent (Lassi et al., Cochrane Database of Systematic Reviews 2016). It is worth reading this result more closely: the effect reached 21 percent where the diagnosis was confirmed by chest examination or X-ray, and with a definition based solely on accelerated breathing, it disappeared. The quality of evidence was rated as low. Transferring this to a well-fed Polish preschooler eating meat and dairy is an abuse, as the studies were conducted where zinc deficiency is a population phenomenon. Supplementation without confirmed deficiency is not justified here, and excess zinc impairs copper absorption.
Which probiotic has evidence in children?
Evidence is attributed to specific strains, not the type of bacteria. A Cochrane review from 2022 included 23 studies and 6950 participants, including children from the first month of life. Probiotics reduced the percentage of participants with at least one upper respiratory infection and shortened episodes by an average of 1.22 days, with low certainty of evidence (Zhao et al., Cochrane 2022).
The best-documented strain in pediatrics is Lactobacillus rhamnosus GG. In a study by Hojsak and colleagues, 281 children from daycare centers received this strain or placebo for three months. The risk of upper respiratory infections decreased by one-third, and the number of days with symptoms was significantly lower. The effect on gastrointestinal infections was not confirmed, as the result did not reach statistical significance (Clinical Nutrition 2010).
In treating acute diarrhea, the picture is more nuanced. A meta-analysis by Szajewska and colleagues from 2019 included 18 studies and 4208 children; the same strain shortened diarrhea by an average of 0.85 days, but a large study published a year earlier found no effect, and the benefit was mainly seen in European countries (Alimentary Pharmacology and Therapeutics 2019). This is not a Cochrane review, although it is sometimes signed as such.
The practical conclusion for a parent is one: the packaging must have the full strain designation along with the alphanumeric symbol, as the name of the type alone says nothing about testing. More about the differences between strains is discussed in our post about choosing a probiotic for gut health and immunity.
Do elderberry and echinacea work in children?
In the case of elderberry, clinical studies have been conducted on adults. A trial involving 312 long-haul flight passengers showed a shorter total duration of colds and milder symptoms, but the difference in the number of illnesses was not significant (Tiralongo et al., Nutrients 2016). An earlier trial during flu involved 60 people aged 18-54 years who were given syrup four times a day for five days; symptoms resolved on average four days earlier than with placebo (Zakay-Rones et al., Journal of International Medical Research 2004).
There are therefore no grounds to transfer these numbers to a child. The raw material also has its own limitation: raw and unripe fruits and leaves contain cyanogenic glycosides, so only thermally processed forms are permissible. A comparison of the raw materials themselves is discussed in our post about aronia and elderberry.
Echinacea has a systematic review of pediatric studies from 2025. Five trials met the inclusion criteria, and the authors reported concerns about randomization, allocation concealment, and selective reporting. Nevertheless, they rated the certainty of evidence as high for shortening symptoms and reducing antibiotic use, and moderate for preventing infections (Mazi and Alqahtani, Journal of Family and Community Medicine 2025). They themselves note, however, that effectiveness depended on the form and dose, some trials did not differ from placebo, and the conclusion requires larger studies.
Which ingredients have studies conducted on children?
Most of the ingredients discussed here have some trial conducted on children, not just adults; the exception is elderberry. The difference between them lies elsewhere: in how many of these trials exist, how long they lasted, and whether the result concerned the number of illnesses or just the duration of symptoms. A summary can be found in the table below.
The least known on the Polish shelf are beta-glucans, and they have the longest trial here. One hundred seventy-five children around six years old, with more than five respiratory infections in the previous year, received syrup with pleuran, a beta-glucan from the oyster mushroom, or a comparative preparation for twelve months. In the beta-glucan group, 36 percent of children did not experience a single respiratory infection during this time, compared to 21 percent in the control group (Jesenak et al., International Immunopharmacology 2013). It is worth noting the detail of the design: both groups received vitamin C, the difference was the beta-glucan itself. This is a single study of one preparation, not evidence for the entire shelf.
| Ingredient | What data show in children | Basis |
|---|---|---|
| Vitamin D | prevention of deficiency, doses specified by guidelines | official norm |
| Vitamin C | cold duration shorter by 14%, incidence unchanged | Cochrane review |
| Zinc | no effect in prevention, uncertain result in treatment | low certainty |
| Probiotics | fewer episodes, shorter course, effect dependent on strain | low certainty |
| Elderberry | studies only in adults | intermediate data |
| Echinacea | five pediatric trials, shorter symptoms and fewer antibiotics | methodological concerns |
| Beta-glucans | one 12-month trial in 175 children, 36% without infections vs 21% | one preparation |
What are the risks of vitamin overdose in children?
Fat-soluble vitamins accumulate, so exceeding the norm is not just a theory in children. EFSA in its 2024 opinion maintained the upper limit for retinol at 3000 micrograms of retinol equivalent daily for adults and calculated it for younger groups, obtaining values from 600 micrograms for infants to 2600 micrograms for teenagers (EFSA Journal 2024). The critical effect on which this limit was based was teratogenicity, and hepatotoxicity was also assessed.
The risk increases when combining preparations. Cod liver oil contains both vitamin D and retinol, a multivitamin adds a second portion of retinol, and a separate capsule with vitamin D adds a third. None of these products exceed the norm individually, but together they can. The same logic applies to vitamin D, for which Polish guidelines state an upper limit of 2000 IU daily for children aged 1-10 years.
A separate trap is the form of the preparation. In the journal Pediatric Emergency Care, a case was described of a twenty-month-old girl admitted with loss of appetite, increasing weakness, and drowsiness, who was found to have severe hypercalcemia and vitamin D overdose. The source was calcium and vitamin D3 gummies given to her by her mother several times a day for weeks, even months; the child required intensive therapy, and hypercalcemia initially did not resolve with standard treatment (Doyle et al., Pediatric Emergency Care 2021). The authors describe this as a case of neglect in a family with a mother suffering from mental illness, so it is not a typical household accident. The practical conclusion for parents is, however: a gummy given daily like candy accumulates the dose just like a tablet. The differences between preparations in this form are described in our post about vitamin gummies.
The sharpest example concerns iron. In one center, five children with an average age of just under 26 months swallowed iron tablets belonging to their pregnant mothers; two of them died from acute liver failure (Chandran et al., Journal of Family Medicine and Primary Care 2023). The authors conclude with a direct appeal for primary care physicians to talk to parents about the safe storage of iron preparations. Iron itself should not be given to a child without confirmed deficiency.
When do recurrent infections require diagnostics?
It is not the number of colds that decides, but their course. A child whose infections are more severe than those of peers, cause complications, or require repeated antibiotics is referred to a pediatric immunologist, as is a child who stops gaining weight and growing. The author of the cited study emphasizes that a child with functioning immunity develops normally (Alkhater 2009).
There are also less obvious situations. An infection caused by a microorganism that usually does not cause disease in a healthy child, an organ abscess, chronic oral thrush after infancy, and a family history of primary immunodeficiency are concerning. Primary immunodeficiencies occur according to the cited study in as many as 1 in 2000 live births, so they are not rare enough to dismiss outright.
More often than immune deficiency, something simpler stands behind a series of infections: allergy, enlarged adenoid, reflux, tobacco smoke in the home, or simply the first year in a group. Diagnostics starts with an interview and examination of the child, not with a panel of tests ordered online. Results of immunological tests in a small child without clinical context can be misleading, as norms change with age.
As long as the child is growing according to the centile chart, eating well, and is active between infections, sleep, outdoor activity, and a varied diet will do more for them than another preparation from the shelf. This is a boring answer, but it is backed by better data than most things sold under the banner of immunity.
Frequently Asked Questions
How many infections per year is normal for a preschooler?
The average child experiences four to eight respiratory infections per year, and daycare, older siblings, and tobacco smoke at home increase this number (Alkhater 2009). A child with normal immunity grows normally, responds to standard treatment, and looks healthy between infections. The mere count of illnesses is not a cause for concern.
Does vitamin C prevent colds in children?
No. A Cochrane review from 2013, involving over 11,000 participants, found no reduction in incidence in the general population. Regular intake, however, shortened the duration of colds in children by 14 percent, or about one day from a week of symptoms. This is a real but modest effect.
How much vitamin D should a child receive according to Polish guidelines?
The 2023 guidelines state 400 IU daily for infants up to six months, 400-600 IU up to one year, 600 IU year-round for children aged 1-3 years, 600-1000 IU for children aged 4-10 years, and 1000-2000 IU for teenagers when sunlight exposure is insufficient. The dose for a specific child is confirmed by a pediatrician.
Is zinc in lozenges suitable for children?
Rather not. In a study published in JAMA in 1998, involving 249 students, lozenges with zinc gluconate did not shorten colds compared to placebo, and an unpleasant taste was reported by 60 percent of children compared to 38 percent in the placebo group. In the youngest, there is a risk of choking on the lozenge.
Do all probiotics work the same?
No. Evidence is attributed to specific strains, not the type of bacteria. A Cochrane review from 2022 included 23 studies and 6950 participants, including children from the first month of life, with low certainty of evidence. Look for the full strain designation with an alphanumeric symbol on the label.
When should you take your child to an immunologist?
When infections are more severe than in peers, cause complications, require repeated antibiotics or hospitalization, when the child stops gaining weight and growing, or when infections are caused by atypical microorganisms. The mere number of colds without these circumstances is not an indication for diagnostics.
If after talking to the pediatrician it turns out that the child actually needs something, you can browse the assortment in the supplements category. A broader overview of the topic can also be found in the post about what is safe in children’s supplementation.
This article is for informational and educational purposes and does not constitute medical advice. Before starting supplementation, consult a doctor, especially if you are taking medications regularly, are pregnant or breastfeeding, or have a chronic illness.
Author: Michał Waluk · Published: 2026-06-02 · Updated: 2026-08-14