ADHD Naturally: Supplements and Herbs for Concentration
What research really says about omega-3, magnesium, iron, zinc, bacopa, ginkgo, and CBD in ADHD. We check which evidence is strong and which is inflated by advertising.
A meta-analysis of 102 studies including 171,756 people estimated the global prevalence of ADHD in children and adolescents up to 18 years old at 5.29% (Polanczyk, The American Journal of Psychiatry, 2007). Psychiatrist waiting lists are long, so parents and adult patients seek support available without prescription, and the supplement market responds with a list of products promising focus. This article checks these promises one by one, directly in the abstracts of studies cited by manufacturers, providing the reference number for independent verification. You will see where evidence truly exists, where the study says something different than the label, where it concerned completely different patients, and why none of the described products replace psychiatric care. You will also learn how to independently verify another product you hear about.
KEY INFORMATION
• Global prevalence of ADHD in persons up to 18 years is 5.29% (Polanczyk, The American Journal of Psychiatry, 2007).
• A meta-analysis of 133 studies places methylphenidate first in children (Cortese, The Lancet Psychiatry, 2018).
• Omega-3s show a small but significant effect (Bloch and Qawasmi, 2011).
• Zinc improved hyperactivity but not attention deficit (Bilici, 2004).
• A review of 16 studies found ginkgo ineffective (Sarris, 2011).
What is ADHD and why is it managed by a psychiatrist?
ADHD is a neurodevelopmental disorder diagnosed based on DSM-5 and ICD-11 criteria, not on an internet test or observation by a single adult. Symptoms of inattention, hyperactivity, or impulsivity must be present before age 12, occur in at least two settings, and significantly impair functioning. Diagnosis is made by a doctor.
The scale of the phenomenon is well measured. Polanczyk et al. reviewed 9,105 records, included 102 studies with 171,756 participants worldwide, and calculated a pooled prevalence of 5.29% in persons up to 18 years (The American Journal of Psychiatry, 2007). They also showed that variation between countries is explained by study methodology, not geography. A newer analysis by the same team found no evidence that the number of children meeting criteria increased over three decades when using a standardized diagnostic procedure.
Biology underlies the symptoms, visible in imaging. A large comparative analysis showed differences in subcortical brain volumes in people with ADHD versus those without diagnosis (Hoogman, The Lancet Psychiatry, 2017). This is important for evaluating supplements: a product that supplements a deficiency or modulates neurotransmitter function acts on a different level than the disorder’s mechanism itself. Therefore, the first step after noticing symptoms is a visit to a specialist, not shopping.
Is ADHD really increasing?
Data do not confirm this. The same team that calculated global prevalence returned seven years later to check if rising diagnoses and prescriptions mean a real increase. They updated the two largest systematic reviews and performed meta-regression by study year (Polanczyk, International Journal of Epidemiology, 2014).
They identified 154 original studies, 135 included in a multivariable model. The result was twofold. First, methodological procedures - diagnostic criteria, requirement of functional impairment, and source of symptom information - were significantly associated with heterogeneity. Second, neither geographic location nor study year was associated with prevalence variation.
The authors conclude that over three decades there is no evidence of an increase in children meeting ADHD criteria in the population when using standardized diagnostic procedures. This should be understood precisely, as it is often misinterpreted. It does not say diagnoses are not increasing - they are. It says the increase in diagnoses does not mean an increase in the disorder, but better detection and diagnostic practice changes. For a parent told ADHD is a fad, this is the best data-based answer. For someone seeking non-prescription support, it means that self-diagnosis based on an internet questionnaire is exactly the kind of procedure that inflates results. Diagnosis without interview, assessment in two settings, and exclusion of other causes is not a diagnosis.
Does ashwagandha help in ADHD?
There is no study that tested this. Ashwagandha, or Withania somnifera, has not been studied in ADHD in children or adults, so any answer is reasoning by analogy, not result. This is important because every other item in this article has a referenced study with participant numbers and duration.
What has been studied concerns a different population and endpoint: stress and anxiety in adults without ADHD, in trials usually lasting six to twelve weeks. Applying this to attention deficit is a leap not supported by data, as anxiety and inattention are not the same symptoms, even if co-occurring.
The practical conclusion is cautious. If ashwagandha helps, it is at best indirectly by reducing tension, not by improving concentration per se. Also remember it is a substance with documented cases of liver damage, so it is not a harmless additive.
Can a supplement replace ADHD treatment?
No, and the difference in evidence strength is huge. A network meta-analysis by Cortese et al. included 133 double-blind randomized studies, with efficacy analysis near 12 weeks based on 10,068 children and adolescents and 8,131 adults (The Lancet Psychiatry, 2018). All studied drugs outperformed placebo.
The table below shows standardized mean differences for core symptoms assessed by clinicians in children and adolescents. Negative values indicate drug superiority over placebo; the larger the absolute value, the stronger the effect.
| Substance | SMD vs placebo | 95% confidence interval |
|---|---|---|
| Amphetamines | -1.02 | -1.19 to -0.85 |
| Methylphenidate | -0.78 | -0.93 to -0.62 |
| Atomoxetine | -0.56 | -0.66 to -0.45 |
The authors conclude clearly: considering efficacy and tolerability, methylphenidate is first-line in children and adolescents, amphetamines in adults. Amphetamines were less tolerated than placebo in both age groups, showing drug choice is a doctor’s job, not a list selection. Supplements do not appear in this comparison as they have not undergone studies of this class.
The separate question of cannabidiol in ADHD is discussed in the text on CBD and ADHD, and herbs supporting concentration are collected in the supplements category.
How does treatment differ between adults and children?
It differs in drug efficacy, tolerability, and especially who assesses improvement. The same meta-analysis of 133 studies broke down results by age group and assessor source, revealing how fragile statements like “stimulants just work” can be (Cortese, The Lancet Psychiatry, 2018).
In adults, clinician-rated, amphetamines outperformed placebo with -0.79 (95% CI -0.99 to -0.58), methylphenidate -0.49 (-0.64 to -0.35), bupropion -0.46 (-0.85 to -0.07), and atomoxetine -0.45 (-0.58 to -0.32). Modafinil was not better than placebo. In children and adolescents, all studied drugs outperformed placebo by clinician rating, but by teacher rating only methylphenidate and modafinil retained superiority.
Tolerability, measured by dropout due to adverse events, showed amphetamines worse than placebo in both age groups, guanfacine worse in children and adolescents, and atomoxetine, methylphenidate, and modafinil worse only in adults. The authors noted a limitation: data sufficed for analysis near 12 weeks, but not for 26 or 52 weeks. This knowledge describes short-term treatment. The same limitation applies to supplement studies, but even more so.
What did the omega-3 meta-analysis show in ADHD?
Omega-3 fatty acids have the strongest evidence base among supplements, but the effect is modest. Bloch and Qawasmi collected ten randomized placebo-controlled studies including 699 children, showing a small but statistically significant impact on ADHD symptoms (Journal of the American Academy of Child and Adolescent Psychiatry, 2011).
The most interesting result was a secondary analysis. Eicosapentaenoic acid content correlated significantly with efficacy, meaning the fatty acid proportions matter and not every fish oil is the same product. The authors found no signs of publication bias or heterogeneity, strengthening the result’s credibility.
The authors soberly called omega-3 efficacy modest compared to available pharmacotherapy - psychostimulants, atomoxetine, and alpha-2 receptor agonists. They considered supplementation reasonable for confirmed deficiencies or families refusing other psychopharmacological options. This cautious statement should be read literally: supplementation, not replacement. The attending doctor decides on the specific product and whether it is needed, especially if the patient is on regular medication.
Does magnesium alleviate ADHD symptoms?
Data are encouraging but come from small older studies, and the effect depended on continued supplementation. Kozielec and Starobrat-Hermelin studied 116 children aged 9 to 12 with ADHD and found magnesium deficiency in 95% (Magnesium Research, 1997).
They measured magnesium by three methods with differing results: deficiency was most often detected in hair (77.6%), less in red blood cells (58.6%), and least in serum (33.6%). This is practical advice for parents receiving lab results. A normal serum value alone does not close the case.
A second French study observed 40 children with ADHD symptoms for at least eight weeks taking magnesium with vitamin B6 (Magnesium Research, 2006). Hyperactivity, excessive emotionality, and aggression decreased, and school attention improved alongside rising red blood cell magnesium. The authors noted explicitly that symptoms returned within weeks after stopping supplementation, and magnesium levels dropped again. This argues for medical supervision, not self-purchasing.
How is iron deficiency linked to ADHD?
The link is documented and measurable but concerns children with actual deficiency, not all. Konofal et al. compared 53 children with ADHD aged 4 to 14 to 27 controls. Mean serum ferritin was 23 ng/ml versus 44 ng/ml (Archives of Pediatrics and Adolescent Medicine, 2004).
Ferritin below 30 ng/ml occurred in 84% of ADHD children and 18% of controls. Lower ferritin correlated with more severe symptoms on the Conners parent scale and greater cognitive deficits. The authors concluded low iron stores contribute to the disorder’s picture. More on the mechanism is in the post about how iron deficiency harms child learning.
Four years later, the same team tested supplementation. They included 23 children without anemia but ferritin below 30 ng/ml, assigned to iron or placebo for twelve weeks (Pediatric Neurology, 2008). ADHD Rating Scale scores dropped by 11.0 points on average in the iron group, with no change on placebo. Improvements on Conners parent and teacher scales were not significant. The study was small, and authors called for larger trials. The practical conclusion is clear: first blood count and ferritin ordered by a doctor, then possible supplementation.
Does zinc improve concentration in children with ADHD?
No, and this is the most often misrepresented result in this area. Bilici et al. conducted a double-blind placebo-controlled study on 400 patients diagnosed with ADHD per DSM-IV, lasting twelve weeks (Progress in Neuro-Psychopharmacology and Biological Psychiatry, 2004). Zinc sulfate outperformed placebo but not in every symptom dimension.
Improvement was seen in hyperactivity, impulsivity, and disturbed social relations. Attention deficit was not reduced. For an article on supporting concentration, this is decisive, as this symptom is most often promised in ads. Full therapeutic response was 28.7% in the zinc group versus 20% on placebo, so a difference exists but is small.
The authors noted the effect was stronger in older patients, with higher BMI, and low baseline zinc and free fatty acids. This again points to blood testing before supplementation, not after. Zinc was well tolerated, with rare adverse events. The study lasted twelve weeks and says nothing about longer use, so duration is a doctor’s decision. An independent review of sixteen studies on herbal and nutritional products listed zinc and iron among substances with best evidence in ADHD (Sarris, Complementary Therapies in Medicine, 2011).
What did the bacopa monnieri study really show?
It showed improvement in a narrow slice of working memory in healthy adults, not ADHD treatment. Stough et al. recruited 107 healthy volunteers for a double-blind placebo-controlled study. Sixty-two completed it with 80% protocol compliance; neuropsychological testing was done at baseline and after 90 days (Phytotherapy Research, 2008).
The product improved a factor called working memory, specifically spatial working memory accuracy. It also reduced false alarms in a rapid visual information processing test. That is what the abstract says. There was no improvement in attention or general processing speed, no ADHD patients, and no children. The authors wrote that further work is needed on effective doses and time to effect.
Sarris’s review placed bacopa monnieri among promising future research directions in ADHD, alongside kava pepper, not among substances with confirmed efficacy. The difference between promise and proof is entire here. If you are interested in the plant outside ADHD context, we described it in a separate text on bacopa monnieri properties for memory and concentration. Whether bacopa makes sense alongside prescribed medication is decided by a psychiatrist, as none of the described studies tested combining it with ADHD pharmacotherapy.
Does ginkgo biloba work in ADHD?
Evidence says no. Salehi et al. compared ginkgo with methylphenidate in 50 outpatient children with ADHD in a randomized double-blind parallel-group six-week study (Progress in Neuro-Psychopharmacology and Biological Psychiatry, 2010).
The difference was clear on both scales. Parent-rated scores improved by 6.52 points in the ginkgo group and 15.92 in methylphenidate. Teacher-rated difference was even larger: 0.84 versus 14.04 points. Ginkgo had milder adverse effects, as appetite loss, headache, and insomnia were more frequent with methylphenidate, but efficacy was incomparable.
The authors concluded ginkgo was less effective than methylphenidate in ADHD treatment. Independently, a review of sixteen herbal product studies classified ginkgo, alongside St. John’s wort, as ineffective for this indication (Sarris, Complementary Therapies in Medicine, 2011). Two sources, same conclusion. Before adding ginkgo to medications, ask your doctor, as with any supplement. If you want a review of herbs without clinical context, see our post on herbs for concentration and focus.
What else did the independent review of herbal products show?
It showed that results depend on the substance, not on whether the product is natural. Sarris et al. searched four scientific databases - PubMed, PsycINFO, Cochrane Library, and CINAHL - up to May 26, 2011, looking only for randomized controlled trials with control groups. Sixteen studies met inclusion criteria and were quality-rated (Complementary Therapies in Medicine, 2011).
The table below shows how authors categorized substances. This is a rare review that does not end with a call for more research but points to specific products on both sides.
| Review rating | Substances |
|---|---|
| Predominant evidence support | zinc, iron, maritime pine bark, Chinese herbal mix Ningdong |
| Mixed evidence, mostly inconclusive | omega-3 fatty acids, l-acetylcarnitine |
| Considered ineffective in ADHD | ginkgo biloba, St. John’s wort |
| Promising directions for further research | bacopa monnieri, kava pepper |
Two things deserve attention. First, omega-3 were placed in the inconclusive category by Sarris, though Bloch’s meta-analysis the same year showed a statistically significant effect. The discrepancy arises from different included studies and assessment thresholds, illustrating how delicate this result is. Second, the last row describes hopes, not findings. A manufacturer citing this review on bacopa packaging moves the statement from “worth investigating” to “proven.”
Do rhodiola and lion’s mane have evidence in ADHD?
They have none. Both plants are marketed as focus support, but cited studies concern completely different populations and endpoints. It is worth separating this before spending money meant for diagnostics.
A systematic review by Hung et al. covered eleven randomized placebo-controlled studies on Rhodiola rosea. Six concerned physical performance, four mental performance, and two patients with psychiatric disorders (Phytomedicine, 2011). Authors allow possible benefit but note lack of independent replication. None concerned ADHD.
Lion’s mane has one often-cited clinical study. Mori et al. administered it for sixteen weeks to thirty Japanese aged 50-80 with mild cognitive impairment in a double-blind placebo-controlled design, assessed by a scale based on Hasegawa Dementia Scale (Phytotherapy Research, 2009). At weeks 8, 12, and 16, the active group performed significantly better than placebo. Four weeks after stopping, scores dropped significantly. These data concern older people with cognitive impairment, not children or adults with ADHD, and the effect depended on continued supplementation.
Does CBD help with ADHD?
There is no evidence it does. The only randomized study worth citing is the pilot EMA-C project: 30 adults with ADHD received cannabinoid product or placebo; the primary endpoint was cognitive performance and activity level measured by QbTest (Cooper, European Neuropsychopharmacology, 2017).
Intention-to-treat analysis found no difference. Secondary endpoints showed nominal improvement in hyperactivity with impulsivity and one measure of cognitive inhibition, plus trends toward better inattention and emotional lability. After correction for multiple testing, none remained significant. One serious adverse event of muscle spasms and three mild events occurred in the active group. Authors called the result preliminary and inconclusive.
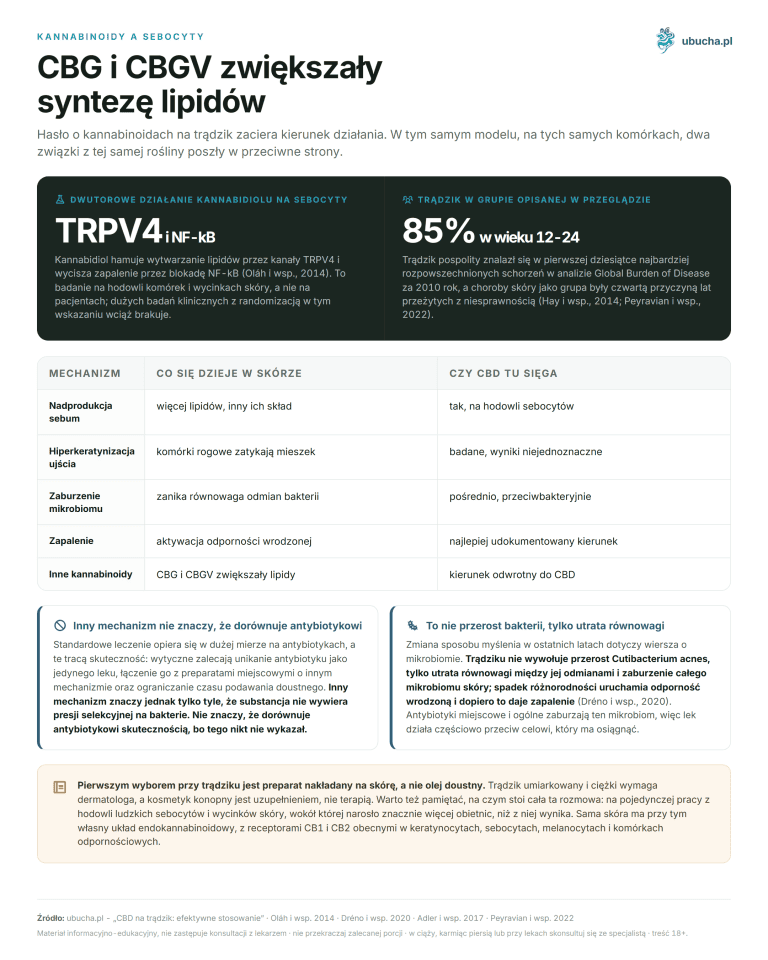
Regarding CBD safety, EFSA’s panel on nutrition, novel foods, and food allergens stated in an updated opinion that safety cannot be established in persons under 25, pregnant or breastfeeding women, and those taking medications. ADHD patients on pharmacotherapy belong to the last group, and adolescents to two groups simultaneously. If sleep is a problem, it is more sensible to start with sleep hygiene; we collected proven approaches in the post on natural ways to treat insomnia.
Which diet myths in ADHD should be rejected?
Two persistent myths have been tested in large studies and both were disproven. The first says sugar worsens symptoms. The second says elimination diets based on blood tests cure ADHD. Conclusions have been available for years but rarely reach guides.
Wolraich et al. conducted a meta-analysis of sixteen reports comprising 23 placebo-controlled studies with artificial sweetener and blinding of children, parents, and staff (JAMA, 1995). For all fourteen assessed dimensions, confidence intervals included zero. The authors conclude sugar does not affect behavior or cognitive performance in children, and strong parental belief arises from expectation and situational association.
The INCA study tested an elimination diet in 100 children aged 4 to 8 (Pelsser, The Lancet, 2011). After five weeks of strict diet, the difference versus control on the ADHD Rating Scale was 23.7 points. In the second phase, foods with high or low IgG antibody levels were added back to responders. Symptom relapse occurred in 19 of 30 children (63%), independent of IgG levels. Authors explicitly advised against diets based on IgG tests. A strict diet under supervision may show if food matters, but commercial intolerance tests do not resolve this.
How to read supplement study results?
Five concepts suffice to independently assess if a label claim is supported. All appeared in studies above, so they are not theory detached from practice. Know them before spending money on a product sold to a parent of a diagnosed child.
Randomization means random assignment to groups, so groups differ only by the substance studied. Blinding means neither participant nor assessor knows who got the supplement or placebo. Without these, improvement may result from expectation, as shown in the sugar meta-analysis where parental belief outweighed measured effect (Wolraich, JAMA, 1995).
The third concept is primary versus secondary endpoint. The primary endpoint is declared before the study and determines the result. In the cannabinoid ADHD study, the primary endpoint was not significant, and secondary improvements disappeared after correction for multiple testing (Cooper, European Neuropsychopharmacology, 2017). Fourth is confidence interval: if it includes zero, the result is consistent with no effect, as in all fourteen sugar dimensions. Fifth is standardized mean difference, allowing comparison across studies using different scales; the larger the absolute value, the stronger the effect. Checking these five takes minutes and saves much more.
How long did the studies cited by the market last?
From six weeks to three months, and in two cases authors checked what happens after stopping the supplement. The table below organizes the scale and duration of studies described here to help weigh a single label claim.
| Substance | Study | Participants | Duration | ADHD relevant |
|---|---|---|---|---|
| Omega-3 | Bloch and Qawasmi, 2011 | 699 children, 10 studies | meta-analysis | yes |
| Magnesium with B6 | Mousain-Bosc, 2006 | 40 children | at least 8 weeks | yes |
| Iron | Konofal, 2008 | 23 children | 12 weeks | yes |
| Zinc | Bilici, 2004 | 400 patients | 12 weeks | yes, no attention improvement |
| Bacopa monnieri | Stough, 2008 | 62 healthy adults | 90 days | no |
| Ginkgo biloba | Salehi, 2010 | 50 children | 6 weeks | yes, weaker than drug |
| Ashwagandha | no ADHD study | not applicable | not applicable | no, studied only stress and anxiety outside ADHD |
| Lion’s mane | Mori, 2009 | 30 persons aged 50-80 | 16 weeks | no |
| Cannabinoids | Cooper, 2017 | 30 adults | pilot | yes, no result |
Read the last two columns together. Where the last column says no, the manufacturer’s promise is based on transferring results from another patient group. This does not mean the plant has no effect. It means the study says nothing about ADHD.
How to talk to a psychiatrist about supplements?
Start simply with a list. Write down everything you take with brand names, attach blood test results if you have them, and ask directly about interactions. The doctor does not judge such questions but needs a full picture to safely manage treatment.
Three questions are always worth asking. Could any supplement interact with my prescribed medication? What symptoms mean I should seek immediate help? What monitoring tests make sense in my case? Answers to these three questions resolve more than any internet list, as they consider comorbidities and specific products.
What not to do alone? Do not stop prescribed medication or change its dose, even if the supplement seems effective. Do not add several new supplements at once, as no reaction can be attributed to a cause. Do not buy products from unclear sources, as supplements lack oversight comparable to drugs. Safe remain things no one questions: regular sleep, exercise, meals at fixed times, and therapeutic work on daily organization. They do not replace treatment but improve conditions where treatment works.
Be prepared for an unexpected answer. The doctor may decide a supplement makes no sense in your case and give a reason you won’t find online, such as interaction or comorbidity excluding the substance. This is not refusal but a result. If a specialist refuses to discuss supplements at all or only offers supplements without considering treatment, seek a second opinion. An approach combining pharmacotherapy, therapy, and correction of confirmed deficiencies is today’s standard, not extravagance.
Frequently Asked Questions
Can supplements replace ADHD medications?
No. A network meta-analysis of 133 double-blind randomized studies identified methylphenidate as first-line in children and adolescents, amphetamines in adults (Cortese, The Lancet Psychiatry, 2018). No supplement has evidence of this class, as none underwent studies of such scale. Treatment decisions and supplementation are made by the attending psychiatrist.
Which supplement has the strongest evidence in ADHD?
Omega-3 fatty acids. A meta-analysis of ten randomized studies including 699 children showed a small but statistically significant effect, with efficacy correlating with eicosapentaenoic acid content (Bloch and Qawasmi, Journal of the American Academy of Child and Adolescent Psychiatry, 2011). The authors called this effect modest compared to pharmacotherapy and saw a complementary role.
Does zinc improve concentration in ADHD?
A study on 400 patients showed no improvement in attention deficit after zinc sulfate, although hyperactivity, impulsivity, and relationship disturbances improved (Bilici, Progress in Neuro-Psychopharmacology and Biological Psychiatry, 2004). Full therapeutic response was 28.7% in the zinc group versus 20% on placebo, so a difference exists but is small.
Does ginkgo biloba work on ADHD symptoms?
Not to a degree comparable with treatment. In a randomized study on 50 children, ginkgo performed clearly worse than methylphenidate on parent and teacher scales (Salehi, Progress in Neuro-Psychopharmacology and Biological Psychiatry, 2010). An independent review of sixteen studies deemed ginkgo ineffective for this indication (Sarris, Complementary Therapies in Medicine, 2011).
Does CBD help with ADHD?
There is no evidence. A pilot randomized study on 30 adults did not reach significance on the primary endpoint, and improvements among secondary endpoints did not survive correction for multiple testing (Cooper, European Neuropsychopharmacology, 2017). One serious adverse event of muscle spasms was reported in the active group.
Does sugar worsen ADHD symptoms?
No. A meta-analysis of sixteen reports covering 23 studies showed sugar does not affect behavior or cognitive functions in children, and confidence intervals for all fourteen measured dimensions included zero (Wolraich, JAMA, 1995). The authors explain parents’ belief as expectation and association with situations where sweets appear.
Is it worth testing iron levels in a child with ADHD?
Yes, if ordered by a doctor. In a comparative study, ferritin below 30 ng/ml occurred in 84% of children with ADHD versus 18% in controls, with mean concentrations of 23 and 44 ng/ml respectively (Konofal, Archives of Pediatrics and Adolescent Medicine, 2004). Supplementation without confirmed deficiency is unjustified and can be harmful.
How long does it take to see the effect of natural support?
Studies lasted from six weeks to several months, and in two cases improvement disappeared after stopping the supplement (Mousain-Bosc, Magnesium Research, 2006; Mori, Phytotherapy Research, 2009). This is the opposite of stimulant drugs, whose effect is assessed in hours. Do not shorten observation time or draw conclusions after a week.
Summary
After reviewing abstracts, the picture is consistent and less impressive than in ads. The strongest data among supplements are for omega-3 fatty acids, though authors called their effect modest compared to pharmacotherapy. Supplementing confirmed iron and magnesium deficiencies is reasonable but only after blood tests ordered by a doctor, not prophylactically.
On the other side are substances whose promises did not withstand verification. Zinc improved hyperactivity but not attention deficit. Ginkgo performed worse than medication in direct comparison and was deemed ineffective in an independent review. Bacopa monnieri, rhodiola, and lion’s mane have no ADHD studies. CBD did not reach significance in the only pilot randomized trial.
The practical conclusion is one. Diagnosis and treatment belong to the psychiatrist, and the role of supplements begins only where the doctor sees a place for them and ends where the promise of replacing therapy begins. None of the products described here passed studies justifying such a promise.
Sources: ADHD, treatment, and micronutrients
- Polanczyk G et al. The worldwide prevalence of ADHD: a systematic review and metaregression analysis. The American Journal of Psychiatry, 2007.
- Polanczyk GV et al. ADHD prevalence estimates across three decades: an updated systematic review and meta-regression analysis. International Journal of Epidemiology, 2014.
- Cortese S et al. Comparative efficacy and tolerability of medications for attention-deficit hyperactivity disorder in children, adolescents, and adults. The Lancet Psychiatry, 2018.
- Hoogman M et al. Subcortical brain volume differences in participants with attention deficit hyperactivity disorder. The Lancet Psychiatry, 2017.
- Bloch MH, Qawasmi A. Omega-3 fatty acid supplementation for the treatment of children with ADHD symptomatology. Journal of the American Academy of Child and Adolescent Psychiatry, 2011.
- Kozielec T, Starobrat-Hermelin B. Assessment of magnesium levels in children with attention deficit hyperactivity disorder. Magnesium Research, 1997.
- Mousain-Bosc M et al. Improvement of neurobehavioral disorders in children supplemented with magnesium-vitamin B6. Magnesium Research, 2006.
- Konofal E et al. Iron deficiency in children with attention-deficit/hyperactivity disorder. Archives of Pediatrics and Adolescent Medicine, 2004.
- Konofal E et al. Effects of iron supplementation on attention deficit hyperactivity disorder in children. Pediatric Neurology, 2008.
- Bilici M et al. Double-blind, placebo-controlled study of zinc sulfate in the treatment of attention deficit hyperactivity disorder. Progress in Neuro-Psychopharmacology and Biological Psychiatry, 2004.
Sources: plants, cannabinoids, and diet
- Stough C et al. Examining the nootropic effects of a special extract of Bacopa monniera on human cognitive functioning. Phytotherapy Research, 2008.
- Salehi B et al. Ginkgo biloba for attention-deficit/hyperactivity disorder in children and adolescents. Progress in Neuro-Psychopharmacology and Biological Psychiatry, 2010.
- Sarris J et al. Complementary medicines (herbal and nutritional products) in the treatment of Attention Deficit Hyperactivity Disorder. Complementary Therapies in Medicine, 2011.
- Hung SK, Perry R, Ernst E. The effectiveness and efficacy of Rhodiola rosea L.: a systematic review of randomized clinical trials. Phytomedicine, 2011.
- Mori K et al. Improving effects of the mushroom Yamabushitake (Hericium erinaceus) on mild cognitive impairment. Phytotherapy Research, 2009.
- Cooper RE et al. Cannabinoids in attention-deficit/hyperactivity disorder: a randomised-controlled trial. European Neuropsychopharmacology, 2017.
- Wolraich ML, Wilson DB, White JW. The effect of sugar on behavior or cognition in children: a meta-analysis. JAMA, 1995.
- Pelsser LM et al. Effects of a restricted elimination diet on the behaviour of children with attention-deficit hyperactivity disorder (INCA study). The Lancet, 2011.
- EFSA Panel on Nutrition, Novel Foods and Food Allergens. Update of the statement on safety of cannabidiol as a novel food. EFSA Journal, 2026.
This article is for informational and educational purposes and does not constitute medical advice. Before starting cannabis or CBD for therapeutic purposes, consult a doctor, especially if you take other medications, are pregnant, or breastfeeding.
Author: Michał Waluk · Published: 2026-05-11 · Updated: 2026-08-24