
Ashwagandha and CBD Together - Are They Safe 2026
Ashwagandha and CBD together: what studies on each substance separately have shown, where evidence ends, and who should avoid combining them.
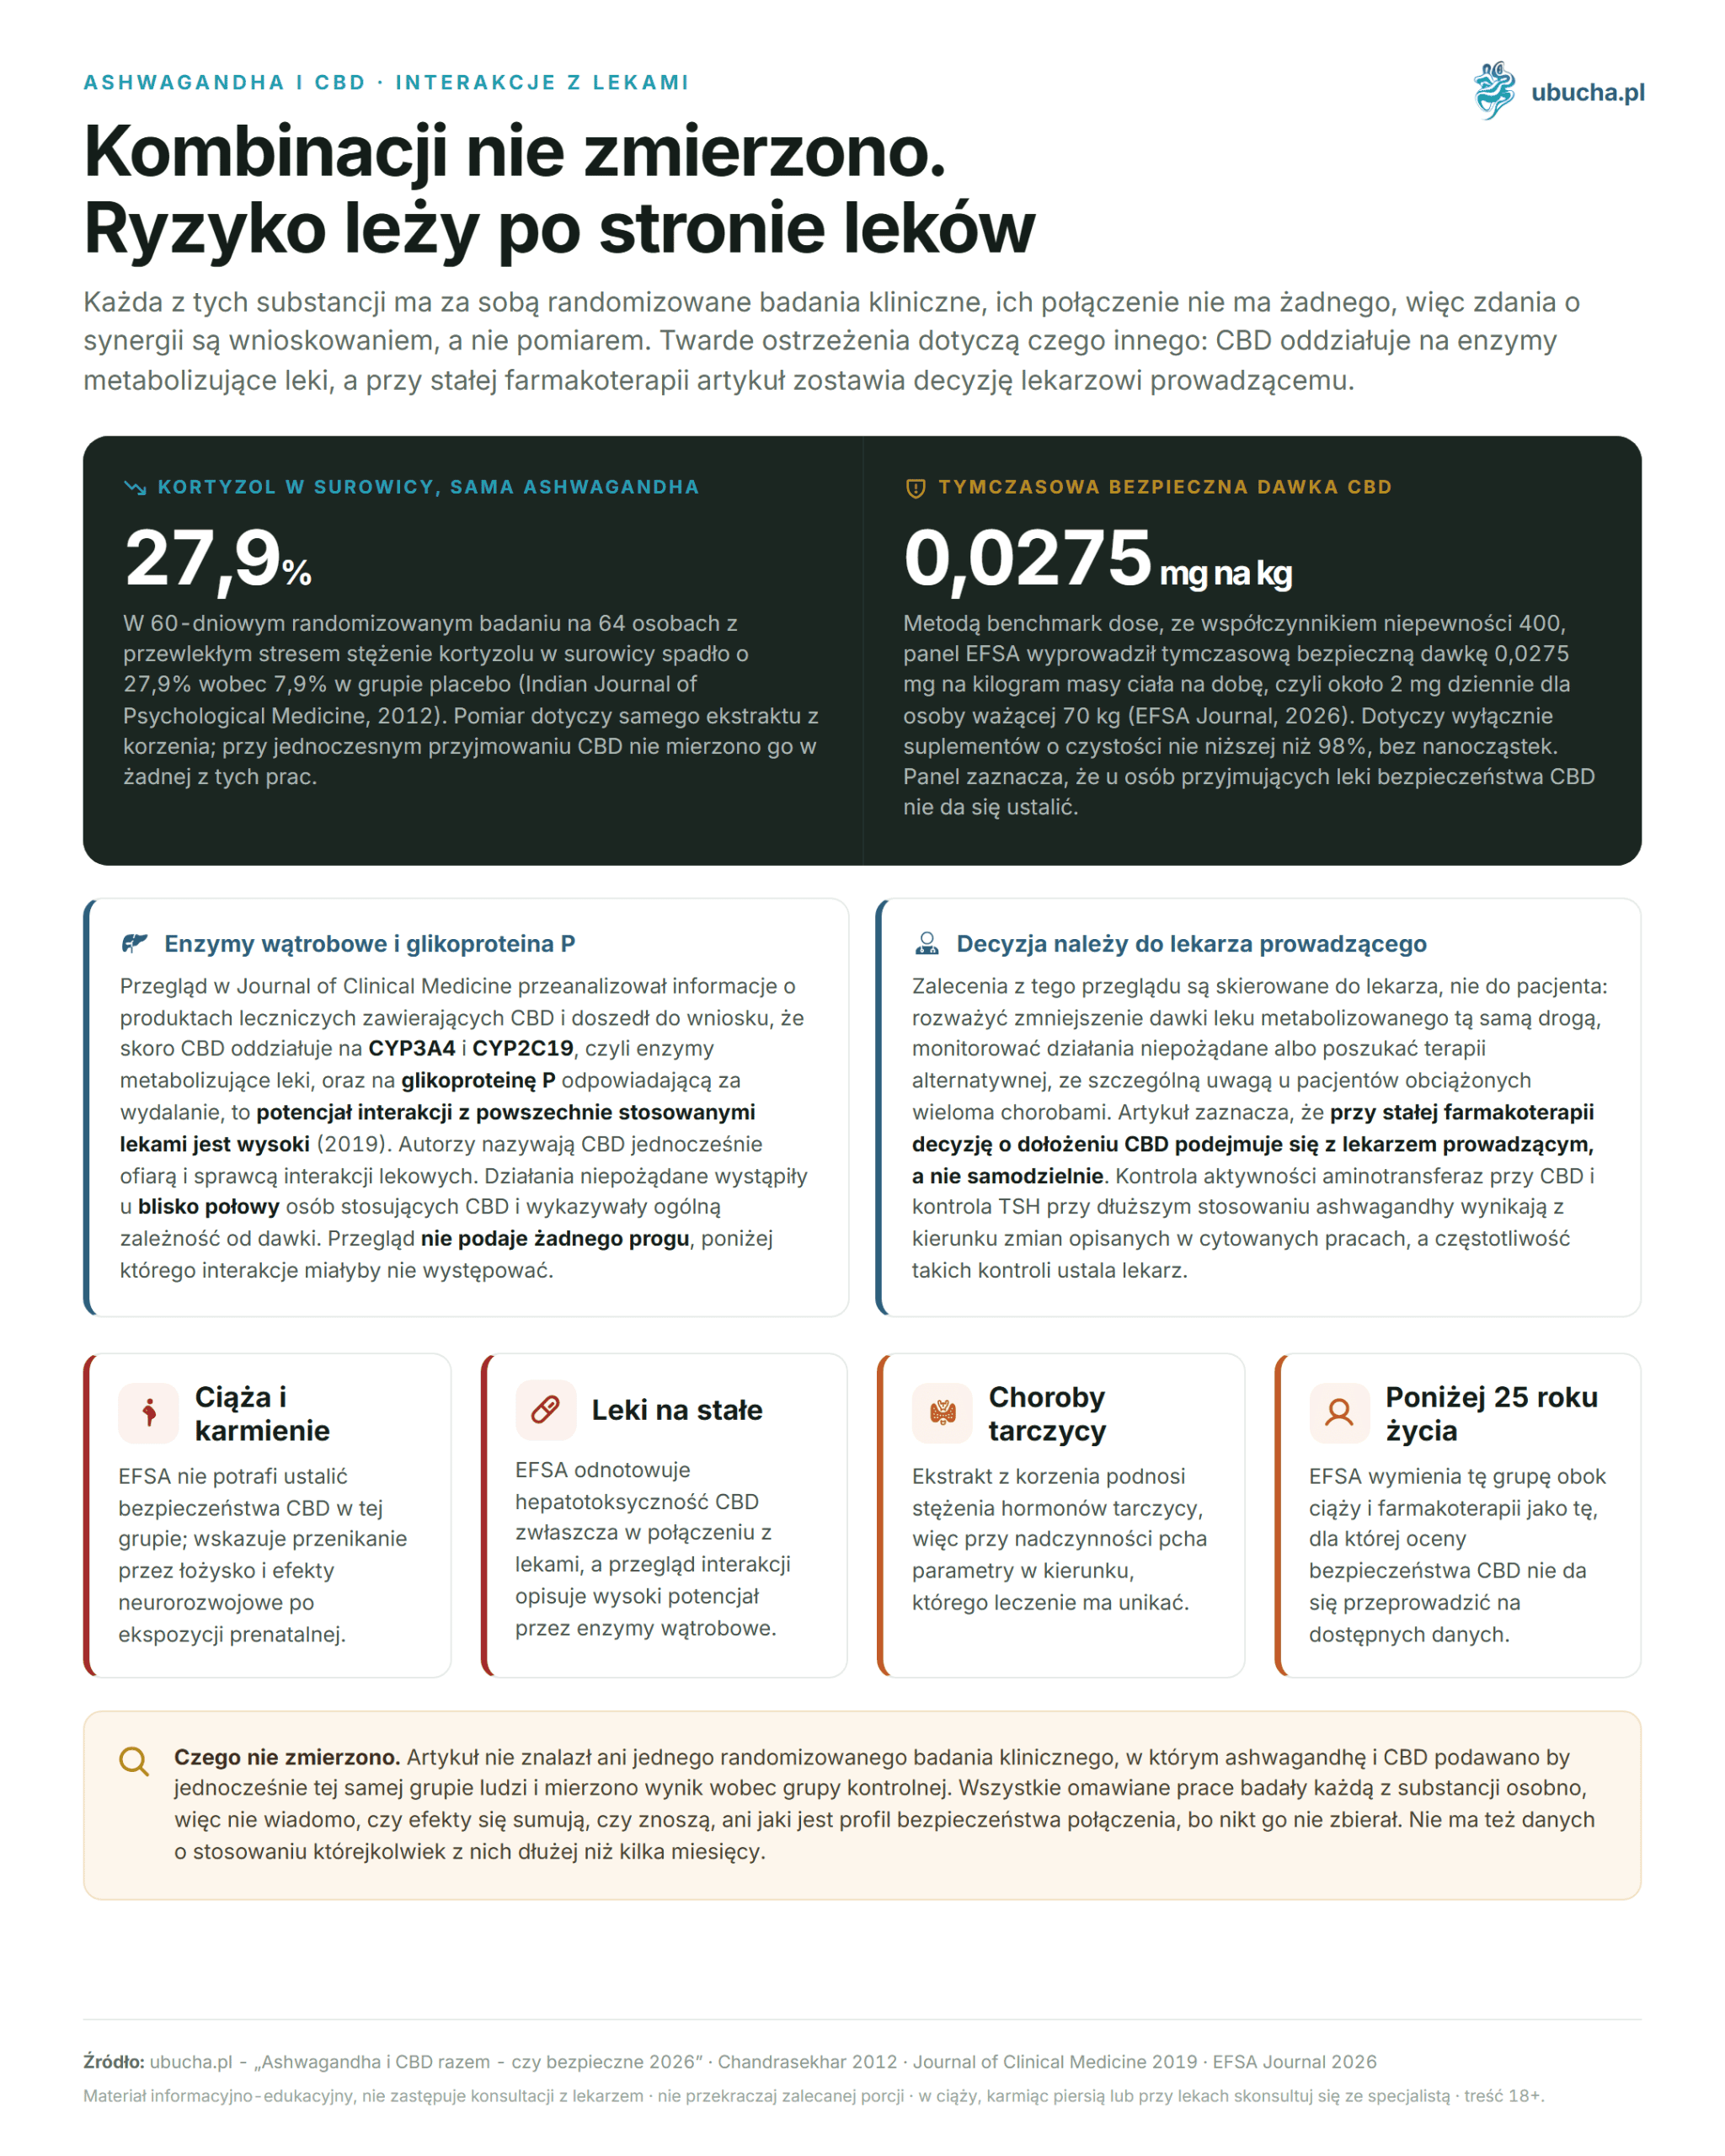
Combining ashwagandha with CBD is one of the more popular protocols for supporting the stress system, yet one of the least documented. Each of these substances has randomized clinical trials behind it. Their combination has none. This distinction determines everything that can be honestly said about this combination, so we place it at the beginning, not in a disclaimer at the end. This text shows exactly what was measured in studies on ashwagandha and CBD separately, where evidence ends and extrapolation begins, what warnings safety authorities issue, and who should avoid this combination regardless of dose. We also list claims removed from the previous version of this article because the cited studies did not support them. The numbers here describe only the course of specific studies and are not recommendations for readers.
KEY INFORMATION
- There is no randomized clinical trial on simultaneous administration of ashwagandha and CBD in humans. Conclusions about synergy are extrapolations from separate studies of each substance.
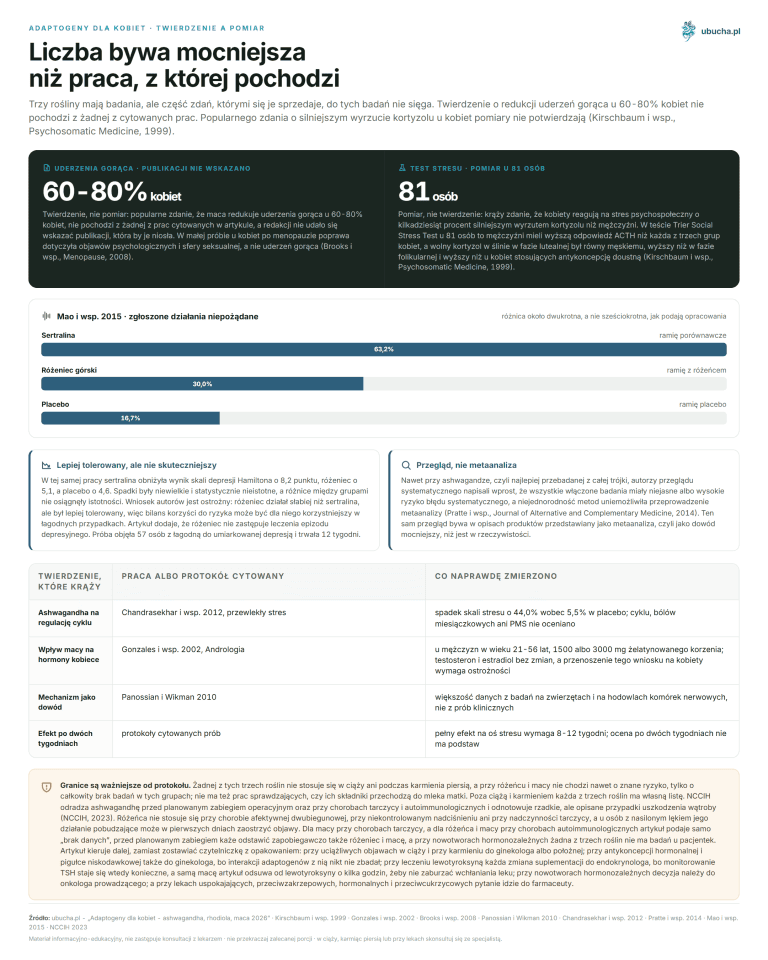
- Ashwagandha root extract reduced serum cortisol concentration by 27.9% versus 7.9% in placebo in a 60-day study on 64 people (Indian Journal of Psychological Medicine, 2012).
- CBD affects CYP3A4, CYP2C19, and P-glycoprotein, so the potential for interactions with commonly used drugs is high, and adverse effects occurred in nearly half of users (Journal of Clinical Medicine, 2019).
- EFSA cannot establish CBD safety in people under 25 years old, pregnant and breastfeeding women, and those taking medications (EFSA Journal, 2026).
- Ashwagandha raises thyroid hormone levels, which is beneficial in hypothyroidism and problematic in hyperthyroidism (Journal of Alternative and Complementary Medicine, 2018).
What is ashwagandha and what exactly was measured in its studies?
Ashwagandha, or Withania somnifera, is a plant used for centuries in Ayurvedic medicine and studied in randomized clinical trials for over a decade as a stress-relieving agent. It is marketed as a dietary supplement, most often as a standardized root extract.
Clinical studies cited by manufacturers are surprisingly few and all short. The three most cited lasted 60 days, 60 days, and 10 weeks respectively, with the largest sample including 64 people. None measured what happens when CBD is taken simultaneously.
| Study | Participants | Preparation and duration | What was measured |
|---|---|---|---|
| Chandrasekhar 2012 | 64 people with chronic stress | KSM-66 extract, 300 mg capsule twice daily, 60 days | Serum cortisol, PSS, GHQ-28, and DASS scales |
| Lopresti 2019 | 60 healthy adults with high stress | Shoden extract, 240 mg once daily, 60 days | HAM-A and DASS-21 scales, morning cortisol, DHEA-S, testosterone |
| Langade 2019 | 60 patients with insomnia and anxiety | Root extract, 300 mg twice daily, 10 weeks | Sleep actigraphy, PSQI and HAM-A scales |
Note that the preparations differ. KSM-66 and Shoden are different extracts with different standardizations and doses, so transferring results from one to another is not straightforward. We analyze their differences in a separate text about KSM-66 and Sensoril extracts.
What did Chandrasekhar’s cortisol study show?
This is the most frequently cited ashwagandha study and is worth knowing precisely because the 27.9% figure circulates online detached from context. The study was prospective, randomized, double-blind, and placebo-controlled. It included 64 people with documented chronic stress who took a capsule twice daily for 60 days. The capsule contained 300 mg of highly concentrated full-spectrum root extract, totaling 600 mg daily (Indian Journal of Psychological Medicine, 2012).
In the active group, serum cortisol concentration decreased by 27.9% after 60 days compared to baseline. The placebo group saw a 7.9% decrease, with the difference between groups statistically significant. We read these values from the full text because the abstract only reported significance levels.
Participant selection also matters for interpreting results. Participants were recruited among those scoring no higher than 15 points on the WHO-5 well-being questionnaire and reporting high perceived stress. A psychiatrist examined each to exclude primary psychiatric disorders. Thus, this was not a study of ill patients but of people burdened with chronic stress, and results should be interpreted accordingly.
Questionnaire results also improved. On the GHQ-28 scale, symptom reductions were 76.1% in the somatic subscale, 69.7% in anxiety and insomnia, 68.1% in social dysfunction, and 79.2% in severe depression. Corresponding decreases in the placebo group were much smaller. Note that 69.7% refers to one GHQ-28 subscale, not the entire questionnaire or perceived stress scale.
Adverse effects were mild and comparable in both groups, with no serious events. The preparation used is explicitly named KSM-66 extract in the full text. We discuss what truly lowers cortisol and what only claims to in our text on stress and cortisol supplements.
What did ashwagandha studies on sleep and anxiety show?
The picture here is more modest than marketing suggests. In a 2019 study, 60 patients with insomnia and anxiety were assigned two-to-one to root extract or starch placebo, given twice daily for ten weeks. Sleep was measured by actigraphy, not just questionnaires (Cureus, 2019).
Sleep onset time shortened in both groups but was significantly shorter in the active group after ten weeks: 29.00 minutes versus 33.94 minutes in placebo, p = 0.019. Sleep efficiency increased from 75.63 to 83.48 in the active group and from 75.14 to 79.68 in placebo. Sleep quality improvement was significant versus placebo (p = 0.002), as were PSQI and HAM-A scale results.
The five-minute difference in sleep onset is real but small, and authors conclude further studies on larger samples are needed. The study does not report a one-quarter reduction in sleep onset time, though this figure circulates online attributed to this study.
A second 2019 study published in Medicine examined 60 healthy adults with high stress over 60 days. Shoden extract was given once daily at 240 mg. Compared to placebo, there was a significant HAM-A scale decrease (p = 0.040), and DASS-21 scale decrease was near significance. Hormonal changes were more pronounced: morning cortisol decreased (p < 0.001) and DHEA-S decreased (Medicine, 2019).
How does CBD work and what was measured in anxiety studies?
The most cited CBD anxiety study is a retrospective review of psychiatric clinic records. Charts of 103 adult patients were reviewed; 72 patients mainly reported anxiety or poor sleep quality (The Permanente Journal, 2019).
Anxiety severity decreased in the first month in 57 patients (79.2%) and remained reduced throughout observation. Sleep improved in the first month in 48 patients (66.7%) but fluctuated in subsequent months. CBD was well tolerated by all but three patients.
Three caveats apply: this was not a randomized or blinded study but a chart review of patients receiving usual care. There was no control group, so CBD effects cannot be separated from natural course or other therapies. Authors conclude controlled clinical trials are needed.
Mechanism descriptions are separate. Statements about CBD acting on 5-HT1A receptor and inhibiting FAAH enzyme come from preclinical studies and are sometimes incorrectly supported by reviews on terpenes and entourage effect, not receptor affinity or bioavailability studies. The previous article version also did this.
Is there research on combining ashwagandha with CBD?
There is none. We found no randomized clinical trial administering ashwagandha and CBD simultaneously to the same human group with a control group. All discussed studies examined each substance separately, and none report participants taking the other substance concurrently.
This means every statement about the combination’s effects is inference, not measurement. Inference can be justified but has a cost: we do not know if effects add, cancel, or if one alters the other’s fate in the body. We also lack a safety profile for the combination because no one has collected it.
Notice how this gap disappears in supplement texts. Simply stating “mechanisms are complementary” and adding two citations, one per substance, formally checks out, leaving readers believing they read about a study that does not exist. We noticed this is the most common construction in content about supplement combinations.
The practical conclusion is not “do not combine.” It is: since no combination data exist, safety reference points remain what is known about each substance separately, plus common sense about overlapping effects. The following sections address this.
Why are the mechanisms of these two substances considered complementary?
The complementarity argument is based on substances targeting the stress system at different points. Ashwagandha acts on the hypothalamic-pituitary-adrenal axis, seen in hormone changes: in the 2019 study, both morning cortisol and DHEA-S decreased, and authors directly link stress relief to modulation of this axis (Medicine, 2019).
On the CBD side, comparable hormonal measurements are lacking. The clinical study cited here recorded patient-reported symptom severity, not hormone levels. This difference in description level gives rise to intuition about non-overlapping effects, but it is intuition, not a comparison result. EFSA notes histopathological adrenal changes among hormonal disorders after CBD, so the claim of CBD neutrality toward this axis lacks support.
The second argument concerns timing. Ashwagandha effects in cited studies were measured after 60 days or 10 weeks because earlier effects were absent. CBD effects in the psychiatric clinic analysis appeared in the first month. The timing gap is real, though no study examined what happens if both courses overlap.
It is fair to add where this argument ends. Complementary mechanisms are not the same as synergistic effects. Two substances may act at different points yet produce no combined effect beyond the stronger one alone. Only a combination study can resolve this, and none exists. We develop this topic in the text on CBD and adaptogen synergy.
Does combining ashwagandha and CBD risk drug interactions?
The greatest risk of this combination lies not in their interaction with each other but in how CBD affects medications. A review published in Journal of Clinical Medicine analyzed information on medicinal products containing CBD and concluded: since CBD affects CYP3A4 and CYP2C19 enzymes metabolizing drugs and P-glycoprotein responsible for excretion, the potential for interactions with commonly used drugs is high (Journal of Clinical Medicine, 2019).
The same study provides a memorable figure. Adverse effects occurred in nearly half of CBD users and showed a general dose-dependence. The most common were elevated aminotransferase activity, drowsiness, sleep disturbances, infections, and anemia. Authors call CBD both a victim and cause of drug interactions.
Recommendations are specific and directed at physicians, not patients: consider reducing the dose of drugs metabolized by the same pathway, monitor adverse effects, or seek alternative therapy, especially in patients with multiple comorbidities. This is why adding CBD during ongoing pharmacotherapy should be decided with the treating physician, not independently.
We found no dose threshold below which interactions would not occur. The claim that risk starts only above a certain milligram daily dose appeared in the previous article version but is unsupported by the cited source. The relationship is described as generally dose-dependent without threshold indication.
What does EFSA say about CBD safety?
The latest and most cautious assessment was issued in 2026 by the EFSA panel on nutrition and novel foods, updating its 2022 position. Using the benchmark dose method with an uncertainty factor of 400, a temporary safe dose of 0.0275 mg per kilogram body weight per day was derived, about 2 mg daily for a 70 kg person (EFSA Journal, 2026).
This value is conditional. It applies only to supplements with CBD purity not less than 98%, without nanoparticles, produced by a process recognized as safe, and with excluded genotoxicity. It does not apply to other forms.
The most important statement concerns gaps. The panel states that CBD safety cannot be established in people under 25 years old, pregnant and breastfeeding women, and those taking medications simultaneously. Animal studies showed consistent liver toxicity, and human studies revealed hepatotoxic potential especially with concurrent drug use. Hormonal disorders, including altered thyroid hormone levels, were noted, and immunotoxicity has not yet been studied.
The panel explains why 2022 gaps remain. The literature review covered animal and human studies up to June 2024, but new studies had methodological limitations: non-standardized protocols, short observation times, and concurrent pharmacological treatment. Four years of new publications have not shifted the assessment to where the panel would like it.
Two additional findings relate directly to administration. Pharmacokinetic studies confirmed CBD bioavailability varies depending on the carrier and whether the supplement is taken with food. Gastrointestinal adverse effects were reported at higher doses, and neurological and psychiatric safety data were deemed insufficient.
For this article’s topic, a concrete conclusion follows. The thyroid issue appears in EFSA’s CBD assessment and in ashwagandha studies on the plant side, meaning thyroid parameters deserve special attention with this combination. No data indicate what happens when both influences sum.
What does ashwagandha do to the thyroid?
This is the best-documented contraindication part of the topic. In a randomized double-blind study, 50 patients aged 18 to 50 with subclinical hypothyroidism (TSH 4.5-10 mIU/L) were assigned to 600 mg daily root extract or starch placebo for eight weeks (Journal of Alternative and Complementary Medicine, 2018).
After eight weeks, ashwagandha significantly improved all three measured parameters versus placebo: TSH (p < 0.001), T3 (p = 0.0031), and T4 (p = 0.0096). Authors describe this as normalization of thyroid markers in this patient group. Mild, transient adverse effects were reported by 8%, with one in the active group and three in placebo.
The beneficial result in hypothyroidism turns into a warning in the opposite condition. Since the extract raises thyroid hormone levels, in hyperthyroidism or Graves’ disease it pushes parameters in the direction treatment aims to avoid. The same applies to people taking levothyroxine, where adding ashwagandha may require dose adjustment after TSH monitoring.
It is worth emphasizing what this study does not say. It included 50 people for eight weeks in one diagnostic group, and authors call it pilot. We develop the thyroid topic in the text on ashwagandha in subclinical hypothyroidism.
Who should not combine ashwagandha with CBD?
Four groups have clear support in cited sources, and in each the decision belongs to a physician, not the reader. First are pregnant and breastfeeding women. EFSA states CBD safety in this group cannot be established, citing placental transfer, systemic accumulation, and observed prenatal neurodevelopmental effects.
Second are people on chronic medications. Here, warnings come from both sides: EFSA notes CBD hepatotoxic potential especially with drugs, and the interaction review describes high potential via liver enzymes and P-glycoprotein (Journal of Clinical Medicine, 2019).
Third are people with hyperthyroidism or thyroid disease treatment, for reasons described above. Fourth are people under 25, listed by EFSA alongside pregnancy and pharmacotherapy as a group for which CBD safety assessment cannot be made with available data.
Separately, sedation deserves mention, though based on pharmacology, not combination studies. Ashwagandha was studied as a sleep aid, and drowsiness is a common CBD adverse effect. Overlapping these effects with sedatives or alcohol has not been measured, so nothing reassuring can be said.
How long did these studies last and what does it imply?
The answer is short and has practical consequences. The longest cited ashwagandha study lasted ten weeks, two others 60 days, and the thyroid study eight weeks. The CBD analysis covered several months of observation but without control group or blinding.
Thus, we have no data on use of either substance longer than a few months, and no data at all on combined use. Statements about safety over a year or longer, common in supplement texts, have no support in these studies.
This has consequences for popular advice on cycling with breaks. The advice can be reasonable but should be understood as caution due to lack of data, not from a study comparing continuous and cyclic use, which does not exist. This difference should be named rather than presenting weekly schemes as if measured.
Similarly, monitoring parameters. TSH control during prolonged ashwagandha use and aminotransferase activity monitoring with CBD are recommendations based on changes described in cited studies. Frequency is determined by a physician based on patient condition, not a table in an article.
What claims about this combination circulate without support?
While organizing this text, we removed several sentences unsupported by sources. It is worth listing them because they circulate on Polish supplement sites and readers may encounter them elsewhere.
| Claim | Fact |
|---|---|
| WHO recognized CBD as safe up to 1500 mg daily | The source address for this claim is inactive, and the latest EFSA assessment states about 2 mg daily for a 70 kg person |
| CBD interaction risk starts above 50 mg daily | The cited review does not specify any threshold, describing the relationship as generally dose-dependent |
| Ashwagandha shortens sleep onset by one quarter | The study reports 29.00 minutes versus 33.94 minutes in placebo, without percentage calculation |
| Ashwagandha raises T3 by 41.5% and T4 by 19.6% | The subclinical hypothyroidism study reports significance levels, not such percentages |
| Optimal combination dose is a specific morning and evening scheme | No combination study exists, so no studied dose exists |
The common denominator of these five items is precision: each sounds exact and gives a measurable number. Precision here is a style feature, not measurement. With supplements, a simple test applies: if a statement gives an exact number, check if the cited study actually measured what the number describes.
Are ashwagandha and CBD legal in Poland?
Both substances are legally available in Poland but on different bases. Ashwagandha is marketed as a dietary supplement ingredient. Note that sanitary notification of supplement market introduction is not authorization but a notification and does not determine ingredient status.
CBD is not listed in any controlled substances schedules. The word “cannabidiol” does not appear in the Minister of Health’s regulation on the list of psychotropic substances, narcotics, and new psychoactive substances (Dz.U. 2024 poz. 1139).
A separate issue is the THC content threshold, around which most misunderstandings arise. According to Art. 4 point 5 of the Anti-Narcotics Act, industrial hemp are Cannabis sativa L. plants with a sum of delta-9-THC and tetrahydrocannabinolic acid in flowering or fruiting tops not exceeding 0.3% dry weight, rounded to one decimal place. The basis is the consolidated act (Dz.U. 2023 poz. 1939) as amended by the March 24, 2022 act.
Two clarifications have practical significance. The threshold applies to the plant, not the finished product, and is calculated as the sum of delta-9-THC and THCA acid, not delta-9-THC alone. This distinction changes lab test results, so product descriptions ignoring it describe a different measurement than the law requires. The national threshold matches the EU threshold but does not derive from it: these are two separate regulations with the same numeric value.
Summary: is it worth combining ashwagandha with CBD?
The honest answer is: we do not know, and this is not an evasion. Each substance has randomized studies behind it; their combination has none, meaning benefits of combining remain a hypothesis, not a finding.
What is known about ashwagandha alone: root extract reduced serum cortisol by 27.9% versus 7.9% in placebo in a 60-day study on 64 people, and in a sleep study shortened sleep onset by a few minutes versus placebo. All these trials were short and small.
What is known about CBD alone: in a psychiatric clinic chart review of 72 patients, anxiety severity decreased in the first month in 79.2%, but without a control group. Safety-wise, the picture is sharper than efficacy, with adverse effects in nearly half of users, and EFSA cannot establish safety in people taking medications.
The practical takeaway for readers boils down to three points. If you take medications chronically, consult a doctor or pharmacist before adding CBD. If you have a thyroid diagnosis, ashwagandha requires endocrinologist supervision. If you are pregnant, breastfeeding, or under 25, available data do not support CBD safety, and there is no room for personal risk assessment.
Frequently Asked Questions
Is there research on combining ashwagandha and CBD?
We did not find any randomized clinical trial on simultaneous administration of both substances to humans. All available studies examined ashwagandha or CBD separately. Therefore, any statement about the combination’s effects is an extrapolation from separate studies, not a result of measuring the combination itself.
By how much does ashwagandha reduce cortisol?
In a 60-day randomized study on 64 people with chronic stress, serum cortisol concentration decreased by 27.9% in the group taking the extract and by 7.9% in the placebo group (Indian Journal of Psychological Medicine, 2012). Participants took a 300 mg capsule twice daily.
Does CBD interact with medications?
Yes. CBD affects CYP3A4 and CYP2C19 enzymes as well as P-glycoprotein, resulting in a high potential for interactions with commonly used drugs (Journal of Clinical Medicine, 2019). The review does not specify a dose threshold below which the risk would not occur.
What dose of CBD does EFSA consider safe?
The temporary safe dose is 0.0275 mg per kilogram of body weight per day, approximately 2 mg daily for a 70 kg person (EFSA Journal, 2026). This applies exclusively to supplements with CBD purity not less than 98%, without nanoparticles.
Can ashwagandha with CBD be used during pregnancy?
No. EFSA states that CBD safety in pregnant and breastfeeding women cannot be established, citing placental transfer and observed neurodevelopmental effects after prenatal exposure (EFSA Journal, 2026). Data are also lacking for ashwagandha in this group.
Does ashwagandha affect the thyroid?
Yes. In an eight-week study of 50 patients with subclinical hypothyroidism, root extract significantly improved TSH, T3, and T4 levels compared to placebo (Journal of Alternative and Complementary Medicine, 2018). The same direction of changes is undesirable in hyperthyroidism.
How much ashwagandha was given in sleep studies?
In a study of 60 patients with insomnia and anxiety, 300 mg of root extract was given twice daily for ten weeks. Sleep onset time after this therapy was 29.00 minutes versus 33.94 minutes in the placebo group (Cureus, 2019). This is a description of the study protocol, not a recommendation for readers.
Are ashwagandha and CBD legal in Poland in 2026?
Yes. Ashwagandha is marketed as a dietary supplement ingredient, and cannabidiol is not listed in any controlled substances schedules (Dz.U. 2024 poz. 1139). The statutory 0.3% threshold applies to the plant and is calculated as the sum of delta-9-THC and THCA acid.
Plant extracts used in stress studies can be found in our adaptogens category.
This article is for informational and educational purposes and does not constitute medical advice. Before starting cannabis or CBD for therapeutic purposes, consult a doctor, especially if you take other medications, are pregnant, or breastfeeding.
Author: Michał Waluk · Published: 2026-05-11 · Updated: 2026-08-10