
CBD for Acne - Effective Use 2026
CBD for acne: what the Olah 2014 study really showed, which cannabinoids help, how to use hemp cosmetics, and when a dermatologist is needed.
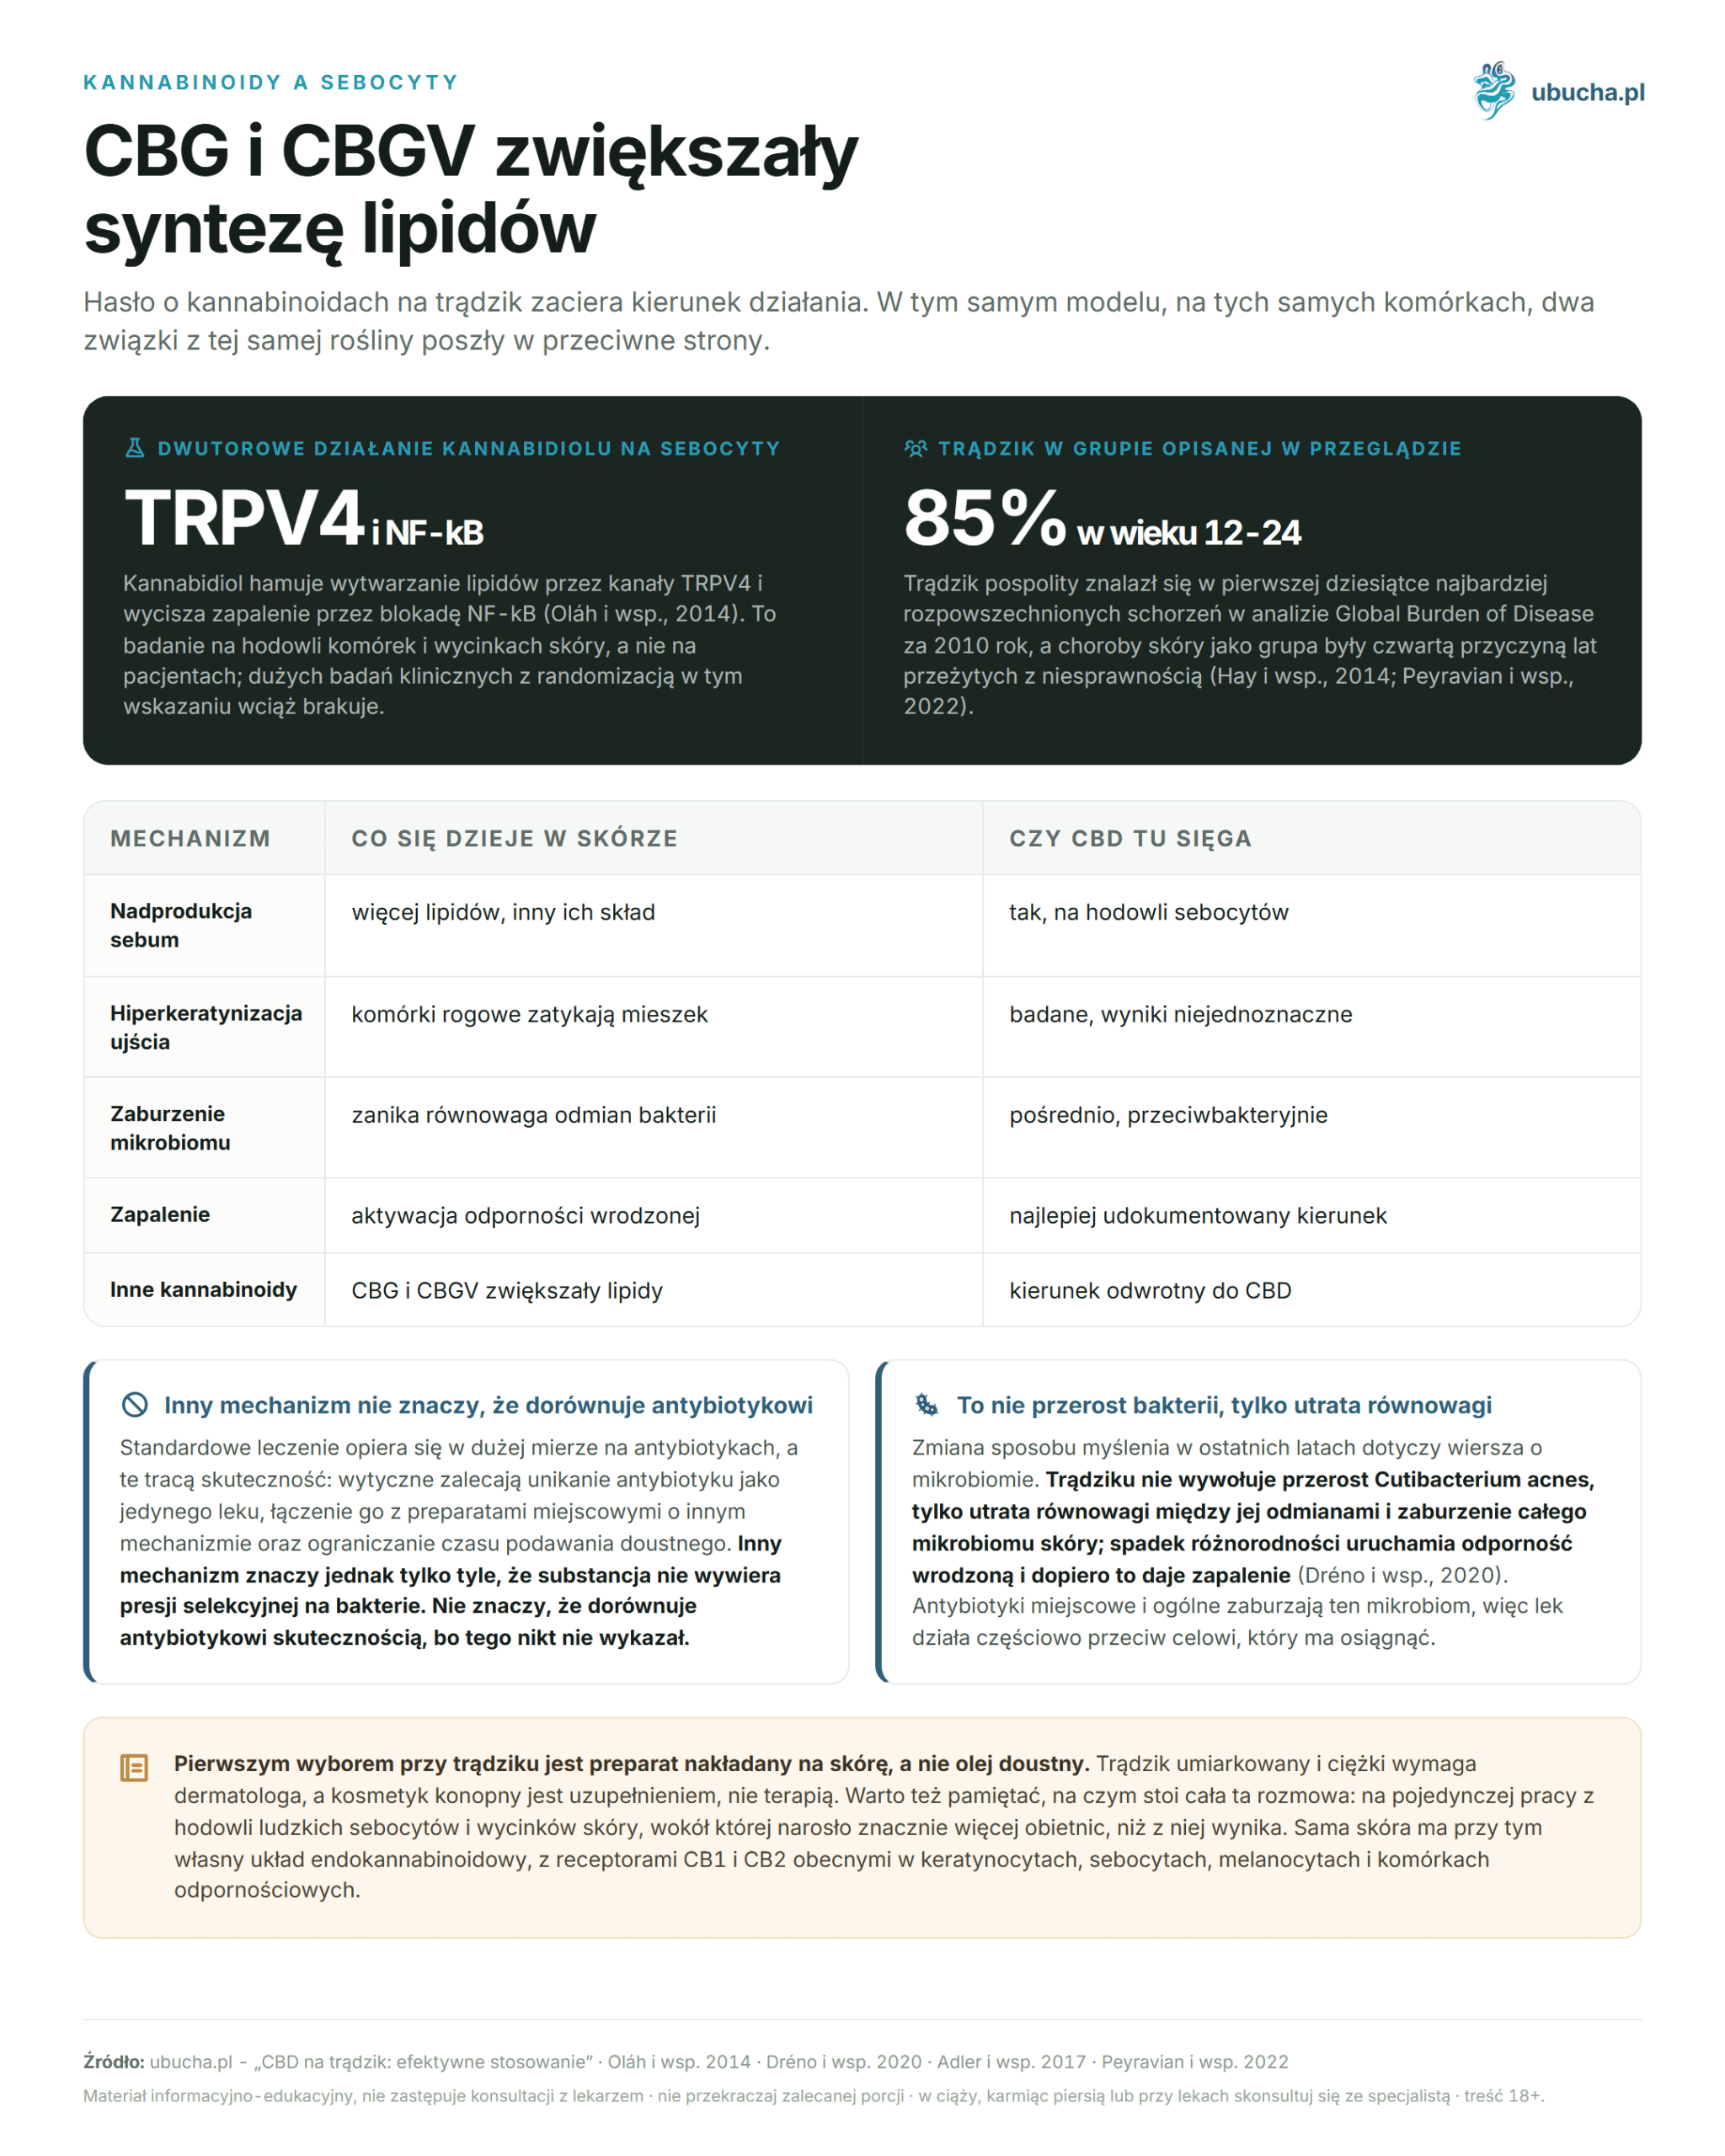
Common acne is one of the most frequent skin diseases in the world. In the 2010 Global Burden of Disease analysis, it ranked among the top ten most prevalent conditions, and skin diseases as a group were the fourth leading cause of years lived with disability (Hay et al., 2014). A 2022 review states that acne affects about 85% of people aged 12-24 (Peyravian et al., 2022). Cannabidiol entered this conversation in 2014 when Oláh’s team showed on human sebocytes that it inhibits lipid production and reduces inflammation. A lot of promises have grown around this one result, which studies do not confirm. This text separates one from the other: what has been shown, in what model, and what this means for the cosmetics shelf.
KEY INFORMATION
• CBD acts on sebocytes in two ways: it inhibits lipid production through TRPV4 channels and reduces inflammation by blocking NF-kB (Oláh et al., 2014).
• This is a study on cell cultures and skin samples, not on patients. Large randomized clinical trials are still lacking.
• Not every cannabinoid acts the same: CBG and CBGV in the same model increased lipid synthesis.
• The first choice for acne is a topical product, not an oral oil.
• Moderate and severe acne requires a dermatologist. A hemp cosmetic is a supplement, not a therapy.
What is acne and why does the skin react with inflammation?
Common acne is a chronic inflammatory disease of the pilosebaceous unit, which is a combination of the hair follicle and sebaceous gland. It develops when excess sebum meets with disturbed keratinization of the follicle opening, a change in the composition of skin bacteria, and an inflammatory response. These processes drive each other, which is why effective care rarely targets just one of them.
The review by Moradi Tuchayi et al. (2015) lists a broader set of mechanisms than the popular “clogged pores”: disturbed function of the sebaceous gland along with a change in the composition of fatty acids in sebum, hormonal environment dysregulation, neuropeptide interactions, hyperkeratinization of the follicle, and disturbances in innate and acquired immunity.
| Mechanism | What happens in the skin | Does CBD reach here |
|---|---|---|
| Overproduction of sebum | The gland produces more lipids, their composition changes | Yes, shown on sebocyte cultures |
| Hyperkeratinization of the opening | Keratinocytes clog the follicle opening, leading to comedone formation | Studied, but results are inconclusive |
| Disruption of the microbiome | The balance between strains of C. acnes is lost | Indirectly, through antibacterial action |
| Inflammation | Activation of innate immunity, papules and pustules | Yes, best documented direction |
The third row of this table has changed the most in recent years. Dréno et al. (2020) describe a change in thinking: it is not the overgrowth of Cutibacterium acnes that causes acne, but the loss of balance between its strains and the disruption of the entire skin microbiome. A decrease in diversity triggers innate immunity, and only then does it lead to inflammation.
Why are alternatives to antibiotics being sought?
Because standard acne treatment largely relies on antibiotics, which are losing effectiveness. Adler et al. (2017) summarize that the use of topical and oral antibiotics in acne is associated with the development of resistance in follicular bacteria and other bacteria, and that this has clinical consequences.
The conclusions from this review are concrete. Guidelines recommend avoiding antibiotics as the sole medication, combining them with topical preparations of a different mechanism, and limiting the duration of oral antibiotic use. In other words: the antibiotic alone has ceased to be a solution that can be used for months.
The second reason was described by Dréno et al. (2020). Topical and systemic antibiotics disrupt the skin microbiome, and since it is the loss of microbiome balance that contributes to acne, the drug partially works against the goal it aims to achieve. The authors predict a reverse direction: therapies targeting pathogenic strains while sparing commensal bacteria.
This opens a place for ingredients with a different mechanism, including cannabinoids. However, it must be immediately noted that “different mechanism” means only that the substance does not exert selective pressure on bacteria. It does not mean that it matches the effectiveness of an antibiotic, as no one has demonstrated that.
How does the endocannabinoid system regulate skin function?
The skin has its own endocannabinoid system. CB1 and CB2 receptors and enzymes responsible for the breakdown of endocannabinoids are present in keratinocytes, sebocytes, melanocytes, and immune cells. This system participates in maintaining skin balance, building the epidermal barrier, and its regeneration.
The review by Tóth et al. (2019) collects two decades of work on this issue. The authors link dysregulation of cannabinoid signaling in the skin with a whole list of common conditions: atopic dermatitis, psoriasis, scleroderma, acne, hair growth and pigmentation disorders, keratin diseases, and pruritus. This is the biological justification for why plant cannabinoids have entered dermatology.
It is worth separating two things, as they usually blend in guides. The presence of a receptor in a cell only indicates that there is a place to act. It does not say which way. The same receptor can enhance lipid production at low stimulation and inhibit it at high stimulation, and this has been observed for anandamide in sebocytes.
Therefore, with every claim about cannabinoids on the skin, one must ask three things: which molecule, at what concentration, and in what model. The answer “cannabis works on the skin” is true and useless. A similar problem was described in another inflammatory skin disease in the text about CBD oil for atopic dermatitis, where the disconnect between mechanism and clinical evidence looks almost the same.
How does CBD affect sebocytes in the Olah 2014 study?
The work of Oláh et al. from 2014 is the foundation of the entire discussion about CBD in acne. The team administered cannabidiol to cultured human sebocytes and human skin samples and described three effects at once: inhibition of lipid production, limitation of gland cell proliferation, and reduction of inflammatory response (Oláh et al., 2014).
The authors examined two stimuli that enhance lipid production. The first was arachidonic acid. The second was a combination of linoleic acid with testosterone, which is closer to what happens in the skin under the influence of androgens. CBD inhibited both.
| Effect | Described mechanism of action |
|---|---|
| Less lipids | Activation of TRPV4 channels, disruption of the ERK1/2 MAPK pathway, and reduction of NRIP1 protein |
| Fewer sebocyte divisions | Also through TRPV4 |
| Weaker inflammation | Adenosine A2a receptor, increased TRIB3, and blockade of NF-kB |
It must be stated clearly what this work does not contain. There are no patients, no counting of lesions, no severity scale for acne, and no percentage “reduction of sebum by this much” that circulates in product descriptions. The authors conclude cautiously: the combination of three effects makes CBD a promising candidate for acne treatment. A candidate, not a drug.
What else have studies shown about cannabinoids in the skin?
After 2014, the same team checked other cannabinoids, and the result turned out to be less convenient for marketing. Not all behave like CBD, and two act even contrary to what product descriptions for “oily skin” suggest.
In the work of Oláh et al. (2016), CBC and THCV inhibited baseline lipid synthesis in sebocytes, CBDV had minimal influence on it, while CBG and CBGV increased it. Lipogenesis induced by arachidonic acid was reduced by CBC, CBDV, and THCV. THCV additionally inhibited cell proliferation. The authors’ conclusion is unequivocal: they see CBG and CBGV as candidates for dry skin, while indicating CBC, CBDV, and primarily THCV as anti-acne agents.
The second work concerns keratinization. Pucci et al. (2013) demonstrated on keratinocytes that CBD and CBG lower the expression of genes involved in epidermal differentiation, including keratin 10, by enhancing DNA methylation. Both behave as transcriptional repressors. This is an interesting mechanism, but it is not evidence that CBD opens the follicle opening, and it should not be interpreted as such.
The third thread concerns bacteria. Appendino et al. (2008) demonstrated that five major cannabinoids, including CBD and CBG, strongly act on methicillin-resistant Staphylococcus aureus strains. The study did not examine C. acnes, so transferring this result to acne remains a hypothesis.
Topical product or oral oil for acne?
For acne, the first choice is a topical product: cream, serum, or gel. The reason is simple. The therapy’s target lies in the skin, and studies on the effects of cannabinoids on sebocytes have been conducted on skin cell cultures and skin samples, not after oral administration.
Oral oil serves a different role and does not replace topical application. It may make sense where acne is clearly associated with psychological stress or poor sleep, but then it works on the accompanying factor, not on the sebaceous gland. This difference can be easily overlooked, as both products are called the same.
| Feature | Topical Product | Oral Oil |
|---|---|---|
| Target of action | Sebaceous gland and epidermis | Whole body |
| Evidence base for acne | Studies on sebocytes and skin samples | No studies targeting acne |
| Risk of drug interactions | Minimal | Real, requires discussion with a doctor |
| When to consider | Always as the first step | When there is a strong stress component |
The practical order looks like this: first, a few weeks with one well-chosen topical product, then evaluation, and only at the end possibly expanding to an oral form. The reverse order costs time and complicates the assessment of what actually worked.
How to use creams and serums with CBD?
The hemp product fits into the routine between cleansing and moisturizing cream. Apply it to dry, washed skin in a thin layer over all affected areas, not just spot treatment on individual pimples. In the morning, the routine ends with sunscreen.
Consistency yields more than intensity. The epidermis renews in a cycle counted in weeks, so an assessment after seven days has no biological basis. A sensible horizon is eight weeks for the first evaluation and twelve for a decision on whether to continue.
- In the morning: gentle cleansing, hemp product, moisturizing cream, sunscreen.
- In the evening: makeup removal, cleansing, hemp product or active ingredient prescribed by a doctor.
- Use retinoid, salicylic acid, and benzoyl peroxide at a different time of day than the hemp product or alternately on consecutive evenings.
- Do not apply the cosmetic to wet skin, as it makes it harder to achieve a repeatable dose.
- Do not introduce more than one new active ingredient at a time.
The last point can be the most challenging, as there is a temptation to speed up the effect. Moradi Tuchayi et al. (2015) point out that complex schemes combining several products reduce adherence to treatment, and it is precisely the lack of regularity that most often determines the failure of acne therapy. A simpler plan that you stick to for three months wins over an ambitious plan abandoned after three weeks.
How to choose a hemp cosmetic for acne-prone skin?
Three things decide: what exactly is in the composition, at what concentration, and what else the manufacturer has added. The name “hemp” on the packaging does not tell you any of these, as it encompasses products with completely different effects.
The first distinction concerns the raw material. Hemp seed oil does not contain cannabinoids; it is a good, light carrier. The extract from flower buds contains cannabinoids, and it is this that the studies on sebocytes concern. A label with just the name Cannabis sativa seed oil describes the first case.
The second distinction concerns concentration. A manufacturer that does not provide the content of the extract in percentages or milligrams per gram does not give you a basis for comparing anything. The third concerns the rest of the composition: high alcohol on the list and highly concentrated essential oils can negate the anti-inflammatory effect you are seeking.
A study by Ali and Akhtar (2015) tested a cream with 3% hemp seed extract on healthy volunteers for twelve weeks. The side of the face treated with the cream had significantly lower sebum levels and less redness than the side treated with just the base. This study was on a small group of people without acne, so treat it as a premise, not as evidence of efficacy. You can find more about the differences between forms in the text about whether hemp cosmetics really work on the skin.
What CBD will not do for acne?
A hemp cosmetic is not a drug and does not replace treatment. It will not cure nodular or cystic acne, will not remove atrophic scars, will not replace isotretinoin in resistant forms, and will not solve the hormonal problem behind recurrences.
The review by Nickles and Lio (2020) presents the state of knowledge fairly: available data indicate a possible benefit in acne, chronic pruritus, and atopic dermatitis, but existing studies are small and poorly designed, and proper randomized studies are needed to assess efficacy. The authors recommend that dermatologists be familiar with this data and discuss it with patients, not promote cannabinoids as therapy.
The realistic range of expectations is narrower than product descriptions suggest and looks roughly like this: less redness around inflammatory changes, calmer skin when used alongside irritating preparations, more stable feeling of moisturization. Subtle changes, spread over weeks.
If after twelve weeks of systematic use you see none of these changes, it is not a signal to increase the dose or to buy another hemp product. It is a signal that the problem lies elsewhere, and you need a diagnosis, not another cosmetic.
Does CBD irritate the skin and when to stop using it?
The safety profile of cannabidiol is good. The review by Iffland and Grotenhermen (2017) confirms a favorable profile in humans, and among the most commonly reported side effects are fatigue, diarrhea, and changes in appetite and body weight. All come from studies on oral administration, mainly in epilepsy and psychiatric disorders.
When used on the skin, the picture is different, as absorption into the bloodstream is minimal. Peyravian et al. (2022) noted that the tested products with hemp extracts in conditions similar to acne were safe and well tolerated. Reactions that do occur are more often related to other ingredients in the formulation than to the cannabinoid itself.
Before first use of a new cosmetic with an active ingredient, do a patch test on a small area, on the inner elbow, and wait a day. Lack of reaction does not rule out a problem later, so for the first two weeks on the face, observe more closely than usual.
- Stop using the product if redness, itching, or burning persists for more than a week.
- Stop immediately if swelling or changes on the eyelids and lips occur.
- Consult a doctor if lesions appear that are clearly different from the existing acne.
- During pregnancy and breastfeeding, discuss any new active ingredient with your doctor.
How do diet, sleep, and stress affect acne?
They do affect, but not as unequivocally as the popular version suggests. The most well-documented is the relationship with diet. A cohort study by Penso et al. (2020) included 24,452 adult French individuals and showed that the consumption of fatty and sugary products was associated with a 54% higher chance of active acne.
In the same cohort, sweetened beverages increased the chance by 18%, and milk by 12%. This is a cross-sectional study, so it shows correlation, not causation. The magnitude is clear enough that changing dietary habits makes sense as part of a plan.
With stress, the matter is more interesting, as the popular explanation turned out to be incorrect. Yosipovitch et al. (2007) studied 94 students during the pre-exam period and during the holidays. The severity of papular-pustular acne correlated with stress levels, but the amount of sebum did not differ between periods of high and low stress. The authors conclude that stress worsens acne through a mechanism other than increased oil production.
This changes the practical conclusion. Reducing tension makes sense, but not because it will “lower sebum”. The same goes for mineral ingredients, which we discuss in the text about zinc for immunity and acne.
What mistakes most often ruin treatment?
Most failed treatments do not break down over product choice, but over how it is used. Four patterns recur most often, and all can be eliminated without spending an extra penny.
| Mistake | Why it harms | What to do instead |
|---|---|---|
| Assessment after a week | The epidermis has not had time to renew | Set the assessment date for the eighth week |
| Several active ingredients at once | Irritation and lack of knowledge about what worked | Space them out at different times of day or days |
| Skipping sunscreen | Worsening redness and post-inflammatory hyperpigmentation | Use sunscreen daily, even in winter |
| Cosmetic instead of diagnosis | You are treating a symptom without identifying the cause | See a dermatologist for deep changes or scars |
To this list, one purely informational mistake is added: transferring results from cell cultures directly to one’s own face. The statement “studies have proven that CBD reduces sebum” is true only in relation to sebocytes in a culture dish. Between this and the predictable effect on a specific person lies a whole stage of research that no one has yet conducted.
The fifth mistake appears only after a few weeks and is the most deceptive. The skin with acne improves and worsens in waves, regardless of care. If you assess a product after a single good or bad week, you are measuring noise, not the effect of the cosmetic. Therefore, the assessment date is set in advance, before starting treatment, and is adhered to regardless of how the skin looks along the way.
When to see a dermatologist?
Always when the changes are deep, painful, or leave marks. A hemp cosmetic has no application as therapy here, and delaying in such a situation costs scars, which are harder and more expensive to remove than treating acne itself.
Moradi Tuchayi et al. (2015) remind us of two things that are easy to forget when looking at the cosmetics shelf: acne often leaves scars and significantly lowers the quality of life for patients. None of these consequences can be reversed with a cream.
- Nodes, cysts, or painful changes upon pressure.
- Scars, indentations, or discolorations that persist for months.
- No improvement after twelve weeks of proper care.
- Sudden exacerbation in an adult after a period of stabilization.
- Suspected hormonal background, for example, with irregular menstruation.
- Clear impact of skin changes on well-being and functioning.
For the visit, bring a list of everything you apply to your skin and take orally, along with supplements. Photos from several moments and notes on what worsens the skin condition will also be helpful. You can usually use a hemp cosmetic alongside treatment, but tell your doctor about it, especially before exfoliating procedures.
Summary: how to safely implement CBD into your care
CBD has a reasonable biological basis in acne and a weak clinical basis. The work of Oláh et al. from 2014 showed three effects at once on human sebocytes, and the review by Nickles and Lio from 2020 adds that large studies on patients are still lacking. Both statements are true simultaneously and together describe the state of knowledge.
This leads to a cautious approach. A topical product as the first choice, one new ingredient at a time, evaluation after eight weeks, and a decision after twelve. Oral oil only when you see a clear link between exacerbations and psychological stress.
Also remember that not every cannabinoid pulls in the same direction. CBG and CBGV in the 2016 study increased lipid synthesis in sebocytes, so the product description promising CBG for oily skin contradicts the work it usually cites. Reading the composition makes very practical sense here.
And the most important thing: a cosmetic is an addition to the plan, not the plan itself. Moderate and severe acne belongs to the dermatologist, and the sooner a person with deep changes gets there, the fewer traces will remain.
Frequently Asked Questions
Does CBD really help with acne, or is it just marketing?
The biological basis is real. Oláh et al. (2014) demonstrated on human sebocytes that CBD inhibits lipid production, limits cell proliferation, and reduces inflammation. However, this is a study on cell cultures and skin samples, not on patients, so we treat it as a premise, not as evidence of clinical efficacy.
How long does it take to see effects from a CBD cosmetic?
Realistically, from eight to twelve weeks of regular use twice a day. The epidermis renews in a cycle counted in weeks, so an assessment after seven days measures nothing. The eighth week is a good time for the first evaluation, and the twelfth for a decision on continuation.
Is CBG better than CBD for oily skin?
No, available studies indicate the opposite. In the work of Oláh et al. (2016), CBG and CBGV increased baseline lipid synthesis in human sebocytes, and the authors see them as candidates for dry skin. As an anti-acne direction, they indicated CBC, CBDV, and primarily THCV. Therefore, the product description promising CBG for oily skin contradicts this work.
Is hemp seed oil the same as CBD extract?
No. Hemp seed oil does not contain cannabinoids and serves as a light carrier and emollient. The extract from flower buds contains CBD, and it is this that the studies on sebocytes concern. A label with just the name Cannabis sativa seed oil describes the first case.
Can I combine a CBD cosmetic with a retinoid or acids?
Yes, provided they are spaced out in time. Use retinoid, salicylic acid, or benzoyl peroxide as directed by your doctor, and the hemp product at a different time of day or on alternate evenings. Do not introduce two new active ingredients in the same week, as in case of irritation, you will not be able to distinguish which one caused it.
Does stress really increase sebum production?
The study by Yosipovitch et al. (2007) on 94 students did not confirm this. The severity of papular-pustular changes correlated with stress levels, but the amount of sebum did not differ between periods of high and low tension. Stress worsens acne through a mechanism other than increased oil production.
Is a CBD cosmetic safe for sensitive skin?
Usually yes. Peyravian et al. (2022) noted good tolerance of products with hemp extracts tested in conditions similar to acne. Reactions are more often caused by other ingredients in the formulation, such as alcohol or highly concentrated essential oils. Before first use, do a 24-hour patch test on the inner elbow and observe the skin for the first two weeks.
Will CBD replace a visit to the dermatologist?
No. Acne with nodules, cysts, or scars requires treatment that no cosmetic can provide. Moradi Tuchayi et al. (2015) remind us that acne often leaves scars and significantly lowers the quality of life for patients. A hemp product can accompany therapy conducted by a doctor, but it does not replace it and should not delay a visit.
If you want to see what recipes with hemp extract look like, browse the available hemp cosmetics and compare the compositions according to the principles described above.
This article is for informational and educational purposes and does not constitute medical advice. Before starting to use cannabis or CBD for therapeutic purposes, consult your doctor, especially if you are taking other medications, are pregnant, or breastfeeding.
Author: Michał Waluk · Published: 2026-05-11 · Updated: 2026-08-10