
MCT vs olive oil as a CBD carrier: why the type of fat changes absorption
MCT or olive oil as a carrier for CBD oil? What has really been measured, how much a fatty meal gives, and why the advantage of MCT is not confirmed in humans.
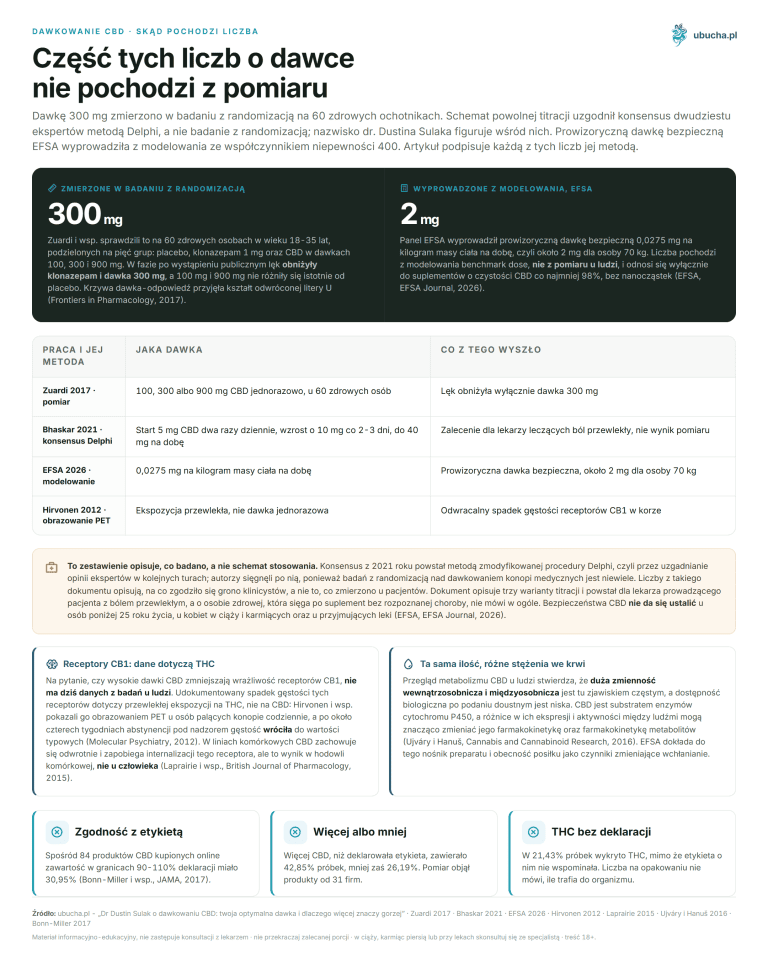
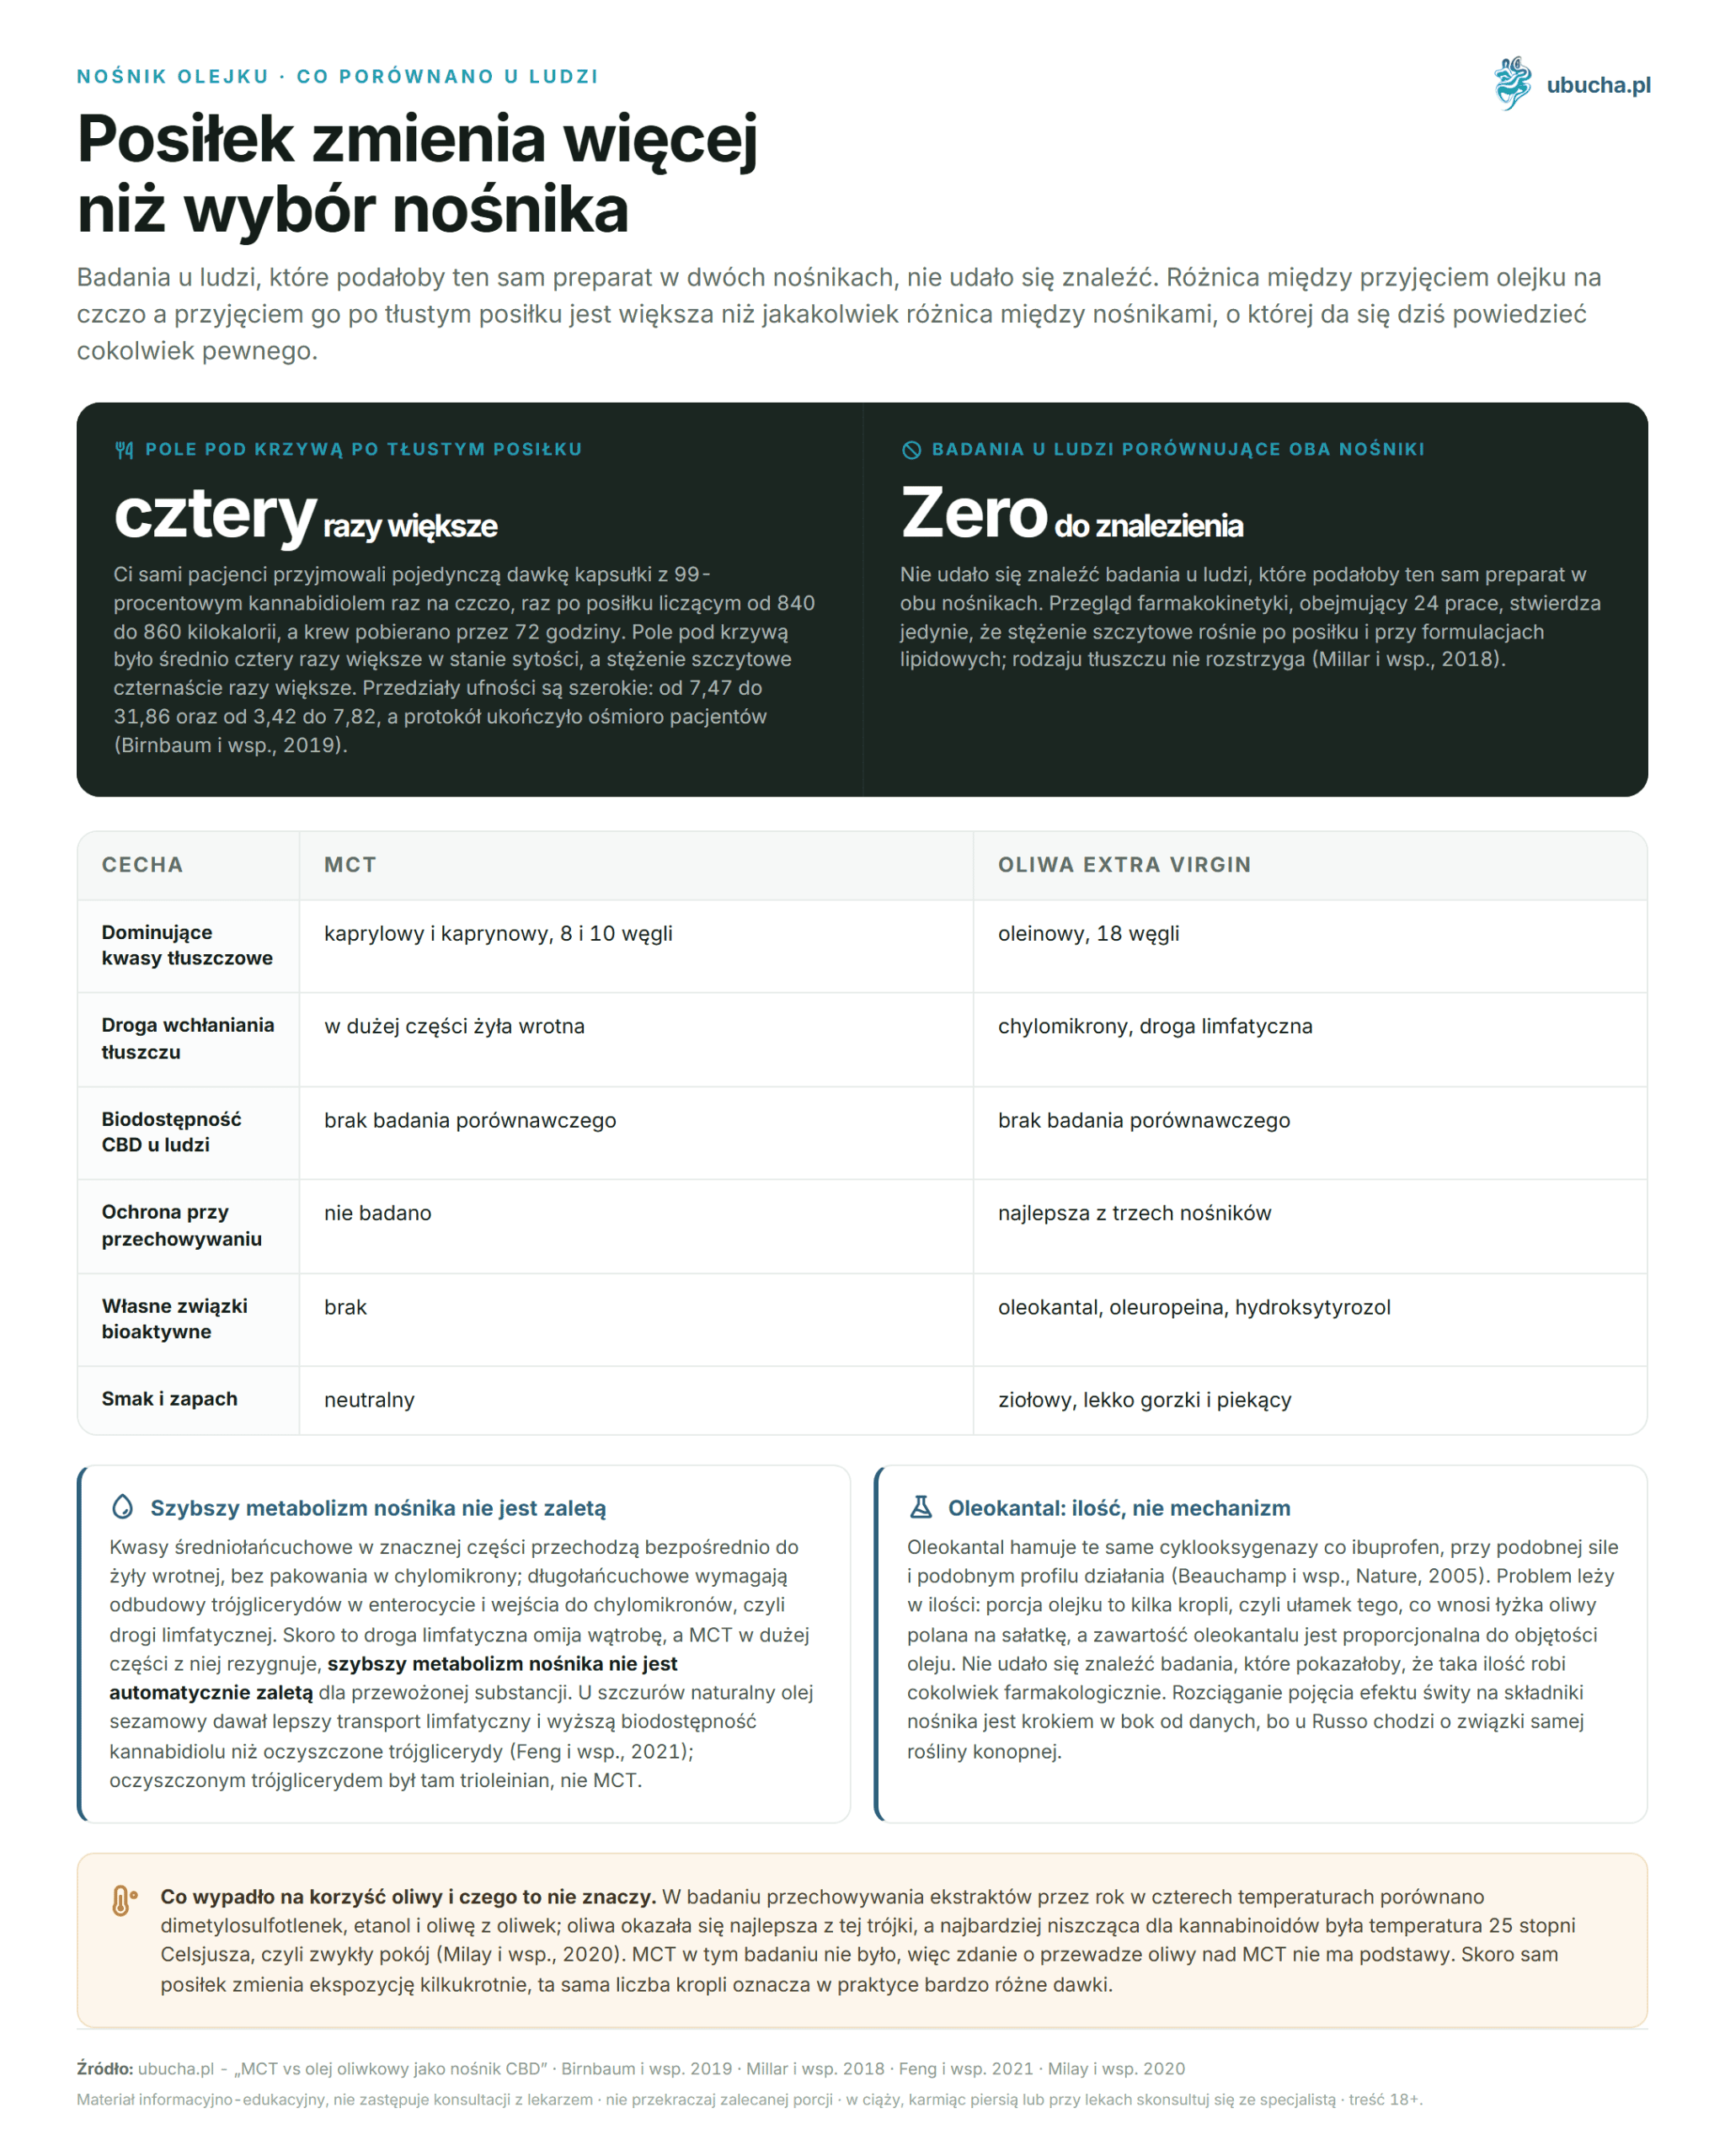
When buying CBD oil, you usually look at the percentage and price, treating the carrier as a filler. Meanwhile, it determines how much of the substance actually passes from the bottle into the blood. The scale is surprising: in patients who swallowed the same capsule once on an empty stomach and once after a fatty meal, the area under the concentration curve was four times greater, and the peak concentration was fourteen times higher (Birnbaum et al., Epilepsia, 2019). MCT and olive oil are the two most common carriers on the market. Below, we separate what has really been measured about them from what marketing has added. You will also find two research results that go against store comparisons, as well as an answer to the question of which decision practically changes the most.
KEY INFORMATION
• A fatty meal increased the area under the CBD curve fourfold and the peak concentration fourteenfold in 8 patients (Birnbaum et al., Epilepsia, 2019).
• No human study has been found that directly compared MCT with olive oil as a CBD carrier.
• In rats, natural sesame oil performed better than refined triglycerides in terms of lymphatic transport and bioavailability (Feng et al., 2021).
• Olive oil was the best of the three tested carriers for storing the extract (Milay et al., 2020).
Why does CBD need fat at all?
Because it is highly lipophilic and practically insoluble in water. In the intestinal content, a molecule without a fat coating cannot pass through the water layer at the intestinal wall, so it goes further and is excreted unused. Fat activates the normal digestive mechanism: bile and lipases form micelles, in which the substance is enclosed and delivered to enterocytes.
Part of the absorbed load goes into chylomicrons, which are lipoproteins that transport fats through the lymphatic vessels of the intestine. This route bypasses direct flow through the liver, and thus the first metabolism, which removes a large part of the dose before it reaches the systemic circulation. We describe the mechanism in more detail in the text about the first-pass effect.
The second layer is sublingual administration. Holding the oil under the tongue before swallowing allows part of the substance to pass through the oral vessels, bypassing the digestive tract, while the rest still goes the intestinal route along with the carrier. A review of the pharmacokinetics of CBD in humans gathered 24 studies and showed that peak concentration increases both after a meal and with lipid formulations (Millar et al., Frontiers in Pharmacology, 2018). A comparison of the routes of administration is described separately in the text about the bioavailability of CBD.
How much does a fatty meal increase CBD exposure?
Fourfold, counting total exposure. This was the result of a crossover study in adults with drug-resistant epilepsy who took a single dose of a capsule with 99 percent cannabidiol once on an empty stomach and once after a high-fat meal, ranging from 840 to 860 kilocalories. Blood was drawn for 72 hours after administration.
The results are worth remembering along with their limits. The area under the concentration curve was on average four times greater in a fed state, and the peak concentration was fourteen times greater. The confidence intervals are very wide: for peak concentration from 7.47 to 31.86, for the area under the curve from 3.42 to 7.82. The study included eight patients who completed the protocol, so it is a signal of high strength and low precision.
However, the practical conclusion is strong. The difference between taking the oil on an empty stomach and taking it after a fatty meal is greater than any difference between carriers that can be said with certainty today. The order of decisions should reflect this: first the timing of administration, then the type of oil. You can find more on this practical side in the text about whether to take CBD oil before or after eating.
How does MCT differ from olive oil in terms of absorption?
By chain length and the route by which fatty acids leave the intestine. MCTs are medium-chain triglycerides, practically a mixture of caprylic and capric acid, obtained from coconut oil or palm kernel oil through fractionation. Olive oil mainly consists of long-chain oleic acid.
Medium-chain fatty acids largely go directly to the portal vein, without being packed into chylomicrons. Long-chain fatty acids require the reconstruction of triglycerides in the enterocyte and entry into chylomicrons, i.e., the lymphatic route. This difference is well described for the fats themselves and is not a subject of dispute.
Note that overturns a popular conclusion. Since this lymphatic route bypasses the liver, and MCT largely forgoes it, a faster metabolism of the carrier is not automatically an advantage for the transported substance. A study on rats directly checked this direction: natural sesame oil provided better lymphatic transport and higher bioavailability of cannabidiol than refined triglycerides and pre-digested lipids (Feng et al., European Journal of Pharmaceutics and Biopharmaceutics, 2021). The refined triglyceride in this study was triolein, not MCT, so do not transfer the result directly. The conclusion that can be drawn from it is narrower and still uncomfortable: the mere fact that the carrier is a purified, isolated fraction, rather than a whole natural oil, has not proven to be an advantage. This is an animal model and does not directly concern either MCT or olive oil, but the direction is opposite to what product descriptions promise.
MCT or olive oil: what can be compared based on research?
The chemical structure, taste, stability, and accompanying composition can be compared. The bioavailability of cannabidiol cannot be compared because no human studies have been found that administered the same preparation in two carriers. The table below separates these two layers, and where data is lacking, it states so directly.
| Feature | MCT (C8/C10) | Extra virgin olive oil |
|---|---|---|
| Dominant fatty acids | Caprylic and capric, 8 and 10 carbons | Oleic, 18 carbons |
| Fat absorption route | Largely portal vein | Chylomicrons, lymphatic route |
| CBD bioavailability in humans | No comparative study | No comparative study |
| Animal data on lymphatic transport | Refined triglycerides performed worse than natural oil (rats) | Not directly studied |
| Protection of extract in storage | Not studied | Best of the three tested carriers |
| Own bioactive compounds | None | Oleocanthal, oleuropein, hydroxytyrosol |
| Taste and smell | Neutral | Herbaceous, slightly bitter and pungent |
| Susceptibility to oxidation | Low, saturated acids without double bonds | Low, one double bond in oleic acid |
Rows where one side states “no study” or “not studied” are the most important here. Store comparisons usually fill them with upward arrows on the MCT side, although there is no measurement behind them in humans. The mere fact that the carrier works is documented; the superiority of one over the other is not.
Does olive oil better protect the extract from degradation?
In the only study that could be found, yes. Milay’s team stored hemp extracts dissolved in three different carriers for a year, at four temperatures, and analyzed the cannabinoid and terpenoid profile every six months (Milay et al., Frontiers in Plant Science, 2020). Dimethyl sulfoxide, ethanol, and olive oil were compared.
Olive oil turned out to be the best of the three, and dimethyl sulfoxide the worst. The most destructive temperature for cannabinoids was 25 degrees Celsius, i.e., a normal room. Terpenoids lost concentration quickly in all variants, so coolness slows losses but does not stop them. Practically, this means that a bottle in a dark cupboard in a cool room will retain more than a bottle on a windowsill, regardless of the carrier. More about this in the text about how to store CBD oil.
However, the limitation of this result is significant and rarely mentioned. MCT was not included in this study, so the statement “olive oil protects the extract better than MCT” has no basis; only the statement “olive oil protects the extract better than ethanol and dimethyl sulfoxide” has a basis. The marketing claim of the exceptional stability of MCT as a carrier of hemp extract has also not been verified in any study that could be found.
Does oleocanthal from olive oil enhance the effect of CBD?
It is unknown, and the premise itself is weaker than it is presented. Oleocanthal is a polyphenol from fresh extra virgin olive oil, responsible for the burning sensation in the throat. A study published in Nature showed that it inhibits the same cyclooxygenases as ibuprofen, with similar strength and similar action profile (Beauchamp et al., Nature, 2005). Olive oil also carries oleuropein and hydroxytyrosol with antioxidant properties (Gorzynik-Debicka et al., International Journal of Molecular Sciences, 2018).
The problem lies in the quantity. A dose of oil is a few drops, which is a fraction of what a tablespoon of oil drizzled on a salad brings, and the amount of oleocanthal in the carrier is proportional to the volume of oil. No study has been found that shows that such an amount does anything pharmacologically. If you care about oleocanthal, the kitchen will provide it, not the dropper.
It is also worth being cautious with the word synergy. The entourage effect in its original formulation by Russo in 2011 was a conditionally formulated hypothesis, “if proven” (Russo, British Journal of Pharmacology, 2011); eight years later, the same author wrote that the arguments for synergy are sufficiently strong (Russo, Frontiers in Plant Science, 2019). However, both texts concern the interaction of compounds of the cannabis plant itself. Extending this concept to the components of the carrier is a step away from the data, not an extension of them.
Which carrier to choose and what does it really change?
Choose based on taste and whether you will use the preparation regularly, as these are the only differences supported by facts. MCT is practically tasteless, making it easier to endure daily sublingual administration. Extra virgin olive oil has a distinct herbal profile that some people like, while others stop using it after a week. A discontinued preparation does not work, so taste is not a trivial matter.
The remaining arguments are worth setting aside. A faster onset of action after MCT has not been measured in humans compared to olive oil. Higher bioavailability after MCT has also not been measured. The superiority of MCT’s stability over olive oil has not been verified, and the only data on storing the extract favored olive oil in comparison with laboratory solvents. Instead of choosing between carriers, you will gain more by taking the oil after a meal containing fat.
Finally, a boundary that manufacturers do not mention. Since the meal itself can change exposure several times, the same number of drops means very different doses in practice depending on the circumstances. The European Food Safety Authority in a position from 2026 derived a temporary safe dose of cannabidiol at the level of 0.0275 mg per kilogram of body weight per day, or about 2 mg for a person weighing 70 kg, and noted that safety cannot be established in individuals under 25 years of age, in pregnant and breastfeeding women, and in those taking medications (EFSA, 2026). You can find products available in the store in the oils category.
Frequently Asked Questions
Which CBD carrier provides higher bioavailability, MCT or olive oil?
It is unknown: no human study has been found that administered the same preparation in both carriers. A review of the pharmacokinetics of cannabidiol in humans only states that peak concentration increases after a meal and with lipid formulations (Millar et al., Frontiers in Pharmacology, 2018). The type of fat was not resolved in this review.
Does MCT work faster than olive oil?
Medium-chain fatty acids are absorbed faster than long-chain ones, and this is documented for the fats themselves. However, no one has measured the translation to a faster onset of action of cannabidiol in humans. In a study on rats, refined triglycerides performed worse than natural sesame oil in terms of lymphatic transport and bioavailability (Feng et al., 2021).
Should CBD oil be taken with food?
This changes more than the choice of carrier. In eight adults with drug-resistant epilepsy, the same capsule after a high-fat meal produced a fourfold greater area under the concentration curve and a fourteenfold higher peak concentration than when taken on an empty stomach (Birnbaum et al., Epilepsia, 2019). The confidence intervals were wide, and the group was small.
Does olive oil better protect the oil from spoilage?
In the only study comparing carriers of hemp extract that could be found, olive oil performed the best, but it was compared with ethanol and dimethyl sulfoxide, not with MCT (Milay et al., Frontiers in Plant Science, 2020). Regardless of the carrier, room temperature was the most harmful, and terpenoids decreased in all storage variants.
What other oils are used as CBD carriers?
Besides MCT and olive oil, you will find hemp seed oil, avocado oil, sesame oil, and sunflower oil. Hemp seed oil contains a lot of polyunsaturated fatty acids, so it oxidizes faster than monounsaturated and saturated carriers. Sesame oil is the only one on this list for which direct data on the lymphatic transport of cannabidiol has been found, and that from an animal model.
This article is for informational and educational purposes only and does not constitute medical advice. Before starting to use cannabis or CBD for therapeutic purposes, consult your doctor, especially if you are taking other medications, are pregnant, or breastfeeding.
Author: Michał Waluk · Published: 2026-08-09 · Updated: 2026-08-15