Bad trip after marijuana: what it is, symptoms and first aid

Bad trip after marijuana: how long it lasts, symptoms, and step-by-step help. What research really says about CBD, black pepper, and when to call 112.
The heart pounds, thoughts chase each other, the room feels alien. Twenty minutes after a strong drag, instead of relaxation, comes the conviction that something is wrong with the body or mind. This is what a bad trip after marijuana looks like, described in literature as an acute anxiety reaction or transient psychotic symptoms after THC. It is not a heart attack or permanent brain damage, though subjectively it can be the worst quarter of an hour in life. Below you will find what research shows: what happens in the body, how long it lasts, how to realistically help, why popular home remedies lack data support, and when to stop waiting and call for help.
KEY INFORMATION
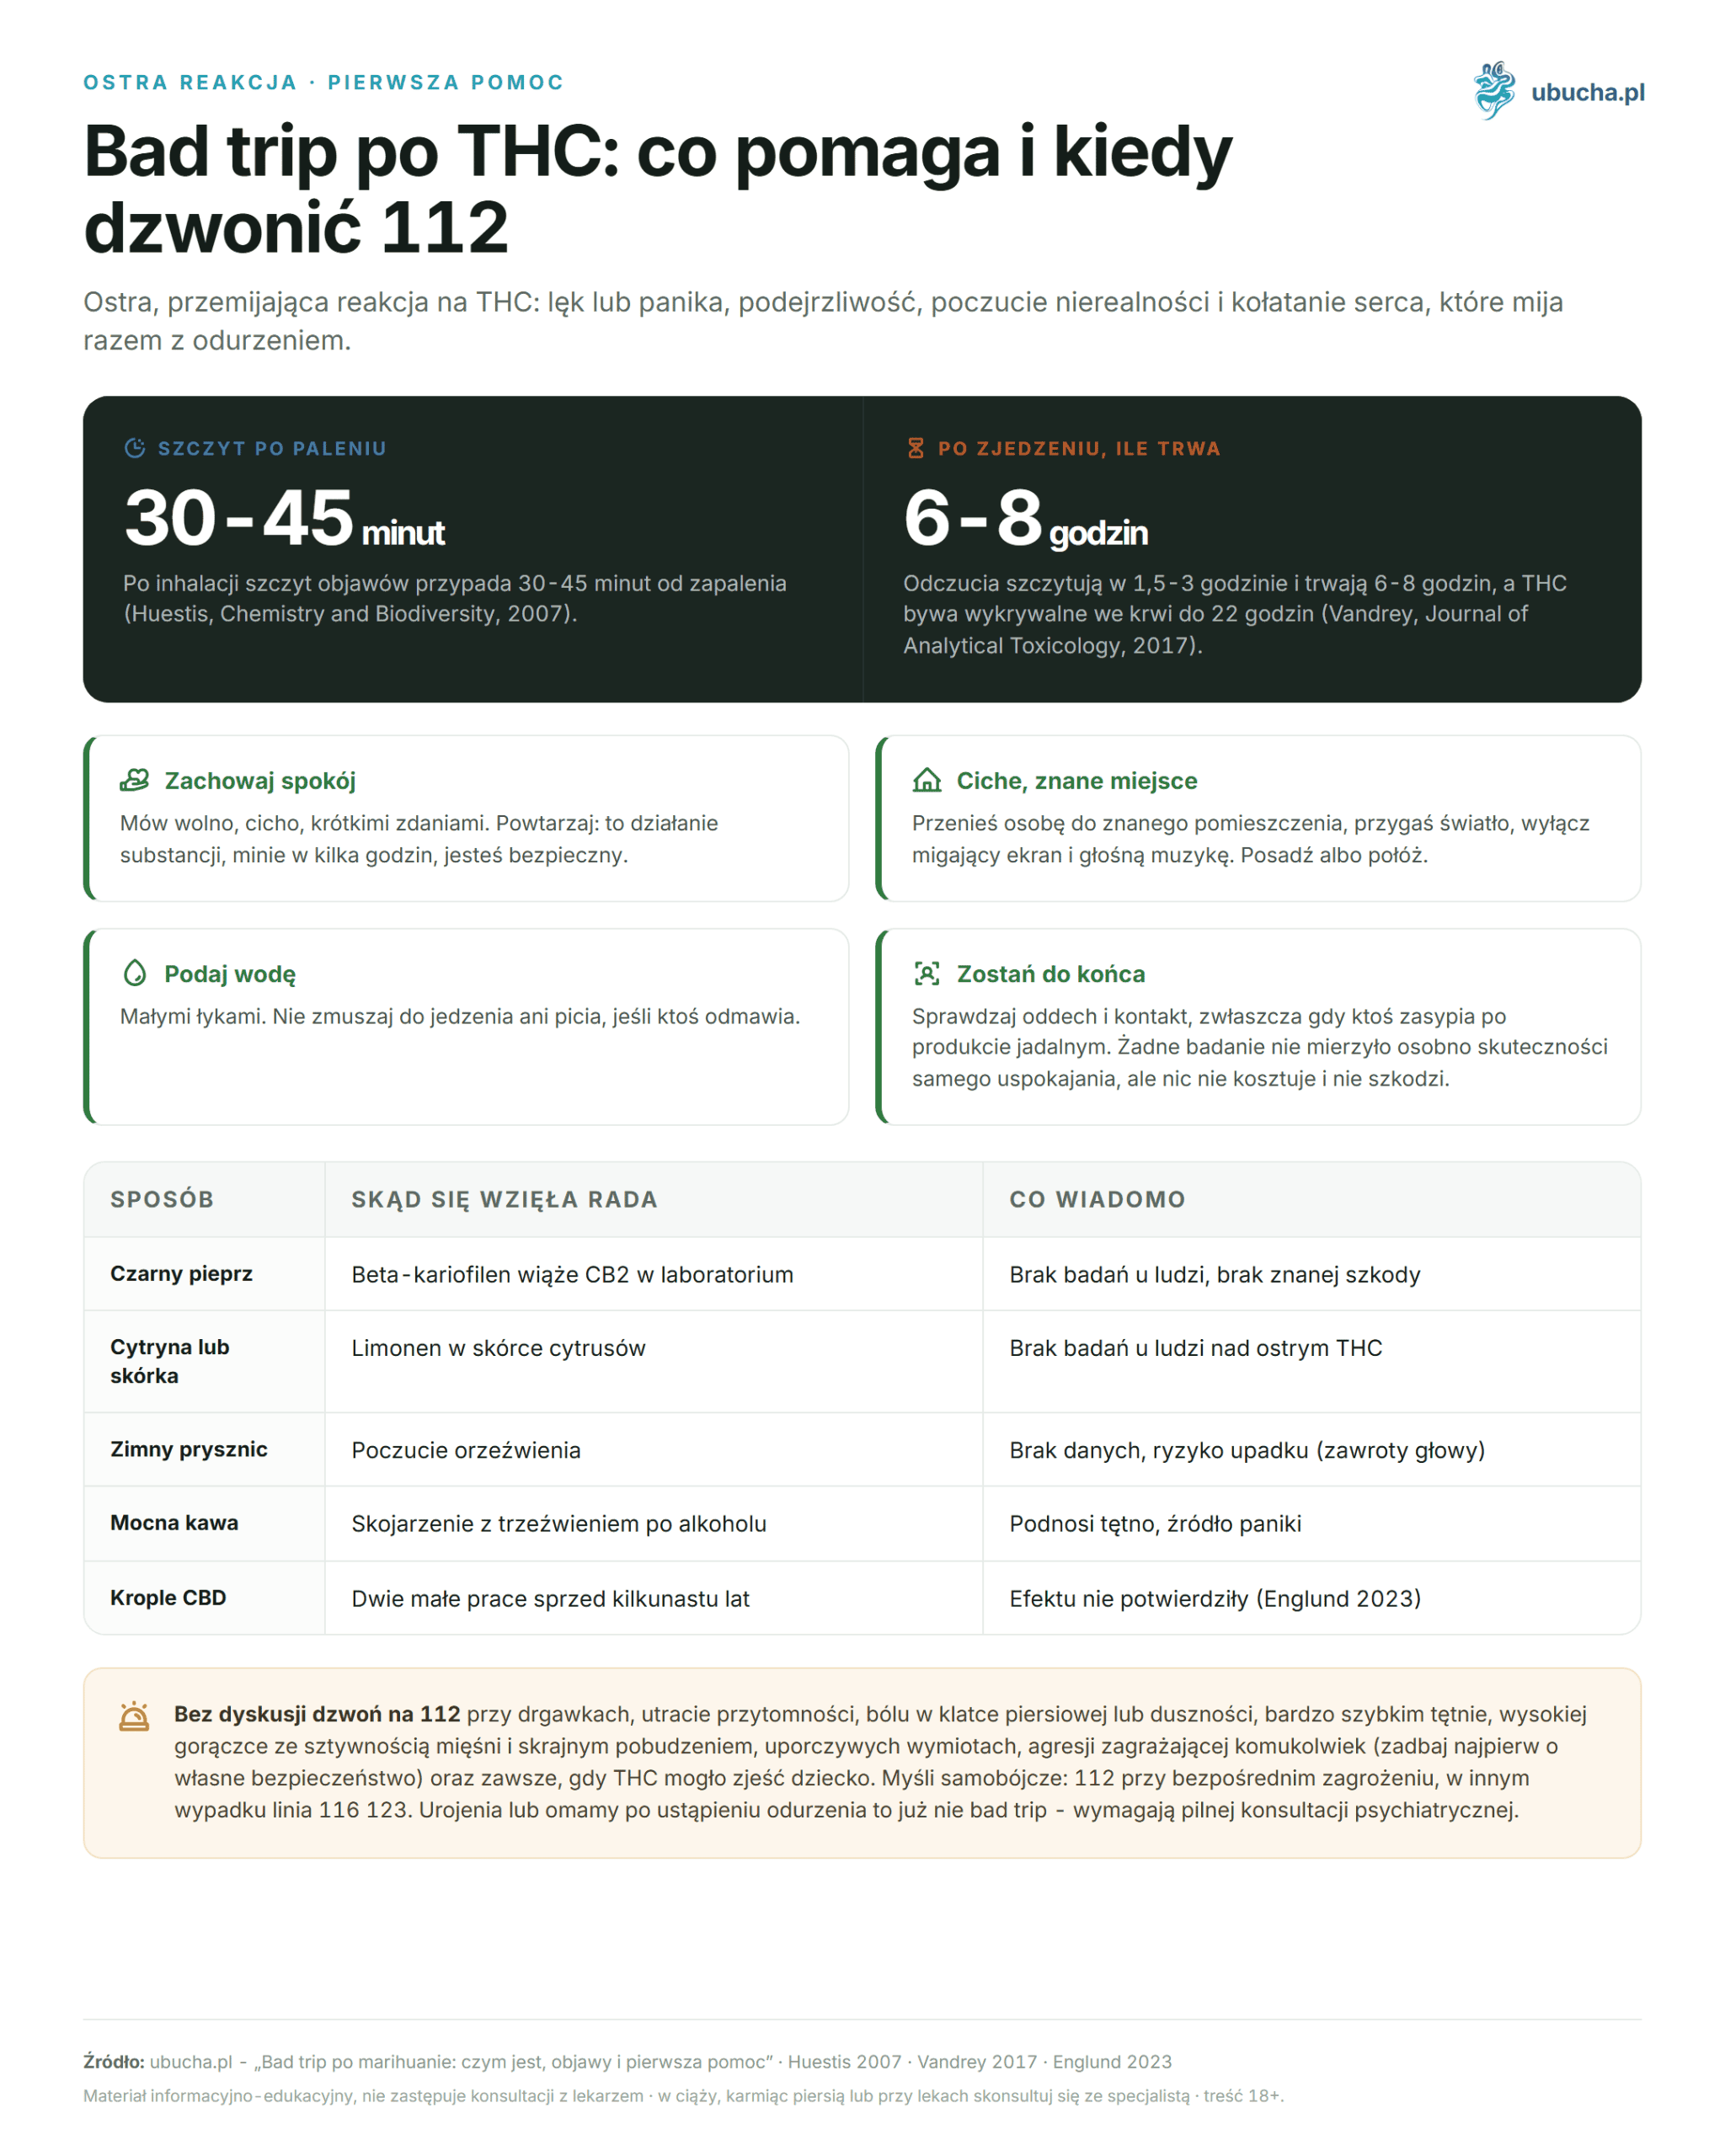
• Bad trip is an acute, transient episode of anxiety and paranoia after THC. After inhalation, the peak occurs 30-45 minutes after lighting, after ingestion sensations peak at 1.5-3 hours and last 6-8 hours.
• Intravenous THC caused transient symptoms resembling psychosis, altered perception, and increased anxiety in healthy volunteers (D’Souza, Neuropsychopharmacology, 2004).
• The thesis that CBD dampens acute THC effects has not been verified. Three newer trials with product-relevant CBD ratios showed no protective effect (Englund, Neuropsychopharmacology, 2023).
• Black pepper, lemon, and cold shower are advice without human studies. Time, calm, and a safe place work.
• Call 112 for seizures, loss of consciousness, chest pain, suicidal thoughts, and always if a child may have eaten THC.
What is a bad trip after marijuana?
A bad trip after marijuana is an acute, transient reaction to THC: anxiety or panic, suspicion bordering on paranoia, a feeling of unreality of surroundings, and bodily symptoms, primarily heart palpitations. ICD-11 classifies this phenomenon among mental disorders caused by cannabis use. The state passes as THC concentration in the brain decreases.
The strongest evidence that THC alone suffices to cause this picture comes from a Yale experiment. D’Souza’s team administered 0, 2.5, or 5 mg THC intravenously to 22 healthy people in a double-blind crossover design. THC caused transient positive and negative symptoms resembling schizophrenia, altered perception, increased anxiety, impairments in immediate and delayed word recall, and increased plasma cortisol (D’Souza, Neuropsychopharmacology, 2004). Participants were followed up at one, three, and six months.
A literature review by Crippa from the same center as later CBD studies states a simple and important fact: anxiety reactions and panic attacks are the most common acute symptoms linked to cannabis use (Crippa, Human Psychopharmacology, 2009). The same review notes that the exact relationship between cannabis and anxiety remains unclear, so any statement about a “dose threshold for bad trip” should be treated as simplification, not fact.
Unlike primary mental disorders, a bad trip can be distinguished by a simple time test. Its onset coincides with intoxication, course follows substance concentration, and it ends with substance elimination.
How does a bad trip differ from a panic attack?
The core symptoms are shared: fear without clear cause, rapid heart rate, sweating, trembling, conviction that something irreversible is about to happen. They differ in course and additions. A panic attack per DSM-5 builds rapidly, peaks around ten minutes, and usually subsides within an hour. A bad trip lasts hours.
The second difference is the set of sensations absent in a pure panic attack. Derealization, the feeling that the world is like behind glass. Depersonalization, the sense of observing one’s own body from outside. Paranoid theme, usually “they know and watch”. Distorted sense of time, where ten minutes feels like an hour.
The third difference concerns who ends up at the doctor. A narrative review of German emergency centers identifies acute cannabis intoxication as the most common hospital admission reason in this group, typically accompanied by acute anxiety and panic attacks (Eichhorn, Deutsches Ärzteblatt International, 2025). In Canada, hospital admissions related to cannabis doubled after legalization, from 15 per 100,000 in 2017 to 32 per 100,000 in 2022.
For the person experiencing it, the distinction matters practically. A panic attack can be “waited out” in minutes. A bad trip requires a plan for several hours, not a quarter hour, which usually disappoints most.
What psychological symptoms does a bad trip cause?
Psychological symptoms form four recurring patterns: anxiety reaching panic, suspicion and paranoia, a feeling of unreality of self or surroundings, and slowed, looping thinking with gaps in short-term memory. One pattern dominates in some, all four mix in others.
The paranoid theme is best studied. In the largest intravenous THC trial, 121 people prone to suspicious thinking were randomly given THC or placebo, and paranoia was measured in real social situations, virtual reality, and self-report scales. THC clearly increased paranoia, and mediation analysis showed this was due to increased negative affect and unusual experiences, not working memory impairment (Freeman, Schizophrenia Bulletin, 2015).
The same study has a result that spoils popular advice. A third group was warned what to expect from THC, hoping for a protective effect of knowledge. The impact of such preparation on paranoia was minimal. We noticed that in the Polish internet the phrase “just knowing it will pass” is still repeated. Knowledge helps make sensible decisions but does not switch off the symptom.
Visual or auditory hallucinations are rarer and usually distortions, not full hallucinations: walls seem to ripple, sounds echo. The boundary between such experiences and psychosis is described below in the section on lasting effects.
What bodily symptoms accompany a bad trip?
The body reacts to THC faster than the psyche and usually triggers panic. The heart accelerates, mouth dries, conjunctiva reddens, hands tremble, dizziness occurs, sometimes nausea. None of these symptoms is dangerous by itself in a healthy person, but each can be easily interpreted as the start of a heart attack.
The loop always looks the same. Accelerated pulse is read as a threat, fear raises pulse further, another measurement confirms the “diagnosis”. Breaking this loop involves naming it directly: this is the substance’s effect on the circulatory system, not a heart disease symptom. In D’Souza’s experiment, THC also raised cortisol, so the stress response is real and measurable, not imagined.
Dry mouth and red eyes result from effects on salivary glands and blood vessels. They pass on their own; water suffices.
Dizziness and unsteady gait can be more dangerous than anxiety itself, as they lead to falls. Stairs, bathtub, stove. Sitting or lying the person in a safe place solves most of this risk. Nausea and vomiting occur less often than anxiety, more often after edibles, and usually subside with other symptoms.
How long does a bad trip after marijuana last?
After inhalation, the peak occurs 30-45 minutes after lighting, and THC blood concentration drops fastest in the first two hours. After ingestion, everything shifts and lengthens: peak concentration occurs in the second or third hour, and sensations last 6 to 8 hours. The absorption route, not product strength, determines this.
Pharmacology of both routes is summarized by Huestis. After inhalation, THC appears in plasma immediately, peak effect is 30-45 minutes after lighting, and after two hours concentration falls below 5 ng/ml. After swallowing, absorption is slow and uneven, bioavailability is only 4-20%, and peak concentration appears 1-2 hours after ingestion (Huestis, Chemistry and Biodiversity, 2007). This explains the unpredictability of edibles.
Sensations were measured separately. Healthy adults, six per dose, were given cookies with 10, 25, or 50 mg THC: subjective effects and cognitive impairment peaked 1.5 to 3 hours after eating, lasted 6 to 8 hours, and THC was detectable in blood up to 22 hours (Vandrey, Journal of Analytical Toxicology, 2017).
| Route of administration | Onset | Peak | Duration |
|---|---|---|---|
| Smoking or vaporization | THC in plasma after first puff | 30-45 minutes after lighting | below 5 ng/ml in plasma after 2 hours |
| Edibles, 10 to 50 mg THC | peak concentration after 1-2 hours | sensations 1.5-3 hours | sensations 6-8 hours, THC in blood up to 22 hours |
Subjectively, each interval feels longer because THC distorts time perception. Tell the person you help: the watch shows less than it seems. More in the post about how long THC effects last.
Symptoms lasting longer than a day are rare and then cease to be a simple bad trip. Persistent anxiety may be a secondary reaction, fear of recurrence, not substance effect, which is no longer in the brain. Persistent delusions or hallucinations are a separate situation, described below.
It is also worth separating anxiety remission from functional recovery. After inhalation, THC blood concentration returns to baseline clearly earlier than effects subside (Spindle, Journal of Psychopharmacology, 2021). The feeling “I’m over it” precedes attention and reaction time recovery, enough reason not to drive that day.
Why do THC edibles cause the heaviest reactions?
The culprit is delay. After eating, nothing happens for half an hour or longer, so people add a second, sometimes a third portion. When everything kicks in at once in the second hour, the dose is many times higher than intended, and there is no turning back because absorption is ongoing.
The same mechanism is visible in poisoning statistics. The US poison control database recorded 7043 exposures to cannabis edibles in children under 6 from 2017-2021, with 207 cases in 2017 and 3054 in 2021, a 1375% increase (Tweet, Pediatrics, 2023). Adults were counted in Colorado: from 2014-2016 edibles accounted for 10.7% of cannabis-related emergency visits, though only 0.32% of sold THC, and visits after edibles more often involved acute psychiatric symptoms, 18.0% vs. 10.9% (Monte, Annals of Internal Medicine, 2019).
There is also the problem of dose per portion. Cookie, gummy, or chocolate do not divide evenly because fat and THC distribute unevenly in the dough. One piece may contain multiples of the neighboring one, even in a product with declared content.
The practical conclusion is boring but effective. After eating, wait at least two hours before judging the effect, and do not add anything in that time. If “nothing happens for half an hour,” it means the dose hasn’t arrived yet, not that it is absent.
What happens in the brain during a bad trip?
THC is a partial agonist of CB1 receptors, the most numerous metabotropic receptors in the brain, especially dense in the prefrontal cortex, hippocampus, amygdala, and striatum. These areas are responsible for threat assessment, short-term memory, and assigning significance to stimuli. Disruption of their signaling simultaneously produces exactly the picture described as a bad trip.
Functional imaging shows this directly. Fifteen healthy men with minimal prior cannabis exposure were given oral THC, CBD, or placebo and scanned during memory tasks, response inhibition, speech listening, and viewing fearful faces. THC and CBD produced opposite activation patterns in the striatum, hippocampus, amygdala, temporal and occipital cortex (Bhattacharyya, Neuropsychopharmacology, 2010).
An important detail rarely mentioned when citing this work: the part concerning CBD’s protective effect involved six people. Six. Enough to hypothesize, but far too few to base a first aid guide on. We return to this in the CBD section.
Why does the same substance sometimes calm and sometimes frighten? The answer, agreed upon by most authors, concerns dose and baseline state. At low limbic activation, CB1 modulation calms; at high, it amplifies threat signals. The same joint on a calm evening and after a hard day are pharmacologically two different situations.
Is marijuana stronger today than before?
Yes, more than the percentage alone suggests. Analysis of 38,681 samples seized by the US DEA from 1995-2014 showed average THC content rising from about 4% to about 12%, with CBD content dropping from about 0.28% in 2001 to below 0.15% in 2014 (ElSohly, Biological Psychiatry, 2016).
The most interesting aspect is not strength itself but ratio. The THC to CBD ratio changed from fourteenfold to about eightyfold in this period. The material today’s user reaches for is chemically a different plant than that of the 1990s, not just a stronger version of the same.
A newer analysis by the same team covering 2013-2022 adds that the cannabinoid profile of strong samples looks similar regardless of region: THC dominates above 10%, other cannabinoids fall below 0.5%, except CBG and CBN, which do not exceed 1% (ElSohly, Frontiers in Public Health, 2024).
For someone returning to smoking after years, this has a concrete consequence. Memory recalls the dose from a decade ago, but the material corresponds to today’s strength. This is one of the most common scenarios leading to a first bad trip after a long break.
Who is most at risk of a bad trip?
The highest risk is for people without tolerance: beginners and those returning after a long break. Next are people with anxiety or suspicious thinking tendencies, those with family psychosis history, and anyone using a product of unknown strength. Dose alone is rarely the only factor.
Freeman’s study selects participants based on paranoia tendency and shows THC reliably induces this symptom in such people. This is the best available argument that prior anxiety or suspicion tendency is not folklore but a measurable risk factor.
Age is often presented more simply than data show. Long-term effects of cannabis use during adolescence are well documented and include addiction risk and psychosocial development impact (Hall and Degenhardt, Lancet, 2009). Acute reaction is a different question, and the answer surprises.
In a London experiment, 24 teenagers aged 16-17 and 24 adults aged 26-29 were given the same weight-adjusted dose of vaporized cannabis. Teenagers did not react stronger or weaker than adults to psychotic symptoms, memory impairment, or subjective effects, and Bayesian analysis supported equivalence (Lawn, Addiction, 2023). The argument against adolescent cannabis use is thus strong but based on long-term effects, not acute sensitivity.
Do women react differently to THC than men?
Partially yes, but not as the internet repeats. A meta-analysis of four double-blind studies included 35 men and 35 women matched by cannabis use frequency. Women rated effects related to addiction potential higher, i.e. “want to repeat” and “good,” but intoxication ratings did not differ by sex, and heart rate rose equally (Cooper and Haney, Drug and Alcohol Dependence, 2014).
The popular thesis of increased THC sensitivity in the luteal phase is attributed to this work. It is not there. Searches in Europe PMC found no human study measuring acute anxiety risk after THC by cycle phase. This does not mean such a relationship does not exist, only that there is no evidence today.
Practically, the conclusion is more modest. Sex influences how pleasant the experience seems and how quickly use problems develop, less so whether a single session ends in panic. Dose, tolerance, and pre-session mental state matter more.
A separate issue is pregnancy and breastfeeding. THC crosses the placenta and passes into milk, and obstetric societies consistently advise against cannabis use during this period. This recommendation does not depend on whether someone ever had a bad trip.
How to help someone having a bad trip?
First aid boils down to four things. Keep your own calm. Move the person to a quiet, familiar place. Give water. Stay with them until the episode ends. There is no home remedy that shortens THC action. Your task is to guide someone through several hours without injury or escalation, not to reverse pharmacology.
It is good to know what hospitals have to offer, so you don’t try this at home. A German emergency department review lists fluid replacement as the basis for severe vomiting and benzodiazepines and antipsychotics as symptomatic treatment (Eichhorn, Deutsches Ärzteblatt International, 2025). These are tools given under supervision after assessment, not from someone else’s medicine cabinet.
- Speak slowly, quietly, in short sentences. Repeat the same: this is the substance’s effect, it will pass in a few hours, you are safe.
- Move the person to a known, quiet room. Dim lights, turn off flashing screens and loud music.
- Sit or lie them down. Most injuries during a bad trip come from falls, not THC itself.
- Give water in small sips. Do not force eating or drinking if refused.
- Stay until the end. Check breathing and contact, especially if the person falls asleep after an edible.
- Watch for alarm signs below. Call 112 without discussion at any of them.
There is no controlled study measuring the effectiveness of calming alone in acute cannabis intoxication. We recommend it because it costs nothing and cannot harm, not because it is proven. Honest framing is more important here than promise.
What to do for specific bad trip symptoms?
The same scheme works for every symptom: fewer stimuli, calm contact, and patience. Differences are in details, so the table below breaks them down by symptom, with a separate column for harmful behaviors. In crisis, no one reads long texts, so save it on your phone before needed.
| Symptom | What helps | What to avoid |
|---|---|---|
| Anxiety and panic | calm, low voice; phrase “you are safe, it will pass”; slow breathing together | raising voice, asking “what did you take”, own panic |
| Paranoia | familiar, private place; fewer stimuli; one trusted person nearby | crowds, whispering near the person, mocking their fears |
| Disorientation | simple tactile stimuli; naming surroundings aloud; questions instead of commands | sudden location changes, harsh light, leaving alone |
| Perceptual distortions | calm acknowledgment of experience; naming it as substance effect; patient presence | confirming experience is real, new stimuli |
| Physical agitation | sitting or lying position; cool compress; water in small sips | coffee and stimulants, forcing movement, phone screen |
The column of behaviors to avoid is not about manners. It is based on an online survey of 1993 people describing their hardest psilocybin mushroom experience. The numbers describe psilocybin, not THC, and are cited only for what they say about the environment. During that episode, 11% of respondents endangered themselves or others physically, and 2.6% behaved aggressively or violently (Carbonaro, Journal of Psychopharmacology, 2016). Injury risk rose with dose and episode duration, and fell with physical comfort and support. Comfort and presence of another person reduced injury risk; their absence increased it. The listed behaviors remove both and are collected on this basis, as the survey did not measure crowd or raised voice effects.
If the person stops responding, loses consciousness, or has seizures, the table no longer applies and you call 112 without delay.
What not to do during a bad trip?
The list of harmful things is shorter than helpful ones but more important. The worst ideas are adding another substance, leaving someone alone, and trying to “sober them up” forcibly. Each either worsens symptoms or adds injury risk.
- Do not give alcohol. It worsens disorientation, increases nausea, and raises choking risk if the person falls asleep.
- Do not add THC “to sleep it off.” Absorption of what is already taken continues, and another dose prolongs the episode.
- Do not give caffeine. It raises heart rate, which usually drives panic.
- Do not take someone else’s benzodiazepines. This is hospital treatment after assessment, not home first aid.
- Do not leave the person alone in a bathtub or shower. Dizziness and balance disturbance pose real drowning risk.
- Do not let them drive a car or bike, even after anxiety subsides. Attention impairment lasts longer than the subjective feeling “I’m over it.”
- Do not ridicule or scare. Shame intensifies paranoia and discourages asking for help when truly needed.
One point rarely considered at night: if the material came from an unknown source, synthetic cannabinoids may be involved, causing heavier and less predictable courses than THC alone. With atypical strong agitation, muscle rigidity, or fever, assume it is not ordinary cannabis intoxication and call for help.
Does CBD alleviate acute THC effects?
Most likely not under conditions people try to use it. The thesis of CBD as a “safety” for THC is based on two small studies from over a decade ago, and three newer, larger trials did not confirm it. None studied CBD given during an ongoing episode.
The table below shows the source of discrepancy. Positive results come from very high oral doses given hours before THC. Negative results come from CBD:THC ratios actually found in products.
| Study | What was given | Participants | Result |
|---|---|---|---|
| Bhattacharyya 2010 | CBD before intravenous THC | 6 people in sub-study | CBD prevented acute psychotic symptoms |
| Englund 2013 | 600 mg oral CBD 210 minutes before 1.5 mg intravenous THC | 48 people, between-groups design | fewer clinically significant episodes and less paranoia; PANSS scale difference not statistically significant |
| Haney 2016 | CBD 0, 200, 400, 800 mg orally 90 minutes before smoking | 31 regular smokers | no effect on sensations, heart rate, or desire to repeat |
| Lawn 2023 | 8 mg THC with 24 mg CBD in vaporizer | 24 teenagers and 24 adults | no CBD effect on memory, psychotic symptoms, or sensations |
| Englund 2023 | 10 mg THC with 0, 10, 20, or 30 mg CBD in vaporizer | 46 infrequent users | no effect on memory, PANSS, sensations, or physiological parameters |
The 2023 authors conclude bluntly: at CBD:THC ratios most common in medical and recreational products, there is no evidence that CBD protects against acute adverse cannabis effects (Englund, Neuropsychopharmacology, 2023). The same group found no CBD effect on attention to cannabis stimuli (Oliver, Addiction, 2024).
Why do CBD study results differ so much?
The discrepancy is not because some researchers erred. It arises from three experimental design differences: CBD dose, interval between CBD and THC, and administration route of both substances. When these approach typical user conditions, the effect disappears.
The positive signal comes from Englund 2013. Participants received 600 mg oral CBD 210 minutes before 1.5 mg intravenous THC. Clinically significant positive symptom severity was less in the CBD group, paranoia measured by SSPS was lower, and episodic memory was better than placebo. The PANSS scale difference was not statistically significant, and the study had a between-groups design with 22 and 26 people (Englund, Journal of Psychopharmacology, 2013).
Now comparison. Six hundred milligrams is a dose equivalent to several dozen milliliters of typical oil, taken over three hours earlier. Negative trials gave CBD together with THC, in amounts from 10 to 30 mg, as found in products and used by people. None of the five studies tested home situations, i.e. CBD taken during an ongoing episode.
What does this mean for someone with oil in a drawer? Several dozen milligrams of sublingual CBD during an episode is an intervention without studied effect, though also without known risk. If someone uses it, they should not delay any effective steps: calm, safe place, and calling for help if alarm signs appear. More about preparations is in the hemp oils category and the post on CBD and THC in anxiety states.
Does black pepper help with a bad trip?
It is folklore, not a method. Beta-caryophyllene in black pepper binds CB2 in lab studies and is the only basis for the advice. No human study on pepper’s effect on anxiety or paranoia after THC was found in Europe PMC. Smelling it won’t harm but does nothing.
The problem with such advice is not that it is harmful itself. It is that it displaces effective actions and gives an illusion of control. Someone looking for pepper in the kitchen is not sitting the friend in a safe place or checking for alarm signs.
| Popular advice | Origin | What is known |
|---|---|---|
| Smell black pepper | beta-caryophyllene binds CB2 in lab studies | no human studies, no known harm |
| Eat lemon or peel | presence of limonene in peel | no human studies on acute THC effects |
| Cold shower | feeling refreshed | no data; fall risk with dizziness |
| Strong coffee | association with sobering from alcohol | caffeine raises heart rate, main panic source |
| Sleep it off | sleep shortens subjective episode time | reasonable if someone watches nearby |
| A few drops of CBD | studies from 2010 and 2013 | newer trials did not confirm effect, see above section |
One advice in this family has a counterpart in literature, but in a completely different place. Persistent, unusual bathing is a described symptom of cannabinoid hyperemesis syndrome, a different disease than bad trip, not a way to acute THC anxiety.
When to call emergency after marijuana?
Most episodes pass without a doctor, but there is a list of situations when you do not wait. The emergency number is 112, active 24/7, also from phones without SIM cards. Fear of legal consequences is not a reason not to call, as saving life has priority.
| Alarm sign | What to do |
|---|---|
| Seizures | 112 immediately, protect head, do not put anything in mouth |
| Loss of consciousness or difficulty waking | 112, place in recovery position, monitor breathing |
| Chest pain or shortness of breath | 112, do not wait for intoxication to subside |
| Very fast pulse that does not slow | 112, especially with heart disease history |
| Suicidal or self-harm thoughts | 112 if immediate threat, otherwise 116 123 |
| Aggression threatening anyone | 112, ensure your own safety first |
| Persistent vomiting and dehydration | 112 or emergency room, fluid replacement is key |
| High fever, rigidity, extreme agitation | 112, atypical for THC alone, indicates other cause |
| Delusions or hallucinations after intoxication | urgent psychiatric consultation, psychiatric emergency room |
| Suspected child ingestion of THC product | 112 always, even if child looks well |
In a mental crisis without immediate life threat, free 24/7 hotlines operate: 116 123 for adults and 116 111 for children and youth.
Accelerated pulse alone in a healthy person is not an ambulance indication. Chest pain is, regardless of age, as differentiating angina cause is not a task for someone panicking on the couch.
What is cannabinoid hyperemesis syndrome?
It is cyclic, persistent vomiting in people using cannabis daily for years, completely different from a bad trip. It does not start after one session but after months or years. Instead of anxiety, nausea, vomiting, and abdominal pain dominate, plus an unusual, persistent need to bathe.
The syndrome was first described in South Australia. Of 19 identified patients, nine detailed cases were presented. All had chronic cannabis use preceding vomiting onset; in seven, cessation ended the illness; those who resumed smoking relapsed. Nine out of ten showed unusual bathing behavior during attacks (Allen, Gut, 2004).
The paradox is that THC is antiemetic, yet long-term use can cause the opposite picture. The mechanism remains unexplained. Practically, something else matters: attacks recur until cannabis is stopped, regardless of symptomatic treatment.
Diagnosis is made by a doctor after excluding other causes, including obstruction, ulcer disease, and pancreatitis. Emergency treatment is fluid replacement for often large losses, and symptomatic treatment is individualized. If vomiting recurs cyclically for months, it is not a home remedy matter but diagnostic. The post on cannabis withdrawal course is also helpful.
What to do if a child eats THC edibles?
Call 112 immediately, do not wait for symptoms or induce vomiting. Take the packaging or remaining product so the team knows the dose. A child who looked well moments ago may become sleepy and hard to wake within the next hour.
The phenomenon grows faster than any other cannabis-related problem. The US poison control database recorded 7043 exposures of children under 6 to cannabis edibles from 2017-2021, rising from 207 cases annually to 3054. Almost all, 97.7%, occurred at home. In 70% of cases with known outcome, central nervous system depression was described, and 22.7% of children were hospitalized (Tweet, Pediatrics, 2023).
Symptoms in small children differ from adults. Instead of anxiety and paranoia, there is sleepiness, difficulty waking, unsteady gait, nausea, and vomiting; at higher doses, respiratory depression and seizures are real risks (Zwiebel, Canadian Family Physician, 2025). Thus, “wait and see” is the worst decision.
Prevention boils down to one sentence: THC products look like sweets, so must be stored like medicines. Locked cabinet, original packaging, out of reach and sight. Handling and prevention recommendations are collected in a separate clinical paper (Ricchezza, Journal of Pediatric Pharmacology and Therapeutics, 2025). Practical storage solutions are in the storage category.
Can a bad trip cause permanent psychosis?
A single episode almost always ends with intoxication and leaves no trace. Psychosis risk relates not to a one-time bad reaction but to use pattern: frequency and strength. Symptoms lasting after intoxication are a different situation requiring urgent psychiatric consultation.
The best data come from the European EU-GEI study, including 901 people with first psychosis episode and 1237 controls in eleven centers in Europe and Brazil. Daily cannabis use was associated with odds ratio 3.2 vs. never users, and daily use of strains with THC content 10%+ with odds ratio 4.8. If strong strains disappeared from the market, authors estimate 12.2% of first psychosis episodes in studied centers could be prevented, much more in London and Amsterdam (Di Forti, Lancet Psychiatry, 2019).
These numbers concern habit, not a single evening. A person who once had hours of anxiety after a too-strong joint is not automatically in this risk group. A person smoking strong herb daily for years is.
Family history requires special vigilance. If schizophrenia or other psychotic disorder occurred in close family, intense THC reaction may be the first signal not worth explaining solely by substance. Psychiatrist visit is not admission but reasonable check.
How to reduce bad trip risk?
Effective prevention is based on four things: low initial dose, patience with edibles, knowing material origin, and avoiding mixing substances. No supplement or trick is among them, as none is confirmed in human studies.
The rule “start low, go slow” sounds banal until compared with material strength data. Since average THC tripled in two decades and CBD dropped, the dose remembered from the past ceases to be a reference point. One puff and fifteen minutes break gives real feedback; two joints in a row give none.
For edibles, one rule applies: wait two hours before judging effect. This is the most common mistake and easiest to fix without sacrifice.
We noticed that guides still recommend “take CBD oil just in case.” After reading five trials above, this is hard to maintain as protection. CBD has its own uses and safety profile but is not insurance allowing higher THC dose. Treating it so raises risk instead of lowering it.
What remains is context you cannot buy. Known place, known company, no time pressure, and no heavy day behind. Since paranoia arises from negative affect, as Freeman’s analysis showed, entering a session in a bad mood is a real risk factor, not superstition.
What is the legal status of marijuana in Poland?
Cannabis with a sum of delta-9-THC and tetrahydrocannabinolic acid (THCA) exceeding 0.3% dry weight is classified in Poland as cannabis other than fiber and subject to the Act of July 29, 2005 on counteracting drug addiction. Possession is a crime. Herb and oils within this threshold are legal and available without prescription; medical marijuana requires a prescription.
The threshold is the sum of both compounds, rounded to one decimal place, and this distinction determines lab test results. Based on Art. 4 point 5 of the Act as amended by the March 24, 2022 Act, Journal of Laws 2022 item 763, effective May 7, 2022; the consolidated text is Journal of Laws 2023 item 1939. EU law allows the same value from January 1, 2023, but these are two separate regulations with convergent thresholds, not one derived from the other. Article 62a allows case dismissal for small amounts for personal use, though practice varies.
This section is not an addendum to the first aid text but part of it. Fear of legal consequences realistically deters people from calling for help, and then a simple transient episode may end in injury or missing a real threat. Medical personnel are bound by professional secrecy, and life-threatening situations prioritize saving life unconditionally.
Medical marijuana has been available on prescription in Poland since November 1, 2017, under the July 7, 2017 amendment (Journal of Laws 2017 item 1458), with indications assessed by a doctor. Standardized THC content reduces accidental overdose risk but does not eliminate it, so patients exceeding recommended dose may experience exactly the same as recreational users. Details are in the post on medical marijuana.
A separate issue is driving. Driving under THC influence is prosecuted in Poland regardless of prescription origin and subjective sobriety. After a bad trip, this limit is confusing, as anxiety passes faster than attention and reaction time impairments.
Summary
A bad trip after marijuana is unpleasant and predictable in course. It starts with intoxication, peaks 30-45 minutes after lighting or in the second to third hour after eating, and fades with THC concentration drop. Nothing you do at home shortens this process. You can make it pass without injury and without turning anxiety into hours-long panic.
The biggest change from what is read online concerns CBD. Two small studies over a decade ago showed a protective signal at very high oral doses given in advance, while three newer, larger trials found no effect at product-relevant ratios. Black pepper, lemon, and cold shower have no such backing. This knowledge is convenient, as it frees from searching for remedies and shifts attention to what really helps: a quiet room, water, someone nearby, and time.
Separately, keep in mind three things that are not bad trips and require a doctor. Cyclic vomiting in long-term smokers, i.e. cannabinoid hyperemesis syndrome. Psychotic symptoms persisting after intoxication. And accidental child ingestion of THC product, where the only correct reaction is immediate 112 call. In other alarm situations, the same rule applies: better to call unnecessarily than too late.
Frequently Asked Questions
What is a bad trip after marijuana?
Bad trip after marijuana, also written as badtrip, is an acute, transient reaction to THC: anxiety or panic, suspicion, feeling of unreality, and heart palpitations. ICD-11 classifies it among disorders caused by cannabis use. Symptoms start with intoxication and pass with it, usually within a few hours, without lasting consequences.
How long does a bad trip after marijuana last?
After inhalation, the peak effect occurs 30-45 minutes after starting smoking, and THC concentration in plasma drops below 5 ng/ml within two hours (Huestis, Chemistry and Biodiversity, 2007). After eating 10 to 50 mg THC, sensations peaked at 1.5 to 3 hours and lasted 6 to 8 hours (Vandrey, Journal of Analytical Toxicology, 2017).
Does CBD alleviate a bad trip from THC?
Probably not. One small 2013 study showed a protective signal after 600 mg CBD given several hours before THC. Three newer trials with CBD ratios found in products showed no effect (Englund, Neuropsychopharmacology, 2023). No one has studied CBD given during an ongoing episode.
Does black pepper help with a bad trip?
This is internet folklore. Beta-caryophyllene from pepper binds the CB2 receptor in lab studies, but there is no human study in the Europe PMC database on pepper and acute THC effects. Smelling pepper won’t harm anyone, but it doesn’t replace calm, a safe place, and the passage of time.
When should you call emergency services during a bad trip?
Call 112 for seizures, loss of consciousness, chest pain, very fast and persistent pulse, suicidal thoughts, aggression, and uncontrollable vomiting. Also call when psychotic symptoms persist after intoxication subsides. Always call if a child is suspected to have ingested THC.
What to do if a child eats THC edibles?
Call 112 immediately, do not wait for symptoms and do not induce vomiting. Take the packaging so the team knows the dose. The US poison control database recorded 7043 exposures of children under 6 years old from 2017-2021, with 22.7% hospitalized (Tweet, Pediatrics, 2023).
What is cannabinoid hyperemesis syndrome?
It is cyclic, persistent vomiting in people who have smoked cannabis daily for years, first described in 2004. It differs from a bad trip by development time, predominance of vomiting over anxiety, and persistent bathing behavior. Symptoms resolve only after cannabis cessation (Allen, Gut, 2004).
Can a bad trip cause permanent psychosis?
A single episode almost always passes with intoxication. Risk relates to usage pattern: daily smoking of strong strains was associated with nearly fivefold higher odds of psychotic disorder in the EU-GEI study (Di Forti, Lancet Psychiatry, 2019). Symptoms persisting after intoxication require urgent psychiatric consultation.
If you are looking for legal hemp-derived products without intoxicating effects, see the hemp oils category.
This article is informational and educational and does not constitute legal advice. The legal status described applies as of publication date: cannabis regulations may change. Consult a lawyer or current legal acts before decisions. In health emergencies, call 112. Smoking any plant substance harms respiratory tracts.
Author: Michał Waluk · Published: 2026-05-06 · Updated: 2026-09-22