
Ashwagandha and libido: what exactly do scientific studies show
Five studies with placebo measured the impact of ashwagandha on sexual functions. How many people, how long, what was found in women and men, and who paid for it.
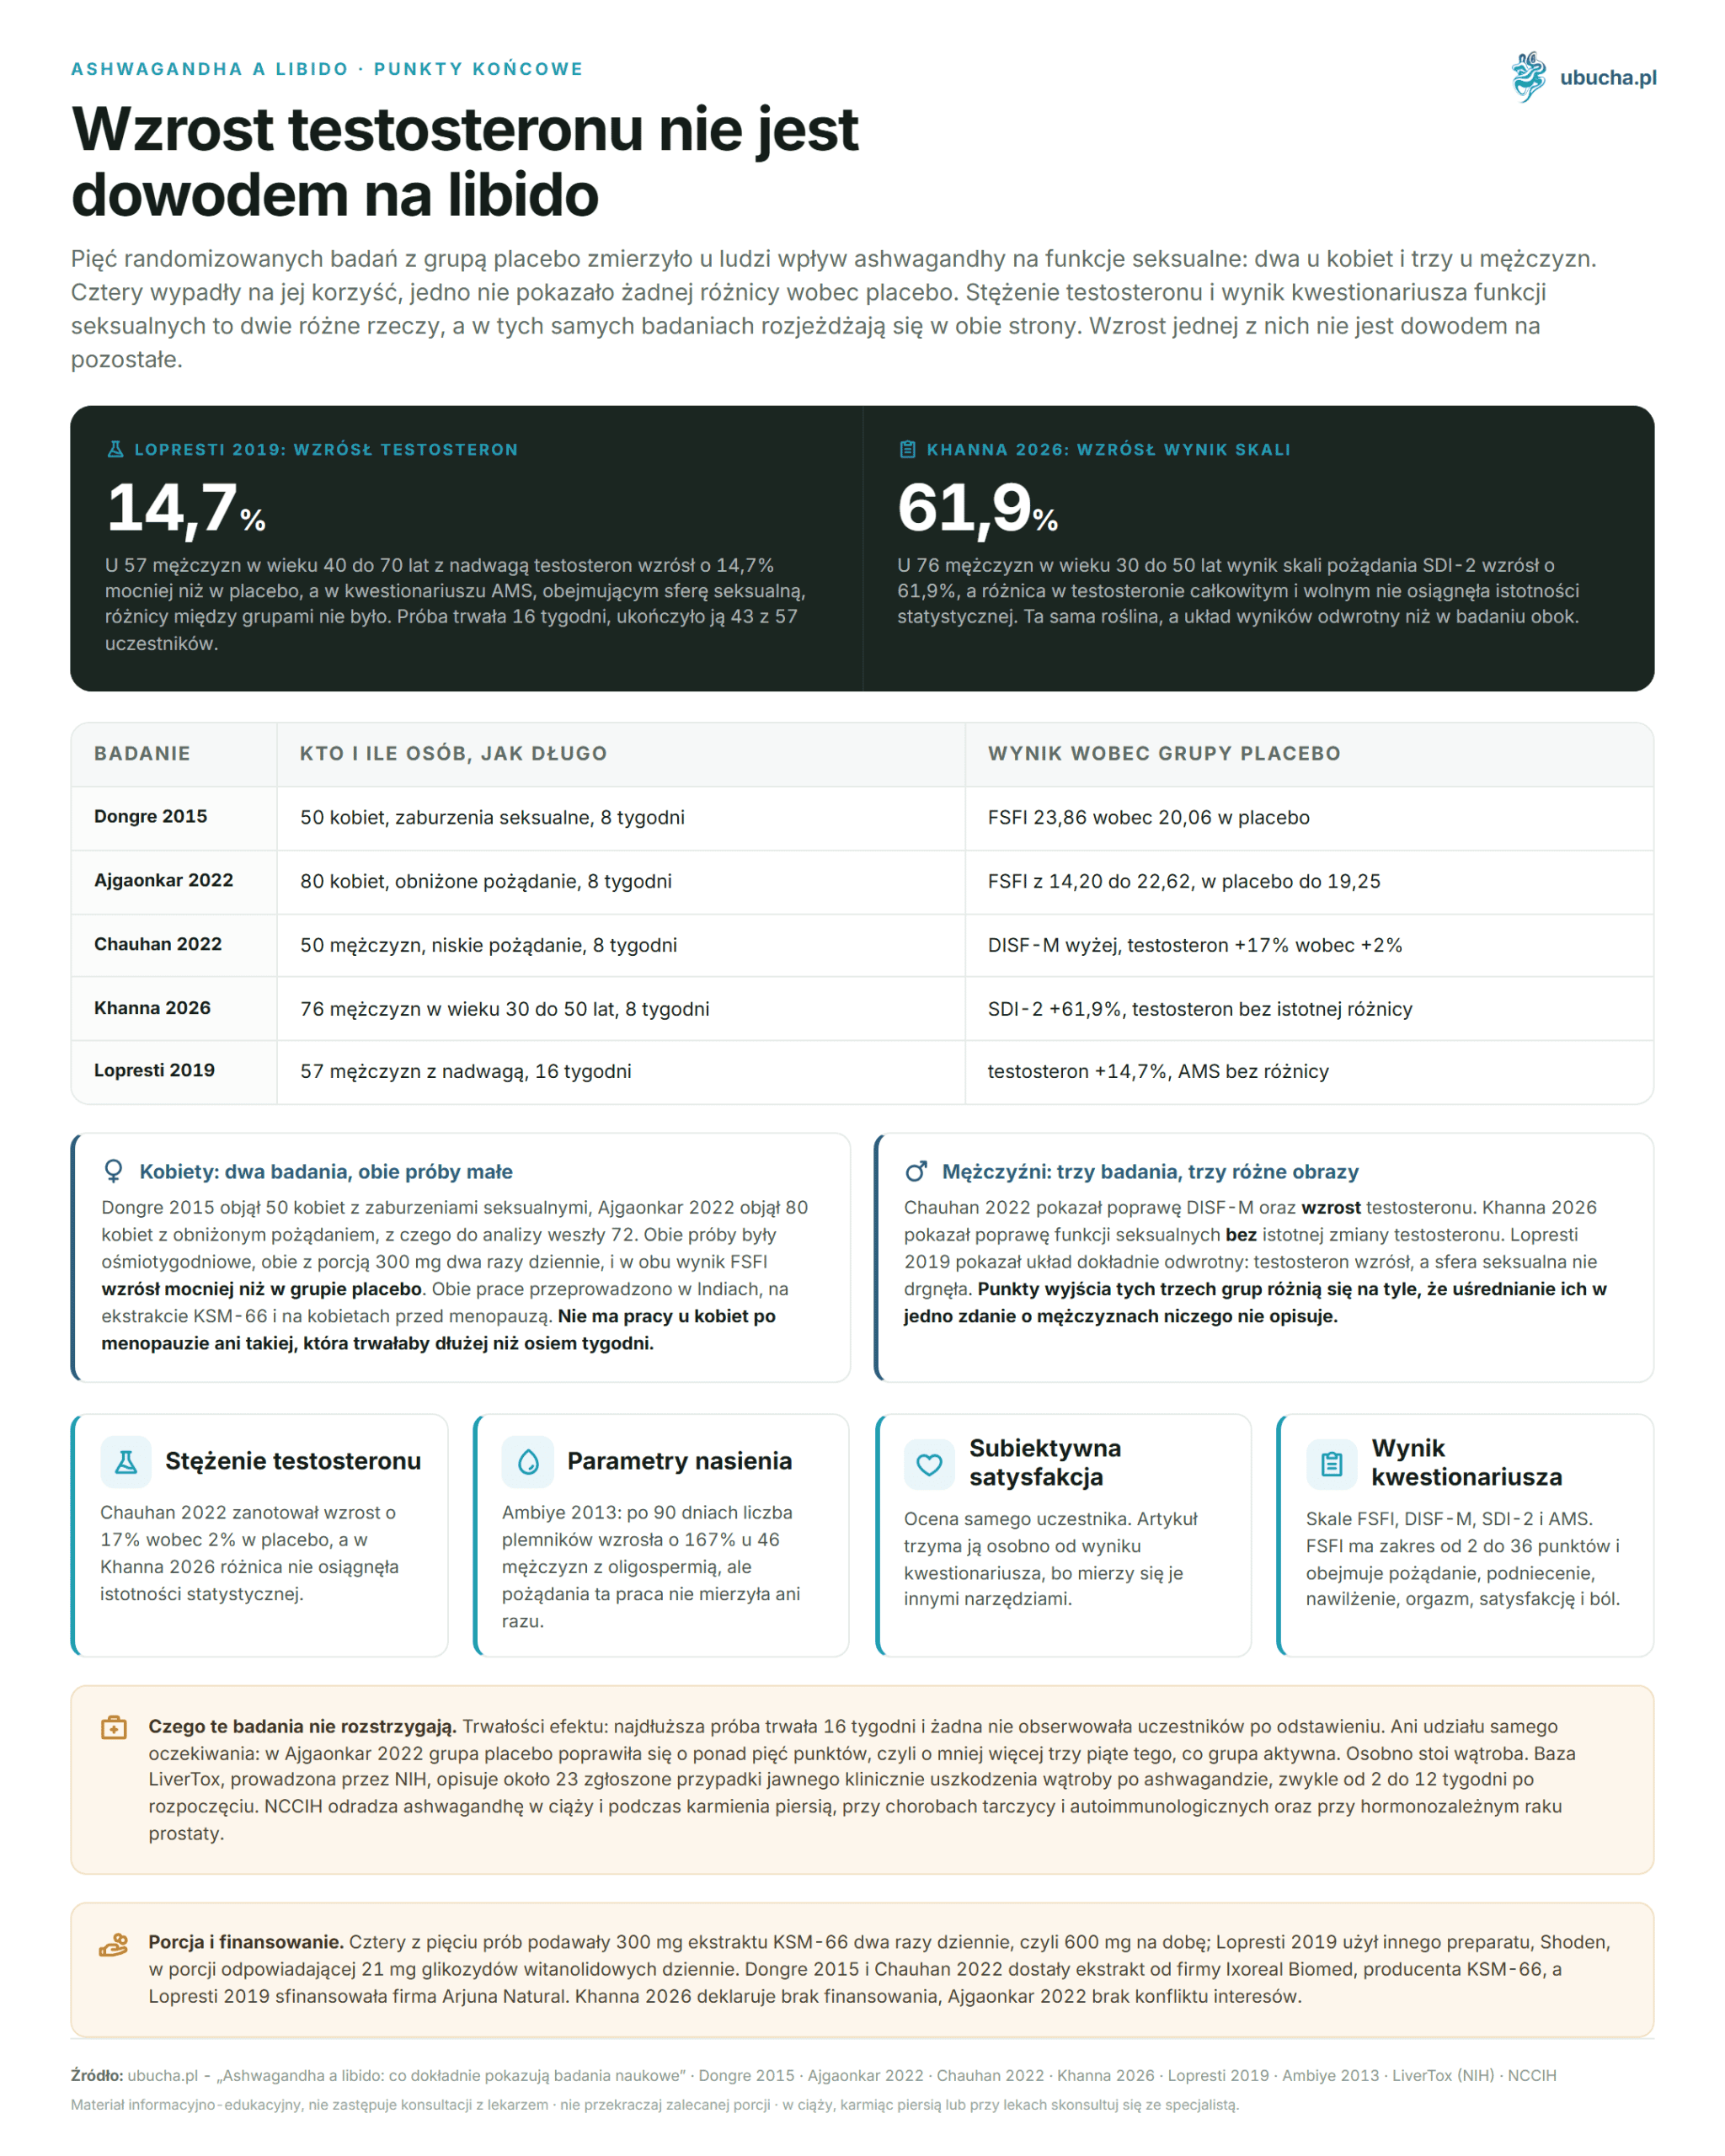
Five randomized placebo-controlled studies measured the impact of ashwagandha on sexual function in humans: two in women and three in men. Four favored its use, one showed no difference compared to placebo. The trials included 50 to 80 participants, and the longest lasted 16 weeks. This is too little to speak of a certain effect, and too much to dismiss the question as mythology. Below, we break down each of these studies: who participated, how many people, how long, what dose, what exactly was measured, and who paid for the research. We keep the sexes separate because the results differ between them. The endpoints also differ, as testosterone levels and the sexual function questionnaire score are two different things, while advertising treats them as one.
KEY INFORMATION
• Dongre 2015: 50 women, 8 weeks, FSFI score 23.86 vs 20.06 in the placebo group
• Ajgaonkar 2022: 80 women, 8 weeks, FSFI from 14.20 to 22.62, in placebo from 14.17 to 19.25
• Chauhan 2022: 50 men with low desire, 8 weeks, improvement in DISF-M questionnaire, testosterone +17% vs +2%
• Khanna 2026: 76 men, 8 weeks, SDI-2 score higher by 61.9%, testosterone with no significant difference
• Lopresti 2019: 57 men, 16 weeks, testosterone +14.7%, and sexual function with no difference compared to placebo
• LiverTox (NIH): about 23 reported cases of liver damage after ashwagandha, usually 2 to 12 weeks after starting
How many studies are there on ashwagandha and libido?
Five randomized placebo-controlled trials measured a sexual endpoint in humans: two in women and three in men. The smallest included 50 participants, the largest 80, and the longest lasted 16 weeks. A sixth study, Ambiye 2013, is often cited here, although it did not measure desire at all.
All five were compared to placebo, all lasted from 8 to 16 weeks, and none checked what happens after discontinuation. Four used the same branded KSM-66 extract, which facilitates the comparison of results, while also narrowing it down to one preparation. Differences between standardizations are described in a separate text about KSM-66 and Sensoril extracts.
| Study | Who and how many participants | Time | Dose | What was measured | Result | Who paid |
|---|---|---|---|---|---|---|
| Dongre 2015 | 50 women with sexual disorders | 8 weeks | 300 mg twice daily, KSM-66 | FSFI, FSDS | FSFI 23.86 vs 20.06 in placebo | Ixoreal Biomed: extract and part of the costs |
| Ajgaonkar 2022 | 80 women with reduced desire | 8 weeks | 300 mg twice daily, KSM-66 | FSFI, FSDS, GHQ-28 | FSFI from 14.20 to 22.62, in placebo to 19.25 | KSM-66 extract, authors with no conflict of interest |
| Chauhan 2022 | 50 men with low desire | 8 weeks | 300 mg twice daily, KSM-66 | DISF-M, testosterone, prolactin | DISF-M higher than placebo, testosterone +17% vs +2% | Ixoreal Biomed: extract and placebo capsules |
| Khanna 2026 | 76 men aged 30 to 50 | 8 weeks | 300 mg twice daily, KSM-66 | SDI-2, IIEF, testosterone, semen | SDI-2 +61.9%, testosterone with no significant difference | authors declare no funding |
| Lopresti 2019 | 57 men aged 40 to 70 with overweight, 43 completed | 16 weeks | 21 mg of withanolide glycosides, Shoden | testosterone, DHEA-S, AMS questionnaire | testosterone +14.7%, sexual function with no difference | Arjuna Natural, producer of the extract |
| Ambiye 2013 | 46 men with oligospermia | 90 days | 675 mg daily | semen, testosterone, LH | sperm count +167%, desire not measured | authors with no conflict of interest |
What did the studies show in women?
Two studies, both small trials, both eight weeks long, and both with a dose of 300 mg twice daily. Dongre 2015 included 50 women with diagnosed sexual disorders, Ajgaonkar 2022 included 80 women with reduced desire, of which 72 were analyzed. In both, the FSFI questionnaire score increased more than in the placebo group.
FSFI is a scale from 2 to 36 points, covering desire, arousal, lubrication, orgasm, satisfaction, and pain. In Dongre 2015 study, the group taking ashwagandha ended with a score of 23.86 points, and the placebo group with 20.06. In Ajgaonkar 2022 study, the active group went from 14.20 to 22.62, and the placebo from 14.17 to 19.25.
The second number from this pair is more interesting than the first. The placebo group improved by over five points, which is about three-fifths of what the active group achieved. At this endpoint, the placebo effect is large, and none of these studies eliminate it; they only measure it alongside the rest. Both studies were conducted in India, both on KSM-66 extract, and both on premenopausal women. Dongre 2015 directly thanks Ixoreal Biomed, the producer of KSM-66, for providing the extract and covering part of the study costs. There is no study on postmenopausal women or one that lasted longer than eight weeks.
What did the studies show in men?
Three studies and three different pictures. Chauhan 2022, on 50 men with low desire, showed improvement in the DISF-M questionnaire and an increase in testosterone. Khanna 2026, on 76 healthy men, showed improvement in sexual functions without a significant change in testosterone. Lopresti 2019 showed exactly the opposite.
In Chauhan 2022 study, testosterone increased by 17% compared to 2% in placebo after eight weeks, and the extract and placebo capsules were provided by Ixoreal Biomed. Khanna 2026 lasted the same amount of time, the desire scale SDI-2 increased by 61.9%, and the difference in total and free testosterone did not reach statistical significance; the authors declare that they did not receive funding for this work.
Lopresti 2019 was an alternating trial lasting 16 weeks, completed by 43 out of 57 participants, who were men aged 40 to 70 with overweight. Testosterone increased there by 14.7% more than in placebo, while in the AMS questionnaire, which includes the sexual sphere, there was no difference between groups. The starting points of these three groups differ enough that averaging them into one sentence about men describes nothing.
Does higher testosterone and better sperm mean higher libido?
No. In these same studies, both measures diverge in both directions: in Lopresti 2019 testosterone increased, but sexual function did not budge, in Khanna 2026 sexual functions improved, but testosterone did not change significantly. These are separate endpoints and separate questions.
The farthest goes Ambiye 2013. After 90 days on a dose of 675 mg daily in 46 men with oligospermia, sperm count increased by 167%, semen volume by 53%, motility by 57%, and testosterone by 17%. Sexual desire was not measured at all in this work, so it is not evidence in this matter, although it often stands in advertisements next to the word libido. Separately, we describe what RCTs say about sperm parameters and male fertility.
Four things are often lumped together in sales: testosterone levels, sperm parameters, subjective satisfaction, and the sexual function questionnaire score. They are measured with different tools, and in ashwagandha studies, they moved independently of each other. An increase in one of them is not evidence for the others.
What do these studies not resolve and who does ashwagandha harm?
They do not resolve the durability of the effect, as the longest trial lasted 16 weeks and none observed participants after discontinuation. They also do not resolve how much of the result was due to the plant itself and how much to expectation, as the placebo groups improved significantly in them. A separate issue is the liver.
LiverTox, a database maintained by the NIH, describes about 23 reported cases of clinically apparent liver damage after ashwagandha. Symptoms usually appeared 2 to 12 weeks after starting, most often with jaundice and itching, and the degree of probability of a relationship was rated as B, meaning a probable cause. Individual cases have been described that ended in liver transplantation or death, mainly in people with pre-existing liver disease.
NCCIH states that safety data extend to a maximum of three months of use, and advises against ashwagandha during pregnancy and breastfeeding, with thyroid and autoimmune diseases, as well as with hormone-dependent prostate cancer. Those looking for raw material with a different evidence base can find it in the text about the properties of maca, and a comparison of several plants at once is in the summary “Adaptogens for libido: which support and which do not.” Products from this group have been gathered in the adaptogens category.
Frequently Asked Questions
Does ashwagandha increase libido in women?
In two eight-week placebo-controlled studies, Dongre 2015 on 50 women and Ajgaonkar 2022 on 80 women, the FSFI questionnaire score increased more than in the placebo group. Both trials were small, both from India, and both used the KSM-66 extract.
Does ashwagandha affect libido in men?
Two out of three studies showed improvement: Chauhan 2022 on 50 men with low desire and Khanna 2026 on 76 men. The third, Lopresti 2019 on 57 overweight men, showed no difference in sexual function compared to placebo.
How long does it take to see effects in these studies?
All trials with a sexual endpoint measured the outcome after eight weeks, and Lopresti 2019 after sixteen. There are no shorter measurements, so the studies simply do not answer the question about effects after one or two weeks.
What dose was used in the libido studies?
Four out of five trials administered 300 mg of KSM-66 extract twice daily, totaling 600 mg per day. Lopresti 2019 used a different preparation, Shoden, at a dose corresponding to 21 mg of withanolide glycosides per day.
Does ashwagandha increase testosterone?
In some studies, yes: Chauhan 2022 noted an increase of 17% compared to 2% in placebo, Lopresti 2019 by 14.7% more than placebo. In Khanna 2026, the difference did not reach statistical significance, although sexual functions improved significantly.
Is improvement in sperm parameters the same as libido?
No. Ambiye 2013 showed a 167% increase in sperm count in 46 men with oligospermia, but sexual desire was not measured at all in this study. These are two different endpoints, studied with different tools.
Were these studies funded by raw material producers?
Partially yes. Dongre 2015 and Chauhan 2022 received extract from Ixoreal Biomed, the producer of KSM-66, and Lopresti 2019 was funded by Arjuna Natural. Khanna 2026 declares no funding, Ajgaonkar 2022 no conflict of interest.
Who should not use ashwagandha?
NCCIH advises against it during pregnancy and breastfeeding, with thyroid and autoimmune diseases, and with hormone-dependent prostate cancer. The LiverTox database describes about 23 cases of liver damage, so it is also better to avoid it in case of liver disease.
This article is for informational and educational purposes and does not replace consultation with a doctor. If you are pregnant, breastfeeding, taking medications, or have chronic conditions, consult the use of supplements or herbs with a specialist.
Author: Michał Waluk · Published: 2026-08-24 · Updated: 2026-08-24