Default Mode Network (DMN) and Afterglow: What Happens in the Brain After an Experience

Default Mode Network (DMN) and afterglow: what has really been measured in psilocybin studies, how long the effects lasted, and what was not shown.
When you sit idly and let your thoughts wander, the brain does not rest. The network called DMN, or default mode network, is responsible for memories, planning, and building a narrative about oneself. Imaging studies have shown that psychedelics significantly reduce its activity, and participants in clinical trials later describe a several-week period of mood improvement called afterglow. This article organizes what has been measured in this story and what has been added along the way. Besides the network itself, it also shows what BDNF protein is associated with afterglow and what studies on the therapeutic relationship say about post-session work. Two numbers circulating in the Polish internet, namely the alleged decrease in blood flow of 10-20% and the exact length of the neuroplasticity window, have no support in the works to which they are attributed. The text describes scientific research and does not encourage the use of controlled substances.
KEY INFORMATION
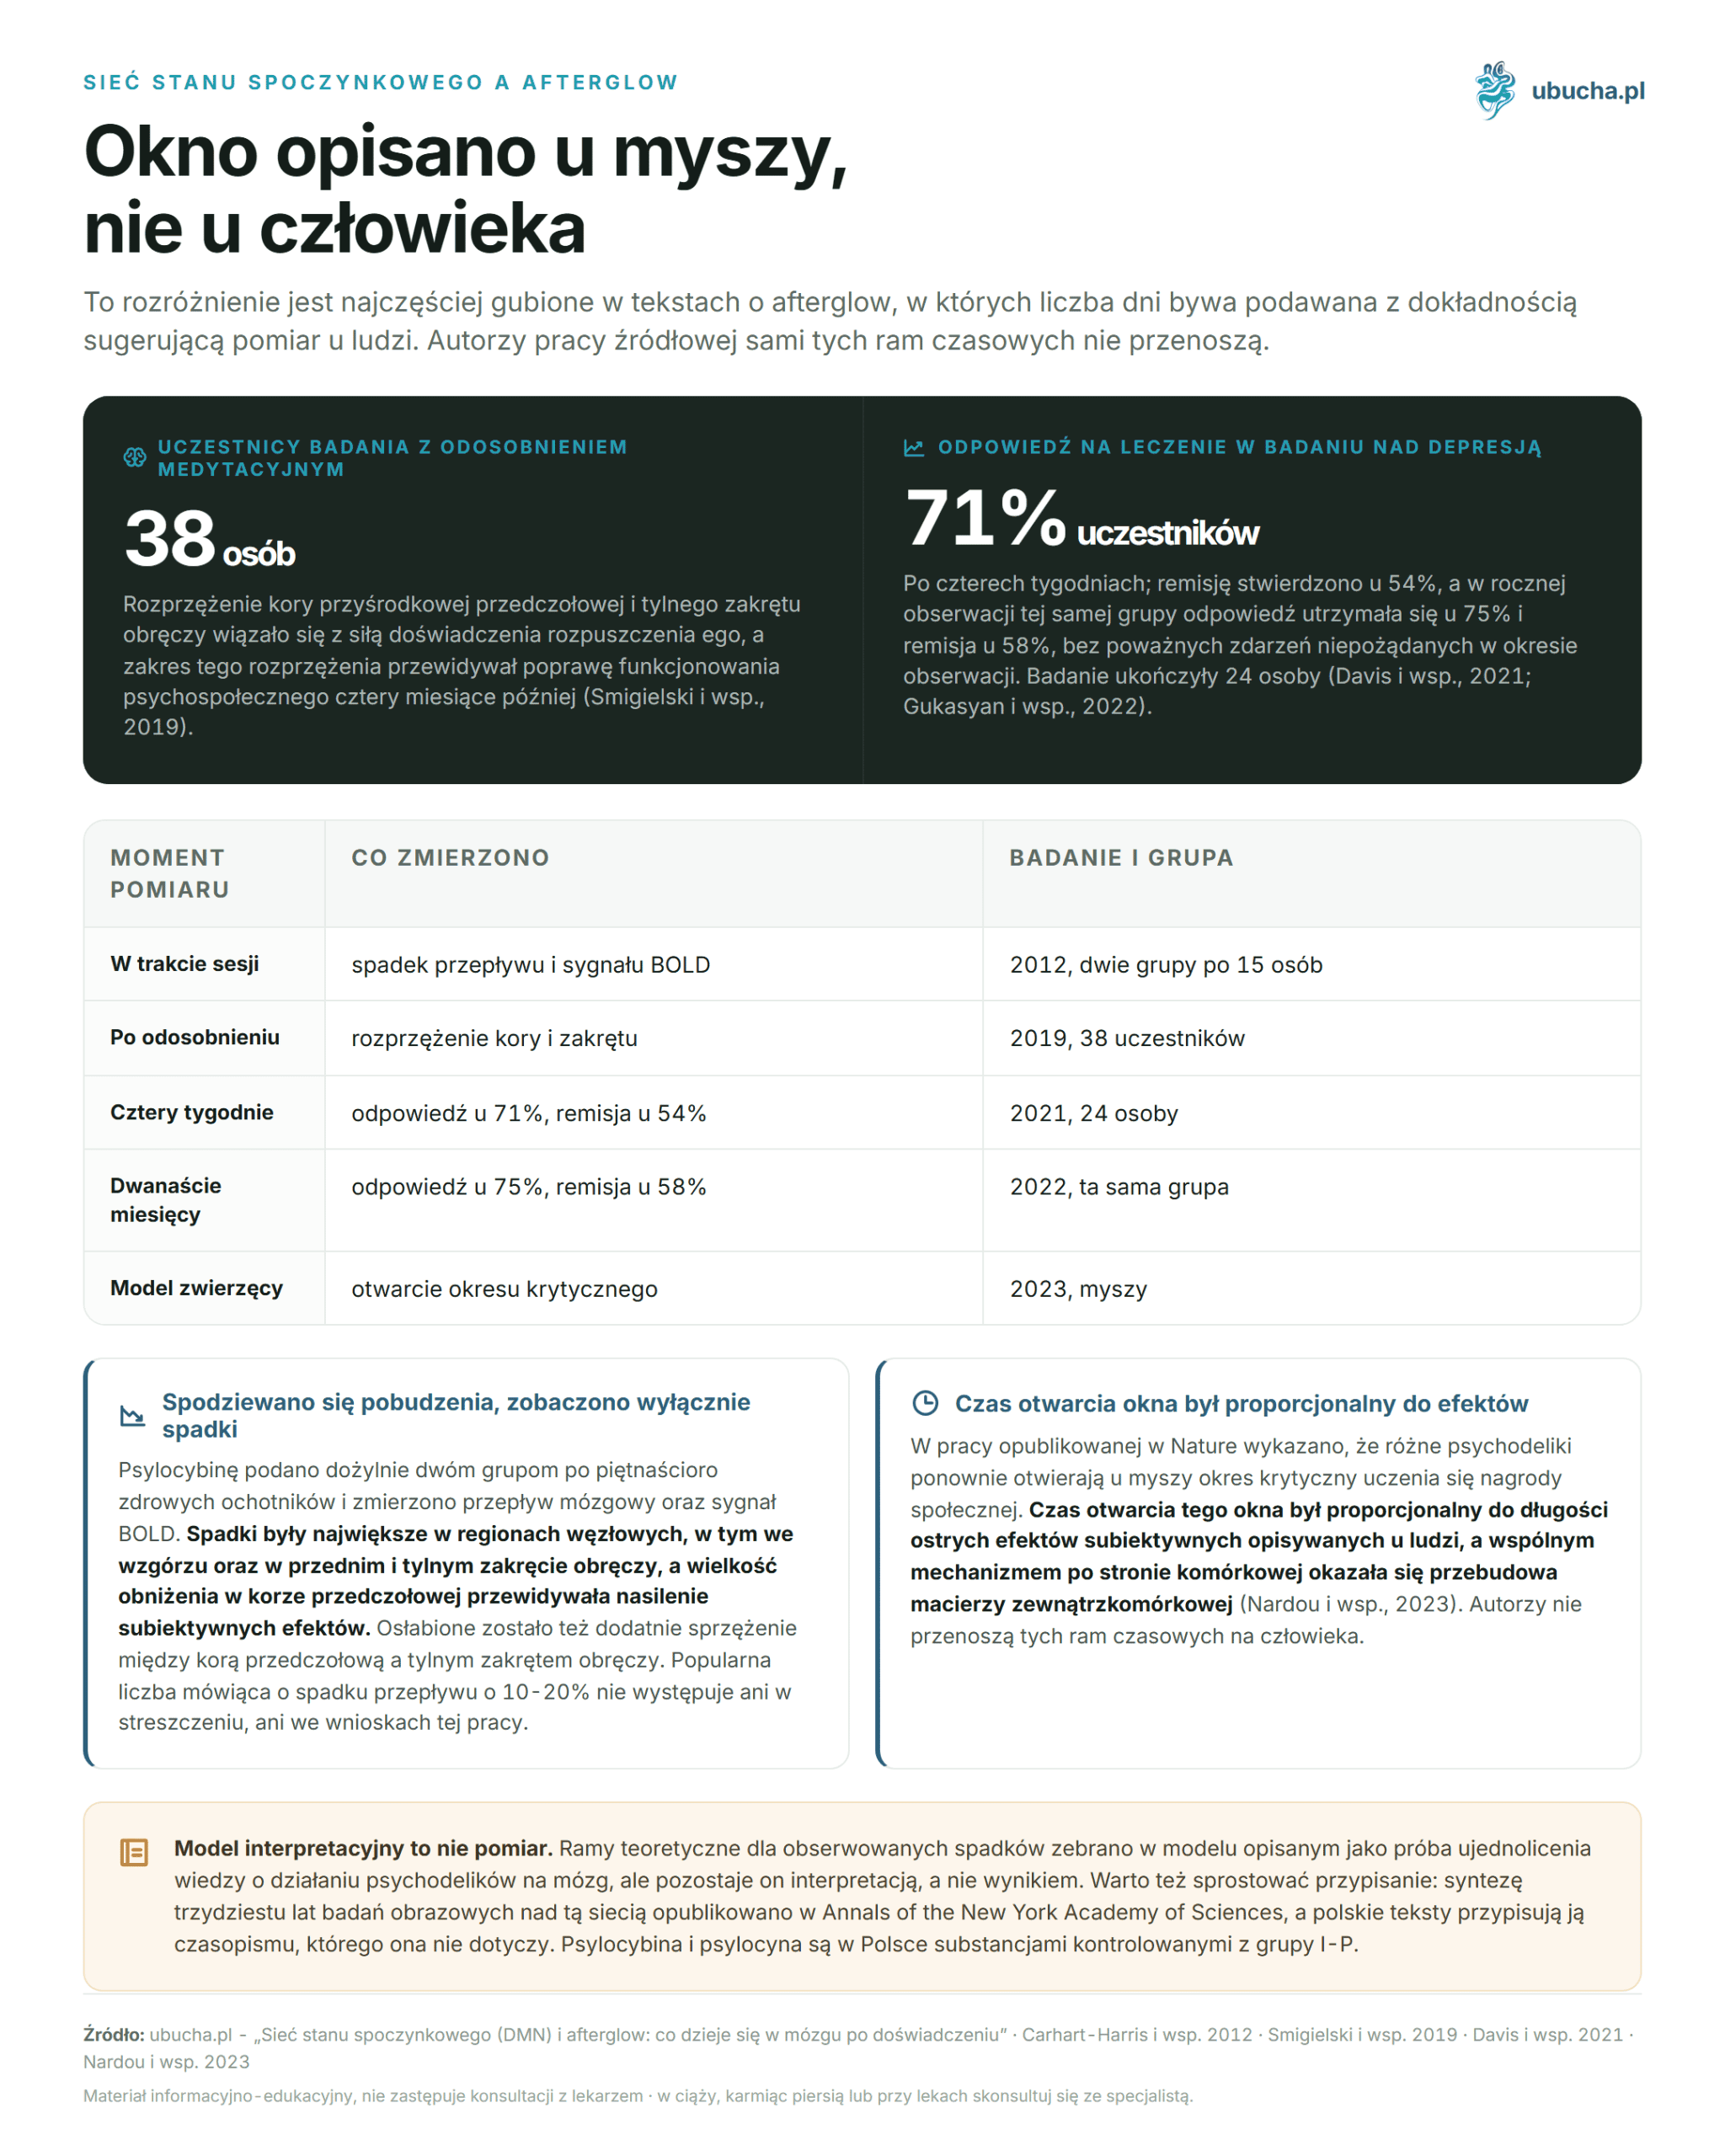
• Psilocybin decreased cerebral blood flow and BOLD signal most strongly in the hubs of the network; the magnitude of the decrease in the prefrontal cortex predicted the intensity of subjective effects (Carhart-Harris, PNAS, 2012).
• The popular number indicating a decrease of 10-20% does not appear in this work or its summary.
• In a study with psilocybin in depression, a treatment response was found in 71% of participants after four weeks, and in a one-year observation of the same group in 75% (Davis, JAMA Psychiatry, 2021; Gukasyan, Journal of Psychopharmacology, 2022).
• The neuroplasticity window has so far been described in mice: the duration of its opening was proportional to the length of acute effects described in humans (Nardou, Nature, 2023).
• Psilocybin and psilocin are controlled substances in Poland from group I-P.
What is the default mode network (DMN)?
It is a system of brain areas that activates when attention is not directed to the outside world. It includes the medial prefrontal cortex, posterior cingulate gyrus, and structures of the medial temporal lobe. The network is responsible for recalling memories, imagining the future, and taking the perspective of others.
A synthesis of thirty years of imaging research on this network was published in the Annals of the New York Academy of Sciences (Buckner et al., 2008). The authors describe it as a system composed of subsystems, with the posterior cingulate gyrus as the convergence point. It is worth clarifying this, as this work is often attributed to the journal Nature Reviews Neuroscience, which it does not pertain to.
The relationship between excessive activity of this network and mental disorders has been described in separate works. Resting state analysis in people with depression showed abnormally heightened self-referential processing within the network (Sheline et al., PNAS, 2009), and in post-traumatic stress disorder, connectivity within this network predicted symptom severity (Lanius et al., Acta Psychiatrica Scandinavica, 2010).
How do psychedelics change DMN activity?
They decrease it, and this was a surprising result for the researchers themselves. In a study published in PNAS, psilocybin was administered intravenously to two groups of fifteen healthy volunteers, and cerebral blood flow and BOLD signal were measured. Stimulation was expected, but only decreases were observed.
The decreases were greatest in hub regions, including the thalamus and anterior and posterior cingulate gyrus. A consistent reduction in activity was observed in the anterior part of the cingulate gyrus and medial prefrontal cortex, and the magnitude of this reduction predicted the intensity of subjective effects. Psilocybin also weakened positive coupling between the prefrontal cortex and posterior cingulate gyrus (Carhart-Harris et al., PNAS, 2012).
In Polish discussions of this work, a number indicating a decrease in flow of 10-20% appears. It is neither in the summary nor in the conclusions of this study, so treat it as an addition. The mechanism itself later received theoretical frameworks collected in a model called REBUS, described as an attempt to unify knowledge about the effects of psychedelics on the brain (Carhart-Harris et al., Pharmacological Reviews, 2019), but this is an interpretative model, not a measurement.
What is afterglow and what is known about it?
Afterglow is a period described by study participants as lightness, openness, and clarity of thought lasting from a few days to a few weeks after the session. It is not a result of the substance lingering in the body, as it is eliminated earlier. However, there is less hard data about its biology than popular discussions suggest.
The closest measurement of a lasting change in the network comes from a study in which 38 participants received psilocybin during a five-day meditation retreat. The decoupling of the medial prefrontal cortex and posterior cingulate gyrus was associated with the strength of the ego dissolution experience, and the extent of this decoupling predicted improvement in psychosocial functioning four months later (Smigielski et al., NeuroImage, 2019).
On the clinical side, afterglow has a counterpart in the form of rapid mood improvement. In a randomized study with a waiting group, two sessions with psilocybin reduced depression severity as early as the day after the first session, and the effect lasted for four weeks of observation (Davis et al., JAMA Psychiatry, 2021).
What did studies on the neuroplasticity window really show?
They showed that the window exists in mice, and did not show how long it lasts in humans. This distinction is often lost in texts about afterglow, where the number of days is sometimes given with an accuracy suggesting measurement in humans.
A study published in Nature demonstrated that various psychedelics reopen the critical period for social reward learning in mice. The duration of this window opening was proportional to the length of acute subjective effects described in humans, and a common cellular mechanism turned out to be the remodeling of the extracellular matrix (Nardou et al., Nature, 2023). The authors do not transfer these time frames to humans.
| Measurement Moment | What was measured | Study and group |
|---|---|---|
| During the session | Decrease in cerebral blood flow and BOLD signal in hub regions; the magnitude of the decrease predicted the intensity of effects | Carhart-Harris, 2012; two groups of 15 healthy volunteers |
| After five-day retreat | Decoupling of the prefrontal cortex and posterior cingulate gyrus associated with ego dissolution | Smigielski, 2019; 38 participants |
| Four weeks | Response to treatment in 71% and remission in 54% of participants | Davis, 2021; 24 people who completed the study |
| Twelve months | Response in 75% and remission in 58%, with no serious adverse events during the observation period | Gukasyan, 2022; the same group |
| Animal model | Reopening of the critical period for social reward learning | Nardou, 2023; mice |
What does BDNF have to do with afterglow?
BDNF is a growth factor supporting neuron survival and synapse formation, and its receptor TrkB is one of the pathways through which psychedelics act. The Ly team showed that serotonergic psychedelics increase neurite and dendritic spine growth in cultures and in animals, and these changes occurred through the TrkB, mTOR, and 5-HT2A pathways (Ly et al., Cell Reports, 2018).
It is important to be precise here, as a shorthand has circulated online in a distorted form. The Ly study did not measure BDNF levels in the blood nor proved that the psychedelic raises its level. It showed that the signal goes through the receptor of this protein, and the structural effect is comparable to ketamine. We describe this pathway more broadly in the entry about the 5-HT2A receptor and brain plasticity.
Physical exercise affects the same system, and here the data comes from humans. A meta-analysis by Szuhany and colleagues included 29 studies and 1111 participants. A single session of exercise resulted in a moderate increase in BDNF (Hedges g equal to 0.46), regular training strengthened the effect of a single session (g equal to 0.59), and resting BDNF levels increased slightly (g equal to 0.27) (Szuhany et al., Journal of Psychiatric Research, 2015). The cannabinoid context of the same signaling is collected in our entry about neuroplasticity and BDNF.
What to do in the afterglow window to solidify the effect?
The short answer is: there are fewer practices with strong evidence in this window than guides suggest. The best-documented is the quality of the therapeutic relationship, followed by aerobic exercise acting on the same pathway, and one popular practice, microdosing, in a self-blind study did not differ from placebo.
| Practice | What the study showed | Source |
|---|---|---|
| Therapeutic relationship and integration | The strength of the alliance predicted the final outcome on the depression scale | Murphy 2021, n=30 |
| Aerobic exercise | Increase in BDNF after a single session, g equal to 0.46 | Szuhany 2015, 29 studies |
| Microdosing as an extension | No significant differences compared to placebo | Szigeti 2021, n=191 |
Meditation itself requires a separate statement, as the aforementioned study with retreat is often cited as evidence for practice in the window after the session. In it, psilocybin was randomized against placebo, but all participants were in retreat, including those in the placebo group. Therefore, it is not possible to read from this work how much the result was contributed by meditation itself.
Why does integration weigh more than the session itself?
Because it is most strongly associated with the final outcome. In the psilocybin arm of a randomized study comparing psilocybin with escitalopram, 30 people participated, who received two doses of 25 mg spaced three weeks apart, with preparation, support during the session, and integration therapy afterward.
The strength of the therapeutic alliance predicted the quality of contact before the session, the intensity of emotional breakthrough and mystical experience, and the final outcome on the QIDS scale. More importantly, the quality of the relationship before the second session influenced the final intensity of depression directly, bypassing the experience itself: a weaker alliance predicted a higher depression score at the end of the study (Murphy et al., Frontiers in Pharmacology, 2021).
We have noticed that popular guides reverse this relationship and attribute the durability of the effect to the intensity of the experience. The data suggest something more cautious: intensity mattered, but it was itself predicted by the relationship with the facilitator. The practical consequences are described in our entry about integration step by step. It is also worth remembering that all these observations come from clinical conditions, with preparation, supervision, and planned care after the session, not from home situations.
Does the effect last for months?
In clinical studies, yes, at least for some participants. A group of 24 people with depression who completed a protocol with two sessions of psilocybin was observed for a year. The treatment response lasted in 75%, and remission in 58%, with all participants attending all follow-up visits.
No serious adverse events related to psilocybin were reported during the observation period (Gukasyan et al., Journal of Psychopharmacology, 2022). In another study involving 51 oncology patients with symptoms of depression and anxiety, about 80% of participants still showed clinically significant mood improvement after six months (Griffiths et al., Journal of Psychopharmacology, 2016).
MDMA therapy for post-traumatic stress disorder has undergone a separate research path and has reached a phase three study with randomization and placebo (Mitchell et al., Nature Medicine, 2021). All these protocols share one thing: the substance was administered in supervised conditions, with preparation and therapeutic work after the session. The results themselves do not transfer to use outside such a setup.
What does Polish law say about these substances?
Psilocybin and psilocin are controlled substances in Poland. They are listed in group I-P of the list of psychotropic substances, under positions 86 and 76, respectively. Possession of a psychotropic substance contrary to the provisions of the Act on Counteracting Drug Addiction is a punishable act under Article 62 of this Act.
The studies described in this article were conducted abroad, in registered clinical trials, under medical supervision and with the consent of bioethics committees. This is not a procedural detail, but a condition under which the described results were obtained. Participants were qualified after excluding psychotic disorders and other contraindications, and sessions took place in the presence of a trained team.
A separate issue is interactions with medications. Classic psychedelics act on the serotonergic system, so combining them with antidepressants can be dangerous, as discussed in more detail in the text about contraindications and interactions with SSRIs and MAOIs. If you are seeking help for depression or post-traumatic stress disorder, the starting point remains a psychiatrist and available treatment methods in Poland. It is also worth remembering that self-discontinuation of an antidepressant before any experience is a separate risk, independent of the substance itself, and also requires guidance from a doctor.
Frequently Asked Questions
What is the default mode network (DMN)?
It is a system of brain areas that is active when attention is not directed outward. It includes the medial prefrontal cortex, posterior cingulate gyrus, and structures of the medial temporal lobe. It is responsible for recalling memories, imagining the future, and taking the perspective of others.
How do psychedelics affect DMN activity?
They decrease it. After intravenous administration of psilocybin, only decreases in cerebral blood flow and BOLD signal were observed, greatest in hub regions, and a weakening of coupling between the prefrontal cortex and posterior cingulate gyrus. The magnitude of the decrease predicted the intensity of subjective effects.
Where did the number indicating a 10-20% decrease in flow come from?
Not from the work it is often attributed to. A study published in PNAS in 2012 describes the direction and location of changes and their relationship to the intensity of effects, but does not provide such a percentage. This number circulates in discussions without grounding in a source.
How long does the neuroplasticity window last after psychedelics?
It has not been measured in humans. In mice, a reopening of the critical period for social reward learning was demonstrated, and the duration of the opening was proportional to the length of acute effects described in humans. The daily frameworks provided in guides do not come from human studies.
Does microdosing extend afterglow?
There is no data for that. The largest self-blind study involved 191 people, and all psychological outcomes improved also in the placebo group, with no significant differences between groups (Szigeti et al., eLife, 2021). The authors explain the effect by expectation.
Does mood improvement after psilocybin last?
In clinical studies, for some participants, yes. In a one-year observation of a group of 24 people with depression, the response lasted in 75%, and remission in 58%. In a study involving 51 oncology patients, about 80% still showed improvement after six months.
Is psilocybin legal in Poland?
No. Psilocybin and psilocin belong to group I-P of the list of psychotropic substances, under positions 86 and 76. Possession of a psychotropic substance contrary to the provisions of the Act on Counteracting Drug Addiction is a punishable act under Article 62 of this Act.
This article is informational and educational. It describes clinical studies in which the substance is administered under medical supervision after participant qualification; using these conditions on one’s own does not replicate the results. These substances are controlled in Poland by the Act on Counteracting Drug Addiction. If you have suicidal thoughts, call the free, 24-hour numbers 116 123 or 800 70 2222. In life-threatening situations: 112.
Author: Michał Waluk · Published: 2026-08-09 · Updated: 2026-09-22