
Supplements for Adrenal Fatigue: Ashwagandha, B5 and Rhodiola
The systematic review from 2016 did not confirm the existence of adrenal fatigue. We check what studies have shown about ashwagandha, rhodiola, B5, and vitamin C.
Type “adrenal fatigue” into a search engine, and you will find supplementation protocols, diets, and dosage tables. Search for the term “adrenal fatigue” in the scientific publication database, and you will come across a systematic review whose title states outright: adrenal fatigue does not exist. This discrepancy does not mean that the symptoms are fabricated. It means that the name given to them describes a mechanism that no one has confirmed by measurement. Below you will find what can be defended today: what exactly has been checked and with what results, which diseases need to be ruled out by a doctor before you reach for anything from the shelf, and how the studies on ashwagandha, rhodiola, vitamin B5, and vitamin C look when read carefully to the end, along with the results section, not just the summary.
KEY INFORMATION
• The systematic review by Cadegiani and Kater (BMC Endocrine Disorders, 2016) analyzed 58 cortisol studies and found no confirmation for “adrenal fatigue” as a disease entity.
• In the study by Chandrasekhara (Indian Journal of Psychological Medicine, 2012), cortisol levels in serum decreased by 27.9 percent after 60 days in 64 individuals with chronic stress, compared to 7.9 percent in the placebo group.
• Brody et al. (Psychopharmacology, 2002) noted a faster return of cortisol to baseline after vitamin C, but not a smaller overall cortisol response.
• Primary adrenal insufficiency is diagnosed by a corticotropin stimulation test and is treated with hormones, not adaptogens.
Is “adrenal fatigue” a real diagnosis?
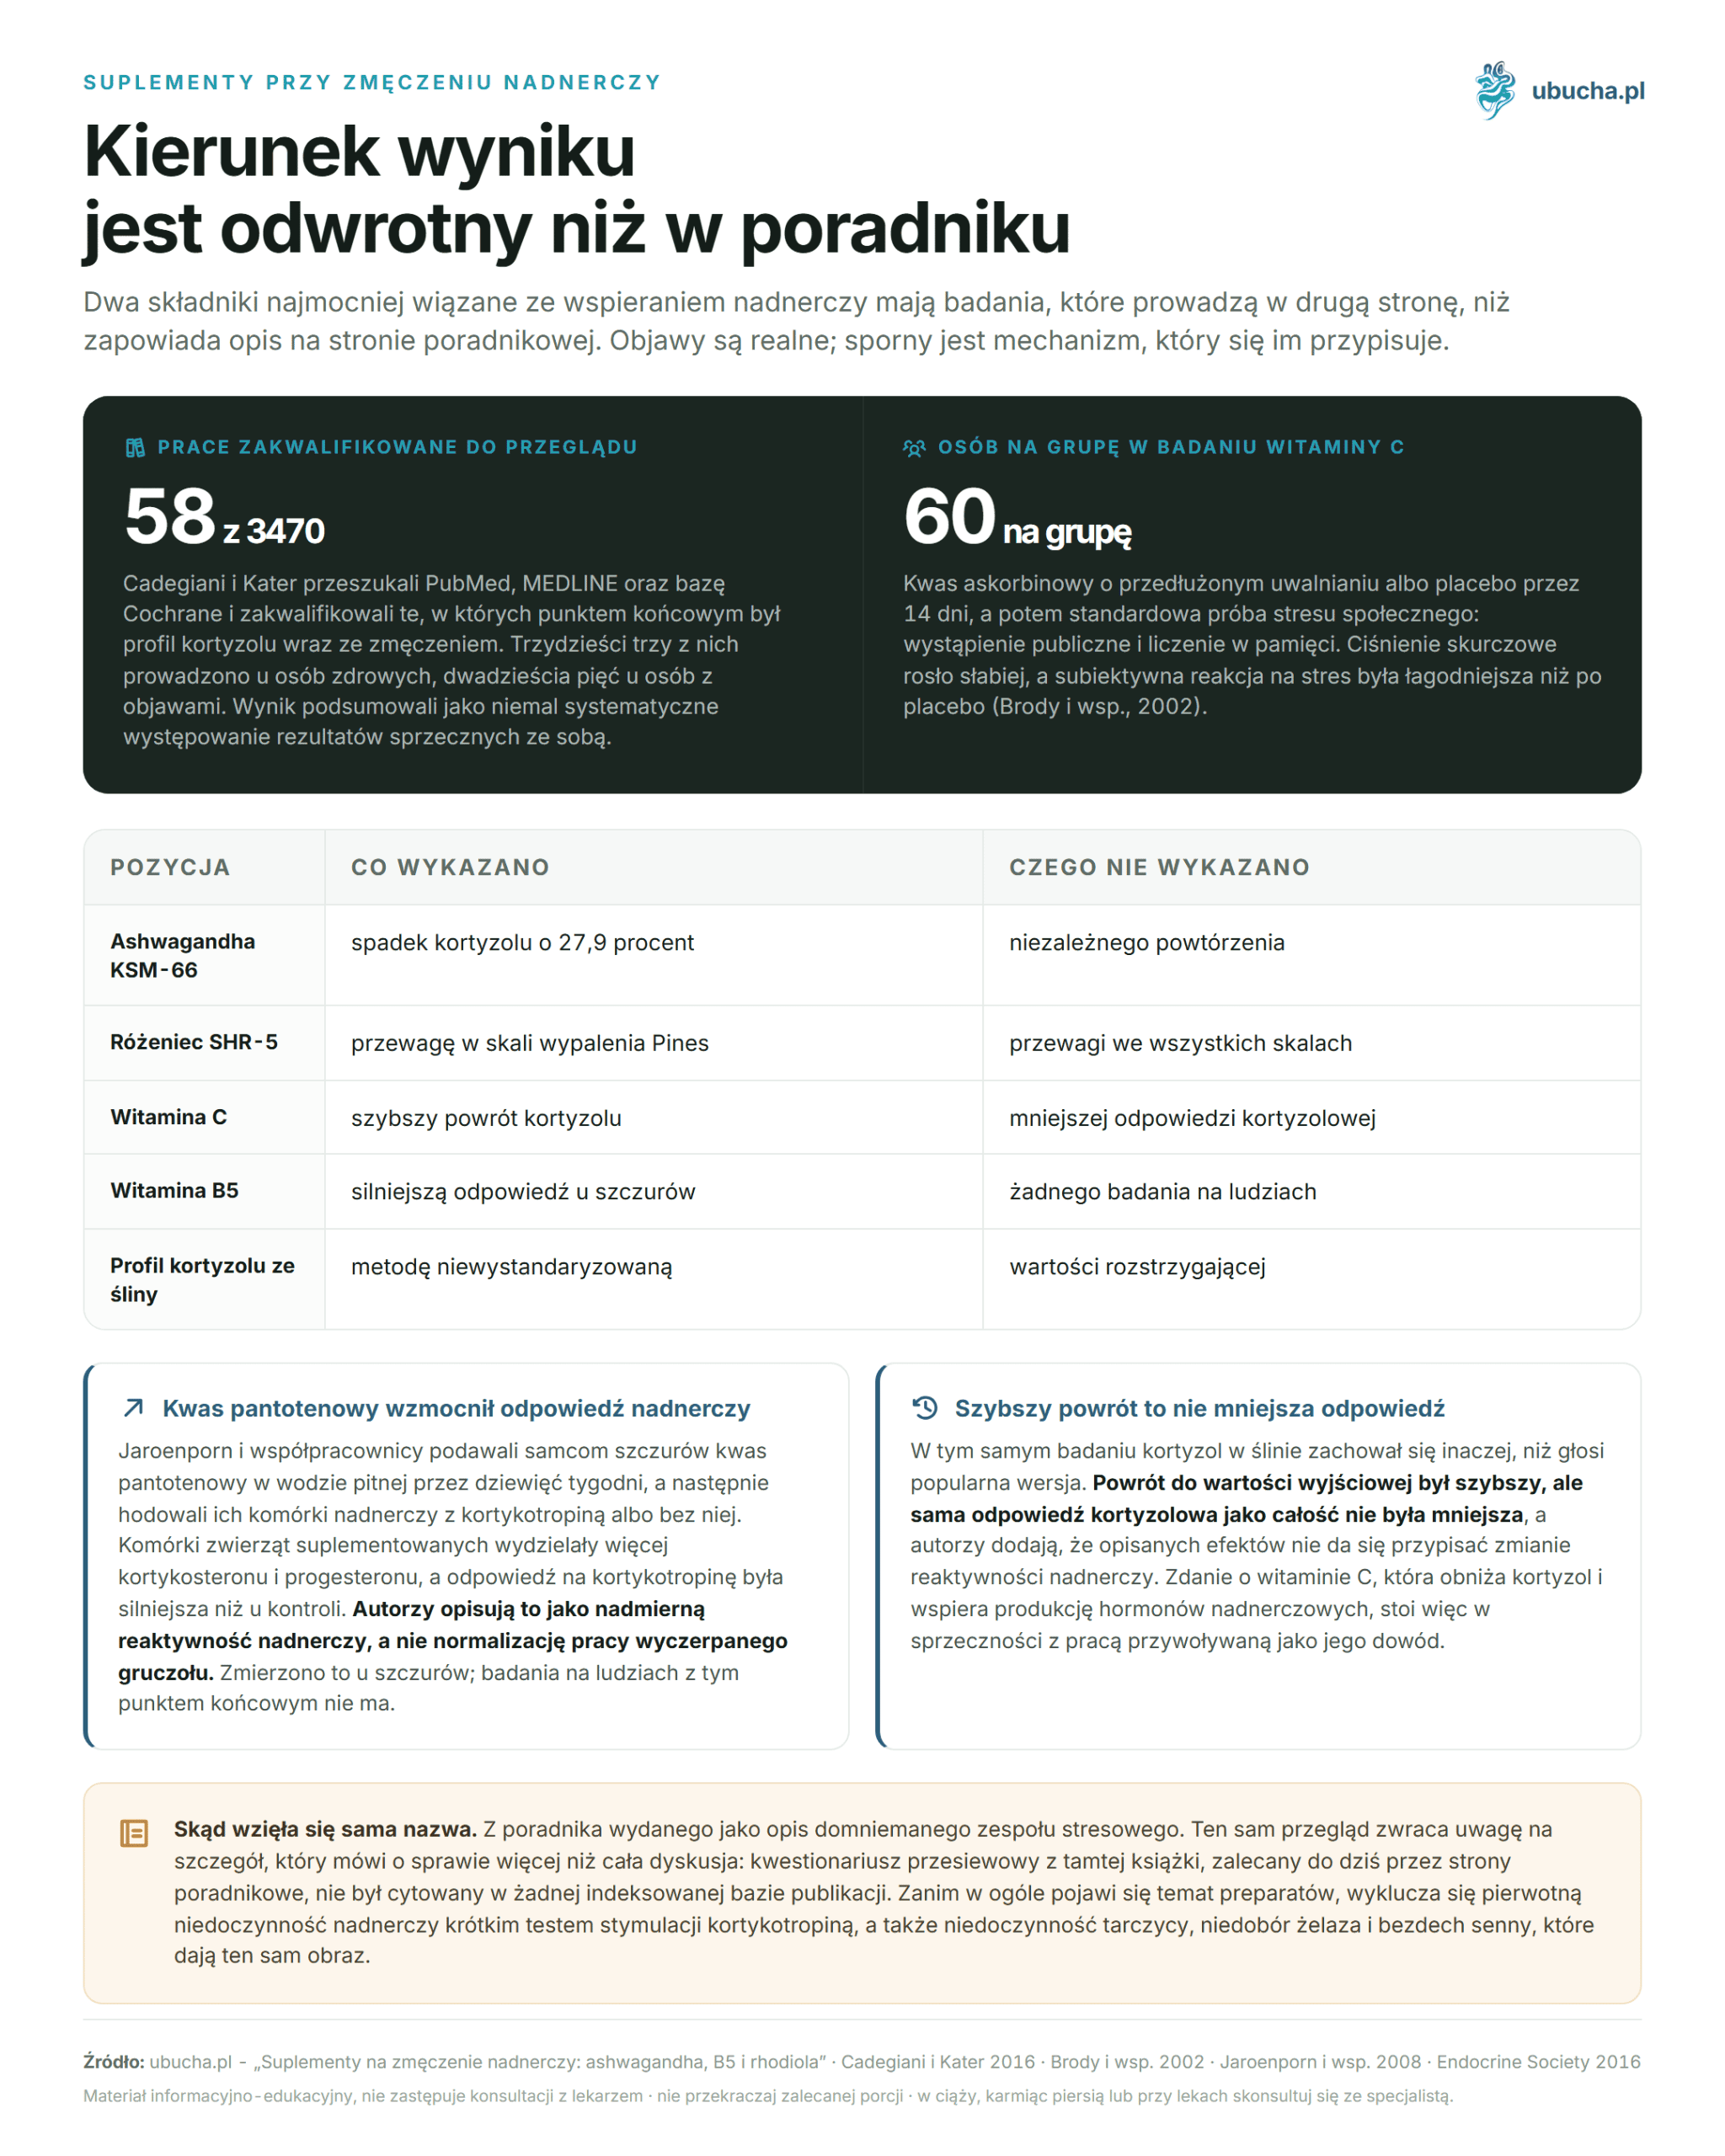
It is not a condition recognized by any endocrinological society, and the attempt to find evidence for it has ended with a negative result. Cadegiani and Kater (BMC Endocrine Disorders, 2016) searched PubMed, MEDLINE, and the Cochrane database and from 3470 found articles, they qualified 58, in which the endpoint was a cortisol profile along with fatigue or energy levels.
Thirty-three of these studies were conducted on healthy individuals, twenty-five on individuals with symptoms. The most commonly used measurements were direct cortisol measurement after awakening, cortisol response to awakening, and the daily rhythm of cortisol in saliva. The authors summarized the result as almost systematic occurrence of conflicting results, regardless of the quality and validation of the tests used. The final conclusion is that adrenal fatigue remains a myth.
So where did this name come from? From the guide “Adrenal Fatigue: The 21st Century Stress Syndrome,” whose author was the first to describe the alleged syndrome. The same review points out a detail that says more about the matter than the entire discussion: the screening questionnaire from that book, still recommended by advisory websites, has not been cited in any indexed publication database.
The symptoms are, however, entirely real. Chronic fatigue, cognitive fog, and poor stress tolerance are reasons why people go to the doctor. Only the mechanism attributed to them is disputed.
What is happening with the HPA axis?
The popular explanation speaks of desensitization of glucocorticoid receptors, weakening of negative feedback, and flattening of the daily cortisol curve. This is a hypothesis, not a determination. If the data confirmed it, the 2016 review would have found a consistent pattern, but it found a lack of it.
The authors also pointed out why this happened. They mention the heterogeneity of research designs, the descriptive nature of most studies, poor quality of fatigue assessment, methodology for measuring cortisol not recognized by endocrinologists, and drawing conclusions about causality from simple correlations. These are criticisms of the research method, not of the patients.
This leads to a practical consequence that saves money. A commercial four-day cortisol profile from saliva, advertised as a way to detect “adrenal fatigue,” belongs precisely to that group of measurements which the review indicated as non-standardized. Its result does not determine anything either way.
A fair summary is therefore as follows: the hypothalamic-pituitary-adrenal axis does indeed respond to chronic stress and is an area actively researched, but there is currently no cortisol profile that would allow a diagnosis for a specific individual. More about the stress mechanisms themselves we have gathered in the post about what really lowers cortisol.
When should you see an endocrinologist?
Before the topic of supplements even arises, primary adrenal insufficiency, or Addison’s disease, must be ruled out. This is a life-threatening condition treated with continuous hormone administration under a doctor’s supervision, not with herbs.
The guidelines from the Endocrine Society (Journal of Clinical Endocrinology and Metabolism, 2016) recommend exclusion tests for every patient with symptoms indicating this disease, and the diagnostic threshold should be lowered for individuals in acute states and those with predisposing factors. Pregnant women with unexplained, persistent nausea, fatigue, and low blood pressure are mentioned separately.
The standard tool for diagnosis is a short corticotropin stimulation test. If it cannot be performed immediately, the guidelines recommend screening in the form of morning ACTH and cortisol measurements in plasma. Determining the cause includes validated measurement of antibodies against 21-hydroxylase; with a negative result, other causes are sought.
Symptoms for which you should not delay: severe weakness with persistent low blood pressure, low sodium levels in the blood, darkening of the skin, gums, scars, unexplained weight loss, and increased nausea or vomiting that worsens with stress. It is worth noting that the Task Force itself worked without corporate funding, which is important to note regarding the guidelines.
What did the ashwagandha study really show?
This is the most cited trial on this topic and one of the few where the decrease in cortisol was given as a percentage. Chandrasekhar, Kapoor, and Anishetty (Indian Journal of Psychological Medicine, 2012) studied 64 adults with a history of chronic stress. The trial was single-center, prospective, randomized, double-blind, with a placebo group.
Participants took one capsule twice a day for 60 days; the capsule in the experimental group contained 300 mg of a highly concentrated, full-spectrum extract of ashwagandha root. On day 60, the experimental group showed significant improvement in all applied stress assessment scales compared to placebo, and serum cortisol levels were clearly lower. The decrease was 27.9 percent from baseline, while in the placebo group it was 7.9 percent.
The full text of the study adds two things that the summary does not include, which change the way the result is read. The extract used is KSM-66, standardized by HPLC for a content of at least 5 percent withanolides, provided by the manufacturer, Ixoreal Biomed. This does not invalidate the result, but the reader has the right to know who supplied the tested preparation.
The rest of the limitations are typical for this field: one center, 64 people, two months of observation, lack of independent replication in the same setup. This is the strongest evidence available, which says as much about ashwagandha as it does about the state of the entire field.
Does vitamin B5 support the adrenals?
The biochemical basis is undeniable, but clinical evidence is practically non-existent, and the only direct study leads in the opposite direction than the guides suggest. Pantothenic acid is a precursor to coenzyme A, without which the synthesis of steroid hormones in the adrenal cortex does not occur. So much for the textbook.
Direct data must be sought in animals. Jaroenporn et al. (Biological and Pharmaceutical Bulletin, 2008) administered pantothenic acid to male rats in drinking water for nine weeks and then cultured their adrenal cells with corticotropin or prolactin or without them. The cells of the supplemented animals secreted more corticosterone and progesterone under basal conditions, and their response to corticotropin was stronger than that of control animals.
Note the direction of this result. The authors describe it as excessive adrenal reactivity to corticotropin stimulation. This is not “normalization” or “support for an exhausted gland,” but rather an enhancement of the response, and it was measured in rats, not in humans.
The good news is the prevalence of this vitamin in food. Poultry, eggs, avocados, and legumes provide enough of it that deficiency in a person eating a varied diet is rare. Until a study in humans with this endpoint is conducted, B5 remains a biochemical hypothesis rather than a proven intervention.
What is known about rhodiola and vitamin C?
Both have studies in humans, but they say something narrower than is summarized. Olsson, von Schéele, and Panossian (Planta Medica, 2009) conducted a double-blind study with 60 individuals meeting the Swedish criteria for fatigue syndrome. Thirty individuals received SHR-5 extract at a dose of 576 mg daily, thirty received placebo, for 28 days.
Improvement occurred in both groups, which the authors directly call a placebo effect. The extract gained an advantage over placebo in the Pines burnout scale and in some attention indicators in the CCPT II test, and the cortisol response to awakening stress differed significantly between groups. The authors’ conclusion: anti-fatigue action with improved concentration ability and reduced cortisol response to awakening in patients with burnout. We write more broadly about this plant in the post about rhodiola rosea.
Vitamin C has a study worth reading to the end. Brody et al. (Psychopharmacology, 2002) administered extended-release ascorbic acid or placebo for 14 days, with 60 healthy young individuals in each group, and then subjected participants to a standard social stress test, consisting of public speaking and counting in memory. In the vitamin C group, systolic blood pressure rose less than in the placebo group, and the subjective response to stress was milder.
However, cortisol behaved differently than the popular version claims. The return of cortisol in saliva to baseline values was faster, but the overall cortisol response was not smaller. The authors add that the described effects cannot be attributed to a change in adrenal reactivity. The statement about vitamin C, which “lowers cortisol and supports the production of adrenal hormones,” therefore contradicts the work cited as its evidence.
What other causes of fatigue should be ruled out?
Before chronic fatigue is attributed to the stress axis, one must go through a list of conditions that give an identical picture and have treatment with proven effectiveness. Each of them is diagnosed by examination, not an internet questionnaire.
- hypothyroidism and Hashimoto’s disease
- anemia and iron deficiency with low body stores
- type 2 diabetes and insulin resistance
- sleep apnea and other sleep-related breathing disorders
- depression and anxiety disorders that require psychiatric treatment
- vitamin B12 deficiency, described separately in the post about vitamin B12 and fatigue
The common feature of this list is simple: each item has a laboratory or imaging test that confirms or rules it out, and a course of action with documented effectiveness. Supplementation with adaptogens does not treat any of them and may delay diagnosis if it replaces a visit to the doctor. This is a practical reason why the order matters more here than the choice of preparation.
It is also worth noting the overlap of symptoms. Hypothyroidism, iron deficiency, and sleep apnea give the same picture as the described “adrenal fatigue”: morning exhaustion despite a full night’s sleep, decreased concentration in the afternoon, and poorer exercise tolerance. Without blood tests and an interview, they cannot be distinguished from one another, and each is treated differently. Therefore, the first step is a referral, not an order.
What to start with before reaching for a supplement?
With things that in stress research constitute the background of every intervention, not with a capsule. No preparation will compensate for the stimulus that maintains the stress response, and no clinical trial has tested a supplement in isolation from sleep, food, and movement.
Regular sleep times make the biggest difference, as the daily rhythm of cortisol secretion is directly related to them. It is about a consistent bedtime and wake-up time, even on weekends, and a dark and cool room. Irregular sleep undermines every other element of the plan.
The second element is glycemic stability. Sharp drops in glucose levels after a meal rich in simple sugars trigger a counter-regulatory response involving cortisol, so meals containing protein and fat smooth this path regardless of what else you take.
The third is moderate-intensity exercise spread throughout the week. A single intense effort temporarily raises cortisol, while regular activity is associated with a more favorable daily course. And the fourth element, the most difficult: naming the stressor that sustains it all. Without this step, the other three work uphill.
Frequently Asked Questions
Is adrenal fatigue an accepted medical diagnosis?
No. A systematic review by Cadegiani and Kater from 2016 included 58 cortisol studies and found no confirmation for this condition; the authors call it a myth. No endocrinological society recognizes it. The symptoms of fatigue and poor stress tolerance remain real.
Is it worth doing a cortisol profile from saliva?
Commercial assessments of the daily rhythm of cortisol in saliva belong to methods that the 2016 review indicated as non-standardized and not recognized by endocrinologists. Their result does not determine the diagnosis. Adrenal diagnostics is conducted by a doctor based on tests recommended in the guidelines.
How many people were studied in the ashwagandha trial?
Sixty-four individuals with a history of chronic stress, over 60 days, in a double-blind trial with placebo. Serum cortisol levels decreased by 27.9 percent from baseline, compared to 7.9 percent in the placebo group. The tested extract was provided by its manufacturer.
Does vitamin C lower cortisol?
Not in the way it is often repeated. In Brody’s 2002 study, ascorbic acid accelerated the return of cortisol in saliva to baseline values, but did not reduce the overall cortisol response. The authors note that the effect cannot be attributed to a change in adrenal reactivity.
Does vitamin B5 help with adrenal fatigue?
There are no human studies to confirm this. Pantothenic acid is a precursor to coenzyme A, needed for the synthesis of steroid hormones, but the only direct study in rats showed excessive adrenal reactivity to corticotropin, not normalization of their function.
When does fatigue require an urgent visit to a doctor?
When accompanied by persistent low blood pressure, low sodium levels in the blood, darkening of the skin, gums or scars, unexplained weight loss, or increased nausea and vomiting. The Endocrine Society guidelines recommend diagnostics for primary adrenal insufficiency in such cases.
Adaptogenic preparations in the store ubucha.pl are collected in the category adaptogens.
This article is for informational and educational purposes and does not constitute medical advice. Before starting supplementation, consult a doctor, especially if you are taking medications regularly, are pregnant or breastfeeding, or have a chronic illness.
Author: Michał Waluk · Published: 2026-05-28 · Updated: 2026-08-16