
Eucalyptol (cineole): refreshing terpene for the respiratory tract
Eucalyptol (1,8-cineole) in studies on sinuses and asthma: who studied, how many patients were involved, and how long. We also check how much has really been described in cannabis.
You inhale eucalyptus oil when you have a cold and soon breathe more freely. This effect is due to eucalyptol, also known as 1,8-cineole. Among the compounds associated with the aromatic profile of cannabis, it is a peculiar case, as its scientific evidence does not come from cannabis. It comes from capsules studied in patients with sinusitis and asthma, in several randomized trials conducted in Germany. Popular descriptions blur this boundary and attribute results obtained on a purified oral preparation to cannabis, while also providing the eucalyptol content in the dried product with precision to hundredths of a percent. This guide shows exactly what was measured in these trials, how many patients were involved, how long the treatment lasted, how much eucalyptol has actually been described in the literature on cannabis terpenes, and where what is known ends and what circulates on the internet without a source begins.
KEY INFORMATION
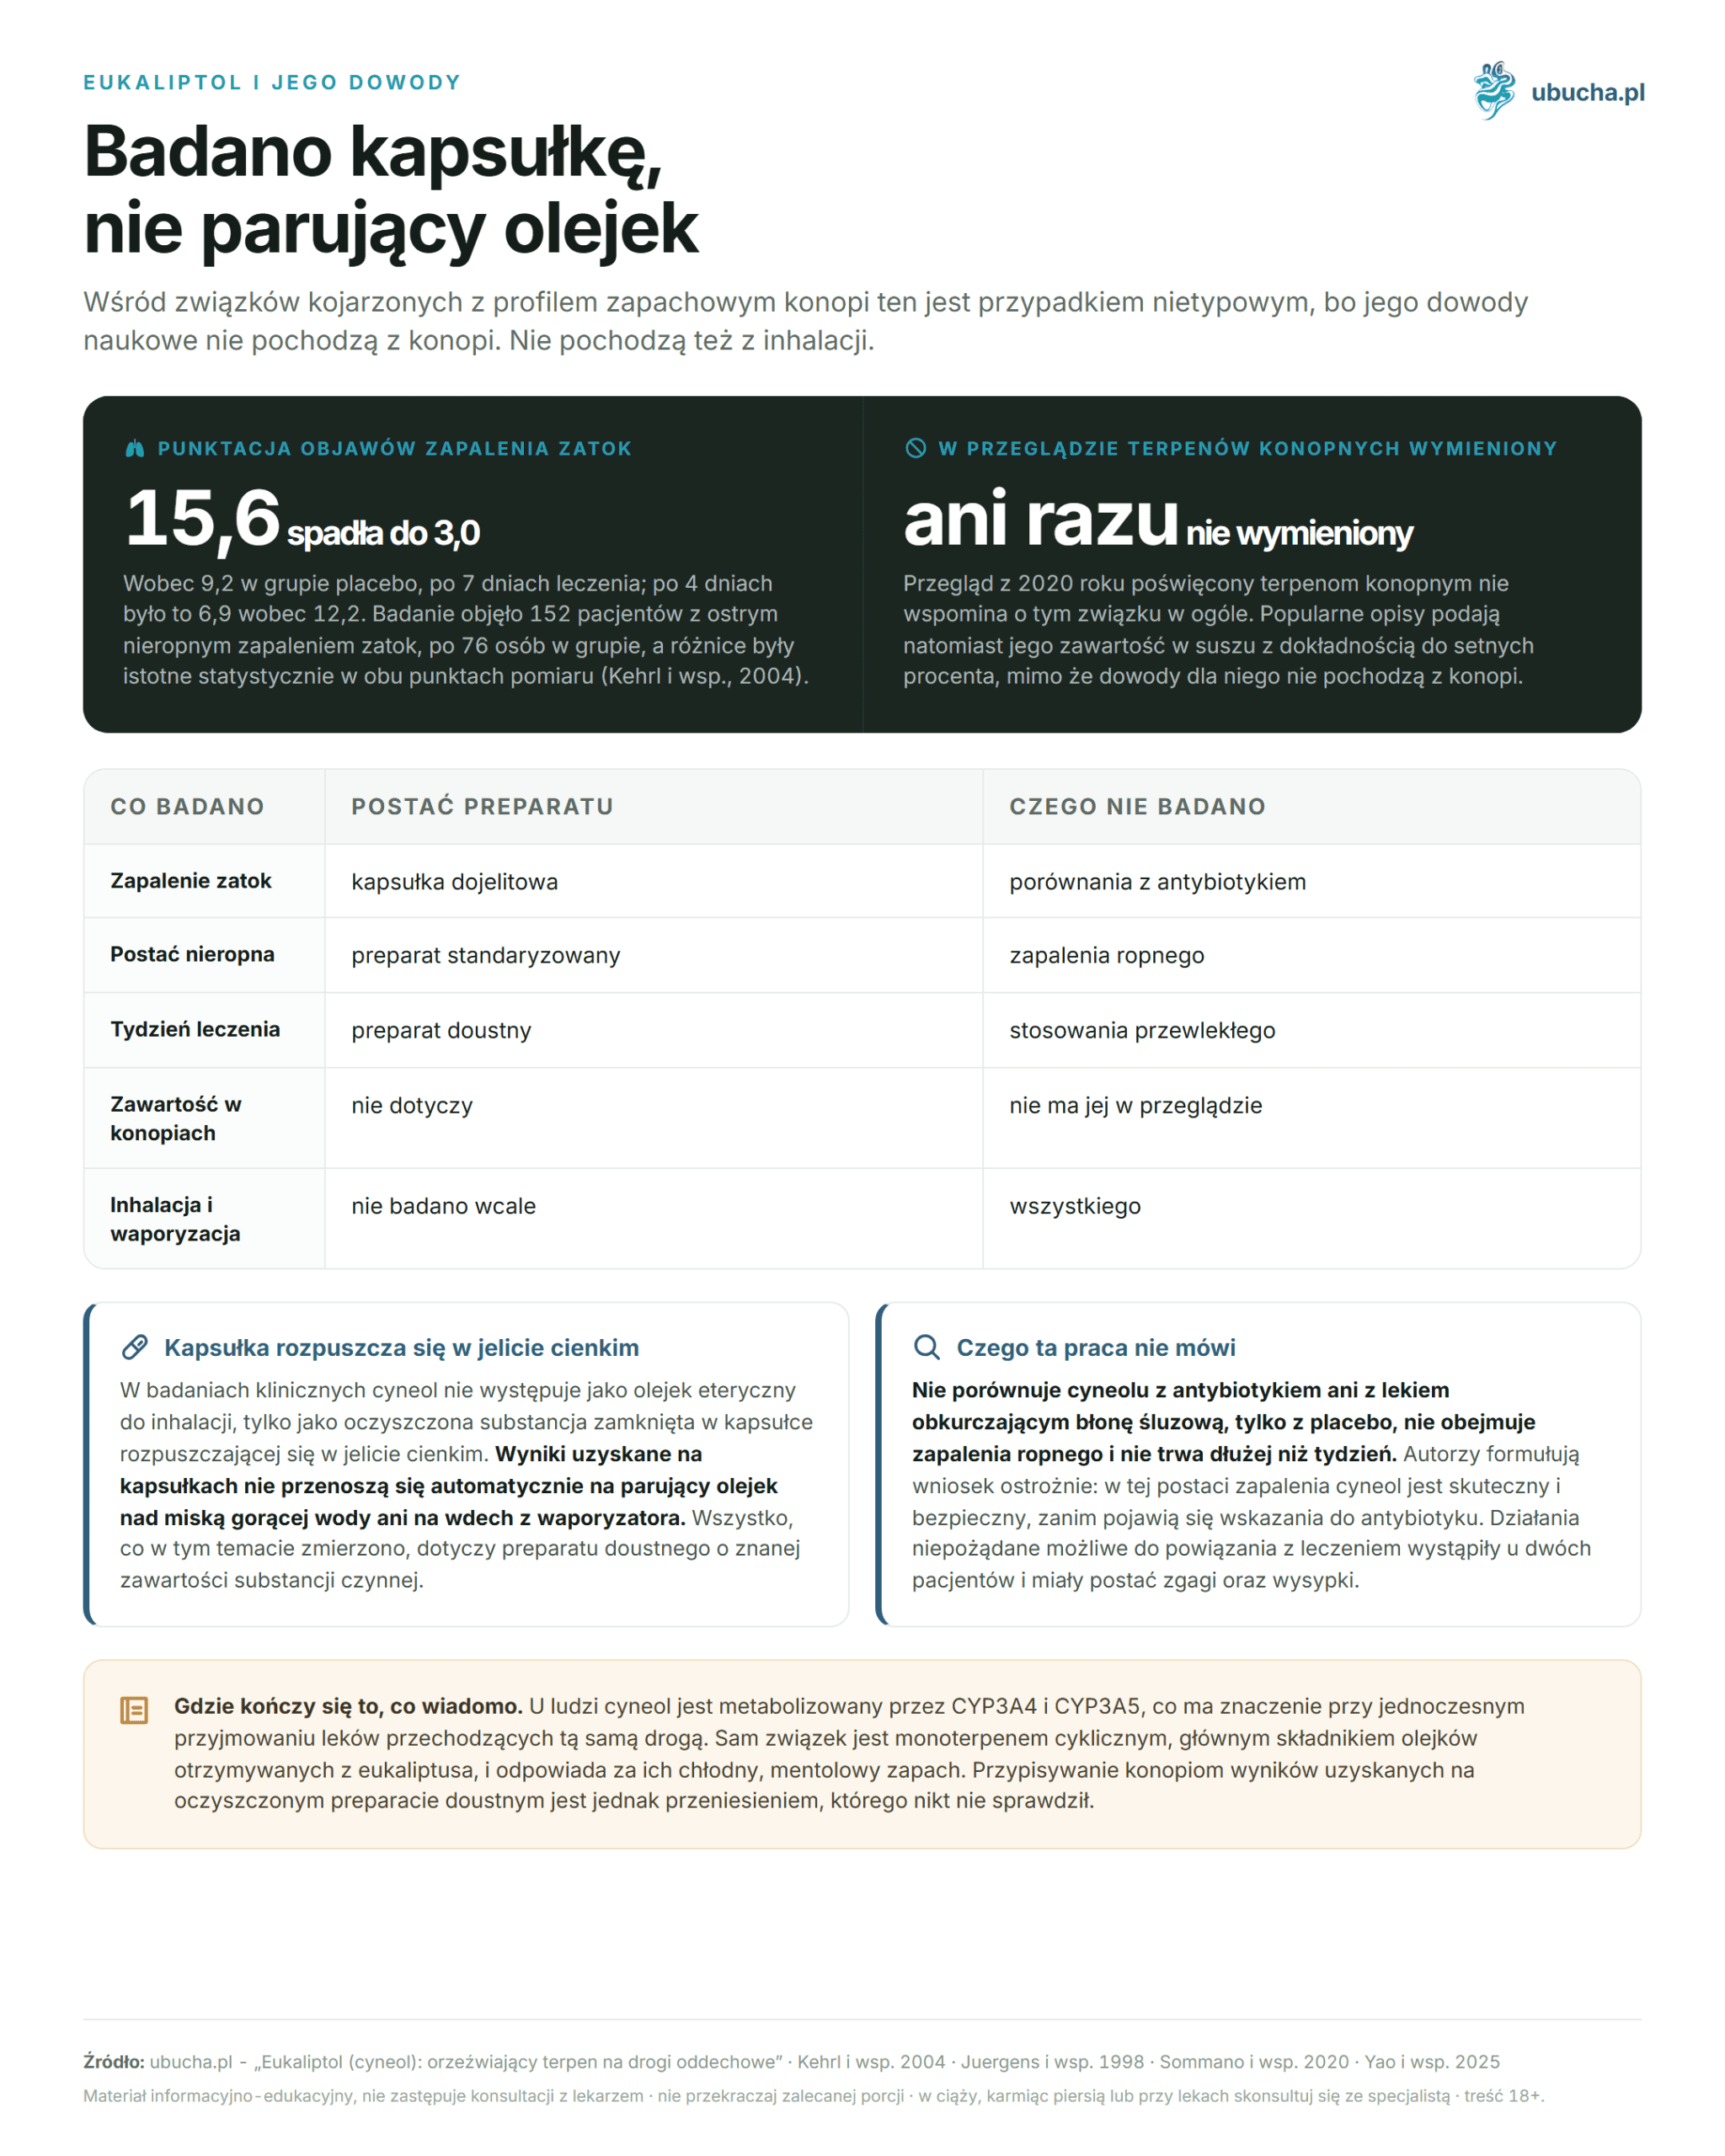
• In 152 patients with acute non-purulent sinusitis, the symptom score decreased after 7 days from 15.6 to 3.0, compared to 9.2 on placebo (Kehrl, Laryngoscope, 2004).
• Evidence pertains to a standardized oral preparation, not dried product or oil.
• The review of cannabis terpenes by Sommano et al. from 2020 does not mention eucalyptol even once.
• In humans, cineole is metabolized by CYP3A4 and CYP3A5.
What is eucalyptol and in which plants does it occur?
Eucalyptol is a cyclic monoterpene with the formula C10H18O, chemically recorded as 1,8-cineole. It is the main component of oils obtained from Eucalyptus species and is responsible for their cool, menthol scent. A review by Yao et al. from 2025 describes it as a compound widespread in plant, animal, and microbiological organisms (Molecular Biology Reports, 2025).
For assessing the evidence, one distinction is important that is easily overlooked. In clinical studies, cineole does not occur as an essential oil for inhalation, but as a purified substance enclosed in a capsule that dissolves in the small intestine. The preparation used in the studies by Juergens’ team is called Soledum and appears under that name in the description of methods (European Journal of Medical Research, 1998). Results obtained on capsules do not automatically transfer to vaporized oil over a bowl of hot water or inhalation from a vaporizer.
This distinction organizes the rest of the article. Everything we describe below as measured pertains to an oral preparation with a known content of active substance. The content of eucalyptol in cannabis is discussed separately, as the evidential situation looks completely different there. If you are interested in a broader background, we started it from the perspective of aromas in the text about what cannabis terpenes are.
Does cineole really help with sinuses?
In one randomized double-blind trial, yes. It involved 152 patients with acute non-purulent sinusitis and nasal mucosa, with 76 people in each group. The treatment lasted 7 days, and the primary endpoint was the change in total symptom score measured from baseline.
The starting score was 15.6 in both groups. After 4 days, it dropped to 6.9 in the cineole group and to 12.2 in the placebo group, and after 7 days to 3.0 and 9.2, respectively. The differences were statistically significant at both measurement points. The authors also noted improvement in secondary endpoints, including headache when bending, nasal congestion, and discharge (Kehrl et al., Laryngoscope, 2004).
It is worth noting what this study does not say. It does not compare cineole with an antibiotic or a decongestant, only with placebo. It does not include purulent inflammation. It does not last longer than a week, so nothing can be inferred about chronic use. The authors cautiously conclude: in this form of inflammation, cineole is effective and safe before indications for antibiotics arise. Adverse effects possibly related to treatment occurred in two patients and manifested as heartburn and rash.
What did studies show about cineole in asthma and COPD?
The second line of evidence concerns the lower respiratory tract and is narrower than popular descriptions suggest. All three studies collected in the table below have a common co-author: U. R. Juergens. This does not invalidate the results, but the reader has the right to know that these are not independent replications from different centers.
| Study | Who and how many participants | Time | Result |
|---|---|---|---|
| Juergens et al., European Journal of Medical Research, 1998 | 10 patients with bronchial asthma and 12 healthy individuals | 3 days | LTB4 production by monocytes decreased by 40.3% in asthma patients and by 57.9% in healthy individuals |
| Juergens et al., Respiratory Medicine, 2003 | 32 patients with steroid-dependent asthma, placebo-controlled double-blind trial | 12 weeks | Daily dose of prednisolone decreased by 36% compared to 7% on placebo; the dose was reduced by 12 out of 16 individuals compared to 4 out of 16 |
| Juergens et al., Advances in Therapy, 2020 | Review of previous randomized trials | Therapy added for 6 months | Improvement in lung function in uncontrolled asthma; in COPD, a decrease in exacerbations by 38.5% during the winter |
The mechanism described in the same review boils down to inhibiting the NF-kappa-B factor. At concentrations corresponding to plasma levels, around 1.5 micrograms per milliliter, cineole strongly inhibited the production of TNF-alpha and interleukins 1-beta, 6, and 8 in human monocytes (Juergens et al., Advances in Therapy, 2020). These are not measurements in patients, but on cells taken from humans, and that is how they should be read. A full description of the trial in patients with steroid-dependent asthma can be found in the paper from Respiratory Medicine from 2003.
How much eucalyptol is in cannabis?
The honest answer is: it is unknown, and the numbers circulating on the internet have no basis in review literature. We checked this in a way that anyone can repeat. We retrieved the full text of the review by Sommano et al. titled The Cannabis Terpenes from Europe PMC and counted the occurrences of the words “eucalyptol” and “cineole”. There are zero occurrences, with 101 occurrences of the word “terpene” (Molecules, 2020).
This same review discusses myrcene, limonene, pinene, linalool, and caryophyllene. Eucalyptol is not mentioned, even though it is one of the most frequently cited review papers on cannabis terpenes in recent years. Popular percentage ranges for eucalyptol in the terpene profile of cannabis and lists of strains allegedly rich in it do not come from such a source. If you come across such a number, check whether the paper cited actually contains it.
The practical conclusion for someone reading a laboratory test certificate is simple. The terpene profile provided with cannabis dried product describes compounds actually measured in that batch, and eucalyptol rarely makes it onto the list of measured analytes. Strains available in the dried product category differ in their aromatic profile, but the name of the strain says nothing about the content of a specific terpene. We discuss this trap further in the text about what the aroma says about the strain and what it does not.
Is eucalyptol safe and what about medications?
In the studies described above, the oral preparation was well tolerated. In 152 patients in Kehrl’s study, adverse effects possibly related to treatment occurred in two individuals. These are data from supervised weekly use, not from any use at home.
The essential oil is a separate matter. The review by Yao et al. from 2025 devotes a separate section to the toxicological issues of eucalyptol, which in itself indicates that the topic is not closed. Pure essential oils are not intended for drinking, and special caution is required with children. If you are looking for herbal ways to support cough, we have gathered evidence for one of them in the text about mullein for cough and respiratory tract.
As for medications, the data say less than is often repeated. Duisken et al. demonstrated in 2005 that in humans, 1,8-cineole is metabolized by isoenzymes CYP3A4 and CYP3A5. Antibody against CYP3A4/5 inhibited its hydroxylation in human liver microsomes, and the corresponding metabolites were confirmed in the urine of volunteers after taking a cold preparation (Biochimica et Biophysica Acta, 2005). Cineole thus uses the same metabolic pathway as many medications. What this means for someone taking medications regularly has not been studied in humans, so inform your doctor or pharmacist about regular use of cineole-containing preparations.
Frequently Asked Questions
What is eucalyptol?
Eucalyptol, or 1,8-cineole, is a cyclic monoterpene with the formula C10H18O and the main component of oils from Eucalyptus species. It is responsible for their cool, menthol scent. A review by Yao et al. from 2025 describes it as a compound widely distributed in plant, animal, and microbiological organisms, with antioxidant and anti-inflammatory properties.
Does eucalyptol help with sinuses?
In a randomized double-blind trial, 152 patients with acute non-purulent sinusitis took capsules with cineole or placebo for 7 days. The total symptom score decreased from 15.6 to 3.0 in the cineole group and to 9.2 in the placebo group (Kehrl et al., Laryngoscope, 2004). The study concerns the non-purulent form and weekly use.
What is known about cineole in asthma?
In a placebo-controlled double-blind trial involving 32 patients with steroid-dependent asthma, adding cineole for 12 weeks reduced the daily dose of prednisolone by 36%, compared to 7% on placebo. The dose was reduced by 12 out of 16 individuals compared to 4 out of 16 (Juergens et al., Respiratory Medicine, 2003). This is one trial from one team, not a standard treatment.
How much eucalyptol do cannabis plants contain?
We have not established a reliable range. The most frequently cited review of cannabis terpenes, Sommano et al. in Molecules from 2020, does not mention eucalyptol even once throughout the text. The percentage figures circulating on the internet and lists of strains allegedly rich in this terpene have no basis in this work.
Does eucalyptol interact with medications?
Duisken et al. demonstrated in 2005 that in humans, cineole is metabolized by CYP3A4 and CYP3A5, which are isoenzymes that also process many medications. Practical consequences of this fact for individuals taking medications regularly have not been confirmed in available summaries, so inform your doctor about regular use of cineole-containing preparations.
Can eucalyptus oil be ingested?
No. Clinical studies were conducted on purified cineole in enteric capsules, not on essential oil. The review by Yao et al. from 2025 discusses the toxicology of eucalyptol as a separate issue. Pure essential oils are not intended for consumption, and special caution is required with children.
This article is for informational and educational purposes only and does not constitute medical advice. Before starting to use cannabis or CBD for therapeutic purposes, consult your doctor, especially if you are taking other medications, are pregnant, or breastfeeding.
Author: Michał Waluk · Published: 2026-08-09 · Updated: 2026-08-16