



CBD for epilepsy and seizures: what medicine says and why CBD is legal
Cannabidiol is a registered drug for Dravet and Lennox-Gastaut epilepsy at a dose of 10-20 mg/kg. Check what distinguishes it from store oil.
Drug-resistant epilepsy in children is the only indication for which cannabidiol has undergone a full research path with randomization and has been registered as a drug. The FDA approved it in June 2018, and the EMA in September 2019. The evidence is strong, but it only concerns a pharmaceutical preparation administered at a dose of 10-20 mg per kilogram of body weight per day, under the supervision of a neurologist and together with clobazam. A whole bottle of oil from a supplement store is not enough for even one day of such therapy. Below you will find what exactly the registration studies showed, how large the gap is between the dose from the study and the portion from the supplement, what interactions with antiepileptic drugs have been documented, and who in Poland can currently receive cannabidiol as a reimbursed drug.
KEY INFORMATION
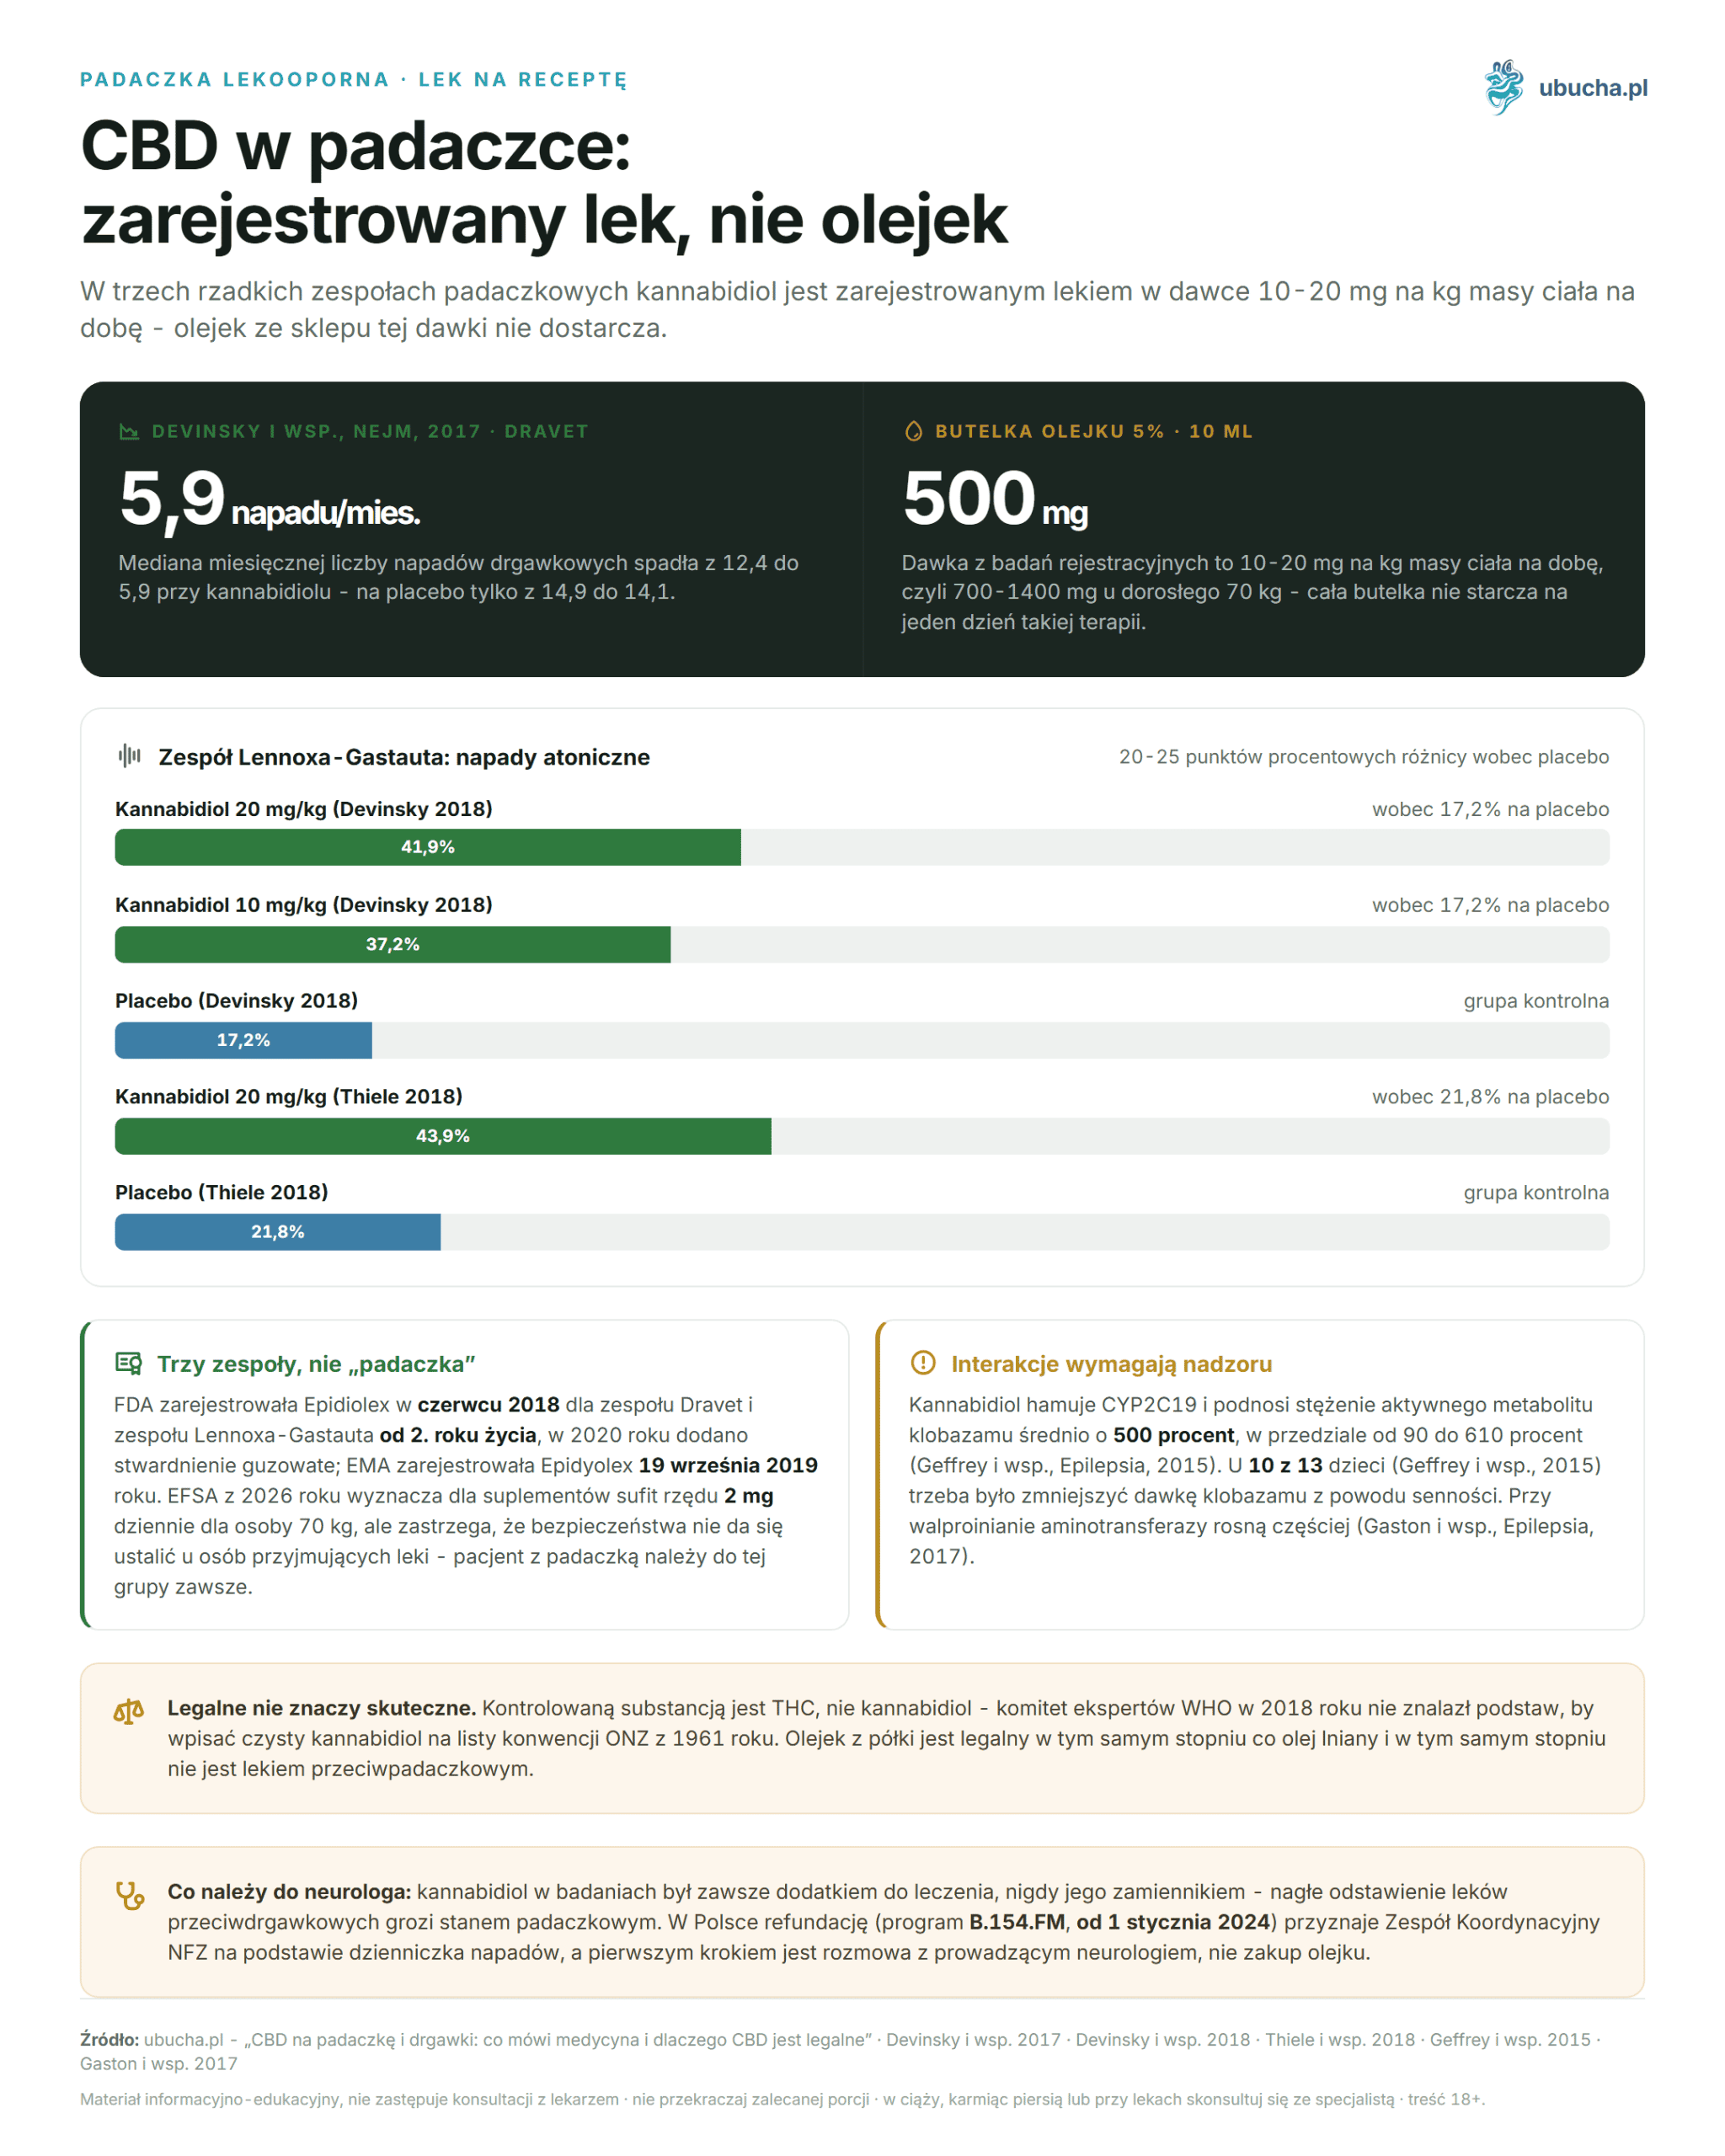
• In Dravet syndrome, the median monthly number of seizures decreased from 12.4 to 5.9 with cannabidiol and from 14.9 to 14.1 with placebo (Devinsky et al., NEJM, 2017).
• The dose from studies is 10-20 mg per kilogram of body weight per day, which is 700-1400 mg for an adult weighing 70 kg. A whole bottle of 5 percent oil with a capacity of 10 ml contains 500 mg.
• Cannabidiol was an adjunct to treatment in studies, never a substitute. Sudden withdrawal of antiepileptic drugs risks status epilepticus.
• The concentration of the active metabolite of clobazam increased by an average of 500 percent (Geffrey et al., Epilepsia, 2015).
Does CBD cure epilepsy?
Cannabidiol does not cure epilepsy, but in three rare epileptic syndromes, it reduces the number of seizures to such an extent that it has been registered as a drug. The registration only includes a pharmaceutical preparation, added to existing treatment. No dietary supplement with cannabidiol has such status or data.
In June 2018, the American FDA approved Epidiolex, an oral solution of purified cannabidiol at a concentration of 100 mg/ml, for the treatment of seizures in Dravet syndrome and Lennox-Gastaut syndrome in patients from the age of 2. In 2020, the indication was expanded to tuberous sclerosis. In the European Union, the same preparation is called Epidyolex and received marketing authorization on September 19, 2019.
The European indication is narrower than might be inferred from press headlines. Epidiolex has been registered as an adjunct therapy for seizures in Lennox-Gastaut syndrome or Dravet syndrome, in patients from the age of 2 and only in combination with clobazam. It is not a first-line drug, it is not monotherapy, and it is not a preparation that the patient chooses for themselves.
This boundary is often blurred in advertisements. The drug has a license number, a leaflet, a product characteristic, and a dose calculated per kilogram of body weight. The supplement has a registration number for products introduced to the market and a declaration from the manufacturer. The differences between the two categories have been described in more detail in our post about what distinguishes a dietary supplement from a drug.
What did the registration studies of cannabidiol show?
The basis for registration was three phase three studies in which patients were randomly assigned, and neither the patient nor the doctor knew who was receiving the drug. A total of 516 people with Dravet syndrome or Lennox-Gastaut syndrome were included. In each of them, cannabidiol was added to the treatment that the patient was already receiving, and the observation lasted 14 weeks.
In the study by Devinsky et al. (New England Journal of Medicine, 2017), 120 patients with Dravet syndrome received 20 mg/kg per day or placebo. The median monthly number of seizures decreased from 12.4 to 5.9 in the cannabidiol group and from 14.9 to 14.1 in the placebo group. This was the primary endpoint and favored the drug: the difference in medians was 22.8 percentage points with a confidence interval from 5.4 to 41.1 (p = 0.01).
The remaining numbers from this study should be read more cautiously. At least half of the seizures were lost by 43 percent of patients on cannabidiol compared to 27 percent on placebo, but the confidence interval for the odds ratio included one (from 0.93 to 4.30), and the result did not reach significance (p = 0.08). The same was true for the total cessation of seizures: 5 percent versus zero, also at p = 0.08. These two numbers circulate on the internet as evidence of efficacy, and they are not evidence.
How did the studies in Lennox-Gastaut syndrome perform?
Two studies concerned Lennox-Gastaut syndrome and measured atonic seizures, or sudden falls. Devinsky et al. (NEJM, 2018) in a group of 225 people achieved median reductions of 41.9 percent at 20 mg/kg and 37.2 percent at 10 mg/kg compared to 17.2 percent with placebo (p = 0.005 and p = 0.002). Thiele et al. (Lancet, 2018) in a group of 171 people measured 43.9 percent versus 21.8 percent, with an estimated median difference of 17.2 percentage points and a confidence interval from 4.1 to 30.3 (p = 0.0135).
It is worth reading these numbers carefully. The difference compared to placebo is within the range of 20-25 percentage points, so the real effect of cannabidiol alone is moderate, not spectacular. Previous treatment was not discontinued in any of these studies. In Thiele’s trial, adverse effects occurred in 74 out of 86 treated (86 percent) and in 59 out of 85 on placebo (69 percent); the most common were diarrhea and drowsiness, less frequently fever. In Devinsky’s 2018 study, elevated aminotransferase activity was noted in 14 patients, or 9 percent of those treated.
How much CBD was administered in studies, and how much does the store oil contain?
In registration studies, 10-20 mg of cannabidiol was administered per kilogram of body weight per day. For a child weighing 20 kg, this is 200-400 mg daily, and for an adult weighing 70 kg, from 700 to 1400 mg. Store oil does not have a dose established in any epilepsy studies, and the manufacturer provides the portion in drops, not in milligrams per kilogram. The most honest comparison is therefore through the content of the entire package.
| Parameter | Epidiolex (drug) | CBD oil (supplement) |
|---|---|---|
| Daily dose | 10-20 mg per kg of body weight | portion from the package, without conversion to body weight |
| Child 20 kg | 200-400 mg per day | dose not established in studies |
| Adult 70 kg | 700-1400 mg per day | dose not established in studies |
| Content of the package | oral solution 100 mg/ml | a 5 percent bottle with a capacity of 10 ml contains 500 mg |
| Supervision | prescription, monitoring of liver enzymes | none, sold over the counter |
| Evidence in epilepsy | three phase 3 studies with randomization | no studies in the indication |
We calculated this based on the bottles from our offer to make the scale visible. A 5 percent bottle with a capacity of 10 ml contains a total of 500 mg of cannabidiol. A child weighing 20 kg on the dose from the study would use such a bottle in one to two days. An adult weighing 70 kg would need one and a half to three bottles daily, every day, for many months.
Hence a simple conclusion. The results of registration studies say nothing about the action of the supplement, as the supplement does not provide the dose that was studied. Citing Devinsky and Thiele in the sale of oil is an abuse, even if the numbers themselves are presented correctly.
Can a CBD supplement replace antiepileptic drugs?
It cannot and should not. In all registration studies, cannabidiol was added to existing treatment, not substituted for it. Sudden withdrawal of antiepileptic drugs risks increasing seizures and status epilepticus, which is a prolonged seizure that is a life-threatening condition.
This warning is not a precautionary addition from the editorial team. The product characteristic of Epidiolex recommends gradually discontinuing cannabidiol itself. If such caution is required for withdrawing a drug that was only an adjunct, it is even more applicable to drugs that are the mainstay of therapy.
The risk also applies to adding a supplement on one’s own. Cannabidiol alters the concentrations of several antiepileptic drugs in the blood, so even without withdrawing anything, the therapy ceases to be what the neurologist planned. The result can be excessive drowsiness, and with an unfavorable arrangement, also loss of control over seizures.
Separately, it is worth knowing the limit set by the agency, not by the study of efficacy. In the updated EFSA position from 2026 established a provisional safe dose of cannabidiol at 0.0275 mg per kilogram of body weight per day, or about 2 mg daily for a person weighing 70 kg, and noted that it applies only to supplements with a purity of at least 98 percent. The same document states directly that the safety of cannabidiol cannot be established in individuals under 25 years of age, in pregnant and breastfeeding women, and in individuals taking medications. A patient with epilepsy always belongs to that last group.
Observational data are sometimes cited as a counterargument, but they say less than it seems. Tzadok et al. (Seizure, 2016) described 74 children with drug-resistant epilepsy who were given hemp oil with a cannabidiol to THC ratio of 20 to 1. Caregivers reported a reduction in the number of seizures in 89 percent of children, with 7 percent experiencing seizures that intensified to the point of discontinuing treatment. However, this 89 percent hides very different results: a reduction of at least three-quarters was reported in 18 percent of children, and in 26 percent, it did not even reach one-quarter. This was a retrospective observation, without blinding and without a control group, based on parental reports.
How does CBD interact with clobazam and valproate?
The best-documented interaction of cannabidiol in epilepsy concerns clobazam. Cannabidiol inhibits the CYP2C19 enzyme, which converts clobazam into N-desmethylclobazam, its active metabolite. The concentration of the metabolite increases, along with its antiepileptic action and the risk of excessive drowsiness.
Geffrey et al. (Epilepsia, 2015) measured this change in 13 children taking both drugs. The average increase in N-desmethylclobazam concentration was 500 percent, and clobazam itself increased by 60 percent. Both numbers are very uncertain: the standard deviation was 300 and 80 percent, respectively, the confidence interval for the metabolite reached from 90 to 610 percent after four weeks, and for clobazam itself from minus 2 to 91 percent, thus including zero. Adverse effects were reported in 10 out of 13 patients and resolved after reducing the dose of clobazam, which was done in 10 individuals. The number of seizures decreased by at least half in 9 out of 13 children, but with the simultaneous increase in clobazam concentration, it is impossible to separate how much of this was contributed by cannabidiol itself.
The second issue is the liver and valproate. Gaston et al. (Epilepsia, 2017) observed 39 adults and 42 children taking cannabidiol in doses ranging from 5 to 50 mg/kg and found that the activity of ALT and AST aminotransferases was significantly higher in individuals taking valproate simultaneously (p below 0.01). Valproate itself was not among the drugs whose concentration changed; the levels of clobazam, rufinamide, topiramate, zonisamide, and eslicarbazepine changed. So it is not about an increase in valproate concentration, but about the cumulative burden on the liver.
The scale of this phenomenon is evident in the open extension of both studies on Lennox-Gastaut syndrome. Thiele et al. (Epilepsia, 2019) included 366 patients and noted elevated aminotransferases in 37 of them, or 10 percent; 29 were taking valproate simultaneously, and 34 cases resolved spontaneously or after a dose change. The practical conclusion is one. Any combination of cannabidiol with antiepileptic drugs requires monitoring of drug concentrations and liver enzymes. We write more about this in our guide on drug interactions with cannabidiol.
Who in Poland can receive cannabidiol as a reimbursed drug?
As of January 1, 2024, Epidiolex is reimbursed in Poland under a drug program, not imported under targeted import. The Ministry of Health confirms that patients can access cannabidiol therapy in two drug programs: for Lennox-Gastaut syndrome and Dravet syndrome, as well as for seizures in the course of tuberous sclerosis.
The program for both epileptic syndromes is designated B.154.FM and is funded from the Medical Fund. Its description lists four entry conditions: age from 2 years, clinical diagnosis of Lennox-Gastaut syndrome or Dravet syndrome, lack of seizure control despite at least three antiepileptic drugs administered at the appropriate dose and for the appropriate time, and, when qualifying for cannabidiol, ongoing therapy with clobazam or starting it together with entry into the program. Fenfluramine is also funded in the same program, so one of the two substances is chosen.
The path is shorter than it was before 2024, but it is not automatic and does not end in the office of the attending neurologist. Qualification is determined by the Coordination Team appointed by the President of the National Health Fund, and a condition for submitting an application is a seizure diary maintained for at least six months before inclusion, from which the average monthly number of seizures is calculated. The same team then assesses efficacy. Before starting cannabidiol therapy, aminotransferases and total bilirubin are measured, and the maximum dose in the program is 10 mg/kg of body weight twice a day.
A practical note for parents. The first step is to talk to the attending neurologist, not to buy oil and inform the doctor afterward. If the center does not implement the program, it is worth asking for a referral to one that does. Patient associations for epilepsy help navigate this procedure and know the current list of centers.
What are Dravet syndrome and Lennox-Gastaut syndrome?
These are two severe childhood epilepsy encephalopathies, in which seizures usually do not respond to standard treatment. That is why they were chosen as the first indications for cannabidiol: the medical need was greatest there, and the available options were the weakest.
Dravet syndrome most often results from a mutation in the SCN1A gene, which encodes a sodium channel. Seizures begin in the first year of life, often with fever, and over time become polymorphic and frequent. The child’s development slows, and the risk of sudden death in epilepsy is increased. The situation is complicated by the fact that some classic sodium channel blockers may exacerbate seizures in this syndrome.
Lennox-Gastaut syndrome is diagnosed by the coexistence of several types of seizures, a characteristic slow spike-wave pattern in EEG, and cognitive developmental disorders. The biggest problem is atonic seizures, in which the child loses muscle tone and falls without warning, resulting in head and facial injuries. Most patients take several medications simultaneously and still do not achieve full seizure control.
Both syndromes meet the definition of drug-resistant epilepsy, which is the lack of seizure control after two properly selected and dosed medications. For this group of patients, cannabidiol is a real complement to therapy, not a trend.
How does cannabidiol affect neurons?
The exact mechanism is not known. Gray and Whalley (Epileptic Disorders, 2020) summarized preclinical data and stated directly that the way cannabidiol reduces the number of seizures in humans remains undetermined. However, the points of action where the molecule shows affinity are known.
The first is the vanilloid receptor TRPV1. Cannabidiol stimulates it, and prolonged stimulation leads to desensitization of the channel, which limits excessive calcium influx into the neuron. The second is the orphan receptor GPR55, whose endogenous agonist is lysophosphatidylinositol. Cannabidiol acts here as an antagonist and suppresses increased synaptic excitability. The third is the ENT-1 nucleoside transporter, whose inhibition raises the extracellular concentration of adenosine, which inhibits excitatory conduction.
It is worth noting what is not on this list. Cannabidiol is not an agonist of the CB1 receptor, so it does not act like THC, and it is not a classic sodium channel blocker like phenytoin or carbamazepine. This explains why it helps some patients for whom drugs with those mechanisms have failed, and why its side effect profile is also different.
For a reader without medical education, the conclusion is simple. Since it is not exactly known how it works, it is even harder to predict the effects of mixing it with other drugs without supervision. Similar reservations have been described in connection with cannabidiol in Parkinson’s disease.
Why is CBD legal if it comes from cannabis?
Because the controlled substance is THC, not cannabidiol. Pure cannabidiol has never been listed in the UN 1961 convention schedules on narcotic drugs, and the WHO expert committee in 2018 concluded that it does not exhibit addictive potential justifying such a listing.
The popular version of this story is sometimes distorted. In December 2020, the UN Commission on Narcotic Drugs removed cannabis and cannabis resin from Schedule IV of the 1961 convention, recognizing their therapeutic use. A separate recommendation regarding cannabidiol preparations was not adopted at that time, which did not change anything in practice, as cannabidiol itself was not listed in any schedule.
In Poland, the definition of industrial hemp matters, and its wording is more precise than the market repeats. According to Article 4 point 5 of the Act on Counteracting Drug Addiction (consolidated text Journal of Laws 2023, item 1939, as amended by the Act of March 24, 2022, Journal of Laws 2022, item 763), these are plants in which the sum of delta-9-THC and tetrahydrocannabinolic acid in flowering or fruiting tops, from which the resin has not been removed, does not exceed 0.3 percent in dry mass, with the sum rounded to one decimal place. Three things from this sentence are lost in the summary: the sum of two compounds matters, not just delta-9-THC, the threshold applies to the plant, not the finished product, and it has been in effect since May 7, 2022. Previously, it was 0.2 percent, so older articles provide this lower value.
However, legality says nothing about efficacy. Store oil is legal to the same extent as flaxseed oil and is not an antiepileptic drug to the same extent. A separate question concerns driving and screening tests, which we described in the post about CBD and drug tests.
Frequently asked questions
Does CBD cure epilepsy?
It does not cure, but it reduces the number of seizures in three rare syndromes. Devinsky et al. (NEJM, 2017) showed a decrease in the median monthly number of seizures from 12.4 to 5.9 with cannabidiol and from 14.9 to 14.1 with placebo. This refers to a drug added to therapy, not a supplement.
Will CBD oil from the store help with epilepsy?
There is no evidence for this. In studies, 10-20 mg per kilogram of body weight was administered daily, which is 700-1400 mg for an adult weighing 70 kg. A whole bottle of 5 percent oil with a capacity of 10 ml contains 500 mg, so it is not enough for even one day of such therapy. The results of studies on the drug do not transfer to the supplement.
Can antiepileptic drugs be discontinued after starting CBD?
No. In registration studies, cannabidiol was always an adjunct to treatment. Antiepileptic drugs are only discontinued gradually and under supervision, as sudden withdrawal risks increasing seizures and status epilepticus, which is a life-threatening condition. Any changes in therapy are determined by a neurologist.
How does CBD affect clobazam?
It raises the concentration of N-desmethylclobazam, the active metabolite of clobazam, by inhibiting the CYP2C19 enzyme. Geffrey et al. (Epilepsia, 2015) measured an average increase of 500 percent in children, and in 10 out of 13 patients, the dose of clobazam had to be reduced due to drowsiness.
Who in Poland can receive reimbursed cannabidiol?
Patients from the age of 2 with Lennox-Gastaut syndrome or Dravet syndrome, whose seizures persist despite at least three antiepileptic drugs. The drug program B.154.FM has been in effect since January 1, 2024, and cannabidiol therapy is conducted together with clobazam, with qualification determined by the Coordination Team appointed by the President of the National Health Fund, not the attending physician.
Why is CBD legal if it comes from cannabis?
Pure cannabidiol has never been listed in the UN 1961 convention schedules, and the WHO expert committee in 2018 found no basis to change that. In Poland, since May 7, 2022, industrial hemp is defined as plants in which the sum of delta-9-THC and tetrahydrocannabinolic acid in flowering or fruiting tops does not exceed 0.3 percent of dry mass (Article 4 point 5 of the Act on Counteracting Drug Addiction).
If you are looking for hemp products for daily use, you can find them in the oils section in the u Bucha store. These are dietary supplements, not antiepileptic drugs, and do not replace therapy conducted by a neurologist.
This article is for informational and educational purposes and does not constitute medical advice. Before starting to use cannabis or CBD for therapeutic purposes, consult a doctor, especially if you are taking other medications, are pregnant, or breastfeeding.
Author: Michał Waluk · Published: 2026-06-22 · Updated: 2026-08-15








