
CBD for Menstrual Pain: What Research Says and Women’s Opinions
The only study on CBD for menstrual disorders had no placebo. What do women's surveys say, where do forum doses come from, and when to see a gynecologist.
Painful menstruation is reported by 16% to 91% of women of reproductive age, depending on the studied population and the definition used, and pain so severe that it disrupts daily plans affects 2% to 29% (Ju et al., Epidemiologic Reviews, 2014). Given this scale, every new proposal spreads quickly, and CBD has spread exceptionally fast. Before you buy oil, it is worth knowing something you won’t find in product descriptions: the entire body of evidence consists of one interventional study without a placebo group and a handful of surveys. This text shows what has really been studied, where the numbers circulating on forums come from, how to read surveys among women using cannabis, and how to recognize pain that requires a gynecologist instead of a supplement.
KEY INFORMATION
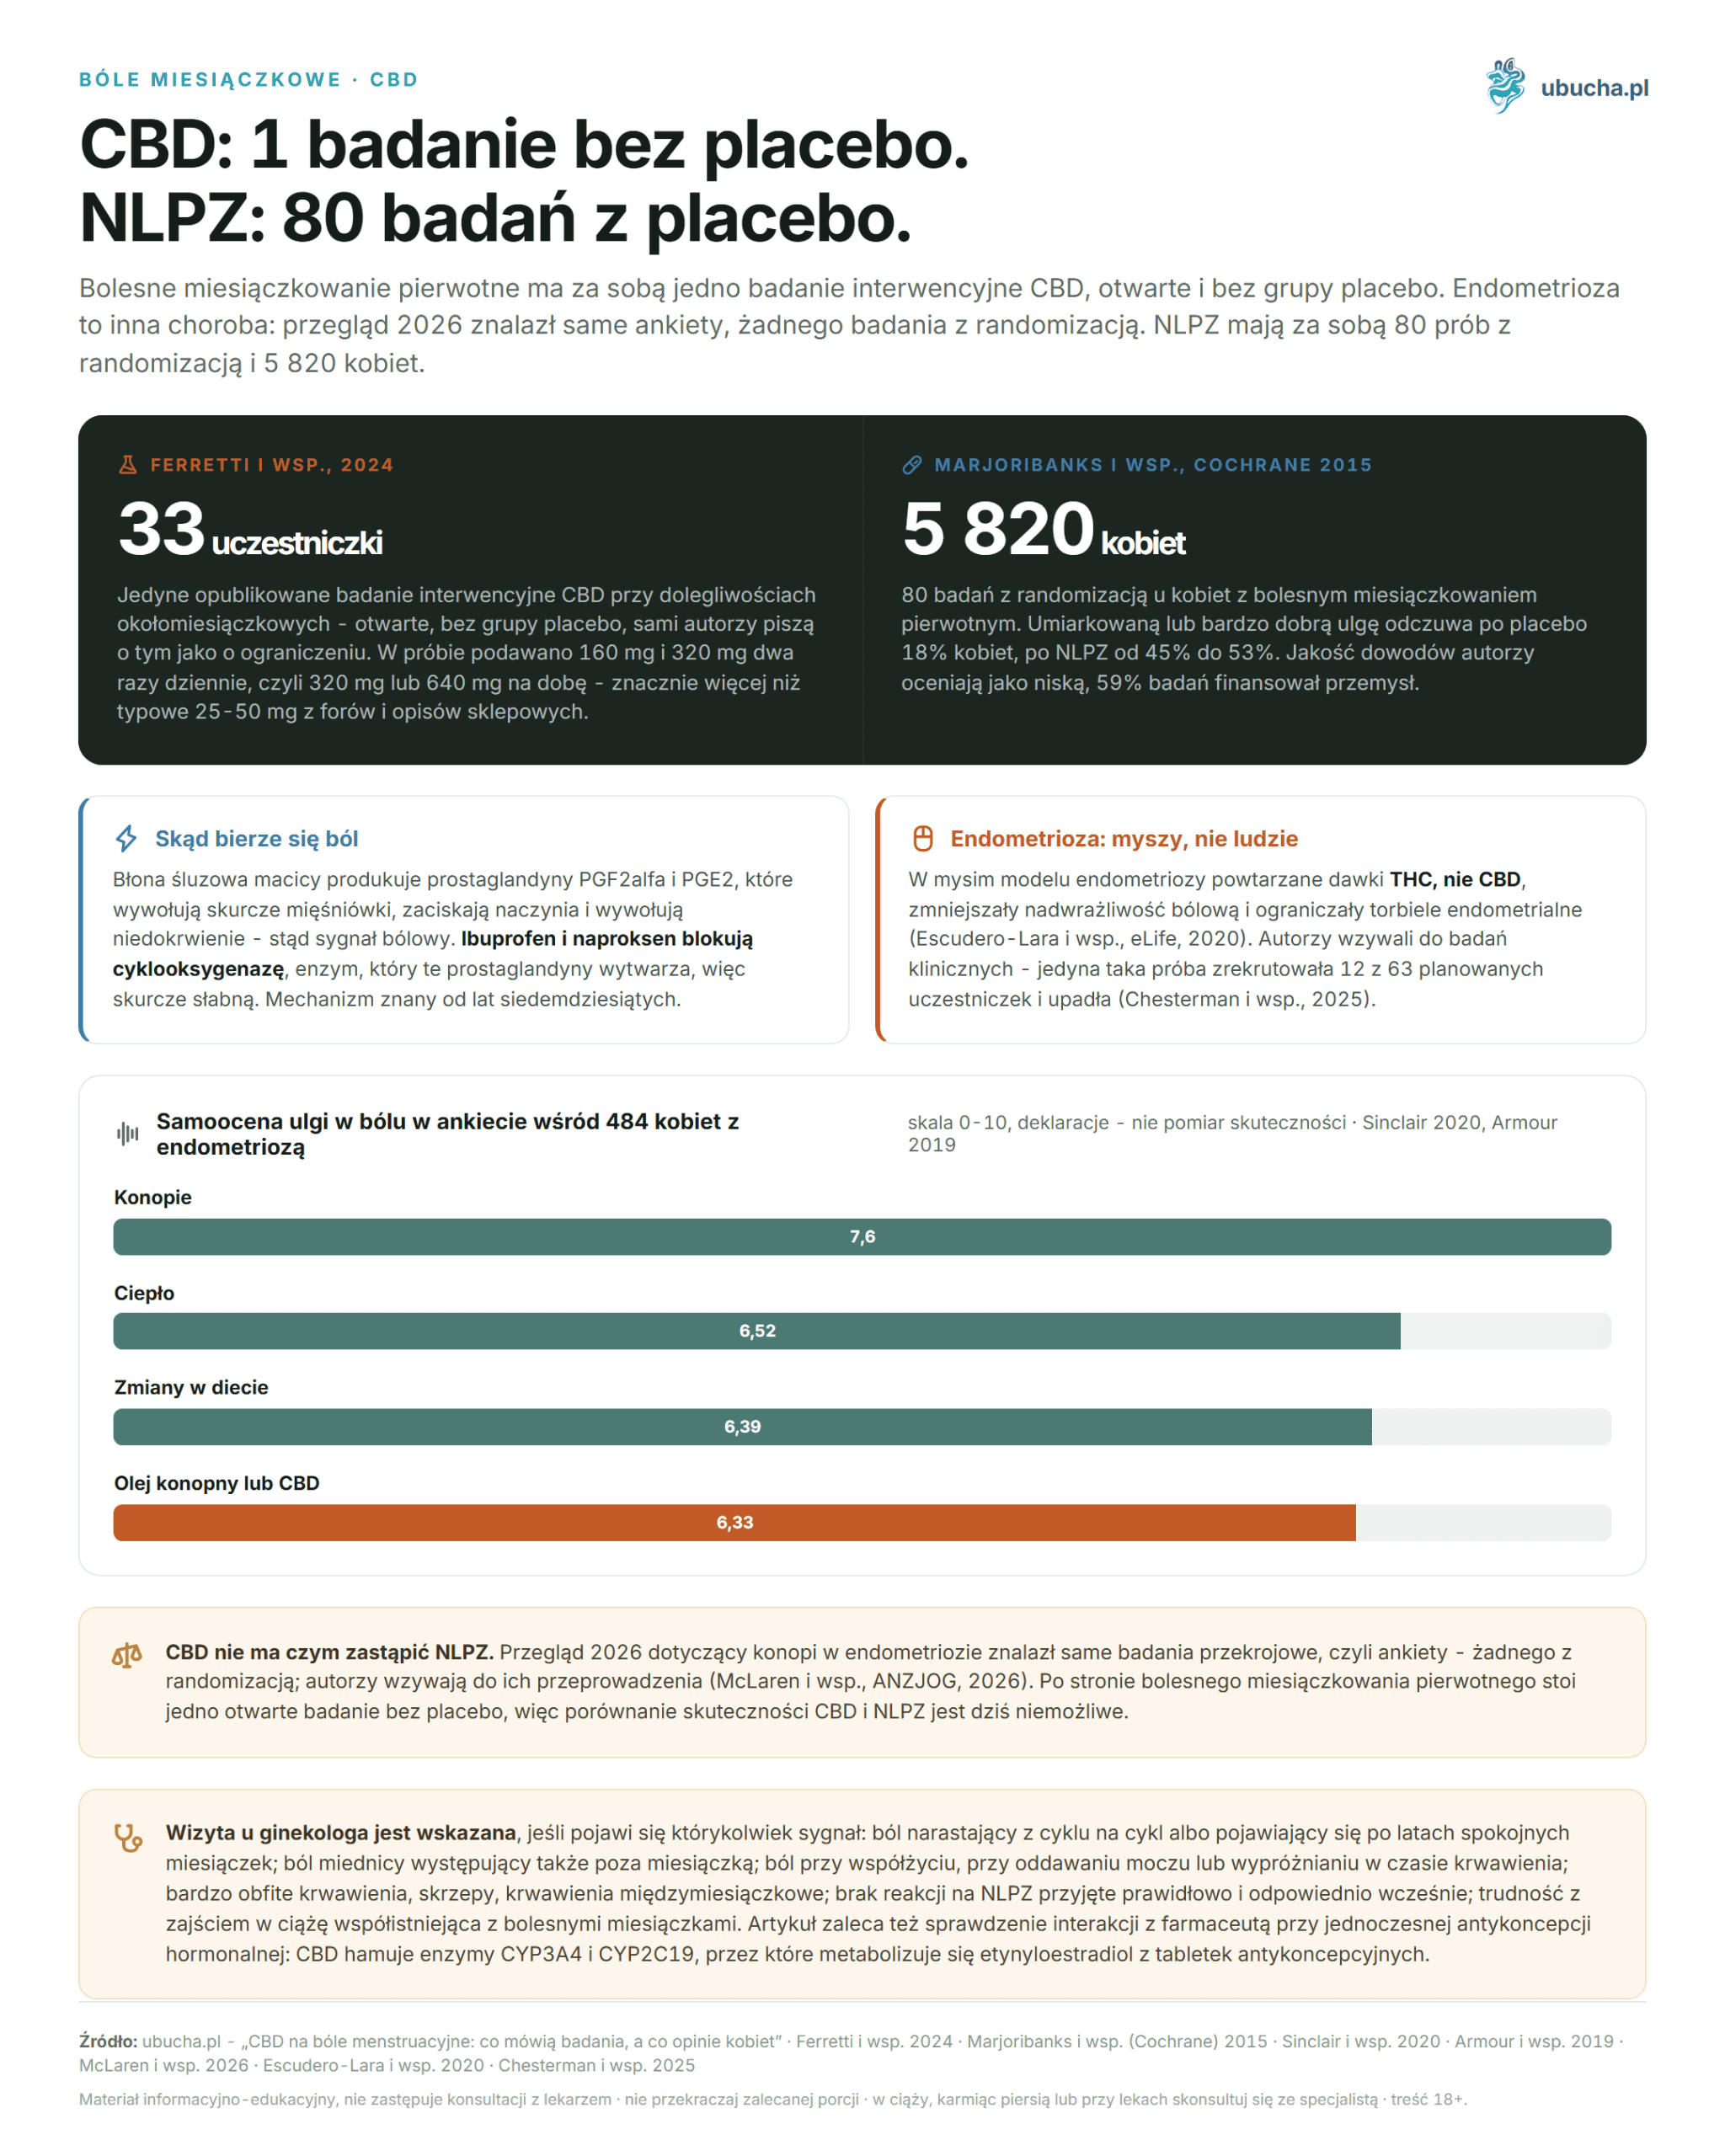
• The only published interventional study on CBD for menstrual disorders involved 33 participants and had no placebo group, which the authors themselves indicate as a limitation (Ferretti et al., Experimental and Clinical Psychopharmacology, 2024).
• In a survey of 484 Australian women with endometriosis, 13% of those who used home remedies reported using cannabis, and self-reported pain relief was 7.6 out of 10 (Sinclair et al., JOGC, 2020). This is a declaration, not a measurement.
• NSAIDs have 80 randomized studies and 5,820 participants (Marjoribanks et al., Cochrane, 2015).
• There is no established dose of CBD for menstrual pain because there is no placebo study that could determine it.
• Pain increasing from cycle to cycle, pain outside of menstruation, and pain resistant to NSAIDs are indications for diagnostics, not supplementation.
Does CBD relieve menstrual pain?
It is unknown because it has not been tested against placebo. However, there is one interventional study worth knowing because it is often overlooked on both sides of the debate. The Ferretti team provided 33 participants with CBD isolate in capsules for five consecutive days each month for three months, in two dosing groups: 160 mg and 320 mg twice a day. The severity of menstrual-related symptoms, irritability, anxiety, and perceived stress decreased in both groups compared to the baseline month, while depression scores did not change (Ferretti et al., Experimental and Clinical Psychopharmacology, 2024).
The limitation of this study is fundamental, and the authors themselves write about it: it was open-label, without a placebo group. The condition after CBD was compared to the condition before CBD in the same individuals, not to anything parallel. In a condition that naturally varies in intensity between cycles and is accompanied by strong expectations of relief, such a setup does not determine effectiveness. In the ClinicalTrials.gov registry, the study is listed under number NCT05679830 as completed, with no published results in the registry itself.
The second registered study never took place. A phase two trial NCT04091789, planned for 30 participants, was supposed to test a sublingual tablet containing 30 mg of CBD, 1 mg of THC, palmitoylethanolamide, and a blend of terpenes. The last update of the entry is from September 2019, results were never published, and the status is listed as unknown. Even if it had concluded, it would not have answered the question about CBD alone, as the tablet combines several substances at once.
Endometriosis stands apart. A systematic review from 2026 gathered thirteen studies on cannabis in this disease, of which nine were completed, and all were cross-sectional, meaning survey-based (McLaren et al., ANZJOG, 2026). The authors state directly that there is a lack of prospective randomized studies and that they need to be conducted. This is not the same as saying “CBD does not work”: the question remains open, and anyone who answers it affirmatively goes beyond the data.
What causes menstrual pain?
Prostaglandins. The endometrium produces prostaglandins PGF2alpha and PGE2 before and during menstruation, which cause strong contractions of the myometrium. The contractions constrict blood vessels, leading to temporary ischemia of the uterine wall, and the ischemic tissue sends a pain signal. This is primary dysmenorrhea, meaning it is not caused by any reproductive organ disease.
Prostaglandins are produced with the help of cyclooxygenase, an enzyme that exists in two forms, COX-1 and COX-2. This is the basis of the entire pharmacology of menstrual pain: ibuprofen and naproxen block cyclooxygenase, thus reducing the production of prostaglandins and weakening contractions. The mechanism has been known since the 1970s, which explains why NSAIDs taken early work better than those taken at the peak of pain.
The frequency of the problem is reported very differently because different studies define “pain” differently. A review of fifteen population studies reports a range from 16% to 91%, with pain limiting daily functioning reported by 2% to 29% of respondents (Ju et al., Epidemiologic Reviews, 2014). The same study shows that symptoms weaken with age, after childbirth, and with the use of oral contraception, while they intensify with high levels of stress. Family history is the strongest single factor here: odds ratios ranged from 3.8 to 20.7, while other factors gave values between 1 and 4.
What do surveys among women using cannabis show?
They show high self-reported relief and nothing more. The most frequently cited work is an Australian online survey from late 2017 and early 2018, in which 484 women with surgically confirmed endometriosis described their coping methods for symptoms. 76% of them resorted to home remedies, and 13% of that subgroup used cannabis, not 13% of the entire sample. The average pain relief rating was 7.6 out of 10, and 56% reported that they reduced their medication doses by at least half (Sinclair et al., JOGC, 2020). This difference in the denominator returns in citations of this work regularly and inflates the scale of the phenomenon each time.
We noticed while checking sources something that is easy to overlook: the second frequently referenced work, Armour et al. (BMC Complementary and Alternative Medicine, 2019), is not an independent confirmation. It is the same survey, the same 484 responses, just described from a broader perspective. When both texts appear side by side as “studies”, it creates the illusion of two consistent results where there is one data set.
This second analysis provides ratings for all home remedies: heat 6.52, dietary changes 6.39, hemp oil or CBD 6.33, cannabis 7.6 out of ten. A review from 2026 gathered nine such studies, totaling 1,787 participants. Adverse effects were reported by 10.2% to 52% of participants, most often intoxication and dry mouth.
Why is self-assessment by users not evidence of effectiveness?
Because the survey has nothing to compare the result to. Only those who already use something respond, so people for whom the method did not help and who abandoned it do not enter the sample at all. Recruitment through support groups on social media further narrows the circle to those engaged in the topic. Without a placebo group, it is impossible to separate the action of the substance from expectations.
Menstrual pain is particularly susceptible to the illusion of effectiveness. It has a natural peak and a natural drop within one or two days, so anything taken at the peak will appear to work well when assessed afterward. The intensity also changes between cycles, which with two or three trials can easily be mistaken for the effect of the preparation.
That this is not a theoretical accusation is shown by an Australian attempt to conduct a proper study. The team planned 63 participants in three groups, including a group with just CBD oil and a placebo group. They randomized 12 people, seven withdrew during the study, and four completed it (Chesterman et al., Complementary Therapies in Clinical Practice, 2025). The main reason was the prohibition of driving during participation. Meanwhile, the market does not wait: an analysis of two American cannabis sales platforms found 408 offers, which made a total of 465 health claims for women. 57.2% of these claims were related to the menstrual cycle, and any health warning was found in 6.6% of the offers (Nali et al., American Journal of Preventive Medicine, 2026).
How much CBD should I take for painful menstruation?
There is no such dosage. Dosage is established in studies that compare several dosage sizes with placebo and check at which the effect outweighs adverse effects. No such placebo study has been conducted for painful menstruation, so there is no number that can be honestly provided as a recommendation.
Note how far apart the numbers from forums and the numbers from the only study are. On forums and in store descriptions, 25-50 mg per day or “five drops of 10% oil” is repeated. In the Ferretti study, both groups received significantly more: 160 mg or 320 mg twice a day, which is 320 mg or 640 mg per day, and that only for five days a month. This is not a dosage guideline because the study had no placebo. It shows that forum numbers do not come from there but from studies on completely different issues: anxiety, sleep, drug-resistant epilepsy. There is also no standard unit: the same “drop” means different substance content in each preparation.
It is worth remembering that a higher dose is not a safer version just because it is a supplement. A review of the characteristics of registered products found adverse effects in nearly half of users, depending on the dose. The authors list increased aminotransferase activity, drowsiness, sleep disturbances, infections, and anemia (Brown and Winterstein, Journal of Clinical Medicine, 2019). If you still want to try despite the lack of data, treat it as an experiment on yourself, not as therapy, and inform your attending physician about it. Especially if you are taking anything regularly.
When does menstrual pain require diagnostics rather than a supplement?
When it changes character. Primary dysmenorrhea usually begins within two years of the first menstruation, lasts one to three days, and tends to weaken with age. If your pain behaves differently, it may be a symptom of a disease, and then no over-the-counter preparation will solve the problem, only cover it.
Signals that are worth scheduling a gynecologist appointment for:
- pain increasing from cycle to cycle or appearing after years of regular menstruation
- pelvic pain occurring outside of menstruation
- pain during intercourse, urination, or bowel movements during bleeding
- very heavy bleeding, clots, intermenstrual bleeding
- no response to NSAIDs taken correctly and in a timely manner
- difficulty getting pregnant associated with painful menstruation
Such a picture usually indicates secondary dysmenorrhea: endometriosis, adenomyosis, uterine fibroids, or a history of pelvic inflammatory disease. Endometriosis affects 6-10% of women of reproductive age (McLaren et al., ANZJOG, 2026). In a study involving 1,418 women in sixteen centers across ten countries, it took an average of 6.7 years from the first symptoms to surgical diagnosis, mainly due to delays at the primary healthcare level; where care was publicly funded, the delay was 8.3 years compared to 5.5 years in other centers (Nnoaham et al., Fertility and Sterility, 2011). Every month of masking pain with a supplement adds to this average. More about the disease itself is discussed in the post CBD for Endometriosis.
What really has evidence for painful menstruation?
First of all, NSAIDs. A Cochrane review included 80 randomized studies and 5,820 women with primary dysmenorrhea. If 18% of women feel moderate or very good relief after placebo, 45% to 53% feel it after NSAIDs (Marjoribanks et al., Cochrane Database of Systematic Reviews, 2015). The price is more frequent adverse effects overall: if 10% of women report them after placebo, 11% to 14% report them after NSAIDs. Gastrointestinal complaints and neurological symptoms were counted separately, and there the odds ratio was clearer. The authors of the review assess the quality of evidence as low, and 59% of the included studies were funded by industry.
The second verified option is hormonal contraception, which reduces the thickness of the endometrium and thus the production of prostaglandins. Among non-pharmacological methods, the best support in the data comes from local heat and regular aerobic exercise; others, from acupuncture to dietary supplements, are based on weaker studies and should complement treatment, not replace it (Kirsch et al., Journal of Pain Research, 2024).
Interestingly, women seek cannabis for various reasons. In a qualitative study involving 26 Australian women with primary dysmenorrhea, the most common reason was dissatisfaction with over-the-counter medications, not a belief in the superiority of cannabis (Sinclair et al., IJERPH, 2022). The authors conclude that clinical studies in this group are urgently needed. Four years later, there is still not a single one with a placebo. If you are looking for options with harder data than CBD, we describe the comparison of ginger with ibuprofen in the post Ginger for Painful Menstruation, and we discuss cannabis preparations in the text CBD Dosage.
Does CBD interact with pain medications and contraception?
It may interact, and this has not been studied in this context. CBD inhibits cytochrome P450 enzymes, including CYP3A4 and CYP2C19, through which a large portion of medications is metabolized, including ethinyl estradiol from contraceptive pills. It is known that this phenomenon exists. It is unknown at what dosage of the supplement it becomes clinically significant because no one has conducted such a study in women using contraception.
This uncertainty works both ways, so we will not write here either “it is safe” or “it poses a risk of pregnancy”. The decision should be discussed with someone who knows your list of medications. A pharmacist can check interactions in a few minutes, and it costs nothing.
Separately, it is worth noting where the belief in the action of cannabis on the disease itself comes from. In a mouse model of endometriosis, repeated doses of THC reduced pain sensitivity and limited the development of endometrial cysts (Escudero-Lara et al., eLife, 2020). This was THC, not CBD, in mice, not humans, and the authors explicitly called for clinical studies. The only attempt at such a study, described above, failed at the recruitment stage. Transferring results from mice to women and from THC to CBD is two jumps at once, and neither has data support.
Frequently Asked Questions
Does CBD help with menstrual pain?
It is unknown. The only published interventional study (Ferretti et al., 2024) was open-label and did not have a placebo group, so it does not determine effectiveness. Besides that, there are surveys, and a survey shows what people declare, not whether the substance works.
How much CBD should I take for menstrual pain?
There is no dosage because there is no placebo study that could determine it. Numbers from forums, most often 25-50 mg per day, were transferred from studies on anxiety, sleep, and epilepsy. In the only interventional study, the doses were multiple times higher. Discuss the use of the supplement with a doctor or pharmacist.
Is CBD safe during menstruation?
This has not been studied separately. However, it is known that CBD inhibits cytochrome P450 enzymes and may change the concentration of other medications. Adverse effects, including increased aminotransferase activity, drowsiness, and sleep disturbances, have been reported in nearly half of those using registered products (Brown and Winterstein, 2019).
Does CBD help with endometriosis?
There is no evidence from clinical studies. A review from 2026 found nine completed studies on cannabis in endometriosis, and all were cross-sectional. An Australian randomized trial from 2025 recruited 12 out of the planned 63 participants, so it did not provide answers about effectiveness or safety.
Can CBD oil replace ibuprofen?
There is no basis for such a substitution. NSAIDs have 80 randomized studies involving 5,820 women with primary dysmenorrhea (Marjoribanks et al., Cochrane, 2015). On the side of CBD, there is one study without a placebo group, so comparing the effectiveness of both options is impossible.
When should menstrual pain be concerning?
When it increases from cycle to cycle, occurs outside of menstruation, is accompanied by pain during intercourse or bowel movements, or when NSAIDs stop working. These are typical signals of secondary dysmenorrhea. Endometriosis affects 6-10% of women of reproductive age, and diagnosis takes an average of 6.7 years from the first symptoms.
The starting point for painful menstruation remains NSAIDs, hormonal contraception, heat, and movement, while for pain changing character, gynecological diagnostics. CBD has one study in this indication without a placebo group, and it should be treated as an untested practice that some women use at their own risk. If you still want to check how it works for you, browse the category cannabis oils and talk to your doctor beforehand.
This article is for informational and educational purposes and does not constitute medical advice. Before starting to use cannabis or CBD for therapeutic purposes, consult your doctor, especially if you are taking other medications, are pregnant, or breastfeeding.
Author: Michał Waluk · Published: 2026-06-22 · Updated: 2026-08-15