
Supplements for Autumn Blues and SAD: What Really Helps (Ranking)
Ranking of supplements for autumn blues and SAD according to the strength of evidence: saffron, omega-3, vitamin D3, magnesium, ashwagandha. Prices from the store, status 08.2026.
In autumn, the day in Poland shortens by half, and along with it, mood, energy, and the desire to go out decline. For some people, this ends in seasonal lethargy. For others, it develops into seasonal affective disorder (SAD), a clinically recognized form of depression with a winter rhythm. The supplement market offers a ready answer to this. We checked what withstands contact with research: we read the studies cited by manufacturers and then compared them with what is actually on our shelf. The ranking below arranges seven substances according to the strength of evidence, not according to margin. We start with the most important thing, which is the boundary beyond which a supplement ceases to be an answer.
KEY INFORMATION
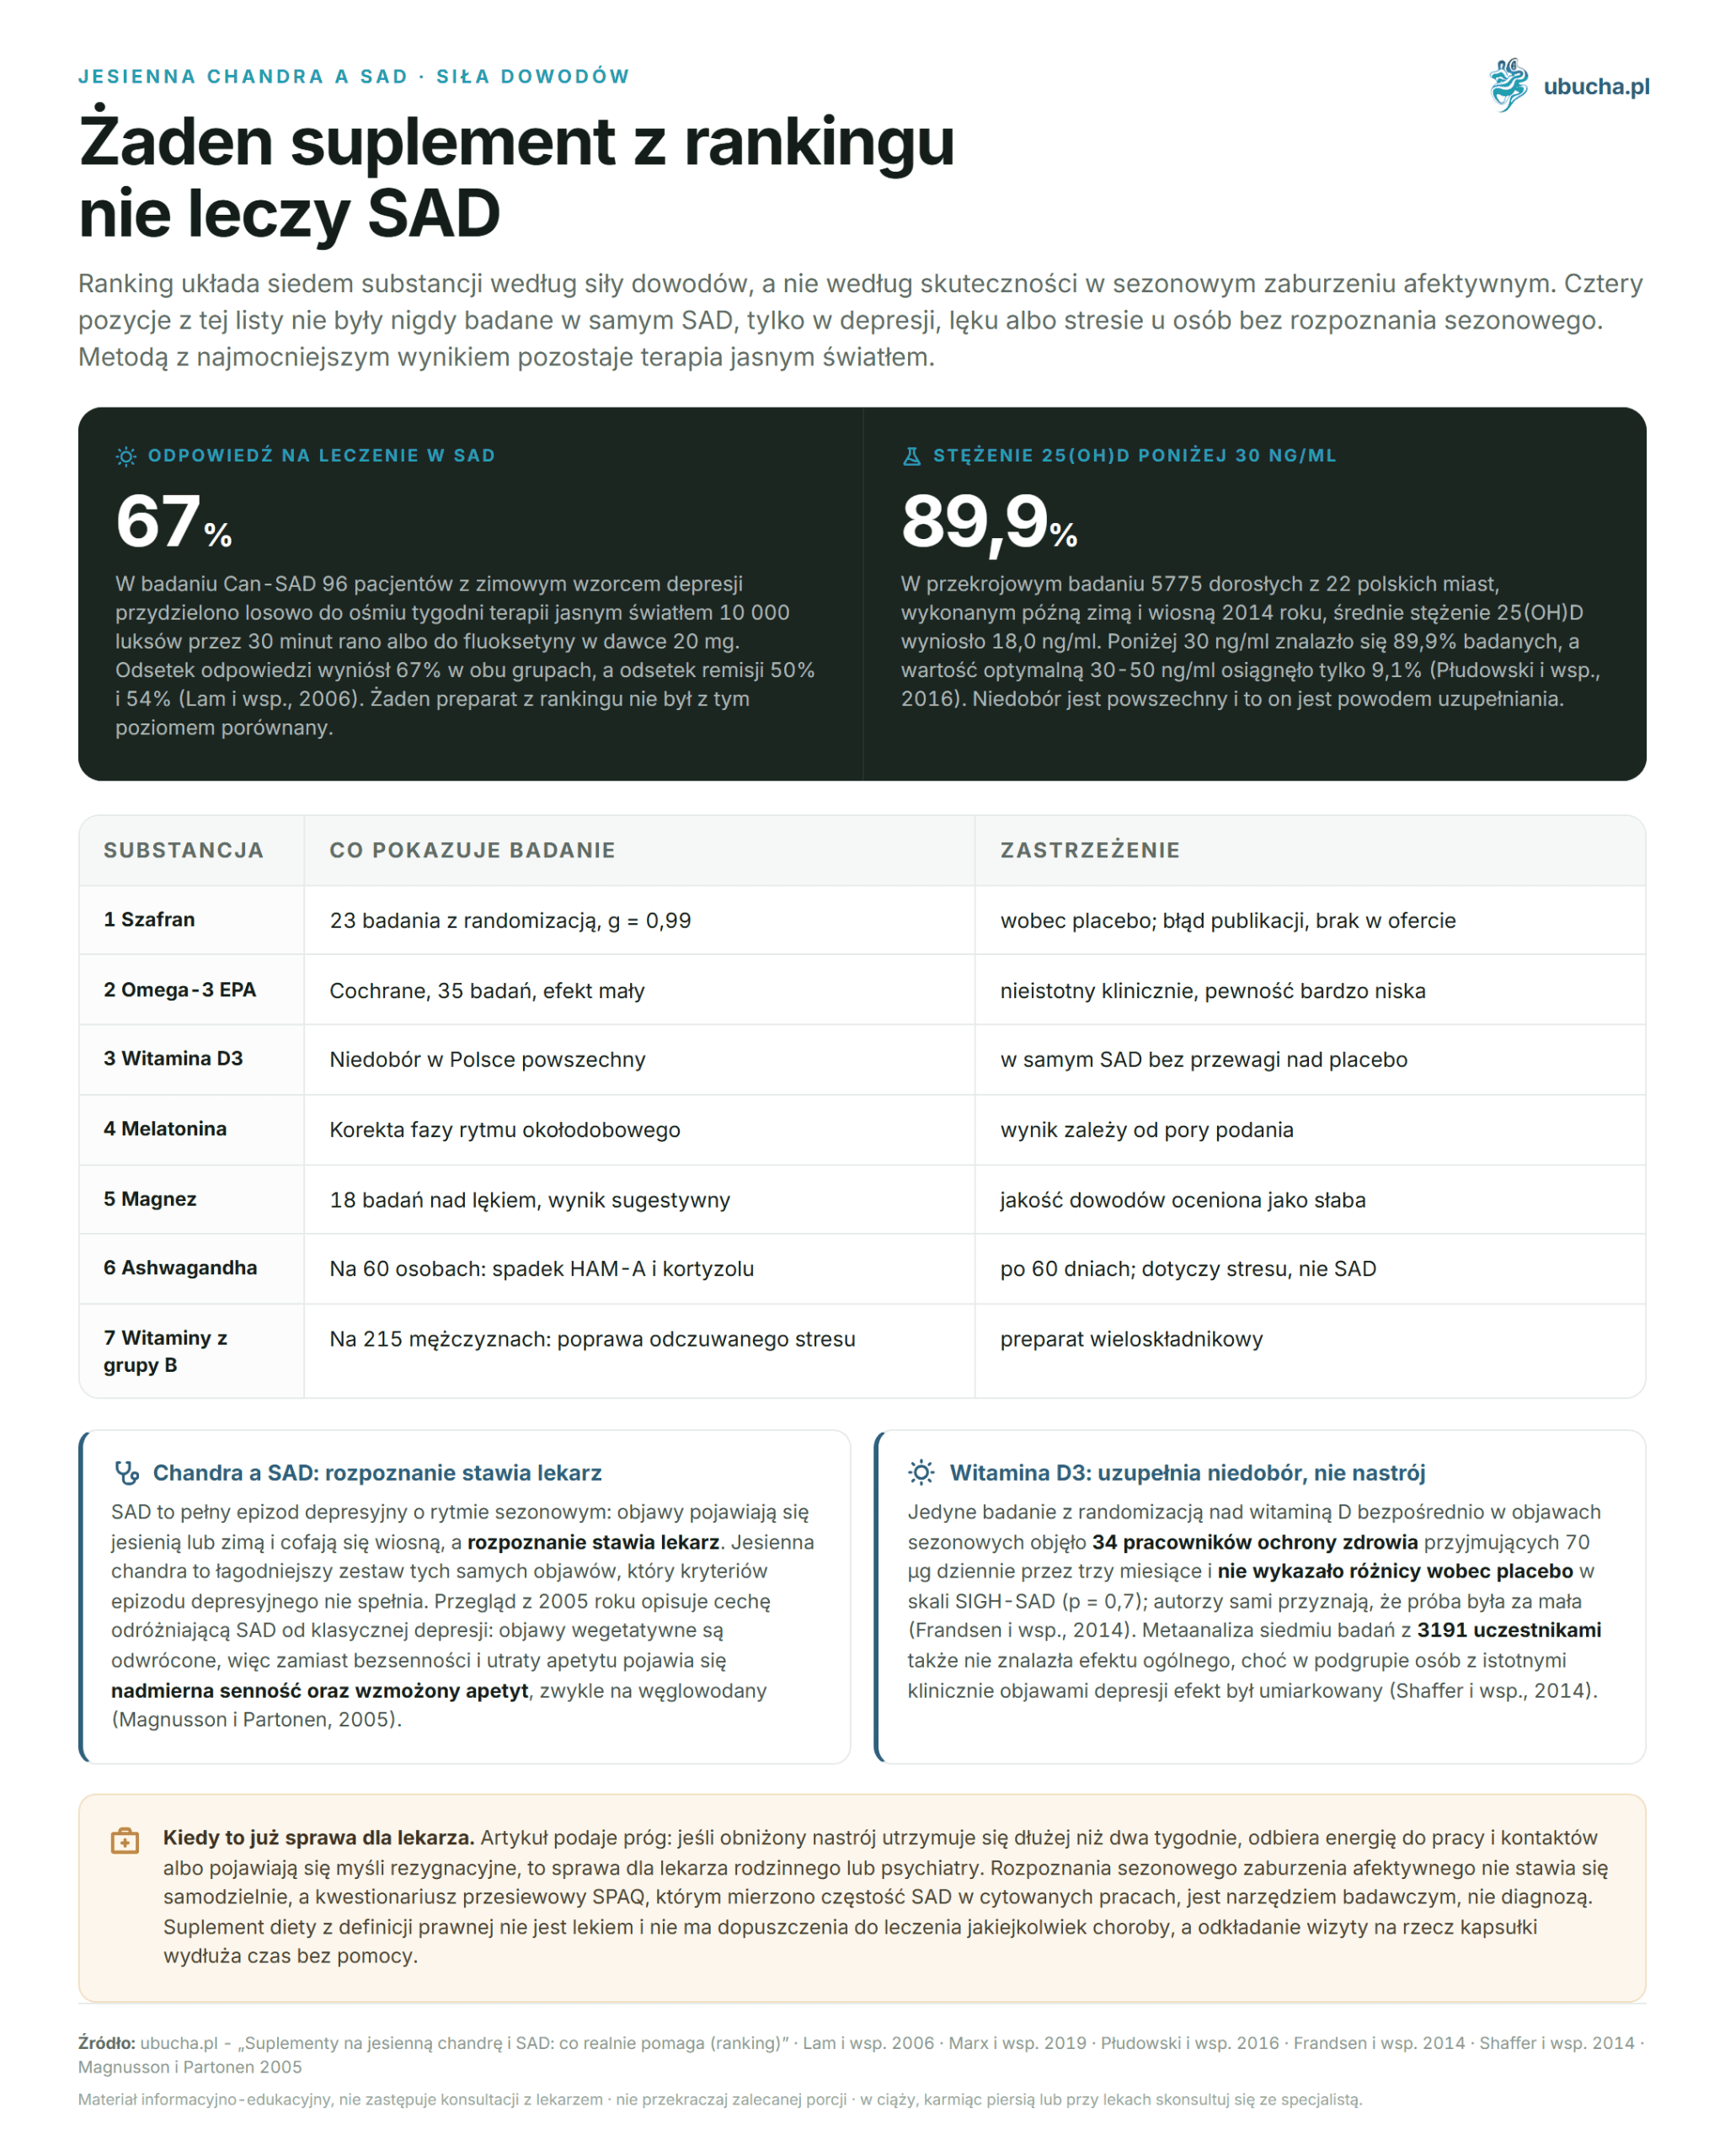
• In winter and spring, 89.9% of adult Poles have 25(OH)D below 30 ng/ml (Płudowski et al., 2016).
• In SAD, bright light therapy is effective: 67% response, the same as fluoxetine (Lam et al., 2006).
• No supplement from this list treats SAD.
• The strongest result is saffron, which we do not have in our offer.
• Prices from the store API, as of August 8, 2026.
What is the difference between autumn blues and seasonal depression?
The difference is formal and has practical consequences. SAD is a full depressive episode with a seasonal rhythm: symptoms appear in autumn or winter and recede in spring, and the diagnosis is made by a doctor. Autumn blues is a milder set of the same symptoms that does not meet the criteria for a depressive episode.
Magnusson and Partonen described in a 2005 review a feature that distinguishes SAD from classic depression: vegetative symptoms are reversed. Instead of insomnia and loss of appetite, there is excessive sleepiness and increased appetite, usually for carbohydrates. The authors also emphasize that symptoms subside with exposure to daylight or light therapy. The frequency of diagnoses increases with latitude, which was confirmed in a study of four locations in the United States by Rosen et al. (1990).
What does this not imply? That a diagnosis can be made independently. The SPAQ screening questionnaire, which was used to measure the frequency of SAD in the cited studies, is a research tool, not a diagnosis. If a low mood persists for more than two weeks and hinders work or relationships, the appropriate address is a doctor’s office, not a shelf with supplements. This text describes the state of knowledge about supplements and is not intended for self-diagnosis of anything.
What really treats SAD, and what won’t a supplement do?
The method with the strongest result in SAD is bright light therapy, not a supplement. In a Canadian study Can-SAD (Lam et al., 2006), 96 patients with a winter pattern of depression were randomly assigned to eight weeks of treatment with 10,000 lux light for 30 minutes in the morning or to fluoxetine at a dose of 20 mg. The response rate to treatment was 67% in both groups, and the remission rate was 50% and 54%.
This study says two things at once. First, SAD is treatable and has established methods. Second, the reference point for any other intervention is precisely such a level of effectiveness, and no product from the rest of the text has ever been compared to it.
Why does light work? Levy et al. (2006) showed that in patients with winter depression, the severity of symptoms is associated with a phase shift of the circadian rhythm, and appropriately planned exposure to bright light corrects this phase. In the same work, the authors correctly call appropriately planned exposure to bright light the treatment of choice.
Where does a supplement fit in? Where there is a deficiency to be supplemented or a single symptom to alleviate: sleep, tension, fatigue. Not where an episode of depression needs to be treated. A dietary supplement, by legal definition, is not a medicine and is not approved for treating any disease, and postponing a doctor’s visit in favor of a capsule prolongs the time without help.
Which supplement has the strongest evidence for improving mood?
The short answer is: saffron, and it has a clear advantage over the rest of the field. A meta-analysis of 23 randomized studies showed a large effect size compared to placebo (g = 0.99), and in direct comparisons, the product did not yield to antidepressants (Marx et al., 2019). However, the authors themselves caution that the collected material shows publication bias.
The table below organizes seven substances according to what their studies actually show. The order is based on the quality and consistency of evidence, not on the popularity of the product. The last column indicates whether the substance is available for purchase from us, as the ranking and assortment diverge at the top.
| Place | Substance | What the study shows | In the store |
|---|---|---|---|
| 1 | Saffron | 23 randomized studies, large effect compared to placebo (g = 0.99), indicated publication bias | no |
| 2 | Omega-3 EPA | Cochrane review, 35 studies, small effect deemed clinically insignificant, very low certainty of evidence | yes |
| 3 | Vitamin D3 | Common deficiency in Poland, but a randomized study in SAD did not show an advantage over placebo | yes |
| 4 | Melatonin | Result depends on the timing of administration, mechanism is correction of circadian rhythm phase | yes |
| 5 | Magnesium | 18 studies on anxiety, suggestive result, quality of evidence rated by authors as weak | yes |
| 6 | Ashwagandha | Randomized study on 60 individuals, decrease in HAM-A scores and morning cortisol after 60 days | yes |
| 7 | B Vitamins | Randomized study on 215 men, improvement in perceived stress, but a multi-ingredient product | yes |
Four items from this list have never been studied in SAD itself, only in depression, anxiety, or stress in individuals without a seasonal diagnosis. This does not mean they do not work. It means we are transferring results obtained elsewhere to autumn blues, and we prefer to say this directly rather than mask it with a letter in the “level of evidence” column.
Vitamin D3: how much is lacking for Poles and how much to take?
Deficiencies are common and well quantified. In a cross-sectional study of 5775 adults from 22 Polish cities, conducted in late winter and spring 2014, the average concentration of 25(OH)D was 18.0 ng/ml. Below 20 ng/ml were 65.8% of respondents, below 30 ng/ml as much as 89.9%, and the optimal value of 30-50 ng/ml was achieved by only 9.1% (Płudowski et al., 2016).
How much should one take then? The update of Polish guidelines from 2023, prepared by 34 authors and a consensus of eight scientific societies, states that for healthy adults, 1000-2000 IU of cholecalciferol is recommended daily throughout the year if sun exposure recommendations are not followed. The upper tolerable daily dose is 4000 IU for normal body weight and 10,000 IU for overweight or obesity. The guidelines themselves and the question of the sense of combining D3 with K2 are discussed in a separate text on vitamin D3.
This is important when shopping. Most vitamin D preparations in our catalog contain 10,000 IU per capsule, which is a dose intended for use under medical supervision and measurement of 25(OH)D, not for daily intake without guidance by a person of normal body weight.
Will supplementing the deficiency improve mood? Here one must be cautious. The only randomized study that directly examined vitamin D in seasonal symptoms involved 34 healthcare workers taking 70 µg daily for three months and found no difference compared to placebo on the SIGH-SAD scale (p = 0.7). The authors themselves admit that the sample was too small (Frandsen et al., 2014). A broader meta-analysis of seven studies with 3191 participants also found no overall effect, although in the subgroup of individuals with clinically significant depressive symptoms, the effect was moderate (Shaffer et al., 2014). The conclusion is less impressive than the headlines: vitamin D is worth supplementing because it is lacking, not because it boosts mood.
How much does a daily portion cost and what is on the shelf?
We calculated the price of the package to the cost of one daily portion, as this is the only number that allows comparing a tablet with a gummy. The range is large: from 0.08 PLN for a vitamin D3 tablet to 1.50 PLN for a melatonin gummy. All prices come from the store API, as of August 8, 2026.
| Product | What distinguishes it | Price | Cost of daily portion |
|---|---|---|---|
| Vitamin D3 4000 IU, 240 tablets | Cholecalciferol from lanolin, one tablet is a daily portion | 19.99 PLN | 0.08 PLN |
| Omega 3 1000 mg, EPA 330 mg / DHA 220 mg, 90 capsules | Advantage of EPA over DHA, added vitamin E | 26.50 PLN | 0.29 PLN |
| Navigator Omega 3, EPA 180 mg / DHA 120 mg, 120 capsules | Lower dose of EPA, packaging for four months | 47.90 PLN | 0.40 PLN |
| Magnesium Complex three forms 400 mg, 120 capsules | 400 mg of magnesium in three forms in one capsule | 38.00 PLN | 0.32 PLN |
| Navigator Magnesium 400 mg, 180 capsules | Vegetarian coating, manufacturer recommends a portion in the evening | 59.90 PLN | 0.33 PLN |
| Himalaya Ashwagandha, 60 tablets | 250 mg of root extract, recommended two tablets daily | 20.99 PLN | 0.70 PLN |
| B Vitamin Complex, eight vitamins, 120 tablets | Complete set of eight B vitamins in one tablet | 18.59 PLN | 0.15 PLN |
| Good Sleep Forte gummies with melatonin, 30 pcs | 1 mg of melatonin per gummy, plus valerian and L-theanine | 45.00 PLN | 1.50 PLN |
Two things become visible only after recalculation. The cheapest items are simple, single-ingredient tablets in large packages, while the most expensive are forms for which you pay for convenience or taste. A melatonin gummy costs almost nineteen times as much per day as a vitamin D3 tablet, with a content of 1 mg of melatonin, which is considered a small dose in studies on circadian rhythm.
What is not in this table? Saffron. We searched the catalog by Polish, English, and Latin names, and then by the compositions of all 386 items available for sale. The substance in first place in the ranking does not appear in our offer in any form, neither alone nor as an ingredient in a mixture. We prefer to write this than to substitute something similarly sounding in its place.
How to combine these supplements and when to see the effect?
The sensible order is one: first supplement what is definitely lacking, then add the rest individually. Vitamin D3 and omega-3 form the base, as both are fat-soluble and should be taken with a meal containing fat. Manufacturers of both products from the table recommend one capsule daily with food.
Magnesium makes sense in the evening, and this is also suggested by the manufacturers of both magnesium products in our offer. Ashwagandha in the Himalaya version is taken twice daily with meals. Melatonin is taken just before sleep and only then, as in studies on circadian rhythm, the timing of administration determines the outcome, not the size of the dose. The differences between the regular form and the extended-release form are described in a comparison of both forms of melatonin.
What not to do? Do not add everything at once in one week, as with seven products, it will be impossible to say later what helped and what caused an allergy. Do not exceed the portions on the label, especially with vitamin D3, where the upper daily limit is stated directly in the guidelines. If you are taking anticoagulant or antidepressant medications, discuss each of these products with your doctor or pharmacist before starting.
When to see the effect? An honest answer is: the cited studies do not answer this question well. It lasted from 33 days for B vitamins, through 60 days for ashwagandha, to 12 weeks for vitamin D, and measurement occurred at the end, not along the way. Earlier timeframes simply have not been measured reliably, so any number like “effect after two weeks” is a guess.
Frequently Asked Questions
Can a supplement replace treatment for seasonal depression?
No. A dietary supplement is not a medicine and is not approved for treating depression. In the Can-SAD study, light therapy of 10,000 lux yielded a 67% response rate, the same as fluoxetine. No product from this ranking has been compared to such a level of effectiveness.
Which supplement for mood decline has the strongest evidence?
Saffron. A meta-analysis of 23 randomized studies showed a large effect size compared to placebo (g = 0.99) and no advantage of antidepressants in direct comparisons. The authors caution about the presence of publication bias, and saffron products are not available in our offer, which we note in the table.
How much vitamin D3 is recommended daily by Polish guidelines?
The update of Polish guidelines from 2023 states that for healthy adults, 1000-2000 IU of cholecalciferol is recommended daily throughout the year when sun exposure recommendations are not followed. The upper tolerable daily dose is 4000 IU for normal body weight and 10,000 IU for overweight or obesity.
Does vitamin D3 improve mood in autumn?
The evidence for this is weak. A randomized study of 34 individuals with seasonal symptoms showed no difference compared to placebo on the SIGH-SAD scale. A meta-analysis of seven studies with 3191 participants also found no overall effect, although in individuals with clinically significant depressive symptoms, the effect was moderate.
Do magnesium and ashwagandha help with autumn blues?
This has not been directly studied. A review of 18 studies on magnesium describes the result as suggestive with weak evidence quality. Ashwagandha has one study on 60 individuals with stress: a decrease in HAM-A scores and morning cortisol after 60 days. Both studies concern anxiety and stress, not seasonal mood decline.
How to tell if it is no longer just ordinary blues?
By the duration and effects. If a low mood persists for more than two weeks, takes away energy for work and social interactions, or if there are thoughts of resignation, it is a matter for a family doctor or psychiatrist. A diagnosis of seasonal affective disorder cannot be made independently.
Vitamin D3 and omega-3 preparations can be found in the supplements category, and melatonin gummies in the gummies category. Check stock levels on-site, as they change more frequently than this article.
This article is for informational and educational purposes and does not constitute medical advice. Before starting supplementation, consult a doctor, especially if you are taking medications regularly, are pregnant or breastfeeding, or have a chronic illness.
Author: Michał Waluk · Published: 2026-06-29 · Updated: 2026-08-08