
Hair Loss Supplements: What Really Works and What to Absolutely Avoid
Biotin, iron, zinc, vitamin D, saw palmetto, and collagen in hair loss. We check what is confirmed by studies in humans and what can be harmful.
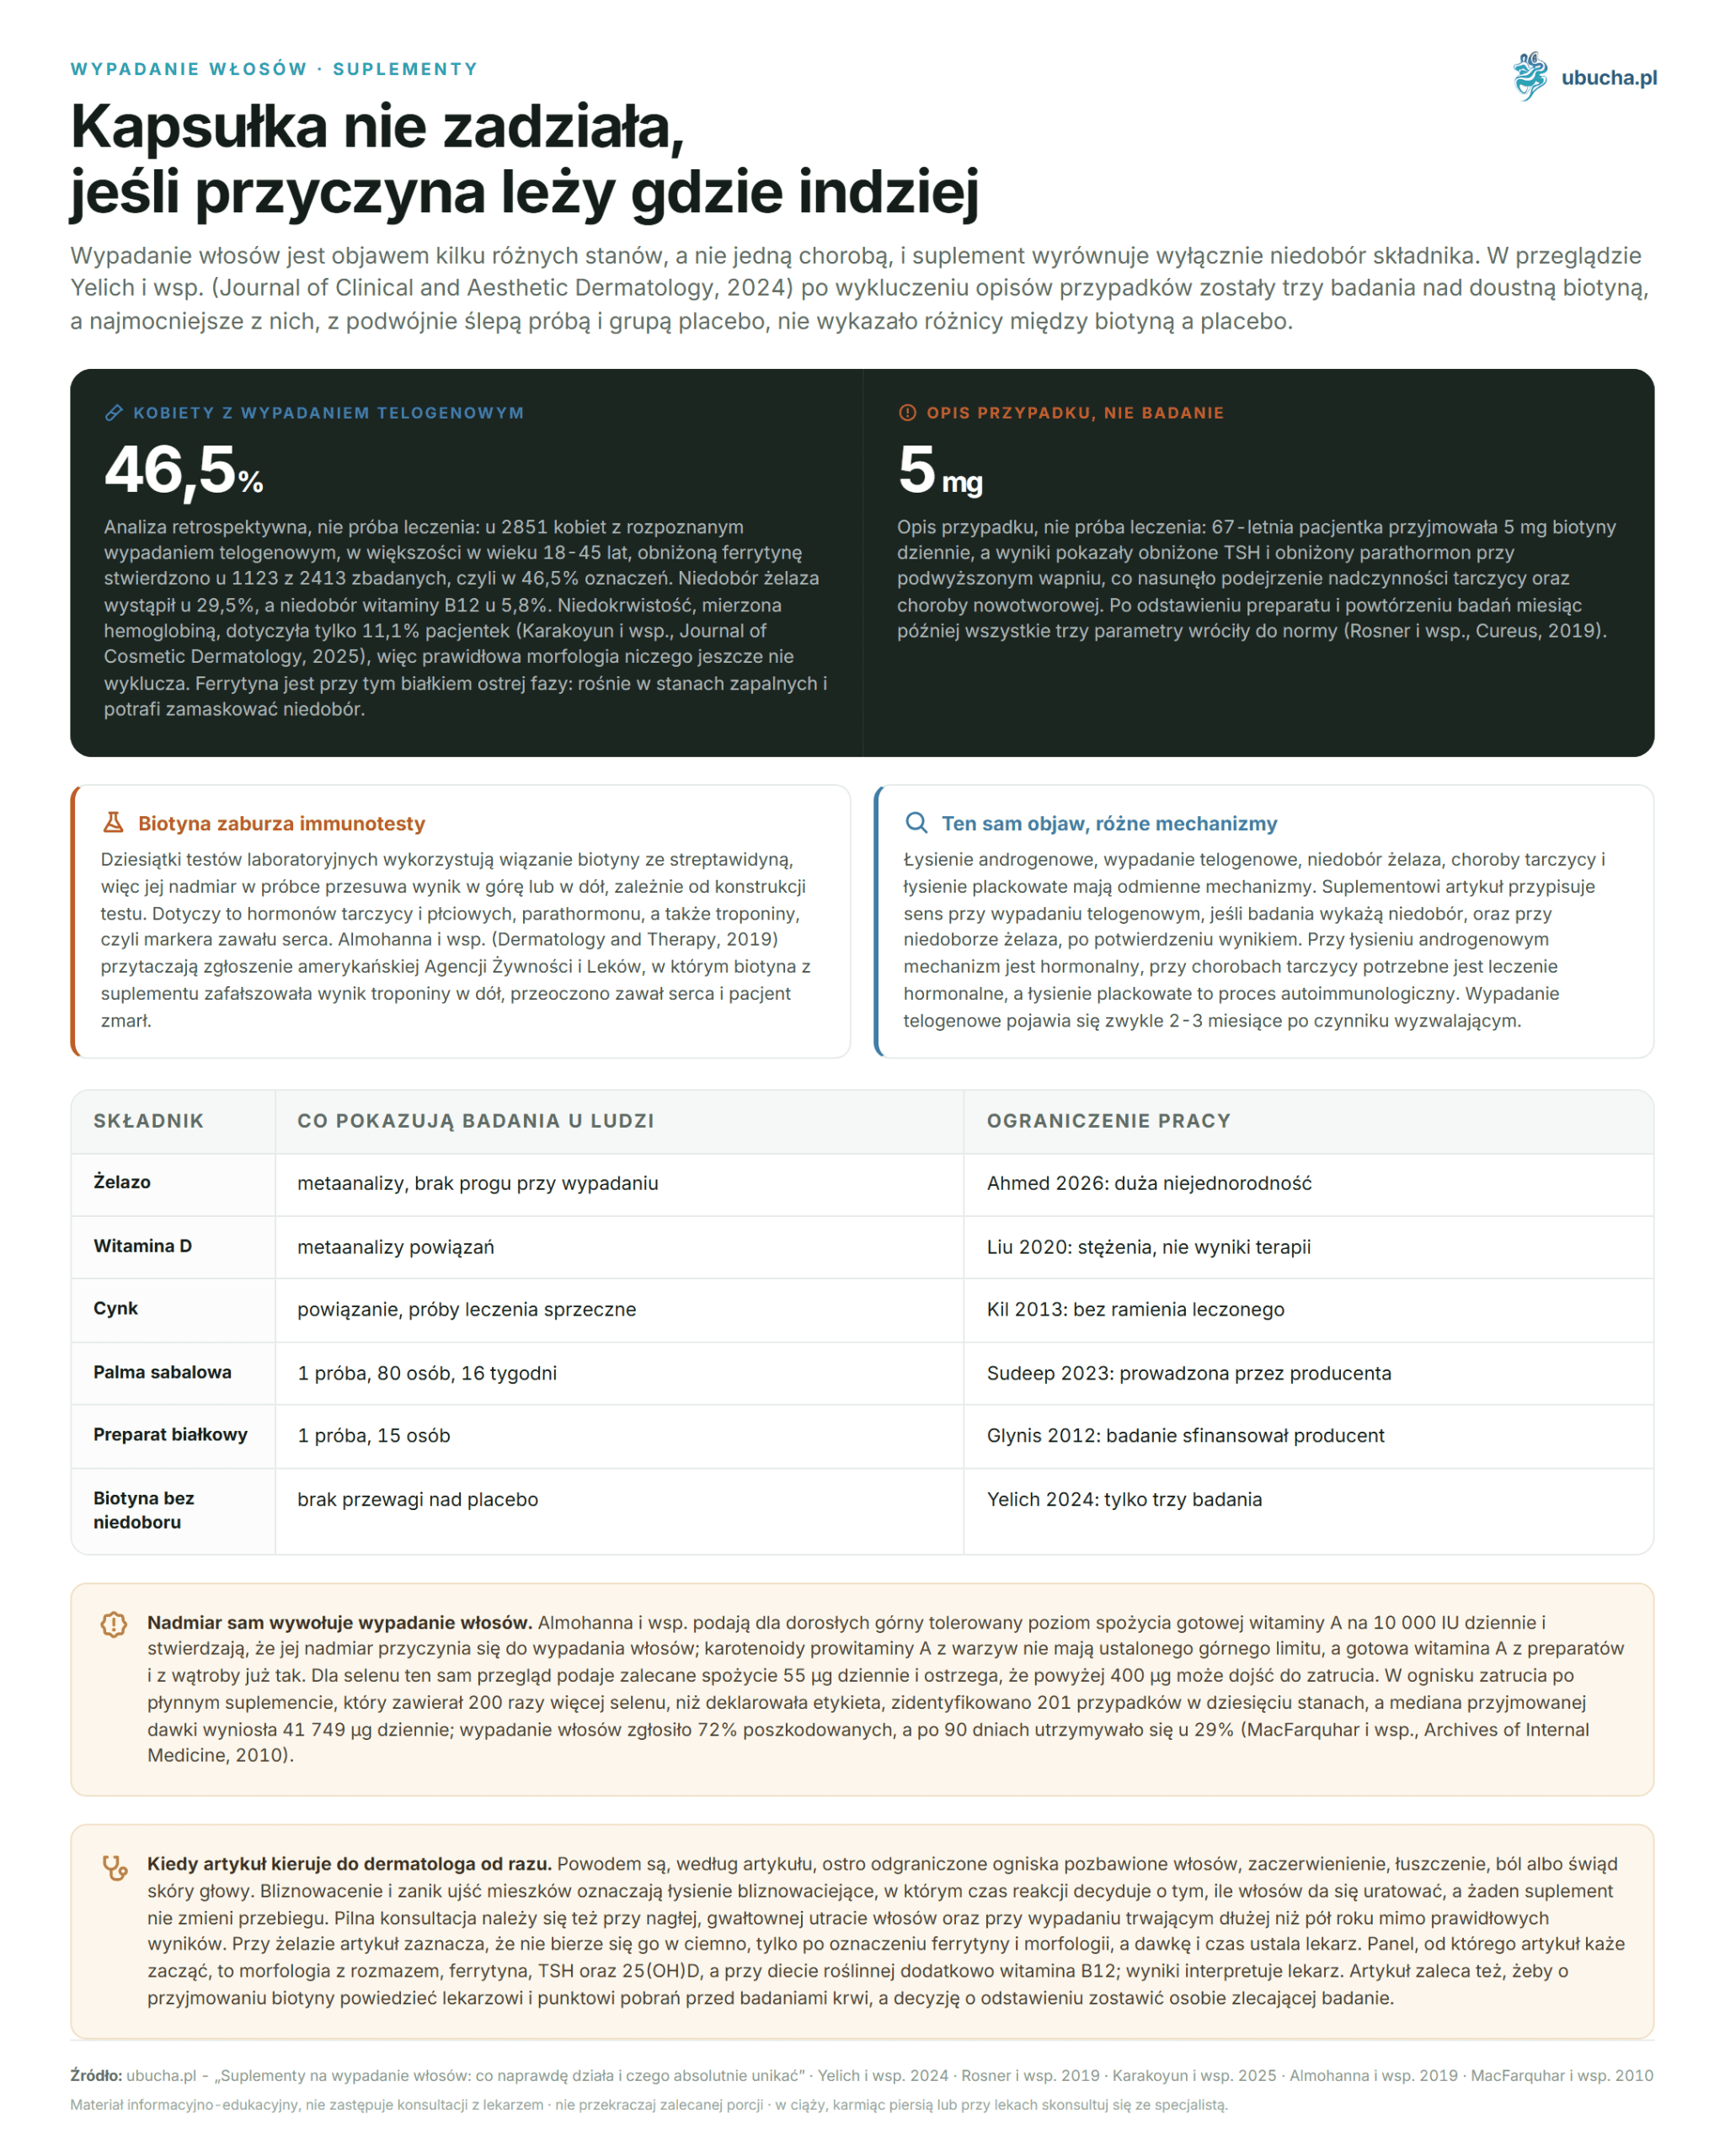
Biotin is the most commonly purchased ingredient in hair products and simultaneously one of the least documented. A 2024 literature review found only three studies meeting basic quality criteria, and the strongest of them showed no difference between biotin and placebo. The problem goes beyond ineffectiveness, as high doses of biotin can skew blood test results, including thyroid hormones and troponin. Meanwhile, hair loss has several completely different causes, and no capsule will work if the cause lies elsewhere. In this text, you will find what can be supported by human studies: where supplementation makes sense, where evidence is simply lacking, and which products can themselves cause hair loss.
KEY INFORMATION
• A review by Yelich et al. (J Clin Aesthet Dermatol, 2024) found only three studies on biotin, and the best of them showed no advantage over placebo.
• Biotin interferes with immunoassays: in a patient taking 5 mg daily, it skewed TSH, parathyroid hormone, and calcium (Rosner et al., Cureus, 2019).
• In 2851 women with telogen hair loss, low ferritin was found in 46.5% of measurements.
• Excess vitamin A and selenium can cause hair loss themselves.
Why won’t a supplement work if you don’t know the cause of hair loss?
Because hair loss is a symptom of several different conditions, not a single disease. Androgenetic alopecia, telogen hair loss, iron deficiency, hypothyroidism, and alopecia areata have different mechanisms. A supplement only addresses a deficiency, so it will help only if that deficiency drives the problem.
| Cause | What it usually looks like | Does supplementation make sense |
|---|---|---|
| Androgenetic alopecia | Years of thinning at the crown, receding temples | No, the mechanism is hormonal |
| Telogen hair loss | Diffuse loss 2-3 months after illness, childbirth, or diet | Yes, if tests show a deficiency |
| Iron deficiency | Fatigue, pallor, low ferritin | Yes, after confirming with results |
| Thyroid diseases | Hair loss plus weight change and dry skin | No, hormonal treatment is needed |
| Alopecia areata | Sharp patches of smooth skin | No, it is an autoimmune process |
The authors of the review Almohanna et al. (Dermatology and Therapy, 2019) summarize cautiously: micronutrients participate in the hair follicle cycle, but their role is not fully understood, and large double-blind placebo-controlled studies are needed to assess the effectiveness of supplementation. We noticed while reading the leaflets of popular products that this caution completely disappears in marketing descriptions.
What is the difference between telogen and androgenetic hair loss?
Telogen hair loss is diffuse and temporary. It usually appears 2-3 months after a triggering factor: fever, surgery, childbirth, strict dieting, or deficiency. Androgenetic alopecia progresses over years, affecting the crown and temples, and its basis is the sensitivity of follicles to androgens.
The scale of the first type in clinics is large. In a retrospective analysis Karakoyun et al. (Journal of Cosmetic Dermatology, 2025) included 2851 women diagnosed with telogen hair loss, mostly aged 18-45. Low ferritin was found in 1123 of 2413 examined, or in 46.5% of measurements, iron deficiency in 29.5%, and vitamin B12 deficiency in 5.8%. Anemia, measured by hemoglobin, affected only 11.1% of patients, which shows that normal morphology does not exclude anything.
Androgenetic alopecia follows a different logic. A review Cortez et al. (Anais Brasileiros de Dermatologia, 2025) concerns the male form and describes it as a process of follicle miniaturization with a multifactorial basis, with a clear involvement of genes and hormones, where therapeutic options with a high level of scientific evidence are limited. Minoxidil and finasteride are medications, not supplements: they have registration, a leaflet, and side effects, and the decision to include them is made by a doctor. Mixing them in the same bag with pharmacy capsules is the most common mistake in hair guides.
Does biotin actually strengthen hair?
In a person without a confirmed deficiency, there is no good evidence for this. A review Yelich et al. (Journal of Clinical and Aesthetic Dermatology, 2024) searched the literature for oral biotin used for hair growth or quality. After excluding case reports, three studies remained.
The strongest of this trio, with a double-blind trial and placebo group, showed no difference between biotin and placebo. The other two concerned narrow groups, patients taking isotretinoin and women after sleeve gastrectomy, and were burdened with a risk of error. The authors conclude that there is a significant discrepancy between the common belief in the effectiveness of biotin and the scientific literature.
The evidence table in the review by Almohanna et al. says the same in different words: biotin levels may be low in people complaining of hair loss, but the effectiveness of its administration is not supported by studies, and monotherapy with biotin has not been studied at all. The same authors note that average biotin intake in Western countries is sufficient, deficiency is rare, and severe deficiency in a healthy person with a normal diet has never been reported.
Why can biotin skew blood test results?
Because dozens of laboratory tests use biotin binding with streptavidin. An excess of biotin in the sample disrupts this mechanism and shifts the result up or down, depending on the test’s design. This applies to thyroid and sex hormones, parathyroid hormone, and troponin, a marker of heart attack.
There is documented harm behind this mechanism. Almohanna et al. cite a report from the American Food and Drug Administration, in which biotin from a supplement skewed the troponin result downwards, missing a heart attack, and the patient died. A specific, milder occurrence of such an event was described by Rosner et al. (Cureus, 2019). Their 67-year-old patient was taking 5 mg of biotin daily. The results showed low TSH and low parathyroid hormone with elevated calcium, raising suspicion of hyperthyroidism and cancer. After discontinuing the supplement and repeating the tests a month later, all three parameters returned to normal.
The scale of the discrepancy between demand and the content of the supplement is large. Almohanna et al. state that the adequate intake of biotin for adults is 30 µg daily and note that hair, skin, and nail supplements significantly exceed this value; doses of 5000 and 10,000 µg can be found on shelves. This makes an ingredient with unproven effectiveness a real diagnostic problem. If you are taking biotin, inform your doctor and the blood draw point before the tests. Leave the decision on whether and for how long to discontinue it to the person ordering the test.
What do the data say about iron and ferritin in hair loss?
The association is well documented, but the threshold and supplementation itself are not. A meta-analysis Ahmed et al. (Skin Appendage Disorders, 2026), covering 29 studies, showed lower ferritin in people with telogen hair loss than in controls, with a standardized mean difference of -0.57 with high heterogeneity of results.
The number 40 µg/l, repeated in guides as a boundary, does not come from an agreed position. Rushton (Clinical and Experimental Dermatology, 2002) states directly that the ferritin level appropriate for people with increased hair loss has not been definitively established, and suggests 70 µg/l with a normal ESR below 10 mm/h. Almohanna et al. show an even wider range: in subsequent studies, iron deficiency was defined by ferritin from 15 to 70 µg/l, and there is no agreement on what constitutes “normal ferritin,” although in practice, most authors supplement below 40.
The practical conclusion is the opposite of the advertising. Iron should not be taken blindly, but after measuring ferritin and morphology, and the dose and duration are determined by a doctor. Ferritin is an acute phase protein, so it rises in inflammatory states and can mask deficiency. As uncertain as the balance of benefits and harms of iron itself looks, it is evident in the review Watt et al. (Family Practice, 2025): 23 studies, 4492 pregnant women without anemia, in whom supplementation halved the risk of anemia, but reporting of adverse events was inconsistent, and the authors indicate that studies assessing the risk of gastrointestinal complaints and iron overload are urgently needed. This is a study about pregnancy, not hair, so it speaks to the safety of the product, not its effect on hair growth.
Do zinc and vitamin D have documented links to hair loss?
They do, but only in the form of observational associations. Studies compare levels in people with hair loss and healthy individuals, which is different from demonstrating that administering a supplement rebuilds hair. The latter has not been shown for zinc.
In a study Kil et al. (Annals of Dermatology, 2013) comparing 312 patients with four types of hair loss and 30 controls, the average serum zinc level was 84.33 versus 97.94 µg/dl in the control group. Values below 70 µg/dl were more common in alopecia areata and telogen hair loss. This is a cross-sectional study without a treated arm. Almohanna et al. noted in the evidence table that information on the effectiveness of zinc supplementation is insufficient; the two treatment trials they cite yielded conflicting results. Rushton went even further and deemed the hypothesis of zinc as a cause of hair loss unsupported by data.
Vitamin D has a stronger observational backing. A meta-analysis Liu et al. (Dermatology and Therapy, 2020) included 1585 people with alopecia areata and 1114 controls from 19 studies. The level of 25(OH)D was on average 9.08 units lower in patients, and the chance of deficiency was more than four times greater (OR 4.14). Calcium levels did not differ. The authors suggest that in alopecia areata, both screening for vitamin D deficiency and supplementation may be beneficial. This does not mean that the effectiveness of such treatment has been proven: the meta-analysis compares levels in sick and healthy individuals, not therapy outcomes.
Do saw palmetto and protein supplements have studies in humans?
They do, but these are single and small trials, additionally conducted by the manufacturers of the studied products. For saw palmetto, the best evidence remains a 16-week randomized placebo-controlled study on 80 individuals, while for the oral protein supplement, there is one study on fifteen women. The scale of these studies does not allow them to be placed alongside medications used in androgenetic alopecia.
Sudeep et al. (Clinical, Cosmetic and Investigational Dermatology, 2023) assigned 80 individuals with mild to moderate androgenetic alopecia to four arms, so 20 per group. The oral capsule contained 100 mg of standardized saw palmetto oil. Hair loss decreased in this group by as much as 29% from baseline, and density increased by 5.17%. The ratio of growing to resting hairs did not change significantly. Four of the six authors work for the manufacturer of the studied extract, which, given such group size, is as important a piece of information as the result itself.
For protein supplements, the situation is weaker, and the popular description of this study can even be misleading. Glynis (Journal of Clinical and Aesthetic Dermatology, 2012) did not study keratin hydrolysate, but a ready-made preparation composed of a marine protein complex from shark skin and mollusks, silica from horsetail, and vitamin C from acerola. The scheme was double-blind and lasted 180 days, but the group consisted of 15 women experiencing hair thinning: ten on the preparation and five on placebo, in one center, and the study was funded by the manufacturer. The reported increase in the number of terminal hairs from 271 to 609 over an area of 4 cm² is difficult to accept with such a small group without repetition in a larger trial. Separately about collagen: it provides glycine and proline, not cysteine and methionine, from which hair keratin is built.
Which supplements can cause hair loss themselves?
Primarily vitamin A and selenium taken in excess. Both substances have a narrow safety window, and their excess manifests as hair loss, which is exactly what they were supposed to protect against. This is the most often overlooked part of the conversation about hair products.
Almohanna et al. provide an upper tolerable intake level for ready vitamin A at 10,000 IU daily and state that its excess contributes to hair loss. The form also matters: carotenoids of provitamin A from vegetables have no established upper limit, while ready vitamin A from supplements and liver does. It is worth checking the label to see which form the product contains.
Selenium works similarly, only faster. The same review provides a recommended intake of 55 µg daily and warns that above 400 µg, poisoning may occur. MacFarquhar et al. (Archives of Internal Medicine, 2010) described an outbreak of acute selenium poisoning from a liquid dietary supplement that contained 200 times more selenium than declared on the label. 201 cases were identified in ten states, with a median intake of 41,749 µg daily against the recommended intake of 55 µg. Hair loss was reported by 72% of the affected, and it persisted in 29% after 90 days. Rushton warns similarly: excessive intake of supplements can itself cause hair loss and is not recommended without confirmed deficiency.
What tests to order and when to see a dermatologist?
Start with morphology with a smear, ferritin, TSH, and 25(OH)D, and if on a plant-based diet, add vitamin B12. This panel has most often gone beyond the norm in the cited works for people with hair loss. Interpret the results with a doctor, not with a calculator on the manufacturer’s website.
See a dermatologist immediately if there are sharply defined patches without hair, redness, peeling, pain, or itching of the scalp, if loss lasts longer than six months despite normal results, or if there are other general symptoms. Scarring and atrophy of follicle openings indicate scarring alopecia, where the response time determines how many hairs can be saved, and no supplement will change the course. An urgent consultation is also warranted in cases of sudden, rapid hair loss and hair loss lasting longer than six months despite normal results.
In the office, the examination begins with an interview about events from 2-3 months ago, medications, and diets, then an assessment of the scalp with trichoscopy. In more difficult cases, the dermatologist takes a skin biopsy. Our observation from reading descriptions of hair products: none of them answer the question that the blood test result resolves, and it is precisely from that answer that it depends whether the supplement has anything to do here. If the doctor confirms a deficiency and you are looking for products with a clear composition, check the supplements section.
Frequently Asked Questions
Does biotin help with hair loss?
Aside from rare, confirmed deficiency, there is no good evidence for this. Yelich et al. (2024) found only three studies on oral biotin and hair growth. The strongest of them, with a double-blind trial and placebo, showed no difference between biotin and placebo.
What level of ferritin is considered too low for hair loss?
The threshold has not been definitively established. Rushton (2002) suggests 70 µg/l with a normal ESR below 10 mm/h, not 40 µg/l as repeated on the internet. The result is interpreted by a doctor along with morphology, as ferritin also rises in inflammatory states.
What is the difference between telogen and androgenetic hair loss?
Telogen hair loss is diffuse and temporary, usually occurring 2-3 months after illness, childbirth, or a strict diet. Androgenetic alopecia progresses over years, affecting the crown and temples, and is due to follicle sensitivity to androgens. A supplement addresses only the deficiency, so it only applies to the first type.
Can high doses of biotin be harmful?
Biotin interferes with immunoassays used in laboratories. Rosner et al. (2019) described a patient taking 5 mg of biotin daily, whose low TSH and PTH with hypercalcemia raised suspicion of cancer. Results returned to normal a month after discontinuing the supplement.
Can a supplement itself cause hair loss?
Yes. Overdosing on vitamin A and selenium is documented causes of hair loss. In a selenium poisoning case described by MacFarquhar et al. (2010), 72% of 201 affected reported hair loss, and it persisted in 29% after 90 days.
When should I see a dermatologist for hair loss?
When there are clearly defined patches without hair, redness, pain, or scarring of the scalp, when loss lasts longer than six months, or when accompanied by other general symptoms. A dermatologist will assess the scalp with trichoscopy and may take a biopsy if necessary.
If you are interested in how the evidence assessment looks for other groups of products, check the texts Supplements for concentration and memory and Collagen: when to take and what to combine for the best effects.
This article is for informational and educational purposes and does not constitute medical advice. Before starting supplementation, consult a doctor, especially if you are taking medications regularly, are pregnant or breastfeeding, or have a chronic illness.
Author: Michał Waluk · Published: 2026-06-22 · Updated: 2026-08-14