CBD for restless legs syndrome (RLS): does it work (FAQ)
CBD for restless legs syndrome: the case description concerned cannabis, not CBD, and a newer trial of THC with CBD was open. What is known and what is not.
The question of CBD for restless legs syndrome comes up regularly and usually receives a more confident answer than the literature allows. In guide texts, there is a statement about a “2020 study in which six patients felt a significant improvement after CBD.” We checked it at the source, and neither the year nor the substance matches: the description concerned six people using cannabis, not taking pure cannabidiol, and was published in 2017. This difference determines the rest, as cannabis containing THC and isolated CBD is not the same evidence. A newer trial, from 2026, also concerned a combined preparation, not CBD alone. Below, we separate what has actually been studied from what has been added along the way and show what to really start with in this diagnosis.
KEY INFORMATION
• The case description cited as evidence concerned cannabis, not CBD alone, and was published in 2017 (Megelin and Ghorayeb, Sleep Medicine 2017).
• The current Cochrane review finds no clear evidence that CBD-dominant preparations reduce neuropathic pain (Ateş et al., Cochrane 2026).
• A meta-analysis of 97 studies indicates a prevalence of restless legs syndrome of about 3% in adults, higher in women (Broström et al., J Sleep Res 2023).
• Before considering anything else, it is worth measuring ferritin: iron deficiency is a reversible cause of symptoms.
• EFSA cannot determine the safety of CBD in people taking medications, which describes most patients with this diagnosis.
What is restless legs syndrome and where to start?
It is a neurological disorder characterized by an urge to move the legs, accompanied by unpleasant sensations in the limbs. Symptoms appear or worsen at rest, primarily in the evening and at night, and temporarily subside with movement. The result is chronically shortened and fragmented sleep.
The frequency of this diagnosis depends on the counting method. A meta-analysis involving 97 studies and 483,079 participants from 33 countries reports a corrected overall prevalence of 3 percent in the adult population, with a confidence interval from 1.4 to 3.8 percent. In women, it was 4.7 percent, and in men, 2.8 percent. The authors note that the result depends on methodological quality and sampling methods (Broström et al., J Sleep Res 2023). The circulating figure of 15 percent in guides does not correspond to this basis.
However, the first step does not lead to any supplement. Iron deficiency in the brain is one of the described mechanisms of this disorder, and an international working group has developed separate guidelines for iron treatment based on a review of 299 studies. Oral iron was considered possibly effective in individuals whose serum ferritin levels do not exceed 75 micrograms per liter (Allen et al., Sleep Medicine 2018). Measuring ferritin is a cheap test that can indicate a reversible cause, and the decision about treatment is made by a doctor.
Has anyone studied CBD in restless legs syndrome?
Not directly. The work cited by guides exists, but it speaks of something else. It is titled “Cannabis for restless legs syndrome: a report of six patients,” published in Sleep Medicine in 2017, and describes six individuals who reported symptom relief after using cannabis (Megelin and Ghorayeb, Sleep Medicine 2017).
The discrepancy between this description and what is made of it has three layers. The year cited in guide texts is 2020, while the work is from 2017. The substance described in the title is cannabis, which is a material containing THC, not isolated cannabidiol. Finally, the type of publication itself: a description of six cases is an observational report, without a control group, without blinding, and without random assignment. No conclusion about effectiveness can be drawn from it, regardless of how convincing the patients’ reports are.
The same author returned to the topic twice. In 2020, he described additional patients and summarized that the benefit of cannabis in treatment-resistant patients should be verified by solid clinical studies (Ghorayeb, Sleep and Breathing 2020). In a review from 2021, he repeated this statement almost verbatim. In other words, the researcher whose work is cited as evidence himself writes that there is still no evidence.
The latest interventional trial does not close anything here, but it is worth knowing. In Journal of Neurology, a study was described in 2026, open, without a control group and without blinding, involving 18 individuals with restless legs syndrome, 16 of whom had multiple sclerosis. A combined preparation with a composition of 2.7 milligrams of THC to 2.5 milligrams of CBD was evaluated. The severity of symptoms on the IRLS scale significantly decreased after one month and after three months, and the time awake after falling asleep also shortened, while sleep efficiency and time to fall asleep did not change significantly. After one year, 66.7 percent of participants continued treatment (Lillo Triguero et al., J Neurol 2026). An open study in a narrow group does not determine effectiveness, and the tested preparation was again not CBD alone.
What does the latest Cochrane review say about cannabinoids?
It says that there is a lack of clear evidence of effectiveness, and for CBD-dominant preparations, this is particularly lacking. The update of the Cochrane review on cannabinoids in chronic neuropathic pain was published in 2026 and replaced the version from 2018, which older texts still cite as valid.
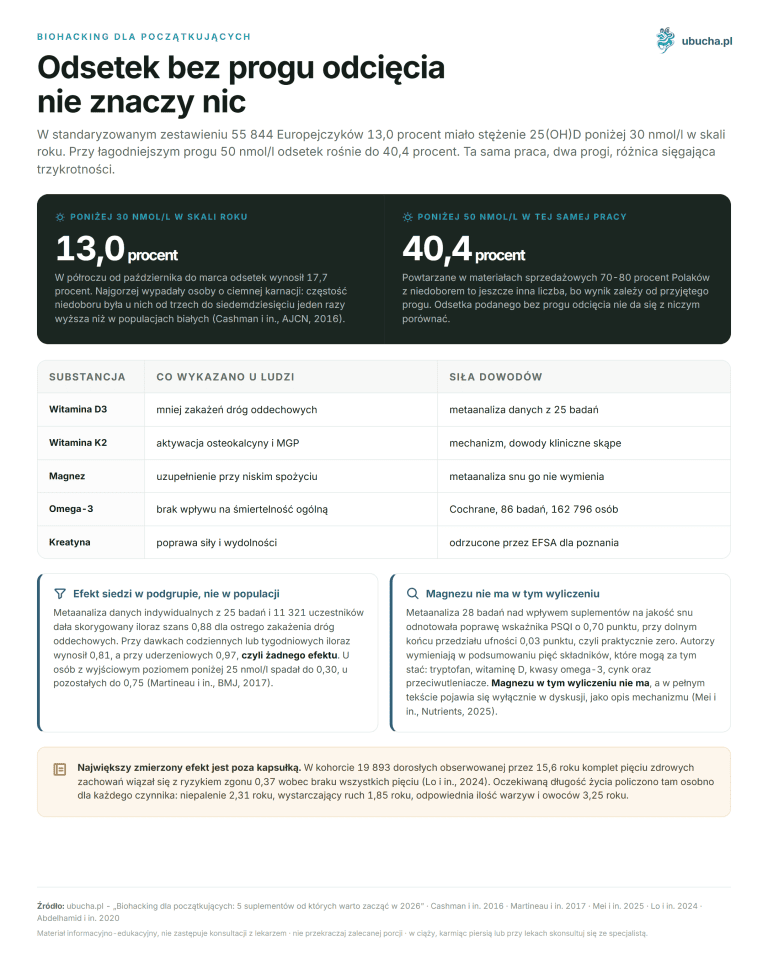
It included 21 studies and 2187 participants, including six new trials with 450 individuals. Five studies concerned CBD-dominant preparations. For this group, the authors found no clear evidence of pain reduction by at least half, with the certainty of evidence rated as very low. For balanced preparations combining THC with CBD, a slight improvement in overall patient assessment was noted, but the authors themselves emphasize that the effect was not clinically significant, and at the same time, the number of individuals discontinuing participation due to adverse effects increased (Ateş et al., Cochrane Database of Systematic Reviews 2026).
This finding has indirect significance for our question because it concerns neuropathic pain, not restless legs syndrome. That is why it is worth citing: since in a well-studied adjacent indication, CBD-dominant preparations do not show clear effects, transferring expectations to an indication that is completely unstudied has no basis. Differences between types of pain are described separately in the text about nociceptive and neuropathic pain.
Does CBD improve sleep enough to help?
The data is weaker than its popularity suggests. The most frequently cited work is a retrospective review of psychiatric outpatient documentation, not a controlled study. Records of 103 adults were reviewed, and 72 individuals were included in the analysis: 47 reported primarily anxiety, and 25 primarily sleep disorders.
The results diverged between these two areas. Anxiety scores decreased in the first month for 57 individuals, or 79.2 percent, and remained lower until the end of the observation. Sleep scores improved in the first month for 48 individuals, or 66.7 percent, but fluctuated in subsequent months. Doses ranged from 25 to 175 milligrams per day, with nearly all patients receiving 25 milligrams in capsule form. CBD was well tolerated by all except three individuals, and the authors conclude that controlled clinical studies are needed (Shannon et al., The Permanente Journal 2019).
The statement about fluctuations in sleep scores is one that is usually omitted in reprints, and without it, the picture becomes too optimistic. The lasting improvement concerned anxiety, not sleep. The topic of sleep itself is explored more broadly in the text about CBD in treating insomnia and other sleep disorders.
What risks does CBD pose when taking prescription medications?
Real and well-documented, and particularly significant in this diagnosis because most patients take medications chronically. A review of the registration documentation for CBD preparations found adverse effects in nearly half of users, with a clear dose-dependent relationship. Commonly mentioned include:
- increased activity of aminotransferases, i.e., liver enzymes,
- sleepiness,
- sleep disturbances,
- infections,
- anemia.
Interactions are a separate issue. CBD interacts with the enzymes CYP3A4 and CYP2C19 and with P-glycoprotein, which are pathways by which the body processes and excretes many commonly used medications. The authors describe CBD as both a perpetrator and a victim of interactions and recommend that doctors monitor, reduce the dose of the primary medication, or choose another therapy, especially in patients taking multiple preparations at once (Brown and Winterstein, J Clin Med 2019). Which specific medications used in this diagnosis are involved is determined by the doctor or pharmacist based on a complete list of medications taken, not by an article.
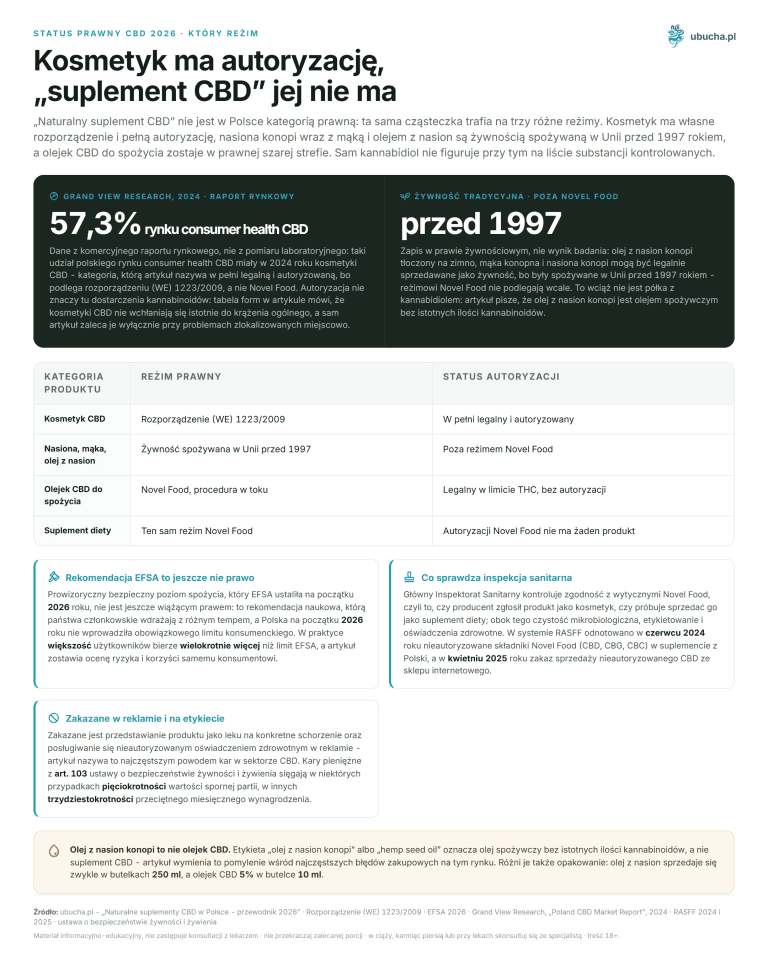
It is also worth knowing the limit set by the authority. The European Food Safety Authority set a temporary safe dose of CBD in 2026 at 0.0275 milligrams per kilogram of body weight per day, or about 2 milligrams for a person weighing 70 kilograms, and related it solely to supplements with a purity of at least 98 percent. It separately stated that safety cannot be established in individuals under 25 years of age, in pregnant and breastfeeding women, and in individuals taking medications simultaneously (EFSA, 2026). This last group is precisely the reader of this text. A similar divide between hope and evidence is described in the text about CBD for trigeminal neuralgia.
Frequently Asked Questions
Does CBD help with restless legs syndrome?
It cannot be said today. There is no controlled study that would examine CBD alone in this diagnosis. A description of six cases from 2017 concerned cannabis, and a trial from 2026 involved a preparation combining THC with CBD and was open, unblinded, and without a control group.
Where did the statement about the 2020 study come from?
From the confusion of two publications by the same author. The description of six patients comes from 2017, and in 2020 a brief report on additional patients was published. Both texts refer to cannabis, and in both, the author states that the matter should be resolved by solid clinical studies.
Can CBD replace medications prescribed for this condition?
No. Pharmacological treatment has documented effectiveness, and CBD has none in this indication. Discontinuing or changing medication on your own can exacerbate symptoms. Any changes should be discussed with the treating neurologist.
What should I start with if I suspect this syndrome?
With a diagnosis from a doctor and measuring ferritin levels. Iron deficiency is one of the reversible causes of symptoms, and international guidelines indicate a serum ferritin concentration of up to 75 micrograms per liter as the threshold at which iron treatment may be effective.
Can CBD interact with medications?
Yes. CBD interacts with the enzymes CYP3A4 and CYP2C19 and with P-glycoprotein, which are pathways for processing and excreting many medications. The authors of the review noted adverse effects in nearly half of the users, depending on the dose. Check your list of medications with your doctor or pharmacist.
Does CBD improve sleep?
The data is ambiguous. In a retrospective review of 72 psychiatric outpatient records, sleep scores improved in the first month for 66.7 percent, but fluctuated in subsequent months. The effect on anxiety proved to be more lasting than on sleep.
What dose of CBD is used for this diagnosis?
There is no established dose because there are no studies in this indication, and this neurological condition requires medical supervision. However, it is worth knowing the regulatory limit: EFSA has set a temporary safe dose at 0.0275 milligrams per kilogram of body weight per day.
This article is for informational and educational purposes only and does not constitute medical advice. Before starting to use cannabis or CBD for therapeutic purposes, consult your doctor, especially if you are taking other medications, are pregnant, or breastfeeding.
Author: Michał Waluk · Published: 2026-07-03 · Updated: 2026-08-16