CBD for asthma and the respiratory system: can cannabidiol alleviate symptoms

Does CBD alleviate asthma symptoms? We check how many clinical studies exist, why smoking and inhaling oil are dangerous, and when to call an ambulance.
Asthma is a disease where a bad decision can be fatal. It affects over 300 million people worldwide (Sule-Saa et al., Cureus, 2025), and a severe exacerbation can close the airways in just a few minutes. Therefore, the question in the title requires an exceptionally cautious answer. We searched the reviewed medical literature, and the result is clear: there is not a single randomized clinical trial of cannabidiol in asthma patients. All we have are animal models and single observations. This is too little to recommend anything and far too little to change treatment. Below, we show what the research really indicates, why inhaling anything with bronchial disease is a bad idea, and how to recognize when you need immediate help.
KEY INFORMATION
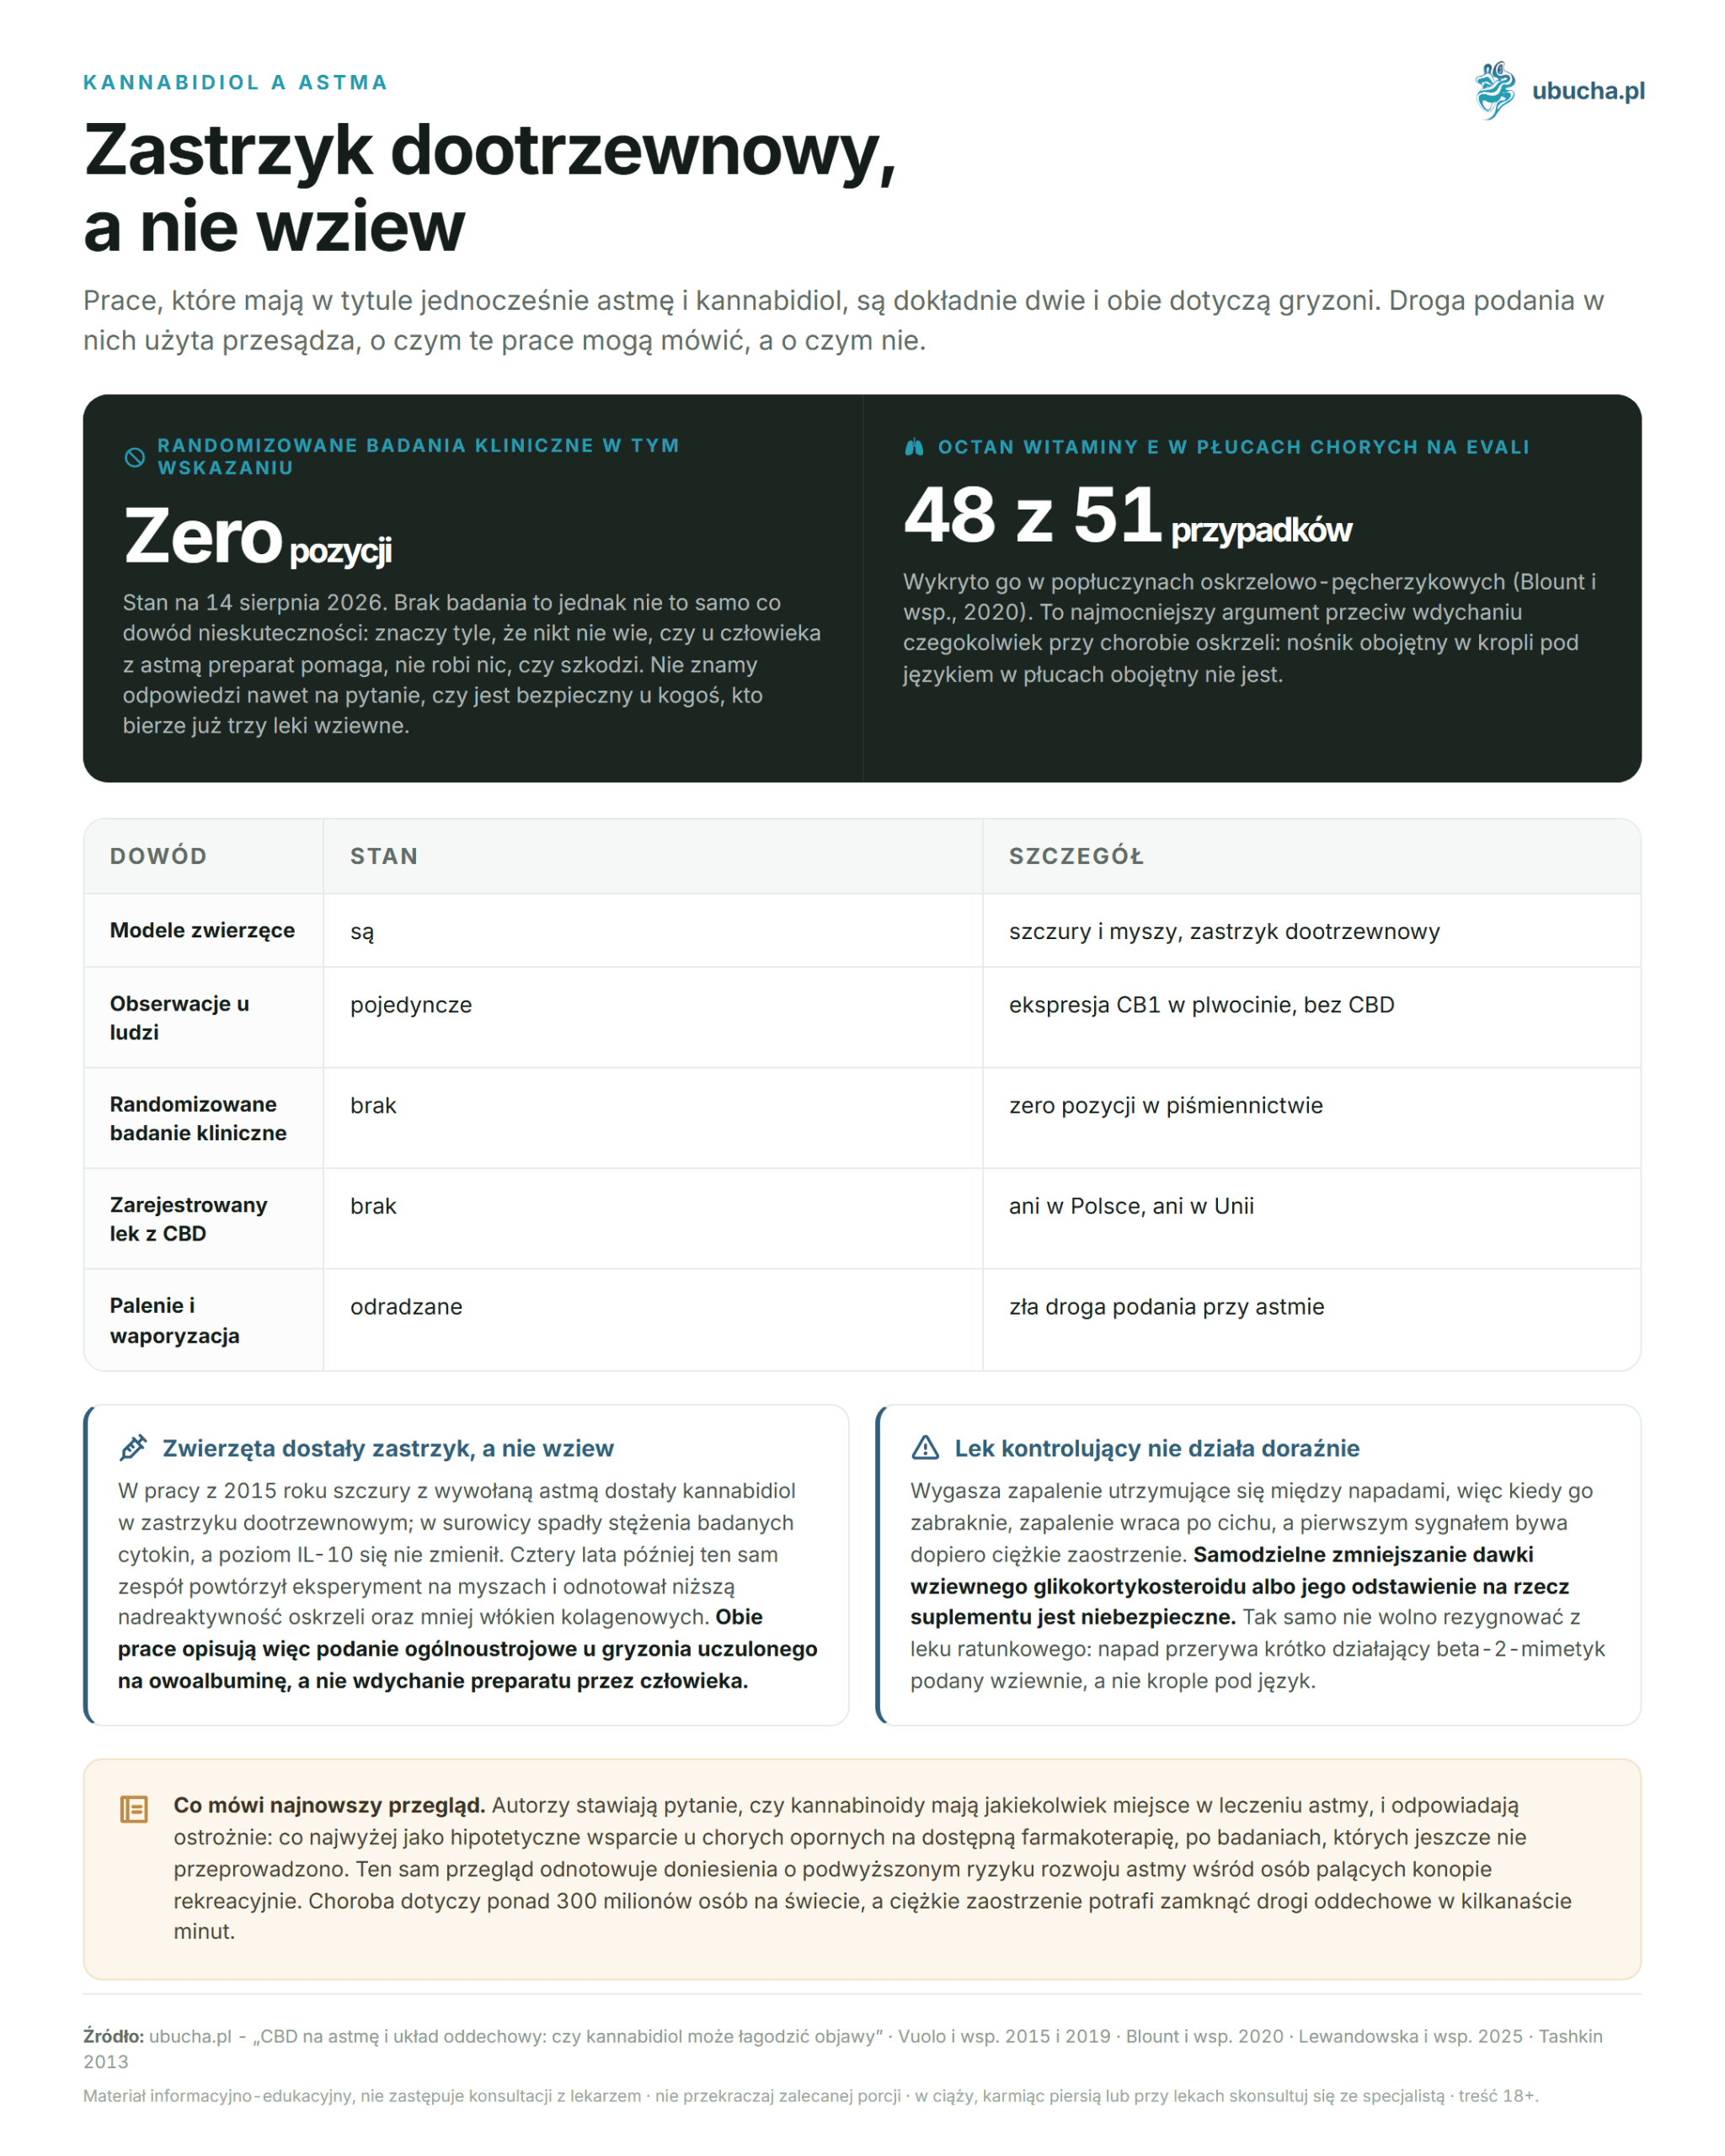
• There is no randomized clinical trial of CBD in asthma patients in the reviewed literature. The two papers with asthma and cannabidiol in the title are animal models (Vuolo et al., 2015 and 2019).
• Treatment of asthma is determined by a doctor. Self-discontinuation of a controlling medication is dangerous.
• Smoking and vaporization are poor routes of administration in bronchial disease (Tashkin, Annals ATS, 2013).
• Vitamin E acetate was found in the lungs of 48 out of 51 EVALI patients (Blount et al., NEJM, 2020).
Can CBD replace asthma medications?
No, and it should never be used that way. Inhaled glucocorticoids and beta-2-agonists have proven efficacy in asthma, and there is no clinical trial of cannabidiol for this indication. The medications you take and their dosages are determined by the attending physician, not an article on the internet.
This is the most important sentence in the entire text, so we will state it directly: self-reducing the dose of inhaled glucocorticoids or discontinuing them in favor of a supplement is dangerous. A controlling medication does not work acutely; it suppresses inflammation that persists between attacks. When it is absent, inflammation quietly returns, and the first signal may be a severe exacerbation. Similarly, you should not give up your rescue medication. An asthma attack is interrupted by a short-acting beta-2-agonist administered via inhalation, not drops under the tongue.
The authors of the review Lewandowska et al. (International Journal of Molecular Sciences, 2025) ask whether cannabinoids have any place in asthma treatment and cautiously respond: at most as hypothetical support for patients resistant to available pharmacotherapy, after studies that have not yet been conducted. The same review notes reports of an increased risk of developing asthma among individuals who smoke cannabis recreationally. No product containing cannabidiol is registered for asthma in Poland or the European Union.
Is there a single clinical trial of CBD in asthma?
There is none. We checked again on August 14, 2026, reviewing the reviewed medical literature. There are exactly two papers that have both asthma and cannabidiol in the title, and both concern rodents. Among randomized clinical trials linking cannabidiol with asthma, there is not a single one in which asthma patients received CBD.
It is important to understand what this means. The absence of a study is not the same as evidence of ineffectiveness. It means that no one knows whether cannabidiol helps, does nothing, or harms a person with asthma. We do not know the answers to the simplest questions: whether it changes the number of exacerbations and whether it is safe for someone who is already taking three inhaled medications. In medicine, the lack of safety data in a potentially fatal disease is treated as a risk, not as a green light.
Therefore, you will not find dosages in this article. There is no study from which they could be derived, and inserting a number would suggest knowledge that no one possesses.
What did animal studies show and what did they not show?
They showed a reduction in inflammation and bronchial hyperreactivity in rodents sensitized to ovalbumin. They did not show anything about humans. These are two different things, and mixing them is the most common mistake in texts about cannabidiol and the respiratory system.
In the study Vuolo et al. (Mediators of Inflammation, 2015), rats with induced asthma received cannabidiol via intraperitoneal injection. Serum levels of IL-4, IL-5, IL-13, IL-6, and TNF-alpha decreased, while IL-10 levels did not change. Four years later, Vuolo et al. (European Journal of Pharmacology, 2019) repeated the experiment on mice: cannabidiol reduced bronchial hyperreactivity, decreased the amount of collagen fibers in the walls of the airways and in the alveolar septa, and lowered inflammation markers in bronchoalveolar lavage fluid.
The same 2019 paper includes the only human thread. The authors measured the expression of CB1 and CB2 receptors in induced sputum from asthma patients and found an inverse relationship between CB1 levels and lung function. No one administered cannabidiol to these individuals. This is an observation about the biology of the disease, not a treatment test. Also, note the route of administration in animals: intraperitoneal injection. It cannot be replicated with drops, gels, or especially inhalation.
How does the endocannabinoid system work in the respiratory tract?
Bidirectionally, and that is the crux of the matter. CB1 receptors sit on the endings of bronchial nerves, and the endocannabinoid anandamide can both inhibit and induce bronchoconstriction, depending on the tension of the vagus nerve. This was described by Calignano et al. (Nature, 2000) in rodents.
This same paper reminds us of something that popular texts ignore: some asthma patients respond to tetrahydrocannabinol with paradoxical bronchoconstriction. Therefore, airway dilation after cannabinoids is not a rule, but one of two possible outcomes. In isolated human bronchi taken from 88 patients, tetrahydrocannabinol inhibited cholinergic contraction via presynaptic CB1 receptors by up to 39% (Grassin-Delyle et al., British Journal of Pharmacology, 2014).
And here appears a gap that is easy to overlook. These data concern tetrahydrocannabinol, which is a CB1 agonist. Cannabidiol is not a CB1 agonist, so the argument “CB1 dilates bronchi, therefore CBD dilates bronchi” is simply false. Cannabidiol is attributed with anti-inflammatory effects through other pathways, generally described by Nagarkatti et al. (Future Medicinal Chemistry, 2009). A coherent mechanism is still a hypothesis, not a result.
Why does smoking cannabis harm the respiratory tract?
Because smoke damages exactly that part of the respiratory system that is already diseased in asthma. Regular smoking of cannabis causes visible and microscopic damage to the large bronchi and is associated with symptoms of chronic bronchitis, which resolve after cessation of smoking. This was shown by Tashkin (Annals of the American Thoracic Society, 2013), summarizing several decades of his own research.
This same review mentions two mechanisms that are particularly inconvenient in asthma: loss of cilia in the bronchial epithelium and impaired ability of alveolar macrophages to kill microorganisms. Cilia are a system for clearing mucus from the bronchi, and there is too much mucus in asthma. Tashkin honestly notes that the pulmonary risk of smoking cannabis is lower than that of smoking tobacco and that a clear link with chronic obstructive pulmonary disease has not been established. However, this is not an argument for smoking in asthma, but rather that tobacco is worse.
Data on asthma patients themselves are scarce and observational in nature. In an analysis of 552,160 hospitalizations due to asthma from 2016 to 2021, a diagnosis of cannabis dependence was associated with higher in-hospital mortality (adjusted odds ratio 2.40) and a higher risk of severe exacerbation (Sule-Saa et al., Cureus, 2025). This is a correlation, not causal evidence, but the direction is clear.
Can CBD oil be inhaled, nebulized, or dropped into an inhaler?
No. Oils are not intended for inhalation, and there is no safe way to make an aerosol from oil for the lungs at home. Fat that reaches the lung alveoli can cause lipid pneumonia, which is a chronic inflammatory reaction around oil droplets that cannot be quickly reversed.
The best-documented warning is the EVALI epidemic. Vitamin E acetate, added as a thickener to cannabinoid cartridges, was found in bronchoalveolar lavage fluid in 48 out of 51 patients and in none of the 99 individuals in the comparison group (Blount et al., New England Journal of Medicine, 2020). The substance was considered harmless until it reached the lungs.
Pure cannabidiol in aerosol is also not neutral. Love et al. (American Journal of Respiratory Cell and Molecular Biology, 2025) showed that in commercial vaporizer cartridges, cannabidiol quinone forms covalent bonds with TOP2A protein in human respiratory epithelial cells, silencing cell cycle genes and inhibiting divisions. A broader review of the toxicology of inhaled vaporization products was compiled by Traboulsi et al. (International Journal of Molecular Sciences, 2020). We noted that oil manufacturers never declare suitability for inhalation, and this is not an oversight but a conscious boundary of responsibility.
Which asthma symptoms require immediate help?
Those for which nothing is checked except calling an ambulance at number 112. An asthma exacerbation can increase over hours or minutes, and some alarm signals are mistakenly perceived as improvement. The table below collects symptoms for which you do not wait until morning.
| Alarm signal | What it means |
|---|---|
| Shortness of breath increases despite rescue medication | Exacerbation is getting out of control |
| No response to rescue medication or need to repeat it every few minutes | Threatening state, medical help needed |
| Cyanosis of lips, tongue, or fingers | Hypoxia, immediate life-threatening state |
| Speaking in single words, lack of strength to finish a sentence | Severe limitation of airflow |
| Wheezing fades, and shortness of breath increases | Airflow is so low that it does not generate sound |
| Drowsiness, confusion, agitation | Hypercapnia symptom, indication for urgent intervention |
The principles of management in acute exacerbations of obstructive diseases were collected by Elsey and Allen (Clinical Medicine, 2021). No supplement is included in this algorithm, and there is no reason for it to ever be included.
Does CBD interact with asthma medications?
It may, as cannabidiol inhibits cytochrome P450 enzymes, through which some medications pass. The review Papakyriakopoulou et al. (British Journal of Clinical Pharmacology, 2026) describes the impact of cannabinoids on CYP3A4 and CYP2C19 as a real problem in polytherapy. Asthma often involves polytherapy.
| Medication | Metabolic pathway | What to ask your doctor |
|---|---|---|
| Theophylline | CYP1A2 | Narrow therapeutic window, monitoring concentration |
| Budesonide, fluticasone | CYP3A4 | Risk of increased systemic exposure |
| Montelukast | CYP3A4, CYP2C8, CYP2C9 | Possible change in drug concentration |
| Salbutamol, formoterol | Mainly outside CYP | Interaction unlikely |
| Biological drugs | Protein breakdown | Without cytochrome P450 involvement |
The table is a map of questions, not a verdict. The strength of each of these interactions depends on the dose of cannabidiol, the form of the preparation, and how well-controlled the asthma is. Only someone who sees your full list of medications, such as your attending physician or pharmacist, can resolve this.
It is worth knowing which way such an interaction works. Inhibition of an enzyme does not weaken the drug; it raises its concentration in the blood, so the risk concerns side effects, not loss of efficacy. With theophylline, symptoms of overdose can include nausea, palpitations, and tremors. Therefore, the conversation about cannabidiol in asthma starts with a list of medications, not with choosing a product.
What to do if you are still considering CBD for asthma?
Start by talking to a pulmonologist or allergist and ask for a clear answer: yes or no. Be straightforward about which product you want to use and in what form. Bring the packaging and a list of all medications, including over-the-counter ones, to the appointment. Until that conversation, do not change anything in your asthma treatment.
If the doctor has no objections, the following three boundaries must not be crossed under any circumstances. Only oral or sublingual forms, never inhaled. The asthma treatment plan remains unchanged, and you carry your rescue medication with you just as before. Any worsening of asthma control means discontinuing the supplement and contacting your doctor, not increasing the amount.
We have noticed that most questions come from people who simply want to reach for their inhaler less often. This is understandable, and it is not the way to achieve the goal. Less frequent use of rescue medication is achieved through better control of inflammation, which means treatment set with a doctor, and by removing triggers from the environment. A diary can be helpful: measuring peak expiratory flow, the number of uses of rescue inhalers, and sleep quality. More about allergic mechanisms is discussed in the post CBD for allergies, and about immunity in the infection season in the post CBD and colds and immunity.
Frequently asked questions
Does CBD cure asthma?
No. There is not a single randomized clinical trial of cannabidiol in asthma patients in the reviewed literature. The two papers that have asthma and cannabidiol in the title are animal models: Vuolo et al. (2015) on rats and Vuolo et al. (2019) on mice. Results from rodents do not automatically transfer to humans.
Can you smoke or vaporize CBD with asthma?
No. Regular smoking of cannabis damages the epithelium of the large bronchi, causes loss of cilia, and is associated with symptoms of chronic bronchitis (Tashkin, Annals ATS, 2013). The aerosol from a vaporizer also irritates hyperreactive airways. With bronchial disease, you inhale only what your doctor prescribed.
Is it allowed to put CBD oil in a nebulizer or inhaler?
No. Oils are not intended for inhalation, and fat in the lung alveoli poses a risk of lipid pneumonia. Vitamin E acetate from vaporizer cartridges was found in the lungs of 48 out of 51 EVALI patients and in none of the 99 healthy individuals (Blount et al., NEJM, 2020).
Can CBD replace inhaled glucocorticoids?
No. Inhaled glucocorticoids and beta-2-agonists have proven efficacy in asthma, and there is no clinical trial of cannabidiol for this indication. The medications and their dosages are determined by the attending physician. Self-reducing or discontinuing a controlling medication leads to exacerbations and can be dangerous.
Does CBD interact with asthma medications?
It can. Cannabidiol inhibits CYP enzymes, including CYP3A4 and CYP2C19, thus altering the concentrations of drugs metabolized through this pathway (Papakyriakopoulou et al., BJCP, 2026). Theophylline, which has a narrow therapeutic window, and inhaled glucocorticoids metabolized by CYP3A4 require attention.
When should you call an ambulance for asthma?
When shortness of breath increases despite rescue medication, when the medication stops working or needs to be repeated every few minutes, when cyanosis of the lips or fingers appears, when you speak in single words and cannot finish a sentence, and when drowsiness or confusion increases. The emergency number is 112.
If the pulmonologist has no objections, you can find hemp oils for oral and sublingual use in the oils section of the store at u Bucha. None of them is suitable for inhalation.
This article is for informational and educational purposes and does not constitute medical advice. Before starting to use cannabis or CBD for therapeutic purposes, consult your doctor, especially if you are taking other medications, are pregnant, or breastfeeding.
Author: Michał Waluk · Published: 2026-06-22 · Updated: 2026-08-14