
Zinc for Immunity and Acne: Dosage, When to Take, and What Effects
How much zinc to take for acne and immunity? The EFSA limit is 25 mg, FDA 40 mg. Data from studies, forms, interactions, and the risk of copper deficiency all in one place.
Zinc is one of the most studied trace elements, yet online guides can recommend doses twice as high as the European safety limit. EFSA has set the upper tolerable intake level at 25 mg per day, while the American FDA has set it at 40 mg. The dose given in studies on acne was 30 mg, which is already above the EU threshold, and was administered for a limited time under the supervision of researchers. This difference gets lost along the way to the product description, and it is precisely from it that the outcome of supplementation will depend on whether it ends with an improvement in skin condition or secondary copper deficiency. This text shows what studies on zinc for acne and colds have really demonstrated, where their results can be exaggerated, and how the available forms differ. We have checked each cited work in the European PMC database, and you can do the same by clicking on the link next to any number.
KEY INFORMATION
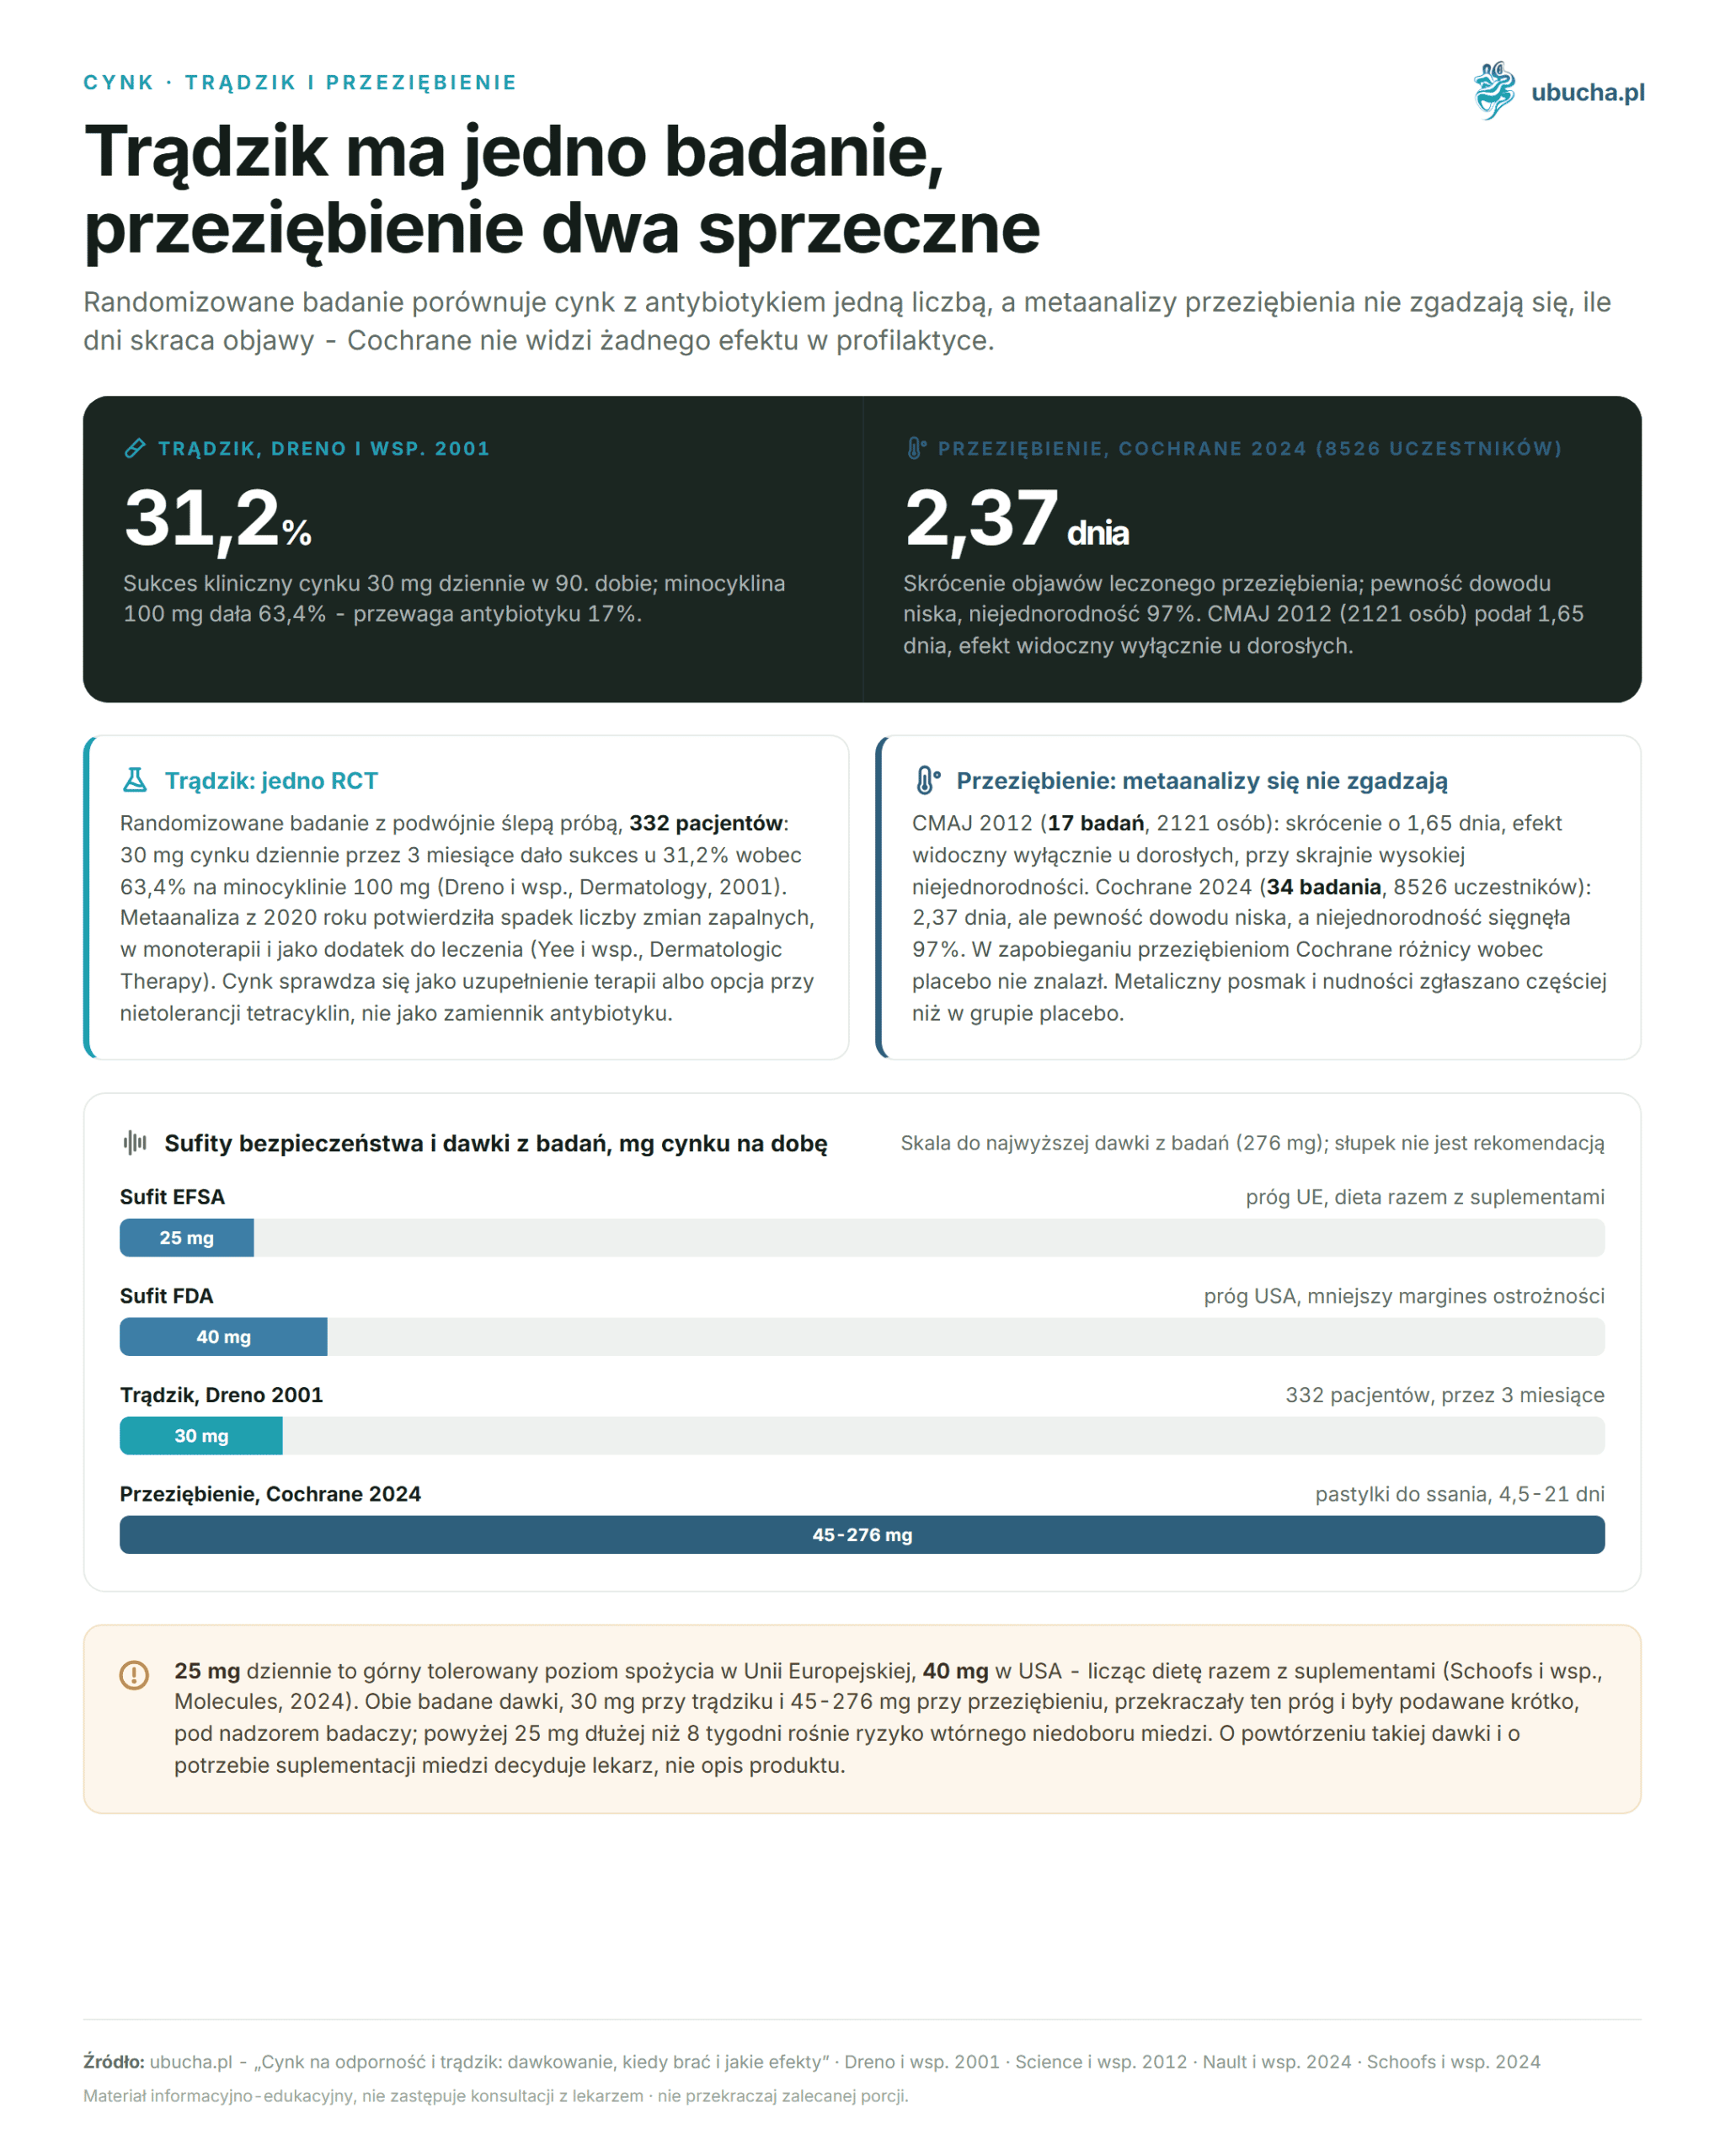
• Upper tolerable intake level: 25 mg per day in the European Union, 40 mg in the USA (Schoofs et al., Molecules, 2024).
• Dreno et al. (Dermatology, 2001): 30 mg of zinc achieved success in 31.2% of patients, minocycline in 63.4%.
• For colds, the data pertains to lozenges used in treatment, not in prevention, and meta-analyses differ in terms of effect strength.
• Above 25 mg per day for more than 8 weeks increases the risk of secondary copper deficiency.
What is zinc responsible for in the body?
Zinc is involved in over 300 enzymatic reactions, in the regulation of gene expression, in apoptosis, and in immune modulation (Schoofs et al., Molecules, 2024). The body does not store it in the same way it stores iron, so intake must be daily.
The skin is the third tissue in the body in terms of zinc content (Ogawa et al., Nutrients, 2018). Hence the clear dermatological symptoms in deficiency: inflammatory changes, slower wound healing, hair loss, and dry skin. Zinc is responsible for keratinocyte division and collagen synthesis in the skin.
The scale of the nutritional problem is estimated by the FAO food balance analysis: 15% of the world’s population, or 1.13 billion people, consume too little zinc (Wessells et al., Nature Food, 2024). This mainly concerns regions where the diet is based on grains rich in phytates. The norms are also not uniform. The American recommendation is 11 mg for men and 8 mg for women, while EFSA (2014) calculates the requirement depending on phytates in the diet: 9.4-16.3 mg for men and 7.5-12.7 mg for women.
We noticed while organizing sources one thing that rarely makes it into product descriptions: serum zinc concentration is a poor screening test. It only drops with a clear deficiency, as the body first draws on reserves from bones and muscles, and any infection lowers the result regardless of tissue reserves. A normal result does not therefore close the case.
Does zinc really help with acne?
It helps, but less effectively than antibiotics. In a randomized double-blind study of 332 patients, 30 mg of elemental zinc achieved clinical success in 31.2% of individuals, while 100 mg of minocycline achieved success in 63.4% (Dreno et al., Dermatology, 2001). The authors assessed the antibiotic’s advantage at 17%.
This study is often summarized online as “zinc is as effective as antibiotics.” The original conclusion is different: both substances act on inflammatory changes, but minocycline performs better. Zinc thus makes sense as a supplement to therapy or as an option for those who cannot take tetracyclines. It is not a substitute for treatment conducted by a dermatologist and should not delay the start of treatment for severe or scarring acne.
A later meta-analysis confirmed two things: people with acne have lower serum zinc levels than control groups, and supplementation reduces the number of inflammatory papules, both in monotherapy and as an addition to standard treatment (Yee et al., Dermatologic Therapy, 2020). A systematic review of 42 studies on supplements for acne, involving a total of 3346 participants, found that adverse effects were rare for most evaluated preparations. Zinc was mentioned separately as one for which gastrointestinal complaints were reported (Shields et al., JAMA Dermatology, 2023).
There are at least three mechanisms. Zinc inhibits the growth of Cutibacterium acnes, suppresses the secretion of pro-inflammatory cytokines by keratinocytes, and limits the activity of 5-alpha-reductase, the enzyme that converts testosterone to DHT. This third effect has been demonstrated on human skin outside the body (Stamatiadis et al., British Journal of Dermatology, 1988), at zinc concentrations of 3 to 9 millimoles per liter, which oral supplementation in the sebaceous follicle is unlikely to replicate. It is also worth remembering the time scale: in Dreno’s study, a full assessment was conducted only on day 90, so observation after two weeks does not yet say anything.
Does zinc shorten a cold?
Probably yes, but the evidence is weaker than suggested by packaging. A meta-analysis of 17 studies involving 2121 people showed an average symptom reduction of 1.65 days, with extremely high heterogeneity of results and the effect visible only in adults (Science et al., CMAJ, 2012).
The Cochrane review from 2024 included 34 studies and 8526 participants. In treating colds, it showed a reduction of 2.37 days, but the authors rated the certainty of evidence as low, and heterogeneity reached 97%. In preventing colds, zinc made no difference: the risk of illness remained practically the same as with placebo (Nault et al., Cochrane Database of Systematic Reviews, 2024).
The most important caveat concerns the form of the preparation. Lozenges were used in half of the studies in the Cochrane review, 17 out of 34, and the most common form was gluconate, administered in doses from 45 to 276 mg per day for 4.5 to 21 days. These doses are many times above the safety limit, used briefly and under the supervision of researchers. The symptom reduction pertains to treatment already started for a cold, as in prevention, the same review found no difference. A daily 15 mg capsule taken on the third day of a cold is therefore a completely different intervention, and those results should not be transferred to it. The price of the effect is real: a metallic taste and nausea were reported more frequently than in the placebo group.
A separate situation is low zinc supply in older individuals. In a year-long study of 50 healthy individuals aged 55 to 87, whose baseline serum zinc levels were lower than those of younger adults, 45 mg of zinc daily reduced the number of infections and the levels of oxidative stress markers compared to placebo (Prasad et al., American Journal of Clinical Nutrition, 2007). The group was small, and the dose exceeded both safety limits, so this was a controlled research scheme, not a recommendation for self-repetition.
How much zinc can be safely taken?
The upper tolerable intake level is 25 mg per day according to EFSA and 40 mg according to FDA (Schoofs et al., Molecules, 2024). The discrepancy arises from different safety margins adopted for the same phenomenon: excess zinc impairs copper absorption. The limit includes the sum from diet and supplements.
| Number | How much elemental zinc | What it really concerns |
|---|---|---|
| Upper limit EFSA | 25 mg per day | threshold for adults in the European Union, counting diet together with supplements |
| Upper limit FDA | 40 mg per day | American threshold, adopted with a smaller margin of safety |
| American norm | 11 mg men, 8 mg women | recommended intake, not therapeutic dose |
| EFSA norm | 9.4-16.3 mg men, 7.5-12.7 mg women | value increases with the content of phytates in the diet |
| Dose from acne study | 30 mg per day for 3 months | Dreno 2001, 332 patients, clinical success in 31.2% |
| Doses from cold studies | 45-276 mg per day for 4.5-21 days | lozenges in Cochrane review 2024, under researcher supervision |
| Dose from study in older adults | 45 mg per day for 12 months | Prasad 2007, 50 individuals aged 55-87 |
| Dose from case report | 65 mg per day | undetectable copper and neutropenia in one patient |
Symptoms of chronic excess are not just nausea. In secondary copper deficiency, anemia, neutropenia, and a decrease in HDL cholesterol along with an increase in LDL have been described, as well as separate neurological symptoms (Schoofs et al., Molecules, 2024). The same work describes the case of a 66-year-old patient who took 65 mg of zinc daily from a multivitamin and gluconate: copper levels dropped below the detection threshold, neutropenia occurred, and recovery from this state required stopping zinc, administering granulocyte growth factor, and copper supplementation. Therefore, how long it is permissible to maintain a dose above the limit and whether copper is needed with it is determined by a doctor, not the product description.
Which form of zinc is absorbed best?
The best-documented advantage is for bisglycinate. In a study of 12 healthy women, a single dose of 15 mg provided 43.4% higher zinc bioavailability than the same dose of gluconate (Gandia et al., International Journal for Vitamin and Nutrition Research, 2007). The trial was small and involved a single dose, so it does not resolve the effects of multi-week supplementation.
| Form | Zinc content in salt | What this means |
|---|---|---|
| Bisglycinate (chelate) | about 30% in pure salt, preparations may be standardized lower | good tolerance, best result in direct comparison |
| Picolinate | about 21% | comparative data comes from the 80s and is scarce |
| Sulfate | 22.7% (heptahydrate), about 36% (monohydrate) | cheapest, often causes nausea on an empty stomach |
| Gluconate | about 14% | form used in lozenges |
| Oxide | about 80%, but practically insoluble | ointments, sunscreens, poor choice orally |
A historical comparison of picolinate, citrate, and gluconate from 1987 favored picolinate, but involved a small group of volunteers and has not been repeated with comparable methodology (Barrie et al., Agents and Actions, 1987). Do not treat it as a decisive argument when choosing a preparation.
The practical conclusion is simpler than product descriptions suggest. When you count the dose in milligrams of elemental zinc, the differences between soluble forms are smaller than the difference made by daily regularity. Bisglycinate has an advantage where sulfate causes nausea and thus may be discontinued after a week.
When and how to take zinc?
With a light meal containing protein, at a regular time of day, and with a gap from antibiotics and iron preparations. Sulfate and gluconate taken on an empty stomach often cause nausea. Bisglycinate may be tolerated without food, but for effect, a regular time matters more than the choice of moment.
Zinc forms insoluble complexes with fluoroquinolone antibiotics, such as ciprofloxacin and levofloxacin, and with tetracyclines, such as doxycycline and minocycline. This reduces their absorption. The interval that must be maintained is specified in the leaflet of the specific antibiotic and is counted in hours, not minutes. This interaction has practical significance in acne, as both substances are often used concurrently. Zinc also reduces the absorption of penicillamine, and thiazide diuretics increase its excretion in urine.
Of dietary components, phytates from whole grains, legumes, and nuts interfere the most. Calcium in larger doses acts similarly. Animal protein works the opposite way and improves absorption. Iron from supplements competes with zinc for the same transporter, so separate them at different times of the day.
From our review of labels, another trap emerges: product descriptions regularly confuse the mass of the salt with the mass of elemental zinc. One hundred milligrams of zinc gluconate is about 14 mg of zinc, not 100 mg. Before you assume you are taking 30 mg, find the line on the label that says “of which zinc.” The same mistake works the other way and can lead to unintentional exceeding of the limit.
More about combining preparations for the infection season can be found in the post Supplements for Autumn and Immunity. We described how differences between forms look with another mineral in the text Magnesium for Stress and Sleep.
Who is at the highest risk of zinc deficiency?
Four groups stand out the most: people on plant-based diets, seniors, patients with inflammatory bowel diseases or celiac disease, and individuals who abuse alcohol. Additionally, pregnant and breastfeeding women have increased requirements. The common denominator is always the same: poorer absorption or a diet based on products rich in phytates that bind zinc in the intestine.
- Plant-based diets: phytates from grains and legumes bind zinc in the intestine, so the requirement shifts towards the upper value of the EFSA range.
- Aged 65 and over: poorer intestinal absorption with a poorer diet and medications altering stomach pH.
- Inflammatory bowel diseases and celiac disease: damaged mucosa limits absorption, and diarrhea increases losses.
- Alcohol abuse: increased renal excretion with simultaneously poorer absorption.
- Pregnancy and lactation: requirements increase, and the diet rarely covers them.
- Endurance sports: some zinc is lost through sweat during long, intense training sessions.
The richest food source is oysters, which exceed other products by an order of magnitude. Next are red meat and liver. Reasonable amounts are also found in pumpkin seeds and cheese. Plant sources, such as lentils, chickpeas, or whole grains, contain zinc, but alongside blocking phytates. Soaking and sprouting, as well as fermentation with sourdough, break down some phytates and realistically improve absorption.
Besides facial skin, zinc is often mentioned in relation to hair loss and wound healing. A review dedicated to nutrition and hair bases the diagnosis of deficiency on history, clinical examination, and targeted laboratory tests, not on trial supplementation (Finner, Dermatologic Clinics, 2013). This is a sensible default approach to all indications described above: first determine if there is a deficiency, and only then supplement.
Frequently Asked Questions
How much zinc should I take daily for acne?
In the study Dreno et al. (2001), 332 patients received 30 mg of elemental zinc daily for three months. This dose is above the European limit of 25 mg per day, administered under supervision and for a limited time, so whether to repeat it for yourself is determined by a doctor, especially due to the risk of secondary copper deficiency.
Can zinc replace dermatological treatment for acne?
No. In a study of 332 patients, 30 mg of zinc achieved clinical success in 31.2% of individuals, while 100 mg of minocycline achieved success in 63.4%, with the authors assessing the antibiotic’s advantage at 17%. Zinc works as a supplement to therapy or an option for those intolerant to tetracyclines.
Does zinc shorten a cold?
Probably yes, but the meta-analyses vary. Science et al. (CMAJ, 2012) reported a 1.65-day reduction with very high heterogeneity, while Cochrane in 2024 reported 2.37 days with low certainty of evidence. The data pertains to lozenges used in the treatment of an ongoing cold, not in prevention.
How much zinc is too much?
The upper tolerable level is 25 mg per day according to EFSA and 40 mg according to FDA, counting both diet and supplements. Chronic excess leads to secondary copper deficiency, and along with it to anemia, neutropenia, and a decrease in HDL cholesterol. Undetectable copper levels and neutropenia have been described in a patient taking 65 mg daily.
Which form of zinc is best?
Bisglycinate provided 43.4% higher zinc bioavailability than gluconate in a study of 12 women after a single dose of 15 mg (Gandia et al., 2007). However, the differences between soluble forms are smaller than the impact of regular intake. Avoid zinc oxide in oral preparations.
What should not be combined with zinc?
Do not combine zinc with a fluoroquinolone antibiotic or tetracycline at the same time, as they form insoluble complexes; the interval is specified in the leaflet of the specific drug. Also, do not combine it with iron from supplements, as they compete for the same transporter. Phytates from whole grains, legumes, and nuts bind zinc in the intestine.
Products from this group can be found in the supplements section of the u Bucha store.
This article is for informational and educational purposes and does not replace consultation with a doctor. If you are pregnant, breastfeeding, taking medications, or have chronic conditions, consult the use of supplements or herbs with a specialist.
Author: Michał Waluk · Published: 2026-06-22 · Updated: 2026-08-14