
CBD Oil for Sleep - How Many Drops and When to Use 2026
CBD oil for sleep without made-up numbers: safe dose according to EFSA 2026, what Shannon, Linares, and Walsh studies really showed, and where data ends.
CBD oil for sleep has been surrounded by numbers that do not appear in the studies cited as their source. This text was created by rechecking every citation at the original source, not by repeating what circulates in guides. The picture has changed significantly: some numbers disappeared because the study addressed something entirely different, and some remained but in a narrower form. Here you will find the provisional safe dose calculated by EFSA in 2026 and descriptions of the Shannon, Linares, Walsh, and Corroon studies along with participant numbers and duration. You will not find dose tables by body weight or titration plans. Below we explain why they are not included here.
KEY INFORMATION
- EFSA calculated in 2026 a provisional safe dose of cannabidiol at 0.0275 mg per kilogram of body weight per day, about 2 mg for a person weighing 70 kilograms.
- Cannabidiol safety cannot be established in people under 25 years old, pregnant or breastfeeding women, and people taking medications.
- The statement about 1500 mg per day attributed to WHO was removed from this article: the source document does not correspond, and the value differs from EFSA’s calculation by three orders of magnitude.
- Shannon’s 2019 study is a retrospective chart analysis of 72 patients, and its abstract does not provide any dose.
- There is no published study on cannabinol with polysomnography or validated sleep questionnaires.
What daily CBD dose is considered safe today?
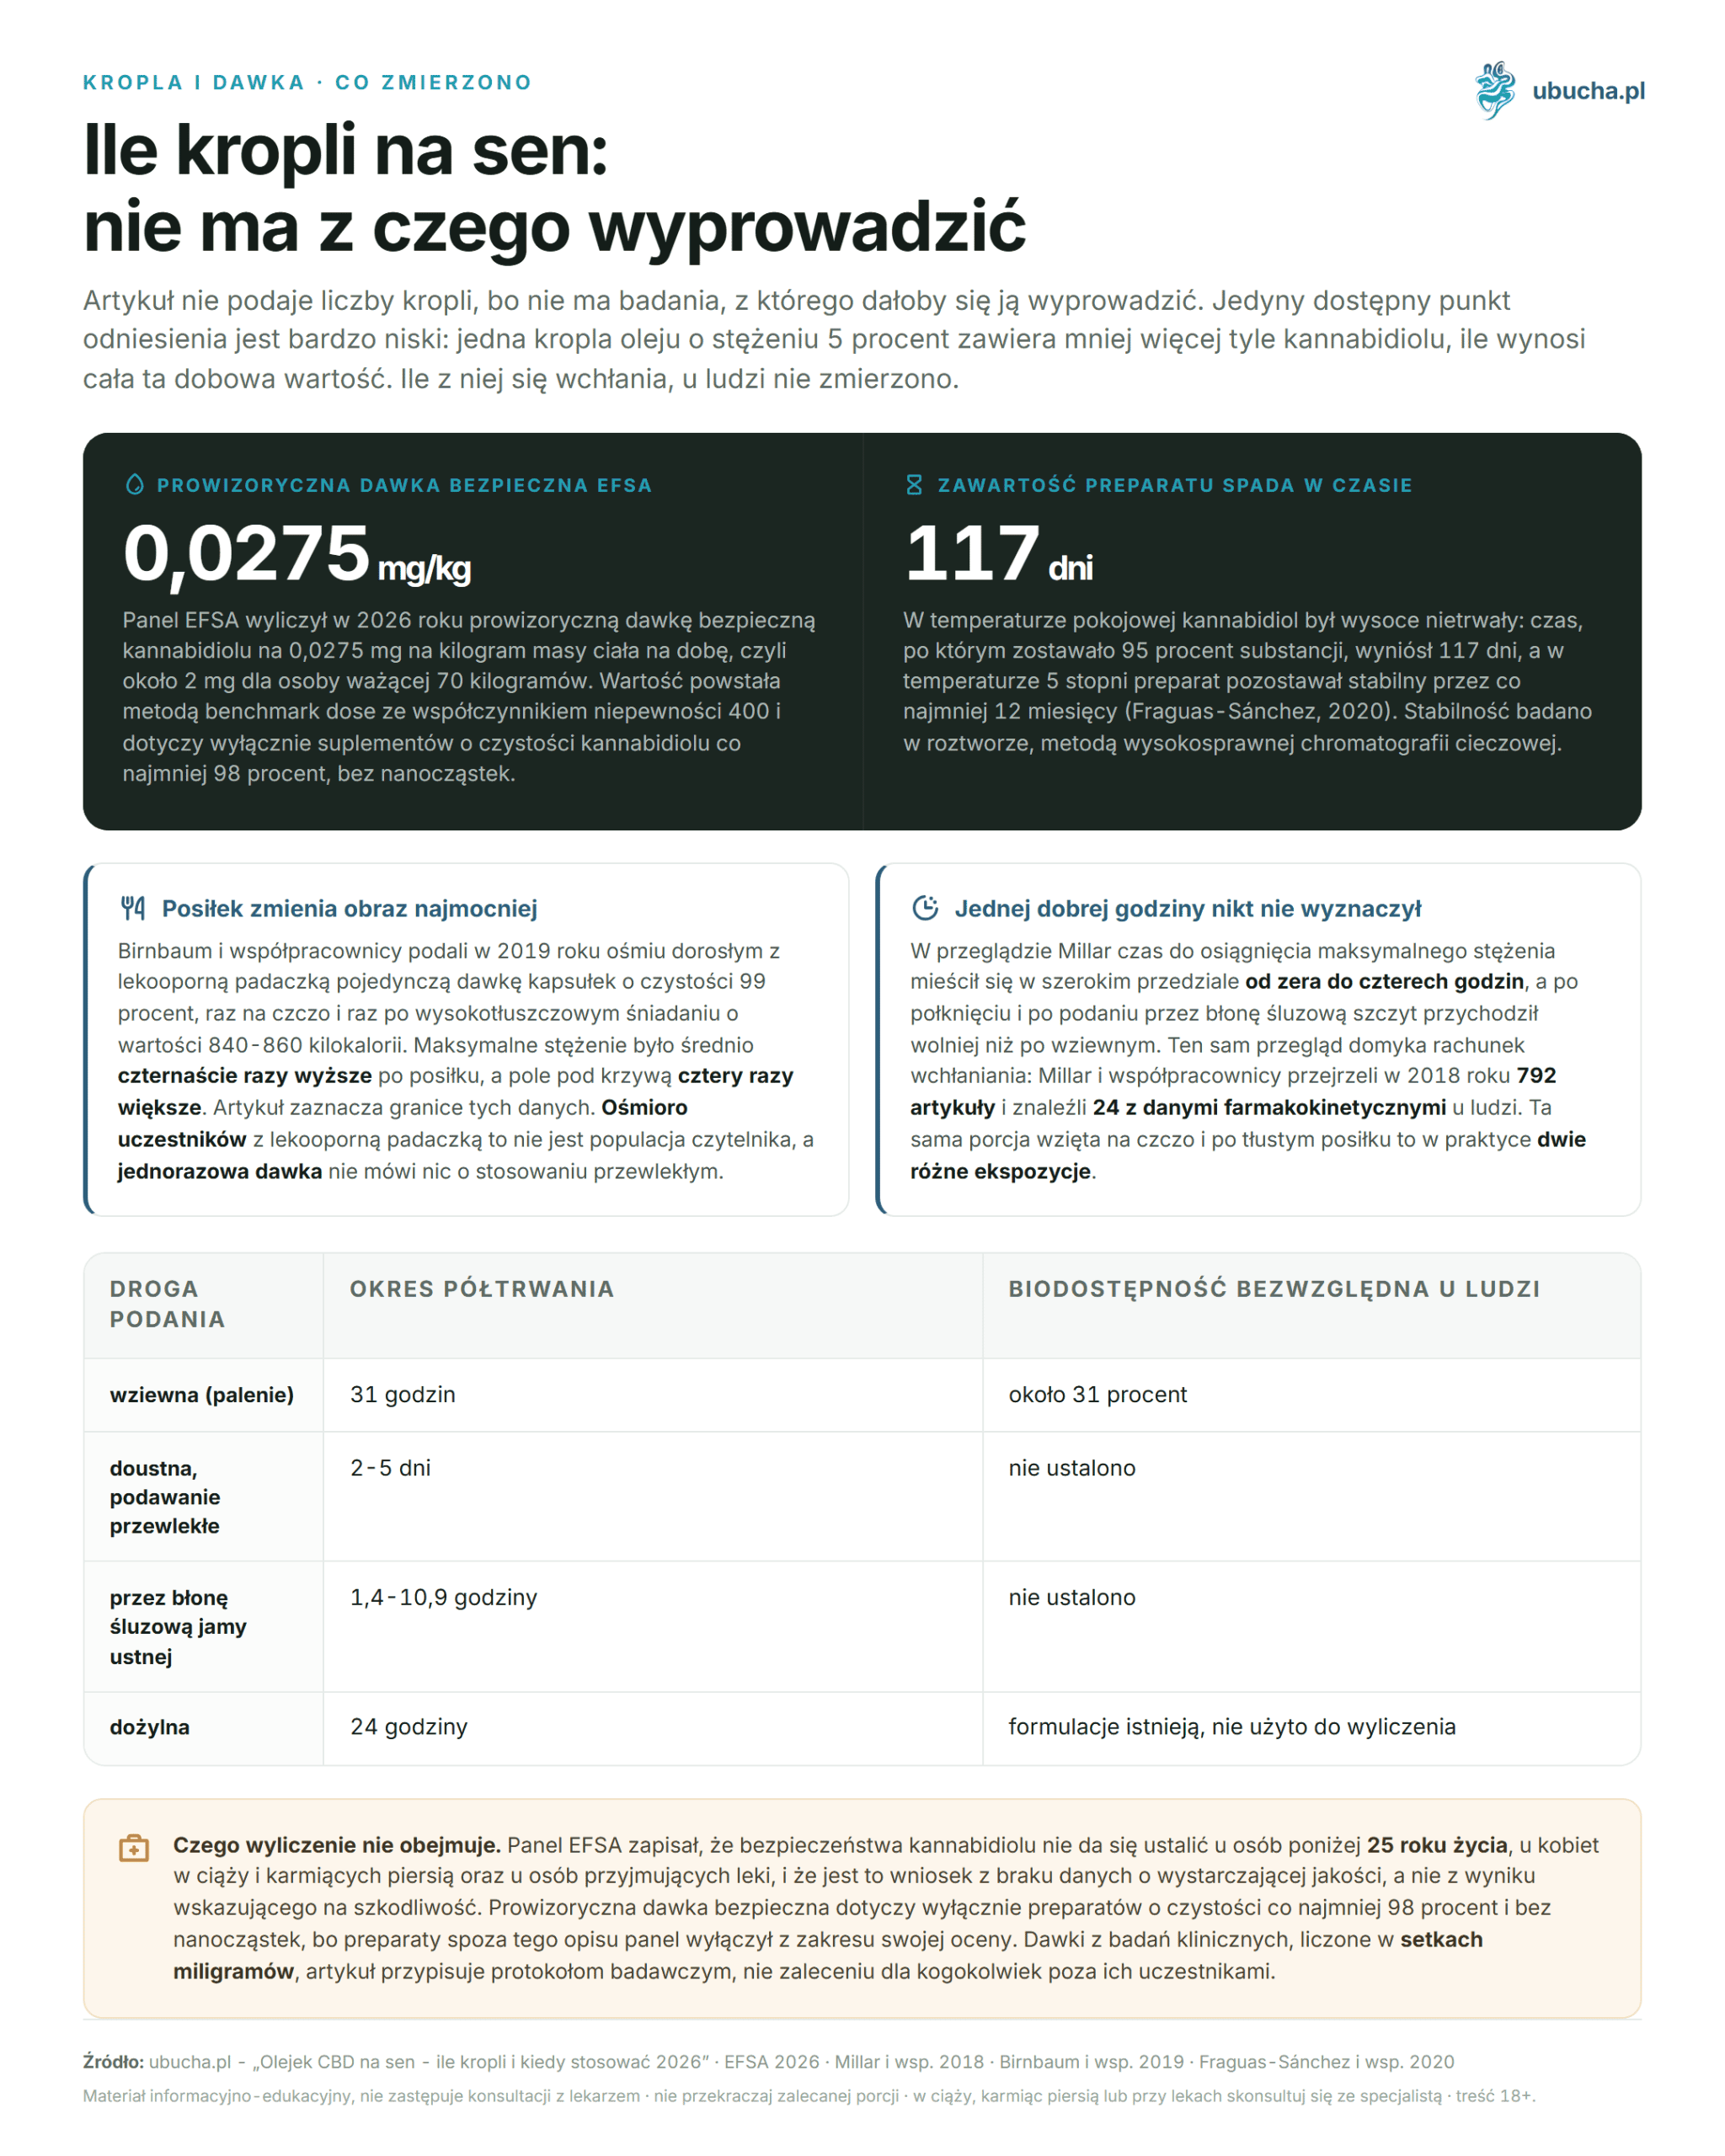
The EFSA panel calculated in 2026 a provisional safe dose of cannabidiol at 0.0275 mg per kilogram of body weight per day, about 2 mg for a person weighing 70 kilograms. This value was derived using the benchmark dose method with an uncertainty factor of 400 and applies exclusively to supplements with cannabidiol purity of at least 98 percent, without nanoparticles (EFSA, 2026).
This single number changes how the rest of the text should be read. Doses appearing in clinical sleep studies are hundreds of milligrams given once under researcher supervision. The study protocol and a supplement bought in a store are two different situations, and the number from one does not transfer to the other. For comparison: one drop of 5 percent oil contains roughly as much cannabidiol as the entire daily reference value.
The panel also included a sentence rarely mentioned in dosing guides but very important. Cannabidiol safety cannot be established in people under 25 years old, pregnant or breastfeeding women, and people taking medications. This is not a precautionary phrase added at the end but a conclusion from lack of sufficient quality data. The panel lists gaps concerning liver, reproductive, nervous, and hormonal systems.
Therefore, there are no dose tables by body weight or plans to increase portions every few days. Such tables circulate on the Polish internet without a supporting study. Milligram numbers appear only when describing a specific study: who conducted it, how many participants, duration, and doses. The statement about 1500 mg per day attributed to WHO, which appeared twice in this article, has also been removed.
What are EFSA’s reservations about cannabidiol?
The list is longer than the word supplement suggests. The 2022 assessment identified significant data gaps, and a literature search of animal and human studies up to June 2024 confirmed these gaps remain. Many new studies have methodological limitations: non-standardized protocols, short duration, and concurrent pharmacological treatment of participants.
The liver is the most frequently mentioned concern. Animal studies showed consistent hepatotoxicity, with liver mass and histopathological changes as the most sensitive endpoints. Based on such subchronic studies conducted according to good laboratory practice, the panel set the toxicological reference point. Human studies indicated hepatotoxic potential, especially with concurrent use of other drugs, and gastrointestinal effects were reported at higher doses.
The second group of concerns relates to reproduction and development. Animal studies reinforced concerns about reproductive toxicity, and prenatal exposure showed neurodevelopmental effects suggesting long-term sex-dependent consequences. Hormonal disturbances were also noted, including altered thyroid hormone levels and adrenal histopathological changes. No study addressed immunotoxicity, although cannabidiol interacts with immune pathways.
Pharmacokinetics completes the picture. The panel confirms cannabidiol bioavailability is variable and depends on the carrier and food intake; the substance crosses the placenta and accumulates in the body. The cautious final conclusion about groups where safety cannot be established results from all these premises, not a single alarming result. For the reader, this means one thing: lack of data is not evidence of safety.
How can CBD oil affect sleep?
The most honest answer is: indirectly and less than advertising suggests. Babson et al.’s 2017 review summarizes that preliminary work on cannabidiol and insomnia indicates therapeutic potential, but cannabis and sleep research is in early stages and results are mixed (Current Psychiatry Reports, 2017).
The same review separates cannabinoids, which the industry usually does not. THC may shorten sleep onset but worsens sleep quality with long-term use. Synthetic cannabinoids, nabilone and dronabinol, provide short-term benefit in sleep apnea. Cannabidiol is mainly linked to REM behavior disorder and excessive daytime sleepiness, and nabilone to reducing nightmares in PTSD.
The path with the most data leads through anxiety, not directly through sleep. Blessing et al.’s 2015 review states that preclinical evidence strongly supports cannabidiol’s anxiolytic effect after acute administration, and human data also support this, but are limited to acute dosing and few clinical populations (Neurotherapeutics, 2015).
Receptor descriptions circulating in guides come from animal and cell model studies. No study shows the full chain from receptor to polysomnography result in humans. Therefore, the paragraph about FAAH enzyme inhibition and increased anandamide levels as an explanation for sedative effect was removed. The mechanism may be true but has not been measured in humans and cannot justify expectations for a specific oil dose.
What did Shannon’s 2019 study really show?
It was a retrospective chart analysis from one psychiatric clinic, not a controlled study. Charts of 103 adult patients were reviewed; 72 entered the final sample: 47 reported mainly anxiety, 25 sleep problems. Cannabidiol was given as an add-on to existing treatment (Permanente Journal, 2019).
Results should be read exactly as recorded. Anxiety scores dropped in the first month in 57 patients (79.2 percent) and remained lower throughout observation. Sleep scores improved in the first month in 48 patients (66.7 percent) but fluctuated in following months. Authors state the preparation was well tolerated except by three patients and conclude controlled clinical trials are needed.
Three things previously stated in this article are not in the study. The abstract does not list any dose, so the 25-175 mg range repeated five times and the table justifying it were removed. There is no basis for the statement that the effect remained stable after three months, as authors explicitly mention fluctuations. The sentence about four patients withdrawing due to adverse effects was replaced with the actual data: three patients poorly tolerated the preparation.
The study’s weight should be set properly. The chart analysis shows what happened to patients who received cannabidiol but does not say how much was due to the preparation itself. There was no placebo or randomization, and patients continued prior treatment and psychotherapy. This is a premise to study further, not proof of efficacy.
Does CBD change sleep architecture?
In healthy volunteers, it did not change it at all. Linares et al.’s 2018 randomized crossover study selected 27 healthy people, one withdrew during the study. Each participant received 300 mg cannabidiol or placebo on the first night, and the other substance on the second night (Frontiers in Pharmacology, 2018).
The preparation was given 30 minutes before an eight-hour polysomnographic recording. Cognitive and subjective tests were done immediately after to detect residual effects. None showed significant differences. Authors conclude acute anxiolytic cannabidiol dose does not interfere with sleep-wake cycle in healthy volunteers and supports the idea of no effect on normal sleep architecture.
In the previous version of this article, the study had a third arm with flunitrazepam and stated benzodiazepine shortened REM phase by 19 percent. No such arm exists in the paper. Only cannabidiol and placebo were compared in a crossover design. The 19 percent figure had no source and was removed along with the sentence carrying it.
A negative result is sometimes misread as evidence of effect. The study says only that a single dose does not disrupt sleep in a good sleeper. It says nothing about helping a poor sleeper. The authors end by calling for studies in patient populations and chronic dosing, which their protocol did not cover.
Does CBN really help falling asleep?
There is no published evidence. Corroon’s 2021 review was written exactly to answer this question. He screened abstracts of 99 human studies, selected eight full texts for detailed analysis, and concluded in one sentence: published evidence is insufficient to support claims of cannabinol’s effect on sleep (Cannabis and Cannabinoid Research, 2021).
Details are stronger than the conclusion. Cannabinol studies are outdated and few; most human studies date from the 1970s and 1980s on small, demographically narrow samples. Studies measuring sedation or fatigue are rare. The author found no published clinical study comparing cannabinol with validated sleep questionnaires or polysomnography.
Also, product amounts matter. Hemp products sold with sleep support claims usually contain 5 mg or less of cannabinol, and the author notes future studies should use significantly higher doses. Even if an effect exists, typical oil amounts are probably below the threshold for any observable effect.
This article previously claimed cannabinol lengthens deep sleep phase and broad-spectrum oils are more sedative than isolates because of it. Both statements were removed. No study supports them, and the review looking at this question ends with advice to remain skeptical of manufacturers’ claims.
Five studies on CBD and sleep with their limitations
Data look best where poor sleep is secondary to another problem, but these are still small samples. The table below collects studies cited here with participant numbers and duration, because without these columns each study sounds stronger than it is.
| Study | Design | Participants | Duration | Result |
|---|---|---|---|---|
| Shannon 2019 | retrospective chart analysis, no placebo | 72 adults | first month reported separately | sleep improvement in 66.7 percent, fluctuations in following months |
| Linares 2018 | randomized, crossover, double-blind | 27 healthy volunteers | two nights | no significant effect of 300 mg dose on polysomnography |
| Walsh 2021 | randomized, crossover, placebo-controlled | 24 chronic insomnia patients, 23 completed | 2 weeks | ISI score lower by 5.07 points, self-reported sleep time longer by 64.6 minutes |
| Elms 2019 | retrospective case series, open dosing | 11 adults with PTSD | 8 weeks | lower PCL-5 score in 10 people, mean from 51.82 to 37.14 |
| Chagas 2014 | case report | 4 Parkinson’s patients with REM behavior disorder | not stated in abstract | rapid and clear reduction in episode frequency, no adverse effects |
Three reservations should be read with the table. Walsh et al.’s study was the only randomized placebo-controlled trial in chronic insomnia patients but tested a cannabinoid extract labeled ZTL-101, not pure cannabidiol, so its result should not be attributed to CBD alone. Elms et al.’s work is a case series with open dosing, and its endpoint was PTSD symptom severity, not sleep quality. Chagas’ report covers four patients.
The 91 percent figure previously in this article referred to sleep improvement. In the study, this percentage describes symptom score reduction in the PCL-5 questionnaire, and authors cautiously state the preparation relieved some patients reporting frequent nightmares. This sentence was corrected, not removed, because the study exists and says something meaningful, just about a different topic. A broader discussion of this disorder is in a separate article on insomnia from a sleep medicine perspective.
How many drops under the tongue are really absorbed?
No one has measured this in humans. Millar et al. reviewed 792 articles in 2018 and found 24 with human pharmacokinetic data. Absolute bioavailability was reported only for inhalation, about 31 percent. No study attempted this for oral or sublingual routes (Frontiers in Pharmacology, 2018).
| Route of administration | Half-life | Absolute bioavailability in humans |
|---|---|---|
| inhalation (smoking) | 31 hours | about 31 percent |
| oral, chronic administration | 2-5 days | not established |
| oral mucosa (spray) | 1.4-10.9 hours | not established |
| intravenous | 24 hours | formulations exist but were not used for calculation |
This is why the four-column table with values 6-10 percent for swallowing, 13-19 percent for sublingual, and 30-40 percent for nanoemulsions was removed. These numbers have circulated on the Polish internet for years, and the cited source is a review on terpenes and entourage effect in mood disorders. It contains no bioavailability data. This table has no correct version, so it was replaced by a statement about what has not been measured.
The practical conclusion is more modest than often stated. Comparing drops to capsules in percentages is guessing today. Holding oil under the tongue for a minute is a manufacturer recommendation, not a human measurement. It is more sensible to observe your own effect with a consistent administration method than to calculate how many milligrams reached the bloodstream.
When to take the oil and should you eat before dosing?
Timing matters less than the meal. Millar’s review found time to maximum concentration ranged widely from zero to four hours, and after swallowing or mucosal administration, the peak came slower than after inhalation. No single good hour before sleep has been set.
Meal changes the picture most. Birnbaum et al. gave eight adults with drug-resistant epilepsy a single dose of 99 percent pure cannabidiol capsules once fasting and once after a high-fat breakfast of 840-860 kcal. Maximum concentration was on average fourteen times higher after the meal, and area under the curve four times larger. No adverse effects were noted (Epilepsia, 2019). Millar’s review confirms the direction: maximum concentration rises when fed and with fatty formulations.
The practical conclusion is different from usual. The same dose taken fasting and after a fatty meal is practically two different exposures. If you want to assess whether something works, keep a consistent routine: same evening time and same relation to dinner. Changing both at once makes it impossible to distinguish a good night from good digestion.
These data limits must be seen. Eight participants with drug-resistant epilepsy are not the article reader’s population, and a single dose says nothing about chronic use. The effect direction is consistent in both studies, enough to treat meal as a variable, not an insignificant detail.
Does more CBD mean better sleep?
The dose-response relationship here is not a simple increase. Linares et al. gave 57 healthy men oral cannabidiol at 150 mg to 15 people, 300 mg to 15, 600 mg to 12, or placebo to 15, in a double-blind design before simulated public speaking (Revista Brasileira de Psiquiatria, 2019).
Only the 300 mg dose significantly reduced anxiety during the speech. Groups receiving 150 mg and 600 mg did not differ from placebo. Authors say the result confirms the bell-shaped curve described in animals and that optimal therapeutic doses must be rigorously determined before clinical use. The caveat is important: healthy men were studied, endpoint was anxiety before speech, not sleep, and administration was single.
The second study in this thread concerns cortisol and is often summarized oppositely to its meaning. Zuardi et al. gave 11 volunteers placebo or cannabidiol at 300 mg to seven and 600 mg to four. Sessions were in the morning. Cortisol levels dropped significantly in placebo sessions, following normal circadian rhythm, but cannabidiol significantly blunted this drop (Brazilian Journal of Medical and Biological Research, 1993).
In other words, cannabidiol did not lower cortisol but dulled its natural morning decline. Prolactin and growth hormone did not change, and calming effects were noted in self-assessment scales. The previous article version attributed the bell curve to Zuardi’s 2017 Journal of Psychopharmacology study on empathy after MDMA. The citation was replaced and the claim rewritten to reflect what both studies actually say.
Does CBD oil interact with medications?
Yes, and this is today the best-established part of all caution around cannabidiol. Nasrin et al. tested in 2021 in vitro on microsomes from cells overexpressing enzymes how cannabinoids inhibit liver cytochrome P450 enzymes. Cannabidiol competitively inhibited CYP3A4, CYP2B6, CYP2C9, CYP2D6, and CYP2E1 (Drug Metabolism and Disposition, 2021).
Authors add that simple modeling suggests possible pharmacokinetic interactions with drugs metabolized intensively by CYP2B6, CYP2C9, or CYP2D6. This is an ex vivo measurement and does not set a human dose threshold. Therefore, the sentence about enzyme inhibition only above 100 mg per day, which appeared twice in this article, was removed. It did not come from any cited study.
The second source says the same from another angle. The EFSA panel writes that human studies indicated hepatotoxic potential of cannabidiol, especially with other drugs, and safety cannot be established in people taking medications. If you take any prescription drug, talking to your doctor is not a formality but a prerequisite. This also applies when the drug seems harmless because interaction occurs at metabolism, not effect level.
The address previously supporting this paragraph led to Udomsinprasert et al.’s 2019 study on adiponectin gene polymorphism and anterior cruciate ligament injury risk. The study exists and has nothing to do with cytochrome P450. The same identifier appears in another article of this pair and dozens of other blog texts, always under claims about drug interactions.
Sleep hygiene before supplement, not instead of it
The preparation will not fix a disrupted circadian rhythm. If bedtime changes night to night and the last hour before sleep looks like any other hour of the day, the variable governing sleep quality remains untouched. It is worth setting it before testing anything because otherwise you cannot say what worked.
The simplest set is a fixed wake-up time, even on days off, morning exposure to daylight, a cool and dark bedroom, and an evening that really differs from daytime. Caffeine consumed in the afternoon still works in the evening. Alcohol shortens sleep onset at the cost of the second half of the night. Intense exercise just before sleep raises body temperature when it should drop. None of these require buying anything.
If the problem lasts longer than a few weeks and impairs daytime functioning, it is time to talk to a doctor, not to try another supplement. Cognitive-behavioral therapy for insomnia is therapist-led and no oil replaces it. We described home habits more broadly in the article on natural ways to sleep without pills, and melatonin dosing is discussed separately in the article on melatonin and its dosing.
There is one more reason to start with habits. All studies described above were conducted with participants having a stabilized daily schedule and researcher supervision. Applying their results to a person who goes to bed at varying times compares two different situations.
How to recognize a worthwhile oil to buy?
By documents, not label description. A certificate of analysis for a specific batch, issued by an independent laboratory, is the only place where declared cannabidiol content meets measured content. It also checks heavy metals, pesticide residues, and solvents used in extraction.
Purity gained additional importance after EFSA’s opinion. The provisional safe dose calculated by the panel applies only to supplements with cannabidiol content of at least 98 percent and without nanoparticles. Preparations outside this description do not even have such a reference point because the panel explicitly excluded them from its assessment scope.
Price alone does not decide anything, but order of magnitude can be useful. In the oil category at u Bucha store, prices ranged on August 10, 2026, from 65 to 240 PLN per package, with various concentrations and volumes. Stock changes faster than the article, so treat this range as a reference point, not a price list.
The choice between broad and full spectrum has no resolution in sleep data today. Corroon’s review showed the argument based on cannabinol has no support, and the entourage effect remains a hypothesis mainly described in reviews. If you undergo drug tests at work, full spectrum carries real risk due to trace THC amounts. This criterion is more concrete than speculation about synergy.
How to store oil to preserve content?
Cool and dark, because cannabidiol is unstable. Fraguas-Sánchez et al. studied its stability in solution by high-performance liquid chromatography in 2020. Temperature was one of the most critical parameters, with activation energy of 92.19 kJ/mol (Journal of Chromatography B, 2020).
Numbers from this study speak for themselves. At room temperature, cannabidiol was highly unstable, with 95 percent remaining after 117 days. At 5 degrees Celsius, the preparation remained stable for at least 12 months. In an oxidizing environment, the same indicator dropped to 1.77 days, and the substance was also light-sensitive, with photolytic reaction appearing oxidative.
Matrix type also matters. Cannabidiol is more stable in ethanol than aqueous environment, and under physiological-like conditions (pH 7.4, 37 degrees), 10 percent decomposed within a day. Kosović et al. added in 2021 an observation from a stress test following ICH guidelines: cannabidiol powder was significantly more stable than dissolved in sunflower oil (Pharmaceutics, 2021).
The practical conclusion is simple and costless. A dark bottle, tight closure, a cool place away from kitchen windowsill, and reasonable use time after opening do more for preparation content than choosing between broad and full spectrum. Oil kept for months on a windowsill may contain significantly less cannabidiol than the label declares, even if the batch’s certificate of analysis was correct at testing.
Summary: what these studies mean in practice
After checking all sources, the picture is more modest and honest than before. Cannabidiol has the best-documented anxiolytic effect after acute administration, and its impact on sleep appears mainly where poor sleep accompanies anxiety or PTSD. In healthy volunteers, a single 300 mg dose did not change polysomnographic recording in any direction.
The reference point for supplements remains EFSA’s calculation, about 2 mg per day for a 70-kilogram person, conditioned by preparation purity and a clear statement about groups where safety cannot be established. Clinical study doses, counted in hundreds of milligrams, belong to study protocols and are not recommendations for anyone outside participants.
What remains to do in the evening? Fixed time, fixed relation to meals, one product with a certificate of analysis, and patience long enough to distinguish effect from chance. If you take medications, are pregnant, breastfeeding, or under 25, decide on cannabidiol with a doctor because data to support independent decisions simply do not exist.
Frequently Asked Questions
How many drops of CBD oil should I take for sleep?
There is no study from which such a number can be derived. The only available reference point is the provisional safe dose from EFSA in 2026: 0.0275 mg per kilogram of body weight per day, which is about 2 mg for a person weighing 70 kilograms. Dose tables by weight have no source and have been removed from this article.
Does CBD oil cure insomnia?
No. In Shannon’s 2019 chart analysis, sleep improvement was noted in the first month in 66.7 percent of 72 patients, but results fluctuated in subsequent months, and the study had no placebo. The only randomized study in people with chronic insomnia tested a cannabinoid extract, not pure cannabidiol.
When is the best time to take CBD oil in the evening?
No one has set a single good hour. In Millar’s 2018 review, time to maximum concentration ranged from zero to four hours. Meal timing matters more: after a high-fat breakfast, maximum concentration was on average fourteen times higher than on an empty stomach. Keep a consistent evening routine.
Does CBD disrupt REM sleep?
In Linares’ 2018 randomized crossover study, a 300 mg dose did not significantly affect any measured sleep parameter in 27 healthy volunteers, including REM phase. The study did not include people with insomnia and did not compare cannabidiol with benzodiazepine, contrary to what was previously stated in this text.
Is it worth looking for CBN oil for sleep?
Corroon’s 2021 review found not a single published clinical study comparing cannabinol with a validated sleep questionnaire or polysomnography. The author concludes that published evidence is insufficient to support claims of sedative effects and advises skepticism toward manufacturers’ declarations.
Can CBD be combined with prescription medications?
Not without consulting a doctor. In Nasrin’s 2021 laboratory studies, cannabidiol competitively inhibited CYP3A4, CYP2B6, CYP2C9, CYP2D6, and CYP2E1, enzymes metabolizing many drugs. The EFSA panel adds that cannabidiol safety cannot be established in people taking medications.
Is it safe to use CBD during pregnancy or before age 25?
The EFSA panel stated in 2026 that cannabidiol safety cannot be established in people under 25 years old, pregnant or breastfeeding women, and people taking medications. This conclusion is due to lack of sufficient quality data, not evidence of harm. Make the decision with your doctor.
Check current assortment and concentrations in the hemp oils category, as stock changes continuously.
This article is for informational and educational purposes and does not constitute medical advice. Before starting cannabis or CBD for therapeutic purposes, consult a doctor, especially if you take other medications, are pregnant, or breastfeeding.
Author: Michał Waluk · Published: 2026-05-11 · Updated: 2026-08-10