
Liver Supplements: Milk Thistle, NAC, Choline, and TUDCA
The strongest evidence is for weight reduction, not a capsule. What has been shown for milk thistle, NAC, choline, and TUDCA and in what doses they were studied.
When searching for “liver supplements,” the search engine suggests milk thistle, NAC, and choline. The problem is that the best-documented intervention for fatty liver is not a capsule. It is weight reduction, exercise, and alcohol limitation. Separately, you ask about TUDCA, and for that term, this page is visible today, so we respond below in the entire section. The Cochrane review on milk thistle found no impact on overall mortality or liver histology, and the only beneficial result disappeared after narrowing the analysis to higher quality studies. Moreover, herbal and dietary supplements account for one-fifth of drug-induced liver injury cases in the United States today, so a supplement can sometimes be not a shield but a culprit. Below, we organize what studies say about these three ingredients, where the evidence ends and marketing begins, and when liver test results require a doctor instead of another product from the shelf.
KEY INFORMATION
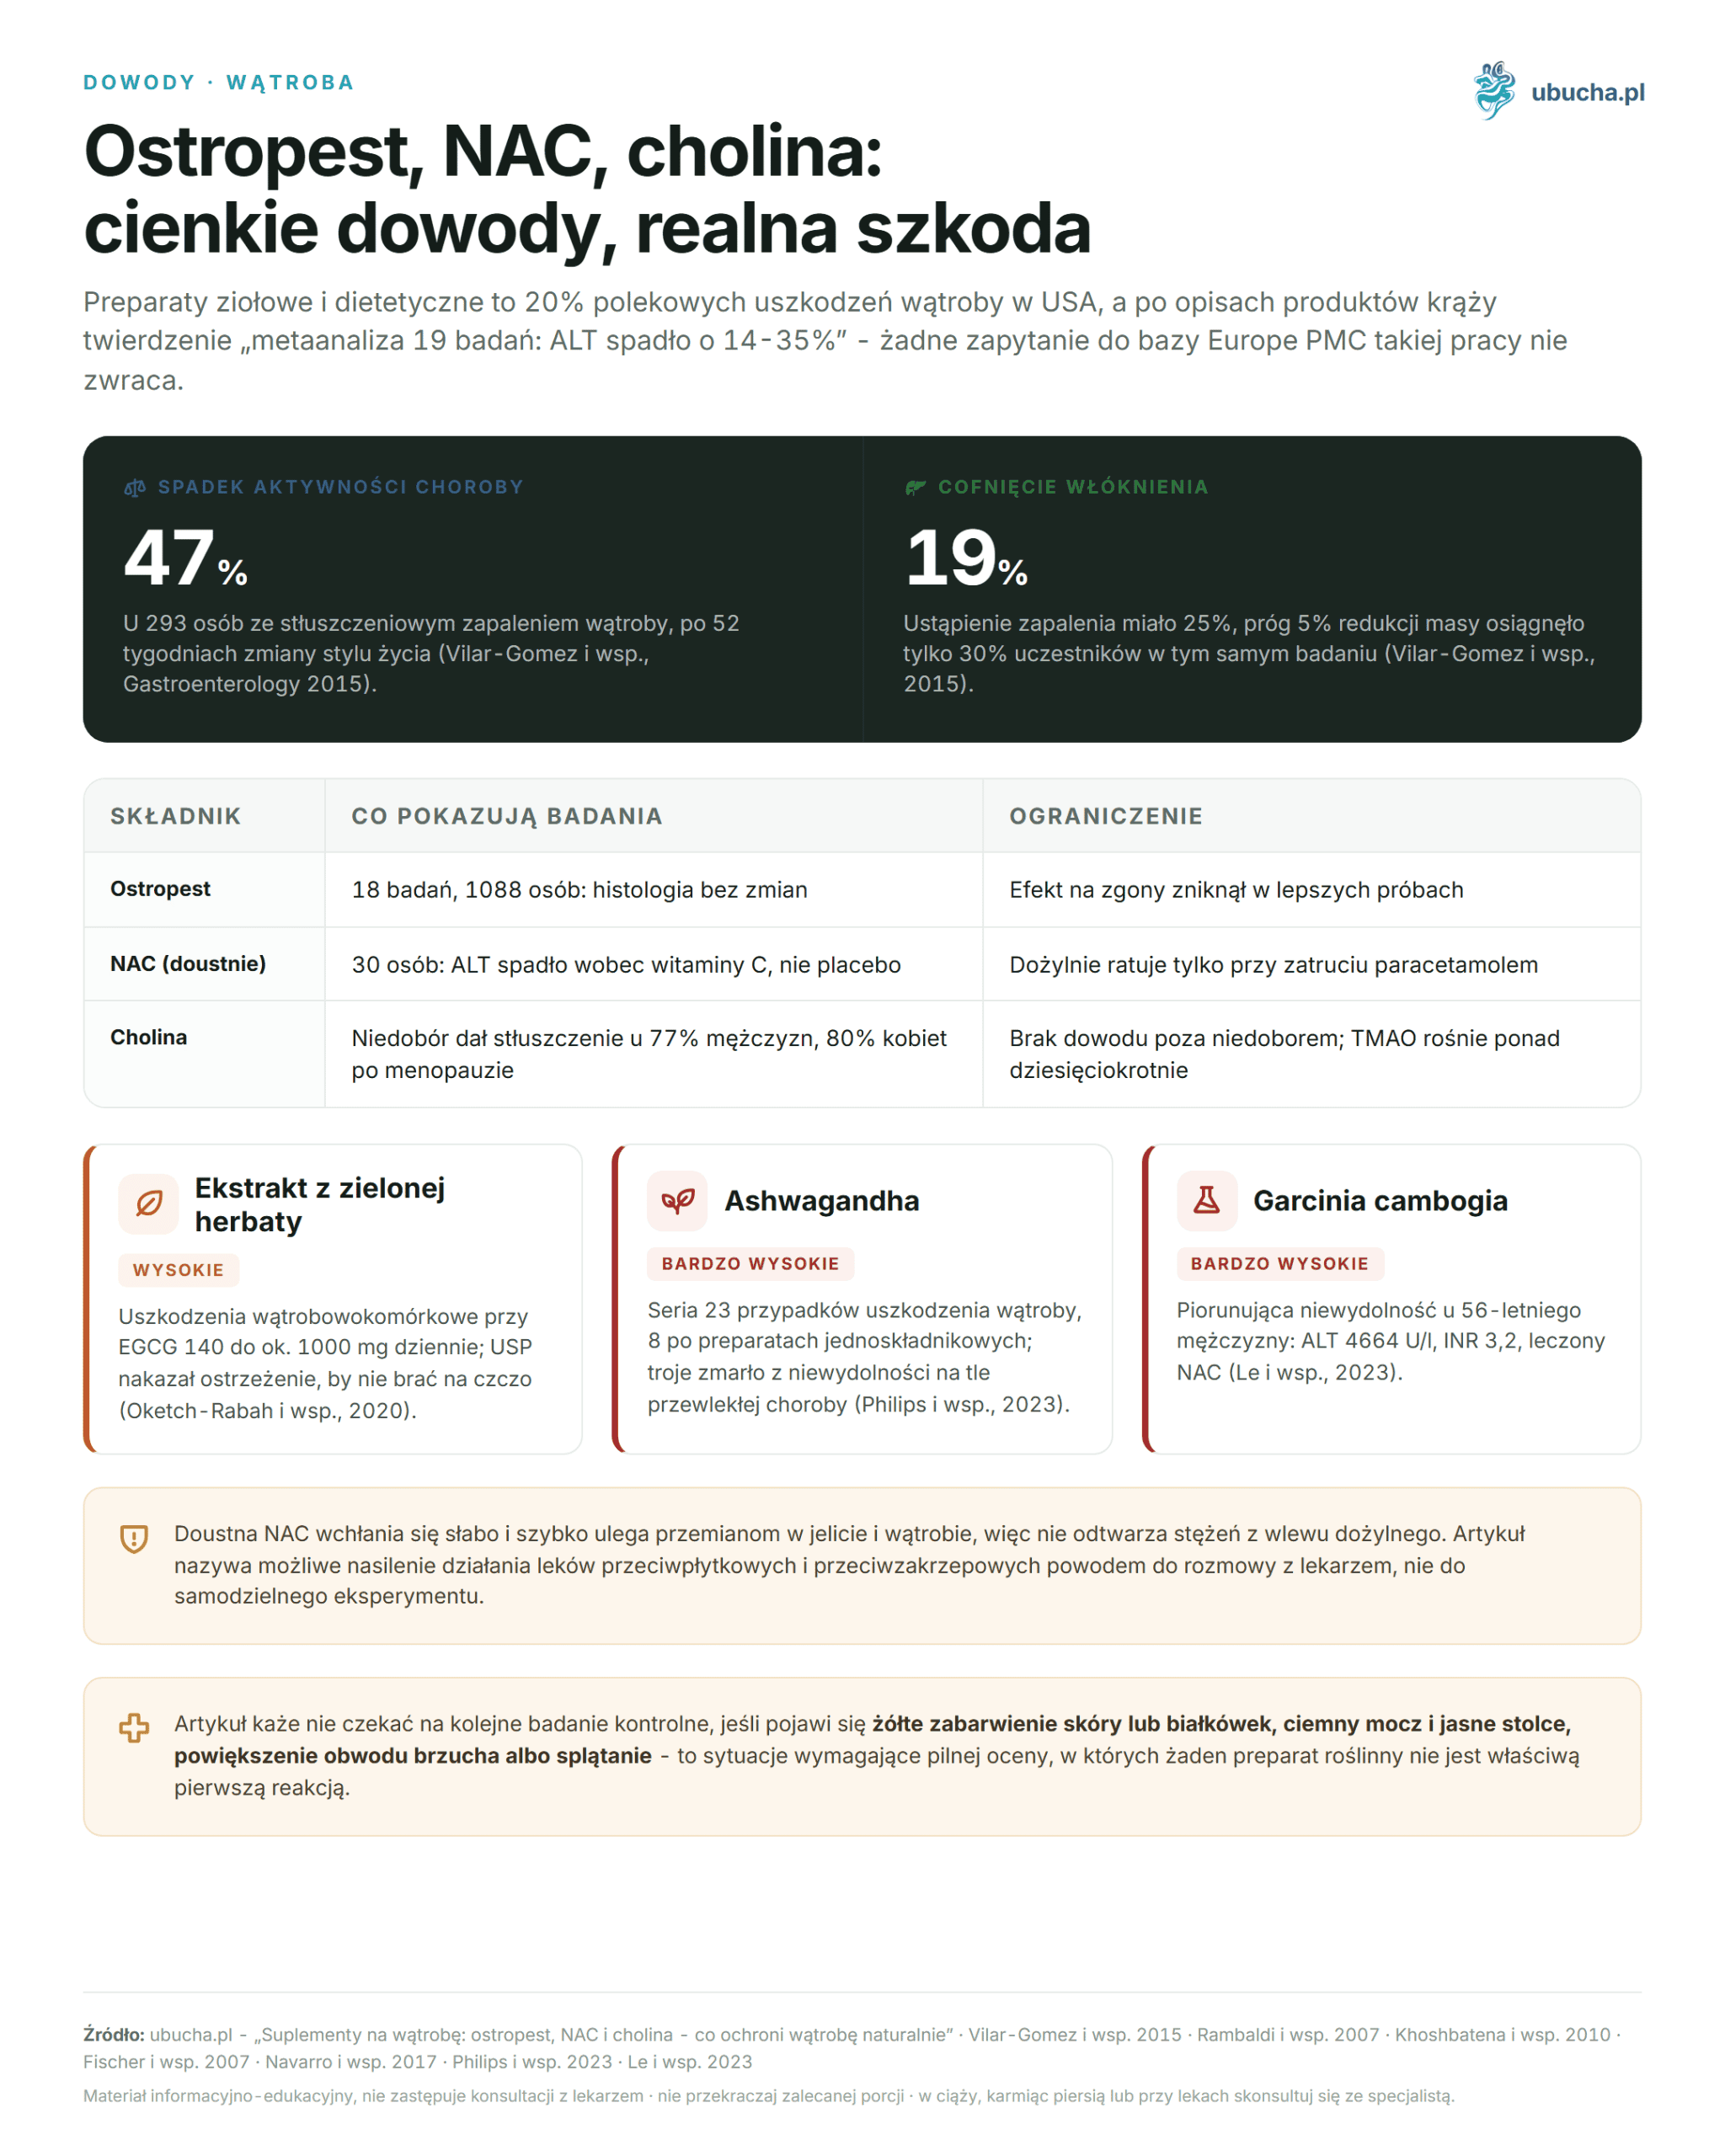
• A yearly lifestyle change in 293 people with fatty liver disease resulted in inflammation resolution in 25% and fibrosis regression in 19% (Vilar-Gomez et al., Gastroenterology, 2015).
• Cochrane review on milk thistle: 18 studies, 1088 people, no impact on overall mortality and liver histology.
• NAC saves the liver in paracetamol poisoning, but intravenously in the hospital, not as a daily capsule.
• Herbal and dietary supplements account for 20% of drug-induced liver injuries in the USA (Navarro et al., Hepatology, 2017).
What really improves the condition of fatty liver?
Weight reduction. In a one-year study of 293 people with biopsy-confirmed fatty liver disease, lifestyle change alone resulted in inflammation resolution in 25% of participants, a decrease in disease activity index in 47%, and fibrosis regression in 19% (Vilar-Gomez et al., Gastroenterology, 2015). No supplement has results of this caliber.
The effect increased with weight loss, and it was very steep. Among all who lost at least 10% of their weight, the disease activity index decreased, inflammation resolved in 90%, and fibrosis regressed in 45%. At the same time, only 30% of participants exceeded the 5% threshold, even under the care of a clinical center for a full 52 weeks. It is clear where the real difficulty lies. Not in choosing a supplement, but in maintaining the change for a year.
The second pillar is alcohol, as its metabolism burdens the liver directly and accumulates with metabolic fatty liver. The third is physical activity, which improves insulin sensitivity regardless of what the scale shows. A supplement added to an unchanged diet, eight hours of sitting, and weekend drinking has nothing to fix because the source of the problem remains untouched.
We noticed while reviewing the descriptions in this category that the order is sometimes reversed: the supplement is presented as treatment, and weight loss as an optional addition. The data align exactly the opposite way, and it is worth remembering this with every claim of “cleansing the liver.”
Does milk thistle really protect the liver?
The evidence is inconclusive, even in liver diseases. A Cochrane review included 18 randomized studies and 1088 patients with alcoholic or viral liver disease. Milk thistle did not significantly affect overall mortality (relative risk 0.78 with a confidence interval from 0.53 to 1.15), complications of the disease, or histological picture (Rambaldi et al., Cochrane, 2007).
One result from this review is often cited without the second half of the sentence. Liver-related mortality did indeed decrease significantly: relative risk 0.50. However, when the authors narrowed the analysis to high-quality methodological trials, the effect ceased to be significant. Such trials made up 28.6% of the entire collection, so this narrowing removes most of the material.
A newer meta-analysis is milder but cautious. Kalopitas and colleagues gathered eight randomized studies on non-alcoholic fatty liver and noted a greater decrease in transaminases than in placebo groups, regardless of weight change. In the same text, the authors point out the poor quality of the included works and state directly that it is unknown whether the decrease in enzymes translates to improvement in biopsy (Nutrition, 2021).
The most frequently cited interventional study also requires a footnote. Loguercio and colleagues treated 179 patients for 12 months and achieved improvements in enzymes, insulin resistance, and histological picture, but the preparation was a complex of silybin with phosphatidylcholine and vitamin E (Free Radical Biology and Medicine, 2012). The effect cannot be attributed solely to silymarin, as vitamin E has its own independent data in fatty liver. Additionally, 41 people dropped out of the study early, and the analysis was conducted on 138 who completed the protocol.
It is also worth knowing one claim that circulates in product descriptions: “a meta-analysis of 19 studies showed a reduction in ALT by 14-35%”. None of the queries we posed to the Europe PMC database returns such a work. Meta-analyses of silymarin that can be found there count in absolute values and come out much more modestly: de Avelar et al. (World Journal of Gastroenterology, 2017) summed six trials and calculated a decrease in ALT of 0.26 IU/ml, calling it clinically insignificant, while Zhong et al. (Medicine, 2017) gathered eight trials involving 587 people and reported a decrease of 9.16 IU/l. None of them provides a result in percentages.
When does NAC work on the liver, and when is it just a supplement?
NAC has one application with hard evidence: it is an antidote in paracetamol poisoning. It is administered in the hospital, usually intravenously, within hours of overdose, and replenishes glutathione stores before the toxic metabolite destroys hepatocytes. This is an emergency situation, not daily prevention.
Oral supplementation is a completely different conversation. Data on fatty liver come from small trials: a study by Khoshbatena and colleagues involved 30 people, the observation lasted three months, and the endpoints were enzyme activity and ultrasound imaging (Hepatitis Monthly, 2010). ALT activity significantly decreased after three months, but the comparison group was vitamin C, not placebo. Comparing one antioxidant to another does not tell how much of that effect would be due to mere observation. No one checked whether this changes anything in biopsy, in the risk of cirrhosis, or in survival.
For chronic use of NAC as a “liver supplement,” there are no studies with hard endpoints. There is, however, a well-known logical trap: since NAC saves in poisoning, it must protect daily. An antidote given in hospital conditions and a capsule taken for years are two different research questions, and we only have an answer to one of them. We describe this more broadly in a separate text about N-acetylcysteine and its interactions.
Oral NAC also has its own practical limitations. It is poorly absorbed and quickly undergoes transformations in the intestinal wall and in the liver, so the concentrations achieved from a capsule have nothing to do with an intravenous infusion. Additionally, it may enhance the effects of antiplatelet and anticoagulant medications, which in the case of ongoing therapy is a reason to discuss with a doctor, not to experiment independently.
Does choline protect against fatty liver?
Choline has a documented role, but on the deficiency side. Without it, the liver cannot assemble molecules that transport fat outside, so triglycerides remain in the cells. In a study involving 57 people, deprivation of choline in the diet caused fatty liver or muscle damage in 77% of men and 80% of postmenopausal women (Fischer et al., American Journal of Clinical Nutrition, 2007).
This is a strong argument for ensuring that choline is not lacking in the diet. However, it is not an argument for a capsule in a person who regularly eats eggs, fish, or meat. There are simply no studies showing that adding choline to a person without a deficiency improves liver picture. Women before menopause reacted much less frequently in the same experiment, as symptoms occurred in 44% of them, suggesting that the demand depends, among other things, on estrogen levels. It is also worth remembering the scale: the groups included 26 men, 16 premenopausal women, and 15 postmenopausal women, so the percentages for women are based on a dozen individuals. Organ disorders appeared in some men even with intake levels considered sufficient. More about the ingredient itself is discussed in the entry about choline for the liver, brain, and memory.
The densest source of choline in the daily diet is egg yolks, followed by liver and fish, and in smaller amounts legumes and cruciferous vegetables. A group that may realistically have too little are those excluding animal products without planning their diet. There, the question of supplementation makes sense and is worth asking a dietitian, rather than deciding independently based on the description on the package.
There is also a signal in the other direction. Choline is processed by gut bacteria into trimethylamine, and the liver oxidizes it to TMAO, a metabolite associated with cardiovascular risk. In eighteen healthy volunteers, two months of choline supplementation raised TMAO levels over tenfold and increased platelet aggregation in response to ADP (Zhu et al., Circulation, 2017). Both effects weakened in individuals taking aspirin. With a diet rich in choline, this effect is not observed on this scale, as the doses are incomparably smaller and spread over time.
What is known about TUDCA and is it worth taking for the liver?
TUDCA, or tauroursodeoxycholic acid, is a bile acid conjugated with taurine, studied in patients with diagnosed liver disease, not in healthy individuals seeking support. In this first group, it improved biochemical results in cirrhosis, cholestasis, and chronic hepatitis type C. This is the entire basis, and it is worth reading it literally.
Doses from clinical studies range from 500 to 1500 mg per day, divided into two or three portions, which corresponds to about 10 mg per kilogram of body weight. In a study on cirrhosis, 750 mg was administered daily for six months. Tolerance was good, and the only regularly reported adverse effect was diarrhea. However, there is no data on use longer than a year.
It should also be said what TUDCA has not shown. A phase three study in amyotrophic lateral sclerosis did not achieve the primary endpoint, and outside of liver and biliary tract diseases, there are no results that would justify preventive use of this compound. In Europe, it is used in cholestatic diseases as a drug, which is a completely different situation than a capsule bought as a supplement.
The practical conclusion does not differ from the thesis of the entire text. If you have abnormal liver results, TUDCA is not an answer to implement independently, but a reason for a visit. If your results are good, there is nothing to improve.
Can a supplement damage the liver?
Yes, and it is not uncommon. Herbal and dietary preparations account for 20% of drug-induced liver injury cases recorded in the United States. The most commonly mentioned ingredients are anabolic steroids sold as supplements and green tea extract, but most cases today fall on multi-ingredient preparations, where the culprit is usually not identifiable (Navarro et al., Hepatology, 2017).
The paradox is obvious: some products advertised as liver support end up on the list of causes of its damage. Below are three examples with described clinical cases and one example of evidence that has ceased to exist.
| Ingredient | What has been described in the literature | Source |
|---|---|---|
| Green tea extract | Hepatocellular damage with EGCG intake from 140 to about 1000 mg daily; the US pharmacopoeia mandated a warning not to take the preparation on an empty stomach | Oketch-Rabah et al., USP, 2020 |
| Ashwagandha | A series of 23 cases of liver damage, including 8 after single-ingredient preparations; three patients with failure due to chronic disease died | Philips et al., Hepatology Communications, 2023 |
| Garcinia cambogia | Acute liver failure in a 56-year-old man, ALT 4664 U/l, INR 3.2, treatment with NAC | Le et al., Cureus, 2023 |
| Artichoke | The Cochrane review cited in advertisements was retracted from the database in 2016 and concerned cholesterol, not liver diseases | Wider et al., Cochrane, 2016, retracted work |
The risk increases when the preparation has a long ingredient list, when you take several such products at once, or when you already have liver disease. In case of worsening well-being, jaundice, or dark urine, the first step is to stop all supplements and get a blood test, not to switch one preparation for another.
Which liver test results require a doctor?
The American College of Gastroenterology guidelines state that a healthy ALT norm is between 29-33 IU/l for men and 19-25 IU/l for women, and a result above these values should be evaluated (Kwo et al., 2017). Elevated ALT is associated in many studies with higher mortality from liver-related causes, so it is not a cosmetic deviation.
The same guidelines organize diagnostics. With ALT and AST predominating over alkaline phosphatase, viral hepatitis types A, B, and C are sought, alcohol consumption and metabolic fatty liver are assessed, and hemochromatosis, autoimmune hepatitis, Wilson’s disease, and alpha-1-antitrypsin deficiency are excluded. A separate point is the history of all medications taken, including over-the-counter ones, and supplements.
Do not wait for the next follow-up test if yellowing of the skin or sclera, dark urine and light stools, abdominal distension, or confusion occurs. These are situations requiring urgent evaluation, in which no herbal preparation is the proper first response. A supplement will not replace determining the cause: with elevated enzymes, diagnostics make sense, not automatically reaching for milk thistle.
In the case of a slight, asymptomatic elevation of ALT, the doctor usually repeats the measurement after a few weeks, as a single result can rise after intense training, after an infection, or after a new medication. Only a persistent deviation triggers broader diagnostics. It is worth coming to this visit with a list of everything you take, including herbs and preparations bought without a prescription, as without it, the medical history simply does not close.
The set you ask about most often is broken down separately in the text about milk thistle, artichoke, and NAC.
What besides supplements really affects the liver?
Alcohol, caloric intake, and exercise, in that order. Additionally, coffee, which surprisingly performs well in observational data: in a meta-analysis of nine studies involving 432,133 people, every additional two cups daily were associated with a cirrhosis risk of 0.56 compared to the group drinking less (Kennedy et al., Alimentary Pharmacology and Therapeutics, 2016).
These are observational data, so they do not prove causality, but they are consistent across many populations and are hard to explain solely by the lifestyle of coffee drinkers. In practice, this means that regular black coffee has stronger evidence backing than most products sold under the liver support label.
A separate thread is the gut. A meta-analysis of 21 randomized studies involving 1252 people with fatty liver showed that probiotics and synbiotics lower ALT activity (Sharpton et al., American Journal of Clinical Nutrition, 2019). Here too, the endpoint was the enzyme, not the liver picture after years. The same situation applies to curcumin. A meta-analysis of 14 randomized studies in people with fatty liver reports a decrease in ALT of 8.72 IU/l and AST of 6.35 IU/l, but with a spread of results reaching 94% (Ebrahimzadeh et al., Food Science and Nutrition, 2025). Here too, the enzyme was measured, not the liver picture. More about the spice itself and its absorption is discussed in the text about turmeric and curcumin.
How to approach liver supplementation sensibly?
Start with diagnosis, not with the shopping cart. A sensible order looks like this: blood test, determining the cause of deviation with a doctor, working on body weight, alcohol, and exercise, and only at the end possibly a supplement as an addition that the doctor knows about. The reverse order costs time in which the disease progresses asymptomatically.
When choosing a supplement, several control questions help. Does the manufacturer refer to a study that can be found by name and year? Is the ingredient list short, because with multi-ingredient preparations, it is impossible to identify the culprit in case of complications? Does the attending physician know about everything you take, including herbs? We also checked the store’s offer in this regard: there is no milk thistle, N-acetylcysteine, choline, or artichoke in it, so this text has nothing to sell.
Under the liver support label, you will most often find omega-3 acids and turmeric with piperine. These are sensible products in their own indications, but they are not liver medications and will not replace weight reduction or alcohol limitation. If you are looking for them for another reason, we describe them in the text about omega-3 acids.
Frequently Asked Questions
Does milk thistle really protect the liver?
The evidence is inconclusive. A Cochrane review included 18 studies and 1088 people with alcoholic or viral liver disease and found no impact on overall mortality, complications, or histology. The reduction in liver-related mortality disappeared when narrowing to high-quality trials. A 2021 meta-analysis found a decrease in transaminases in fatty liver, but its authors themselves warn about the quality of the included studies.
Does NAC in capsules work the same as NAC in the hospital?
No. Intravenous NAC is an established antidote in paracetamol poisoning and saves the liver from necrosis. Oral supplementation is based on small trials, such as a 30-person study by Khoshbatena et al. from 2010. ALT significantly decreased after three months, but the comparison group was vitamin C, not placebo, and no one assessed biopsies.
Will choline help if I don’t have a deficiency?
There is no good data for that. The opposite effect is documented: deprivation of choline caused fatty liver or muscle damage in 77% of men and 80% of postmenopausal women, with groups numbering a dozen to twenty-some people (Fischer et al., 2007). Supplementation raises TMAO levels over tenfold and increases platelet aggregation (Zhu et al., Circulation, 2017).
Does artichoke support the liver?
Artichoke is sometimes advertised citing a Cochrane review, but that work was retracted from the database in 2016 and is no longer evidence for anything. It actually concerned cholesterol, not liver diseases. Referencing it in the product description should be treated as a warning signal regarding the rest of the claims.
How much weight do you need to lose to reverse fatty liver?
In the study by Vilar-Gomez et al. from 2015, among those who lost at least 10% of their weight within a year, inflammation resolved in 90%, and fibrosis regressed in 45%. However, only 30% of participants reached the 5% threshold, despite clinical center care for 52 weeks.
What tests should you do before reaching for a liver supplement?
The basics are ALT, AST, alkaline phosphatase, and bilirubin. According to the American College of Gastroenterology guidelines, a healthy ALT norm is 29-33 IU/l for men and 19-25 IU/l for women, and a result above that requires evaluation. Diagnostics include viral hepatitis, alcohol, and a review of medications and supplements.
If you are looking for specific preparations after talking to a doctor, the full offer is in the supplements section.
This article is for informational and educational purposes and does not constitute medical advice. Before starting supplementation, consult a doctor, especially if you are taking medications regularly, are pregnant or breastfeeding, or have chronic illnesses.
Author: Michał Waluk · Published: 2026-05-29 · Updated: 2026-08-24