
Intermittent Fasting and Supplements: What Can Be Taken on an Empty Stomach (Table)
Which supplements have been studied on an empty stomach during intermittent fasting, and which recommendations are based only on mechanisms. A table with sources and a list of at-risk groups.
Intermittent fasting, described in the review by Vasim et al. (Nutrients, 2022), is a way of eating where all-day food intake is confined to a designated window of the day. The question that often arises with it is: what can be swallowed during the fasting window without ruining it. The answers circulating online are definitive, but most lack any measurement in humans, relying instead on reasoning about insulin and autophagy. This text separates these two layers. For each row in the table, we indicate whether there is a study with a specified population and result or just the mechanism. At the end, we list individuals for whom fasting may be contraindicated.
KEY INFORMATION
• We did not find a study in humans that would set a caloric threshold that breaks fasting. Thresholds like 50 kcal are a convention from guides, not a result of measurement.
• Autophagy in humans is rarely measured and indirectly. A pilot randomized study of 30 individuals noted a change in its index after a fasting-mimicking diet, though not at every measurement point (Espinoza et al., GeroScience, 2025); the sponsor was the producer of this diet.
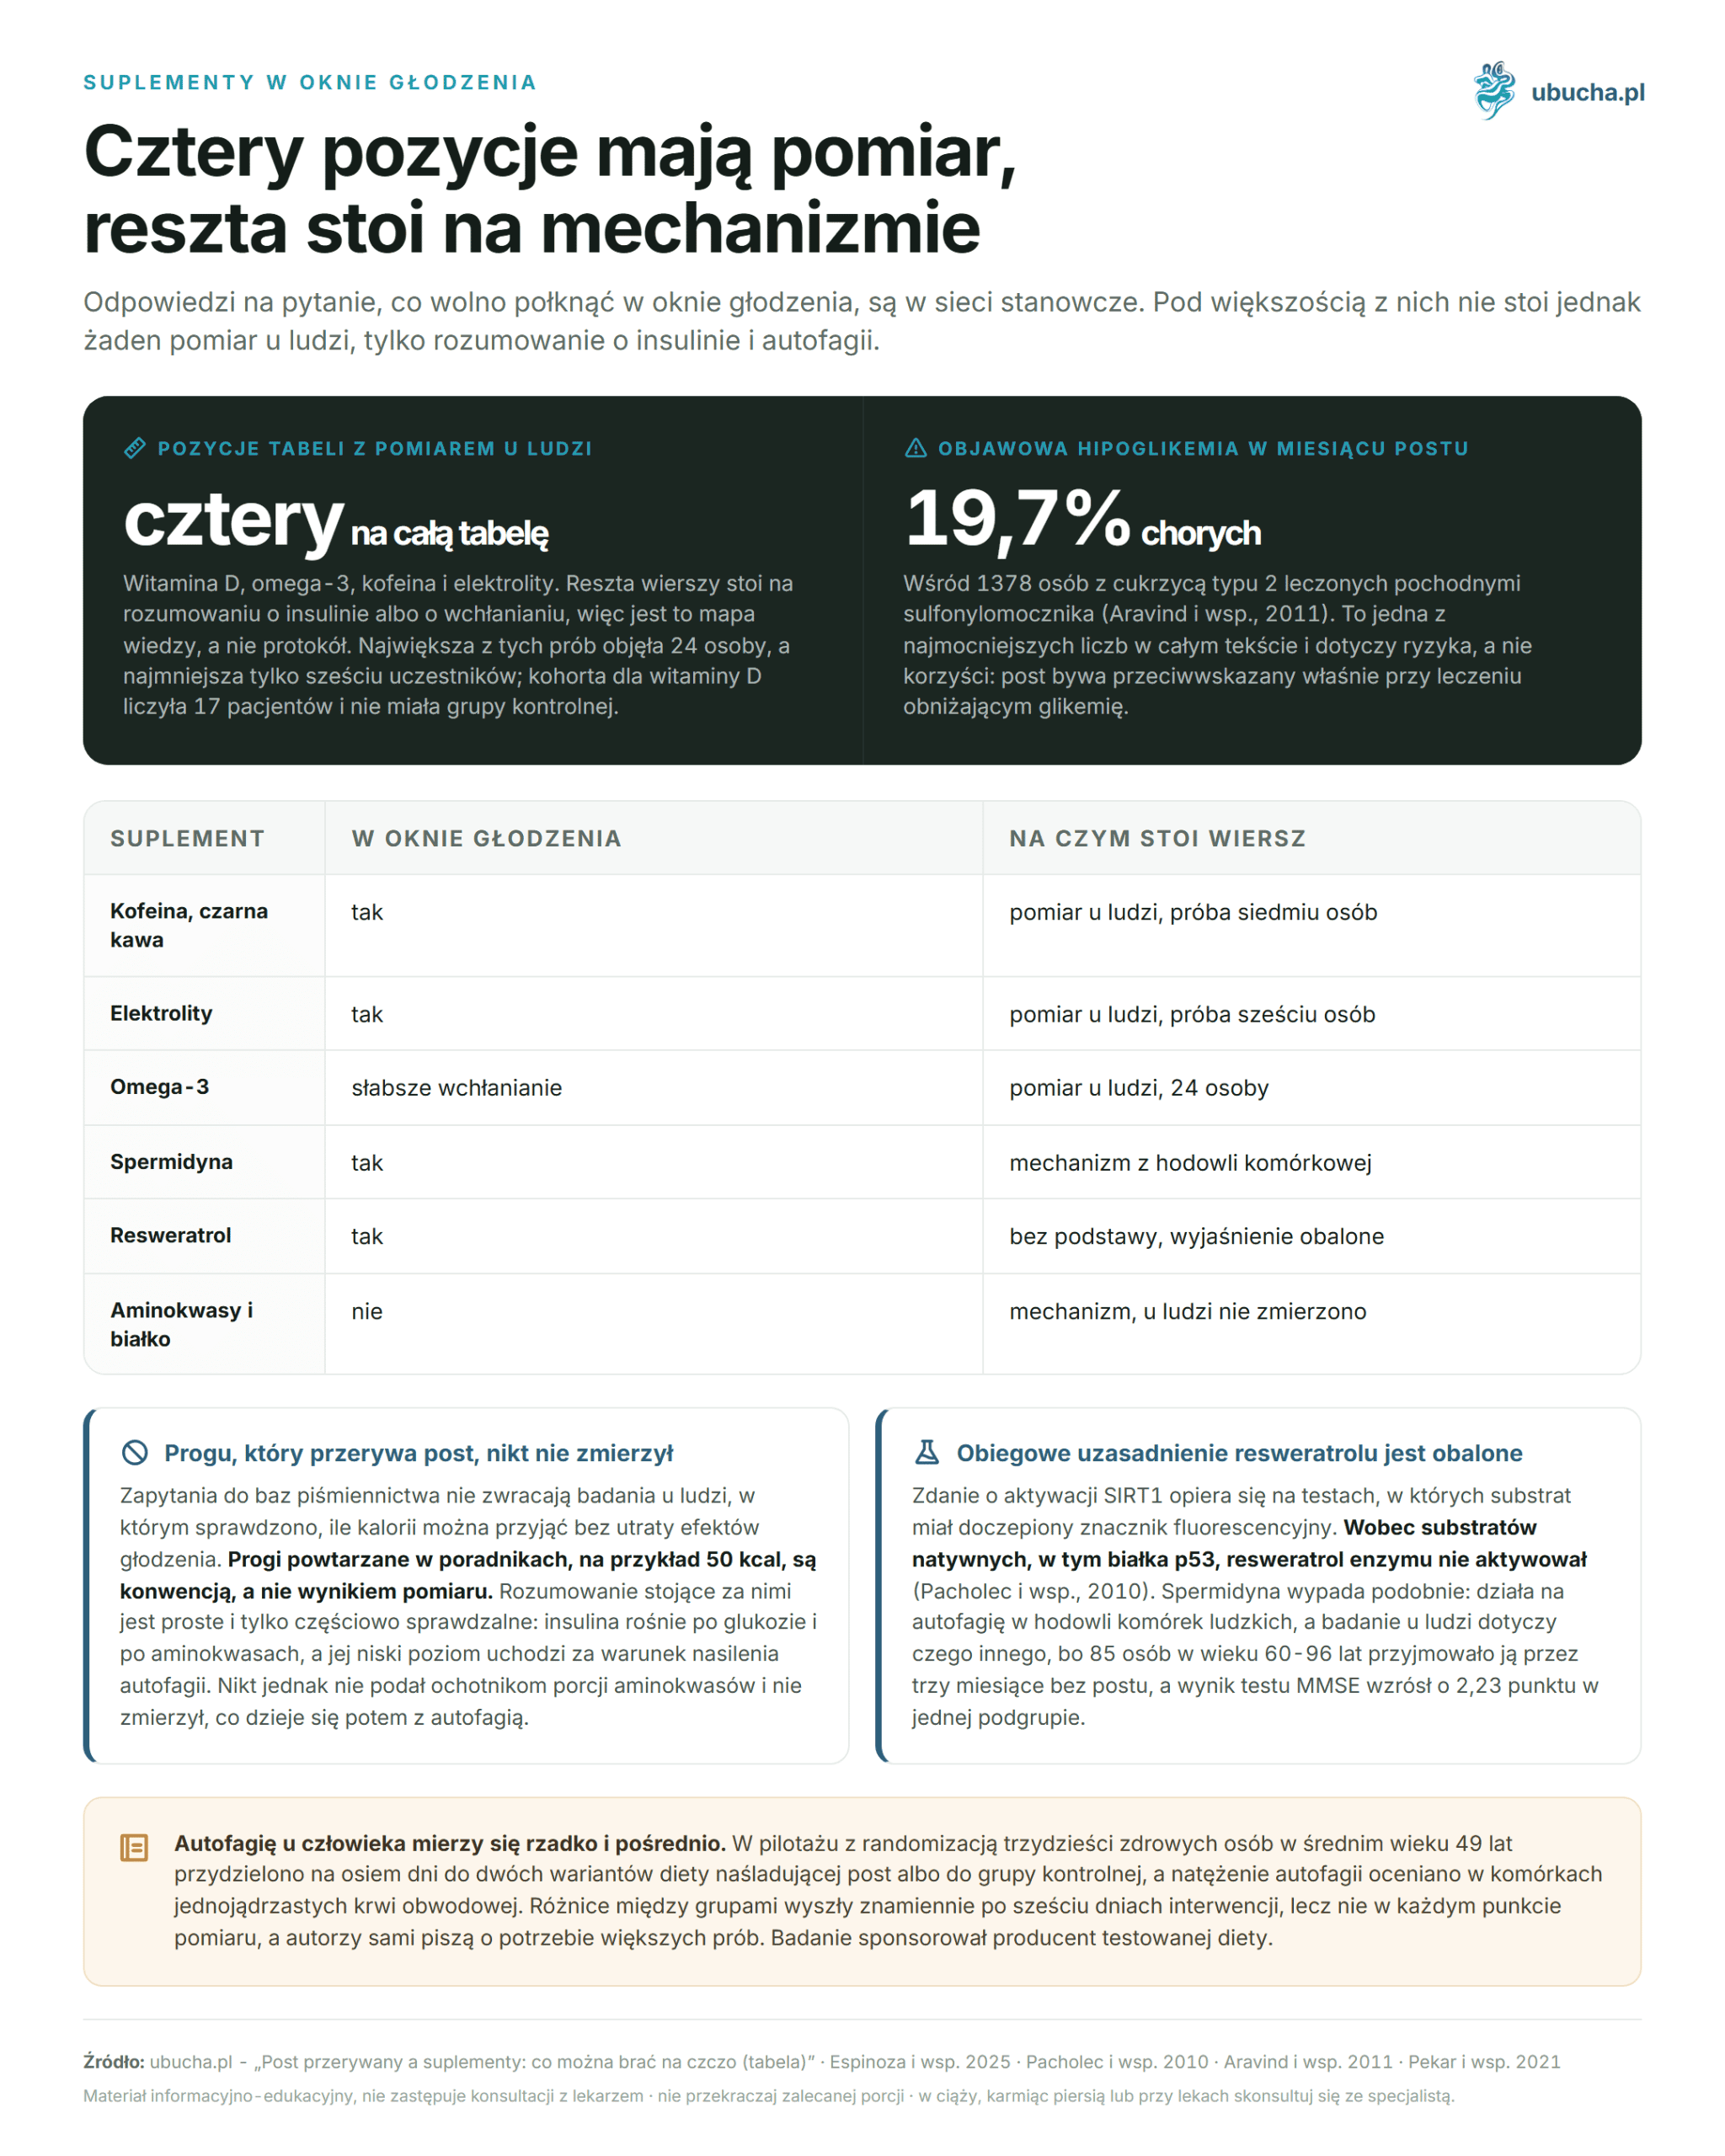
• The table includes four positions with measurements in humans: vitamin D, omega-3, caffeine, and electrolytes. The rest is based on mechanisms.
• The common justification for resveratrol is false: it does not directly activate SIRT1 against native substrates (Pacholec et al., J Biol Chem, 2010).
• Among 1378 individuals with type 2 diabetes treated with sulfonylurea derivatives, 19.7% reported symptomatic hypoglycemia during a month of fasting (Aravind et al., Curr Med Res Opin, 2011).
What Really Breaks Intermittent Fasting?
It is unknown because no one has measured the boundary. Queries to Europe PMC do not return studies in humans that checked how many calories can be consumed without losing the effects of fasting. Thresholds repeated in guides, such as 50 kcal, are conventions, not results of measurement.
The reasoning behind these thresholds is simple and only partially verifiable. Insulin rises after glucose and amino acids, and its low level is considered a condition for enhancing autophagy. Hence the conclusion that a supplement without calories and amino acids does not ruin fasting. This is a mechanism, not a result of research: no one has given volunteers a portion of amino acids and measured what happens to autophagy afterward.
Autophagy in humans is difficult to measure, and most claims about it come from yeast, cell cultures, and rodents. There is a measurement in humans, but it is weak. In a pilot randomized study, thirty healthy individuals with an average age of 49 were assigned for eight days to two variants of a fasting-mimicking diet or to a control group, and the intensity of autophagy was assessed in peripheral blood mononuclear cells. Differences between groups were significant after six days of intervention, but not at every measurement point, and the authors themselves note the need for larger trials (Espinoza et al., GeroScience, 2025). The study was sponsored by the producer of the tested diet.
Which Supplements Have Been Studied on an Empty Stomach, and Which Have Not?
Few have been studied. The table separates rows into those with human studies and those based solely on reasoning about insulin or absorption. The second group is larger, so this is a map of knowledge, not a protocol.
The layout corresponds to the 16:8 protocol with a food window from 12:00 to 20:00. We discuss the timing of collagen intake in the text Collagen at Night or in the Morning.
| Supplement | In the fasting window? | In the eating window? | What supports this row |
|---|---|---|---|
| Magnesium | Yes | Yes | Mechanism: without calories and amino acids; we found no comparisons with meals |
| Vitamin C | Yes | Yes | Mechanism: water-soluble |
| B Vitamins | Yes | Yes | Mechanism: water-soluble |
| Spermidine | Yes | Yes | Mechanism from cell culture, not measurement in fasting individuals |
| Resveratrol | Yes | Yes | No basis: explanation via SIRT1 debunked (J Biol Chem, 2010) |
| Caffeine (black coffee) | Yes | Yes | Measurement in humans, trial of seven individuals (J Nutr Metab, 2021) |
| Electrolytes (sodium, potassium) | Yes | Yes | Measurement in humans, trial of six individuals (J Clin Invest, 1975) |
| Vitamin D | Technically yes | Yes, better | Measurement in humans, cohort of 17 patients without control (J Bone Miner Res, 2010) |
| Vitamin K2 | Technically yes | Yes, better | Mechanism: lipophilic. The work on vitamin D does not cover it |
| Omega-3 (EPA, DHA) | Weaker absorption | Yes, better | Measurement in humans, 24 individuals (J Clin Lipidol, 2017) |
| Vitamins A and E | No data | Yes, better | Mechanism: lipophilic. Warnings about accumulation were not substantiated |
| BCAA Amino Acids | No | Yes | Mechanism: amino acids stimulate insulin and mTOR; the effect on autophagy in humans has not been measured |
| Collagen and whey protein | No | Yes | Mechanism: it is protein |
| Probiotics | Technically yes | Yes, better | Measurement in a digestion model, not in humans (Benef Microbes, 2011) |
Does Any Supplement Enhance the Effects of Fasting?
None have a study in fasting humans to support this. Three substances mentioned in this role have varying levels of evidence, but none come from a study involving fasting.
Spermidine acts on autophagy in human cell cultures: it inhibits acetyltransferase EP300, and autophagy markers increase. The inhibition of this enzyme was also confirmed on purified protein, in vitro (Pietrocola et al., Cell Death Differ, 2015). There is also a study in humans, but about something else: 85 individuals aged 60-96 from six nursing homes took spermidine for three months in a double-blind setup, and in the subgroup with mild dementia and higher intake, the MMSE test score increased by 2.23 points (Pekar et al., Wien Klin Wochenschr, 2021). Fasting was not part of this study.
Resveratrol is listed in the table with a note because the common justification turned out to be false. The statement about activating SIRT1 is based on tests where the substrate had a fluorescent marker attached. Against native substrates, including protein p53, resveratrol did not activate the enzyme (Pacholec et al., J Biol Chem, 2010).
Caffeine has the measurement closest to the topic. In a controlled double-blind study, seven healthy volunteers drank decaffeinated coffee with MCT oil or coconut oil, with caffeine or without. Caffeine raised the concentration of beta-hydroxybutyrate, most strongly in combination with tricaprylin (Baumeister et al., J Nutr Metab, 2021). Seven individuals is a trial from which no rules can be derived.
Why Are Lipophilic Vitamins Absorbed Better with Meals?
Because they require micelles for absorption, which are formed from dietary fat and bile acids. However, measurement in humans in this group has only been done for vitamin D, and it is weaker than the popularity of the recommendation suggests.
Seventeen patients with vitamin D deficiency, for whom treatment was ineffective, were asked to move the supplement to the largest meal of the day. After two or three months, the concentration of 25-hydroxyvitamin D increased by an average of 56.7% (Mulligan and Licata, J Bone Miner Res, 2010). This is a cohort without a control group, not a randomized study, so part of the change may have resulted from the passage of time or better adherence to recommendations.
This work should not be extended to other lipophilic vitamins. Vitamins A, D, E, and K are four different molecules with different kinetics, and only vitamin D derivatives were studied. For vitamins K2, A, and E, we found no comparisons on an empty stomach versus with meals in humans. What is known about combining vitamin D3 with K2, and what is a myth in this regard, is discussed in the text Vitamin K2 MK-7.
Omega-3 fatty acids have their own measurement. In a crossover study of 24 healthy individuals, the same preparation was given on an empty stomach, after a low-fat meal, and after a fatty meal. For EPA, the area under the curve of concentration was clearly higher after the fatty meal than on an empty stomach; for DHA, no difference was found (Lopez-Toledano et al., J Clin Lipidol, 2017). The result pertains to one form of ethyl esters, so it is a guideline, not a rule for any fish oil.
How Does Intermittent Fasting Change the Gut Microbiome?
It remodels it during the duration and reverts the change after completion. This was measured in individuals who fasted during the day and ate after dark for a month of Ramadan, thus in a setup similar to intermittent fasting.
Researchers collected stool and blood from two groups in two different years and assessed the composition of the microbiota through 16S sequencing. The proportion of the Lachnospiraceae family increased from 24.6% to 39.7%, and the Ruminococcaceae family from 13.4% to 23.2%. After the fasting ended, the composition returned to baseline (Su et al., Am J Clin Nutr, 2021). The authors link the result to the production of butyric acid by Lachnospiraceae, but they do not mention inflammatory status in the abstract, so such a conclusion should not be drawn from this work. We discuss how gut bacteria relate to mood in the text Psychobiotic.
For probiotics themselves, the basis is weaker. The survival of strains was checked in a model of the upper gastrointestinal tract, that is, in apparatus, not in humans. Bacteria survived best with a meal or half an hour before it, worst half an hour after it, and the fat content was more significant than protein (Tompkins et al., Benef Microbes, 2011). The study was conducted by authors associated with the company selling the tested preparation. Prebiotics, such as inulin, are not covered by this work.
Do Different Fasting Protocols Require Different Supplementation?
It is unknown because no one has compared this. We did not find a study that compared the need for supplements with the 16:8, 18:6, OMAD, or 5:2 schemes. Every statement comparing protocols in this regard is a conclusion from physiology, not a result of measurement.
The physiology in question pertains to sodium. An insulin infusion in six healthy individuals reduced sodium excretion in urine from 401 to 213 microequivalents per minute, with unchanged glomerular filtration and unchanged aldosterone concentration; potassium excretion dropped even more (DeFronzo et al., J Clin Invest, 1975). When insulin drops, this brake releases. Hence the belief that with prolonged fasting, the need for electrolytes increases, but we found no measurement in fasting individuals.
Creatine shows why the mechanism alone is insufficient. The uptake of creatine into muscles indeed depends on insulin, but in a study with euglycemic clamps in seven men, the creatine content in muscle only increased at physiologically high or supraphysiological insulin levels (Steenge et al., Am J Physiol, 1998). A regular meal does not provide such levels, so the advice to take creatine with food is less substantiated than it is presented.
Who Is Intermittent Fasting Not Recommended For?
Individuals treated with insulin or sulfonylurea derivatives, pregnant and breastfeeding women, individuals with underweight or a history of eating disorders, and children and adolescents in developmental age. This list is not a precaution: measurements exist for two positions.
In an observation conducted in five countries, 1378 individuals with type 2 diabetes treated with glibenclamide, glimepiride, or gliclazide filled out diaries throughout a month of Ramadan fasting. Symptomatic hypoglycemia was reported by 19.7% of participants, and severe hypoglycemia, requiring assistance from another person, by 6.7% (Aravind et al., Curr Med Res Opin, 2011). This is an observational study without randomization, but the scale is sufficient to avoid starting fasting without consulting a doctor about what to do with medication.
The second position pertains to eating disorders. In a nationwide survey of 2762 adolescents and young adults in Canada, the use of intermittent fasting was associated with an increase in eating psychopathology across all gender groups studied, and with behaviors related to eating disorders most consistently in women (Ganson et al., Eat Behav, 2022). The cross-sectional study does not determine the direction of the relationship: it is unclear whether fasting induces such symptoms or attracts them.
For pregnancy, breastfeeding, underweight, and developmental age, there is no measurement in this role. These are states of increased energy demand, where extending breaks in eating requires a doctor’s decision, not a table from the internet.
Frequently Asked Questions
Can magnesium be taken on an empty stomach during intermittent fasting?
We did not find a study measuring this. The reasoning is as follows: magnesium in powder or capsule form without fillers does not contribute calories or amino acids, so it does not stimulate insulin. Sugar tablets are a different case. This is a mechanism, not a measurement.
Does vitamin D break intermittent fasting?
It contributes negligibly to calories; absorption is more important. In a cohort of 17 patients without a control group, moving the supplement to the largest meal of the day increased the concentration of 25-hydroxyvitamin D by an average of 56.7% (Mulligan and Licata, J Bone Miner Res, 2010). This result pertains only to vitamin D, not the entire lipophilic group.
Does spermidine or resveratrol enhance fasting?
This has not been measured in fasting individuals. Spermidine enhances autophagy in human cell cultures by inhibiting acetyltransferase EP300, and resveratrol does not directly activate SIRT1 against native substrates, contrary to the most commonly repeated explanation (Pacholec et al., J Biol Chem, 2010).
How many calories break intermittent fasting?
There is no measurement that sets such a boundary in humans. Thresholds like 50 kcal circulate in guides as a convention, not as a result of research. In a strict sense, every calorie ends a fasting state, but what that changes for autophagy remains unmeasured.
Who might be harmed by intermittent fasting?
Individuals treated with insulin or sulfonylurea derivatives are at risk of hypoglycemia: in an observation of 1378 patients with type 2 diabetes, 19.7% reported it (Aravind et al., Curr Med Res Opin, 2011). Caution is also required for pregnancy, breastfeeding, underweight, developmental age, and a history of eating disorders. Make the decision with your doctor.
Supplements available in the store at Bucha are gathered in the category Supplements.
This article is for informational and educational purposes and does not constitute medical advice. Before starting supplementation, consult your doctor, especially if you are taking medications regularly, are pregnant or breastfeeding, or have a chronic illness.
Author: Michał Waluk · Published: 2026-07-15 · Updated: 2026-08-16