CBD Oil: Reviews and Effectiveness - What Research Says

CBD oil in user opinions and scientific survey data: why people use it, how long they wait for effects, and what EFSA says about a safe dose.
Opinions in this text come from two surveys, with 2409 and 387 participants respectively, not from forum threads, and this difference is shown below in the numbers. The phrase “CBD oil opinions” is now searched more often than the name of any single manufacturer. The problem is that most circulating numbers come from sales materials, not research. Percentages like “78% of customers choose” or “62% report improvement” look like data but upon checking lead to the journal’s homepage or nowhere. We decided to verify how many of these opinions can be confirmed in scientific publications and cut out everything that cannot be confirmed. Three large datasets on cannabidiol users remain, one pharmacokinetic review, and one fresh EFSA opinion. This guide shows what they mean for someone considering their first bottle, where knowledge ends, and marketing begins.
KEY INFORMATION
• In a survey of 2409 people, 62% used CBD due to a specific ailment, most often pain, anxiety, and depression (Corroon and Phillips, Cannabis and Cannabinoid Research, 2018).
• EFSA derived in 2026 a provisional safe dose of 0.0275 mg per kilogram of body weight per day, about 2 mg for a 70 kg person.
• Absolute bioavailability of CBD was measured in humans only after smoking and was 31%; no one measured it for oral or sublingual routes.
• The 0.3% THC threshold in Polish law is calculated as the sum of delta-9-THC and THCA, not delta-9-THC alone.
What is CBD oil and how did it become popular?
CBD oil is an extract from industrial hemp Cannabis sativa L. dissolved in a carrier oil, most often MCT, hemp, or olive oil. The leading substance is cannabidiol, a non-intoxicating compound. Its popularity comes from a simple combination: the product does not intoxicate but has behind it the registration of a drug for a serious neurological indication.
In June 2018, the US FDA approved Epidiolex, the first cannabidiol-based drug, for treating rare and severe forms of epilepsy (VanDolah et al., Mayo Clinic Proceedings, 2019). This event moved CBD from a curiosity category to a substance worth investigating. The rest of the market followed this signal much faster than regulations could keep up.
Why does CBD not cause intoxication? Because it does not stimulate the CB1 receptor like THC does. Laprairie et al. showed in cells with the CB1 receptor that cannabidiol acts as a non-competitive negative allosteric modulator: it reduces the efficacy and potency of CB1 agonists instead of activating the receptor itself (British Journal of Pharmacology, 2015). This explains the profile where the effect is perceived as subtle, not intoxicating.
This subtlety is also the source of half the negative opinions. A person expecting an effect comparable to a sleeping pill will consider the product ineffective after the first evening. A person who waits a month and records observations will evaluate it very differently. The difference lies in expectations, not the bottle.
What do CBD oil users say in large surveys?
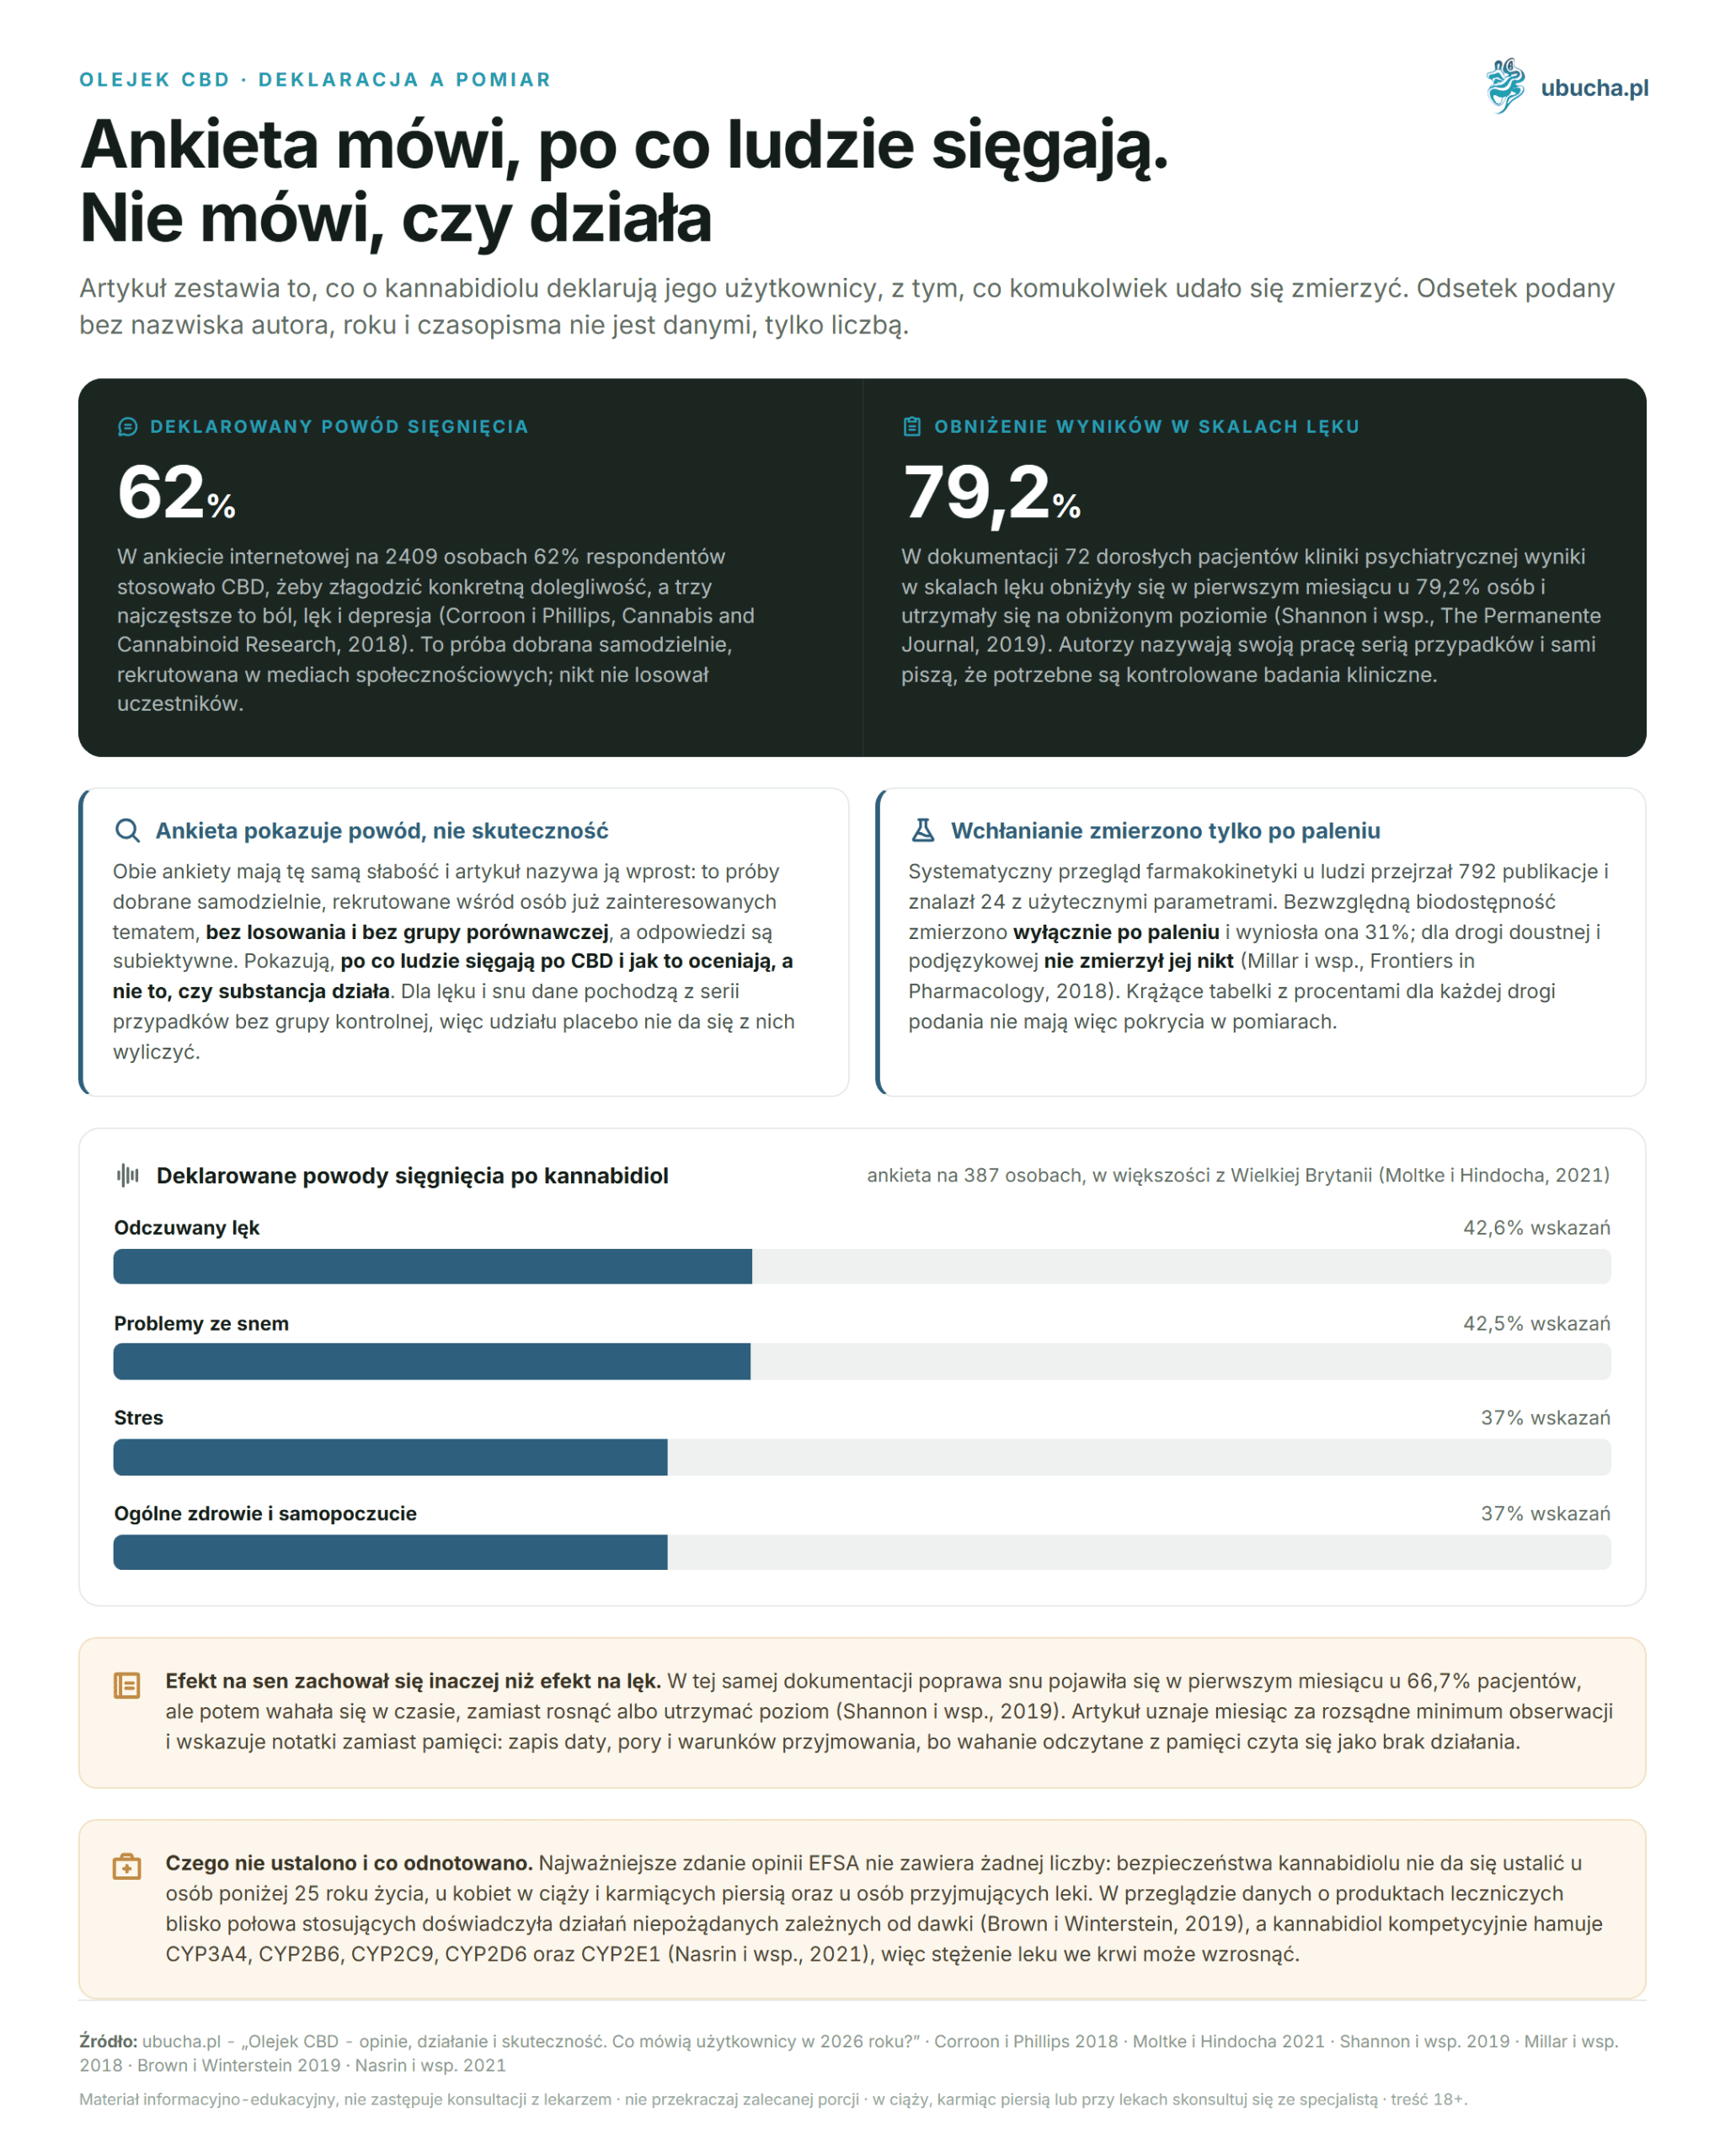
The largest published set of opinions comes from an online survey of 2409 people. Almost 62% of respondents used CBD to relieve a specific ailment, with the three most common being pain, anxiety, and depression. Nearly 36% rated CBD’s effect as “very good,” while only 4.3% chose “not very good” (Corroon and Phillips, Cannabis and Cannabinoid Research, 2018).
A second survey, conducted on 387 mostly UK participants, shows a very similar picture of reasons. The four most common reasons for cannabidiol use were anxiety (42.6%), sleep problems (42.5%), stress (37%), and general health and well-being (37%). The authors also noted how low the actual doses were: 54% took less than 50 mg daily, and 72.6% used the sublingual route (Moltke and Hindocha, Journal of Cannabis Research, 2021).
One observation from the first survey goes beyond the list of ailments and says something about the buyer profile. The chance that someone uses CBD for medicinal purposes was 1.44 times higher among non-regular cannabis users than among regular users (95% confidence interval: 1.16 to 1.79). In other words, cannabidiol is more often used by people who have nothing to do with cannabis daily. This is the opposite of the image suggested by most marketing communication in this category.
Both surveys share the same weakness and it must be named directly. These are self-selected samples recruited via social media among people already interested in the topic. No one randomized participants, no control group was monitored, and responses are subjective. They show why people use CBD and how they rate it, not whether the substance works.
It is worth comparing them with one clinical measurement to see the scale of difference between declaration and measurement. We return to this in the section on time to effect.
How do forum opinions differ from survey results?
By the selection of people who speak. On forums, those who have a reason write: very good or very bad experience. In surveys, the entire sample answers, including people for whom nothing happened, and this group often disappears from threads, although it may be the largest.
The effect is predictable and visible in numbers. Threads give extremes and individual stories, surveys give percentages with denominators. Therefore, a description like “everyone says it works” is not a result but a picture of who was motivated to write.
The second difference concerns what no one controls on forums: dose, concentration, duration of use, and whether the product even contained the declared amount of cannabidiol. Surveys do not measure this perfectly either but at least ask everyone the same way.
A practical conclusion: read forum threads as conversations, not data, and look for product descriptions and batch certificates, not ratings on a scale from one to ten.
How is CBD oil made and what does the certificate of analysis reveal?
The path from field to bottle has four stages, each leaving a trace in the final composition. The first is selecting a variety from the EU industrial hemp register and soil control, as hemp is a bioaccumulator and absorbs heavy metals along with nutrients.
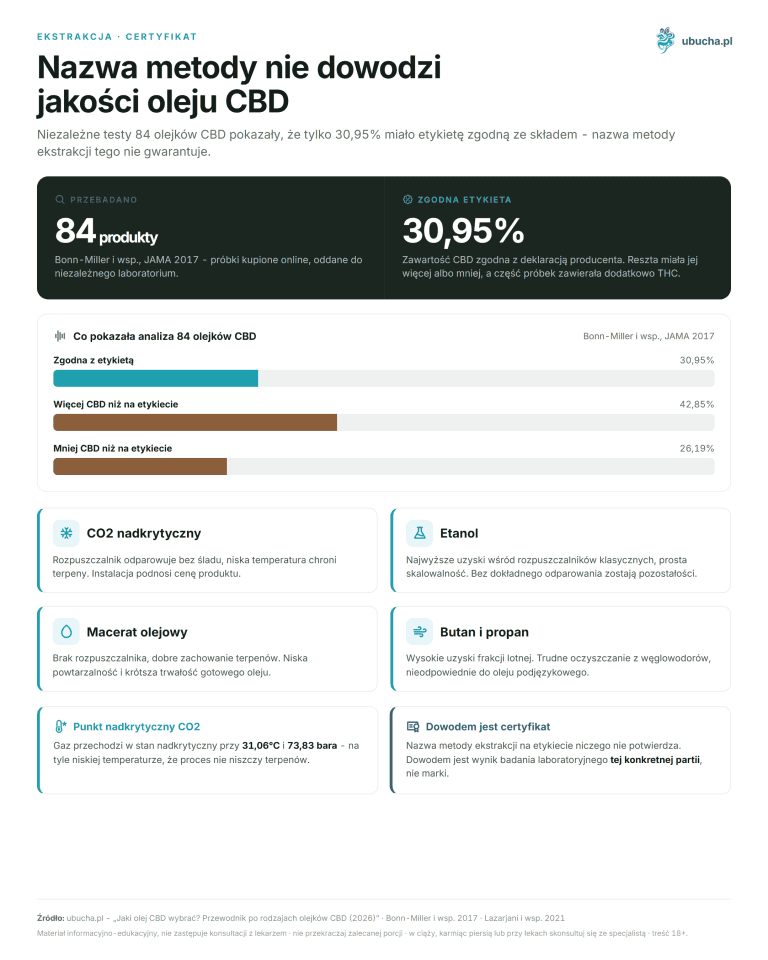
The second stage is extraction. The standard is supercritical carbon dioxide extraction because it leaves no solvent residues. A cheaper ethanol alternative requires careful evaporation, and any shortcomings at this step show up in solvent residue testing.
The third stage is decarboxylation. In the living plant, cannabinoids occur in acidic forms, as CBDA and THCA. Only heating removes the carboxyl group and produces the form known from labels. A producer who intentionally retains some cannabinoids in acidic form obtains a product with a different profile; the difference between both versions is discussed in detail in the post about RAW and decarboxylated oils.
The fourth stage is formulation and batch testing. A certificate of analysis from an independent laboratory is the only document that allows verifying whether the content matches the label declaration. It should concern a specific batch, be no older than one year, and provide cannabinoid profile with THC content, terpene profile, and test results for pesticides, heavy metals, microbiology, and solvent residues. Lack of such a document is not a minor issue: a review for clinicians in Mayo Clinic Proceedings directly warns that the market is poorly regulated and studies showed discrepancies between declared and actual CBD and THC content (VanDolah et al., 2019).
What distinguishes good CBD oil from poor quality?
Documentation, not the label description. A good producer publishes a certificate of analysis from an independent lab for a specific batch, and what should be in such a report is detailed in the section above. Lack of a report is the strongest single warning signal detectable before purchase, because then the label declaration has no confirmation.
The scale of the problem was measured by Bonn-Miller’s team, who bought 84 CBD products online from 31 companies and tested their actual composition. Label compliance, understood as deviation within 10%, was found in 30.95% of samples (Bonn-Miller et al., JAMA, 2017). In 42.85% there was more CBD than declared, and in 26.19% less. Separately, researchers detected THC in 18 samples, in concentrations up to 6.43 mg/ml, although labels did not indicate it.
This second result has practical significance for anyone subject to drug testing. A product labeled “THC-free” without a lab report is a declaration, not a fact.
The percentage on a label without a batch test report thus describes the producer’s intention, not the bottle’s content: in the cited study, the declaration matched content in less than one-third of products.
What else is in the bottle besides cannabidiol?
Full hemp extract is a mixture in which cannabidiol is only the most abundant component. Alongside it are minor cannabinoids and terpenes, and the whole is dissolved in a carrier oil that contributes its own fatty acids. This complexity is the basis of the so-called entourage effect hypothesis.
The most frequently cited work on this topic is by Ethan Russo, whose name is often linked online with Mechoulam in this one paper. The 2011 review has a single author. Russo discusses eight hemp terpenoids and notes that these compounds are potent enough to affect animal and human behavior at serum concentrations of single nanograms per milliliter, inhaled from ambient air (British Journal of Pharmacology, 2011).
- Limonene, myrcene, alpha-pinene, and linalool, terpenoids giving hemp its characteristic smell.
- Beta-caryophyllene and caryophyllene oxide, nerolidol, and phytol, described in the same paper.
- All share a common precursor with phytocannabinoids, so they come from the same biosynthetic branch of the plant.
- All are also flavor and aroma components common in the diet, recognized by the US FDA as safe in this role.
Russo also proposes a hypothesis rarely appearing in sales materials because it does not sell products: some non-cannabinoid plant components may act as antidotes to THC’s intoxicating effects, thus increasing its therapeutic index. This shows that the entourage effect in the original concept includes weakening effects, not only enhancement.
The way Russo formulates the conclusion is more important than the list of compounds. Cannabinoid-terpene synergy is presented conditionally, as a hypothesis to be proven, and much of the text proposes methods to study it. This is not a discovery announcement. Later reviews of the same literature repeat the same cautious tone.
A practical conclusion for the reader is simple. A richer extract profile is a reasonable reason to choose a fuller product than an isolate, but it is not clinically proven. A seller who talks about the entourage effect as a fact is ahead of science by several steps.
How to choose a specific product and where to start is explained in the CBD oil selection guide.
Which carrier oil works best?
One that provides fat, because CBD is lipophilic and absorbs poorly without fat. A pharmacokinetic review of CBD in humans states directly that maximum blood concentration increases after a meal and with lipid formulations. This argues for MCT and olive oil, and against aqueous preparations.
The strongest single measurement of this effect comes from a pharmacokinetic study in eight patients with drug-resistant epilepsy: the same capsule taken after a fatty meal gave four times higher area under the concentration curve and fourteen times higher maximum concentration than on an empty stomach. The group was small and the preparation was pure CBD in a capsule, so do not directly transfer numbers to drops, but the direction is clear.
Practically, this means you choose the carrier according to tolerance and taste, not according to a promised absorption multiplier. MCT is neutral in taste and remains liquid in the fridge, olive oil brings its own bitter note that some like and others mask with a drop of juice. Hemp seed oil is sometimes advertised as a nobler carrier, although it practically contains no cannabidiol itself.
What is the difference between full spectrum, broad spectrum, and isolate?
Three extract formats correspond to three different compromises between full composition and lack of THC. Full spectrum retains the entire natural plant profile with trace legal THC. Broad spectrum retains other components but removes THC. Isolate is a single compound with purity above 99%, lacking both terpenes and minor cannabinoids.
| Format | THC | Composition besides CBD | For whom |
|---|---|---|---|
| Full spectrum | trace, at legal limit | full profile of cannabinoids, terpenes, and flavonoids | people without THC testing |
| Broad spectrum | removed during processing | minor cannabinoids and terpenes | professional drivers and athletes |
| Isolate | none | none, pure cannabidiol above 99% | people allergic to other hemp components |
The label gives the percentage concentration, which translates directly to milligrams. 5% oil is 500 mg cannabidiol in 10 ml, 10% is 1000 mg, 20% is 2000 mg. A standard drop from a pipette is about 0.05 ml, so in 5% oil it carries roughly 2.5 mg. This arithmetic allows comparing two products with different prices and concentrations before looking at anything else.
A common mistake is confusing CBD oil with hemp seed oil. These are two products with different raw materials and purposes; they are distinguished in detail in the post hemp oil vs CBD oil. Hemp seed oil goes to the kitchen, CBD oil to supplementation.
How much CBD does the body absorb and why is it a difficult question?
Tables with bioavailability percentages for each administration route circulate widely online but mostly lack measurement support. A systematic review of cannabidiol pharmacokinetics in humans examined 792 publications and found 24 with useful parameters. The conclusion is surprisingly modest: absolute bioavailability was measured only after smoking and was 31%. No one performed such measurement for any other route, although intravenous preparations necessary for it are available (Millar et al., Frontiers in Pharmacology, 2018).
What did the review actually establish? Cannabidiol half-life ranges from 1.4 to 10.9 hours after mucosal spray, 2 to 5 days with chronic oral administration, 24 hours after intravenous administration, and 31 hours after smoking. Time to maximum concentration ranges from zero to four hours after intake.
This finding directly affects advice read in stores. The recommendation to hold oil under the tongue is reasonable and convenient, but it is impossible to say by how much it increases absorption because no one measured this value. It is worth remembering this when reading guides promising doubled effect; practical differences between administration methods are collected in the post how to use CBD oil: sublingual, swallow, or mix with food.
What is certain is that food changes the picture; the scale of this difference is shown in the carrier oil section above. If you compare your feelings from two weeks, take oil under similar conditions, because otherwise you compare two different pharmacokinetics, not two doses.
How long do you need to use the oil before assessing the effect?
Here user opinions diverge most from clinical data, so it is worth starting with measurement. In a psychiatric clinic, records of 72 adult patients who added cannabidiol to usual treatment were analyzed. Among 47 people reporting anxiety and 25 with sleep problems, anxiety scale scores decreased in the first month in 79.2% of patients and remained lowered throughout observation (Shannon et al., The Permanente Journal, 2019).
Sleep results behaved differently and this is the most interesting part of the study. Improvement appeared in the first month in 66.7% of patients but then fluctuated over time instead of increasing or maintaining level. The authors call their study a case series and note that controlled clinical trials are needed.
What conclusions follow for someone who just bought their first bottle? A month is a reasonable minimum observation period because changes were visible in the cited records during this time. At the same time, the sleep effect is unstable, so one bad week does not disqualify the product, and one good week does not confirm it.
The practical consequence is inconvenient for sellers and buyers alike. A reliable assessment requires notes, not memory. Record date, time, conditions, and one sentence about well-being; after four weeks you have material that can be read instead of an impression that can be interpreted arbitrarily.
What do studies confirm and what remains a hypothesis?
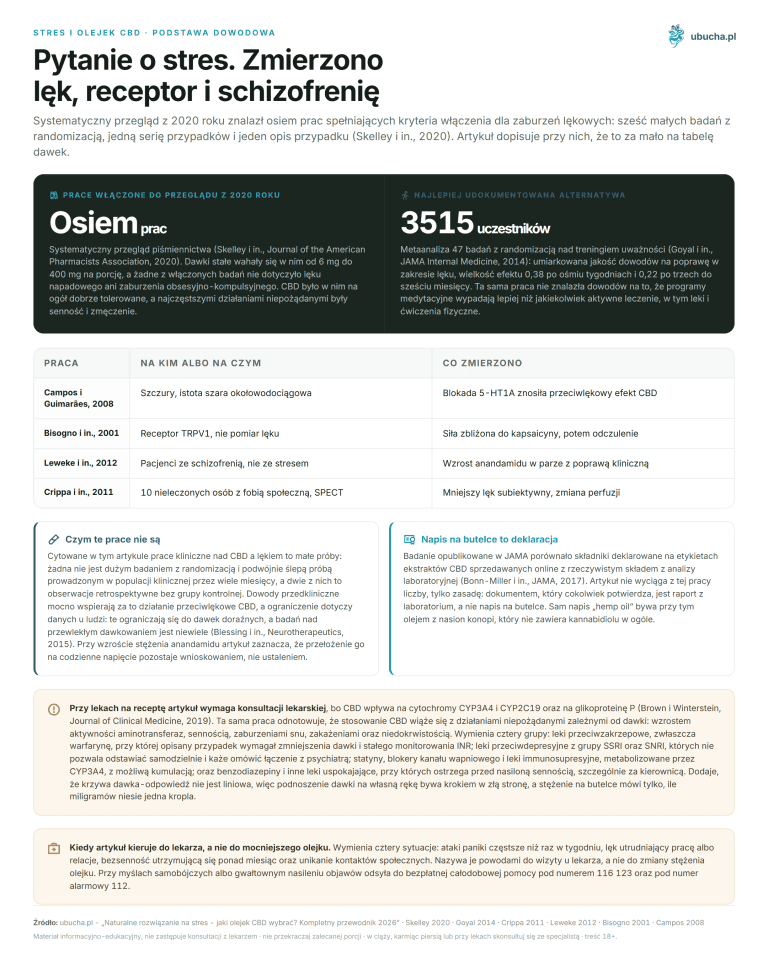
The division is sharper than most sales materials suggest. On the confirmed side is one indication: registration of a cannabidiol-based drug for rare, severe forms of epilepsy, granted by the FDA in June 2018 (VanDolah et al., Mayo Clinic Proceedings, 2019). This is proof that the substance has pharmacological activity, not that it helps with everything.
On the promising but unconfirmed side are anxiety and sleep. Shannon’s case series shows changes in clinical scales but without a control group or randomization. A review for clinicians notes a growing body of preclinical and clinical evidence for chronic pain, describing CBD as a possible adjunct option, not an established therapy.
On the hypothesis side is the entourage effect. Neither Russo’s 2011 review nor later reviews present it as proven; they describe it as a concept requiring research. Marketing usually does not mark this difference.
From our observations while organizing this text, one more thing emerges beyond individual indications. Much of the numbers repeated in the Polish internet about CBD, especially percentages describing users, do not lead to any publication. When all are cut off, less material remains, but what remains can be checked in two minutes.
How much cannabidiol is safe according to EFSA?
Since 2026, there is a number to refer to, differing from what was previously repeated by several orders of magnitude. The European Food Safety Authority derived by the benchmark dose method, with an uncertainty factor of 400, a provisional safe dose of 0.0275 mg per kilogram of body weight per day. For a 70 kg person, this is about 2 mg daily (EFSA Journal, 2026).
The range of this value is narrow and must be given with the number. It applies only to supplements with cannabidiol purity of at least 98%, without nanoparticles, produced by a process recognized as safe, and with genotoxicity excluded. The panel based it on subchronic studies compliant with good laboratory practice.
The most important sentence in this opinion contains no number. Cannabidiol safety cannot be established in people under 25 years old, pregnant and breastfeeding women, and people taking medications. If you belong to any of these groups, this information is more important than any dose given in a guide.
EFSA also lists where data are still incomplete: liver, gastrointestinal tract, nervous, hormonal, and reproductive systems. Animal studies showed consistent liver toxicity, and human data indicate hepatotoxic potential especially with concurrent drug use. An older safety review described cannabidiol as well tolerated but listed inhibition of liver drug metabolism among documented effects (Bergamaschi et al., Current Drug Safety, 2011).
What do we still not know about cannabidiol safety?
The same EFSA opinion is also the most honest list of gaps existing on CBD, and it is worth reading alongside the 2 mg number. The panel reviewed animal and human studies published up to June 2024 and found that previous data gaps persist because many new works have methodological limitations: non-standardized protocols, short duration, and concurrent pharmacological treatment of participants.
The strongest signal concerns the liver. Animal studies showed consistent liver toxicity, with organ mass and histopathological changes as the most sensitive endpoints. Human studies indicate hepatotoxic potential, especially when cannabidiol is used with drugs. Higher doses also reported gastrointestinal symptoms.
Three areas remain open, each concerning a different reader group. Data on neurological and psychiatric safety are insufficient. Animal studies reinforced concerns about reproductive toxicity, and prenatal exposure showed long-term and sex-dependent neurodevelopmental effects in offspring. Hormonal disturbances were also noted, including changes in thyroid hormone levels and histopathological changes in adrenal glands. Immunotoxicity has not yet been studied, although cannabidiol interacts with immune pathways. Another limitation is the composition of products themselves: studies were conducted on products with varying composition, whose other post-extraction components are rarely described.
For balance, it is worth listing what an older safety review did not find, as the list is long. Cannabidiol was not toxic to non-transformed cells, did not change food intake, did not cause catalepsy, did not affect heart rate, blood pressure, or body temperature, did not alter gastrointestinal transit, and did not impair psychomotor or mental functions. Documented effects included inhibition of liver drug metabolism, reduced fertility, and decreased activity of P-glycoprotein and other drug transporters (Bergamaschi et al., 2011).
Does CBD interact with medications?
Yes, and this is the best documented safety issue of cannabidiol. A review of data from medicinal products containing CBD showed that nearly half of users experienced dose-dependent adverse effects. The most common were increased aminotransferase activity, sedation, sleep disturbances, infections, and anemia (Brown and Winterstein, Journal of Clinical Medicine, 2019).
The interaction mechanism lies in drug-metabolizing enzymes and transporters. The authors point to cannabidiol’s effect on cytochrome P450, listing CYP3A4 and CYP2C19, and on P-glycoprotein responsible for excretion. A lab study examining cannabinoids and their metabolites on microsomes overexpressing specific isoforms showed cannabidiol competitively inhibits CYP3A4, CYP2B6, CYP2C9, CYP2D6, and CYP2E1 (Nasrin et al., Drug Metabolism and Disposition, 2021).
What does this mean at the kitchen table, not in the lab? If you take a drug metabolized by any of these pathways, its blood concentration may increase. This concerns drugs with a narrow therapeutic window, where a small concentration change alters effect. Talking with a doctor or pharmacist is not a formality added at the article’s end but a condition for sensible product use.
Caution also applies the other way, with drugs taken occasionally. The fact that something is available over the counter says nothing about how it behaves in the presence of cannabidiol.
Is CBD oil legal in Poland?
Yes, provided the tetrahydrocannabinol content in the raw material meets the condition. Industrial hemp in Polish law are Cannabis sativa L. plants in which the sum of delta-9-THC and tetrahydrocannabinolic acid in flowering or fruiting tops does not exceed 0.3% by dry weight. The basis is Article 4 point 5 of the Act of July 29, 2005 on Counteracting Drug Addiction, as amended by the Act of March 24, 2022, Dz.U. 2022 item 763.
Three details of this regulation are often distorted online, each changing the lab test result. First, the threshold is calculated as the sum of delta-9-THC and THCA, not delta-9-THC alone; the sum is rounded to one decimal place. Second, the 0.3% value applies since May 7, 2022; earlier it was 0.20%, so older guides give a different number according to the then legal status.
Third, the Polish threshold does not come from EU regulations, although it has the same value. Regulation (EU) 2021/2115, effective January 1, 2023, sets a 0.3% threshold for hemp grown under the Common Agricultural Policy. This is a separate regulation with the same numeric value, not the source of the Polish threshold. The earlier Regulation 1307/2013, still cited by some texts, set a 0.2% threshold and was repealed on January 1, 2023.
It is also important to know what this threshold does not cover. The 0.3% number, repeated in product descriptions, concerns the plant, not the finished oil, and cannabidiol itself is not listed in any controlled substance lists. Separately, the food status: in 2022, EFSA stated that CBD safety as novel food cannot be established. Four years later, in the 2026 opinion discussed above, the same agency derived a provisional safe dose.
It is also worth noting hexahydrocannabinol, or HHC, sometimes advertised as a legal alternative. HHC is a controlled substance in Poland and nothing has changed in this regard.
What mistakes most often spoil the assessment of oil effectiveness?
Most negative opinions can be reduced to five recurring situations, each with a counterpart in the data cited above. We collected them in one place to check off before writing your own review.
- Too short observation period. Clinical records show anxiety scale changes appearing in the first month, not after the first evening (Shannon et al., 2019).
- Dose lower than expected. In the survey of 387 people, 54% took less than 50 mg daily, so comparing your feelings with forum descriptions may be comparing different things (Moltke and Hindocha, 2021).
- Product without a certificate of analysis. A review for clinicians notes discrepancies between declared and actual CBD and THC content as a documented market problem (VanDolah et al., 2019).
- Variable administration conditions. Oil taken sometimes on an empty stomach, sometimes after a meal gives two different absorption profiles, as explained in the carrier oil section above.
- Assessment from memory instead of notes. The sleep effect in the cited case series fluctuated over time, and fluctuation without notes reads as no effect.
A sixth, higher-order mistake concerns reading opinions themselves. A percentage given without author name, year, and journal is not data but a number. While organizing this text, we rejected a dozen such percentages, including alleged market shares and consumer survey results, because none led to a publication that could be opened.
Where to buy CBD oil to ensure quality?
The deciding factor is not the sales channel but whether the seller provides a certificate of analysis for a specific batch and whether the batch number on the document matches the number on the bottle. A review for clinicians describes the CBD market as poorly regulated and recommends directing patients only to products with verifiable quality (VanDolah et al., Mayo Clinic Proceedings, 2019).
What should be in the batch test report is detailed in the certificate of analysis section above. Before purchase, also check what the report does not cover: whether the producer states the extraction method and carrier composition.
What to avoid? Offers without a stated producer, sales through social media accounts without registered business, and products where the certificate question is answered descriptively instead of with a file. Price difference rarely compensates for the risk that the bottle contains different content than the label.
The price itself carries limited information and does not replace documentation. The cheapest product per milligram is often cheapest because it contains fewer milligrams than declared, exactly the defect described in the Mayo Clinic Proceedings review.
How much does good CBD oil cost?
The price per milligram decides, not the bottle price. Divide the amount by the total CBD content stated on the packaging, and bottles of different volume and concentration become comparable in one number. This one operation eliminates most price traps, as the cheapest bottle on the shelf is often the most expensive milligram.
In the oil category at u Bucha store, prices per milligram of CBD as of August 10, 2026, range roughly from 0.10 to 0.13 PLN. We give the range for the whole category and with a date because the catalog changes faster than the article, and the price of a single product copied into the text becomes outdated within weeks.
Price includes costs not visible on the label. Cultivation in a farm with phytosanitary supervision costs more than raw material from a region without such supervision. Laboratory testing done twice, at extract and finished product stages, is an expense for each batch. A producer publishing this documentation includes its cost in the price; a producer without it may be cheaper but transfers risk to the buyer.
Frequently Asked Questions
Does CBD oil really work, or is it a placebo?
Cannabidiol has documented pharmacological effects: in June 2018, the FDA approved the drug Epidiolex for rare, severe forms of epilepsy (VanDolah et al., Mayo Clinic Proceedings, 2019). This does not mean it will help with every ailment. For anxiety and sleep, data come from case series without a control group, so the placebo effect cannot be calculated from them.
What do people who use CBD most often say about it?
In a survey of 2409 people, 62% used CBD due to a specific ailment, most often pain, anxiety, and depression, and nearly 36% rated its effect as very good (Corroon and Phillips, 2018). A second survey of 387 people gave a similar list of reasons: anxiety 42.6%, sleep 42.5%, stress 37% (Moltke and Hindocha, 2021).
How long does it take to see the effects of CBD oil?
In the records of 72 psychiatric clinic patients, anxiety scale scores decreased in the first month in 79.2% of people, and sleep improvement occurred in 66.7%, but fluctuated over time (Shannon et al., 2019). A month of regular use is therefore a reasonable minimum observation period before forming your own opinion.
Is CBD oil legal in Poland?
Yes, if the raw material is industrial hemp, in which the sum of delta-9-THC and THCA does not exceed 0.3% by dry weight. The basis is Article 4 point 5 of the Act on Counteracting Drug Addiction as published in Dz.U. 2022 item 763. The threshold is calculated as the sum of both compounds, not just delta-9-THC alone.
What concentration of CBD oil should I start with?
Lower concentration allows for smaller dosing steps, which facilitates observation. A 5% oil contains 500 mg cannabidiol in 10 ml, and a standard drop about 2.5 mg. At 10%, the same drop carries twice as much. Decide on the dose size with your doctor, especially if you take any medications.
Does CBD interact with medications?
Yes. Cannabidiol competitively inhibits CYP3A4, CYP2B6, CYP2C9, CYP2D6, and CYP2E1 (Nasrin et al., Drug Metabolism and Disposition, 2021), and a safety data review also indicates P-glycoprotein (Brown and Winterstein, 2019). Blood drug concentration may increase, so the combination should be discussed with a doctor.
What does broad spectrum mean on the label?
Broad spectrum is an extract from which tetrahydrocannabinol has been removed, retaining minor cannabinoids and terpenes. It is chosen by people subject to THC testing, including professional drivers and athletes. Retaining other components is an argument based on the entourage effect hypothesis, not clinical evidence.
What side effects do CBD users report?
In a review of medicinal product data, nearly half of users experienced dose-dependent side effects: increased aminotransferase activity, sedation, sleep disturbances, infections, and anemia (Brown and Winterstein, 2019). In a consumer survey, one in three reported mild side effects (Corroon and Phillips, 2018).
If after reading you want to compare available formats and concentrations, the full offer is collected in the hemp oils category.
This article is informational and educational and does not constitute medical advice. Before starting cannabis or CBD for therapeutic purposes, consult a doctor, especially if you take other medications, are pregnant, or breastfeeding.
Author: Michał Waluk · Published: 2026-05-11 · Updated: 2026-09-22