
CBD for Social Phobia: What Research Says and What Has Not Been Compared
CBD for social phobia: what was measured in three small trials, why therapy and SSRIs remain first choice, and when anxiety requires same-day help.
You stand in a conference room, a presentation is about to start. Your hands are sweaty, your heart races, your thoughts go blank. Social phobia (social anxiety disorder, SAD) is a psychiatric diagnosis, not shyness or weak character. In a review of 21 European population studies, the median lifetime prevalence was 6.65%, and the annual prevalence 2.0% (Fehm et al., European Neuropsychopharmacology, 2005). More and more people turn to cannabidiol (CBD), hoping to ease social anxiety. This guide shows what has actually been measured: on whom, how many people, for how long, and with what result. It also shows the limits of these measurements and the moment when a specialist, not a supplement, is needed. You will not find a dose to measure here, and below we explain why.
KEY INFORMATION
- Median lifetime prevalence of social phobia in 21 European population studies was 6.65% (Fehm et al., European Neuropsychopharmacology, 2005).
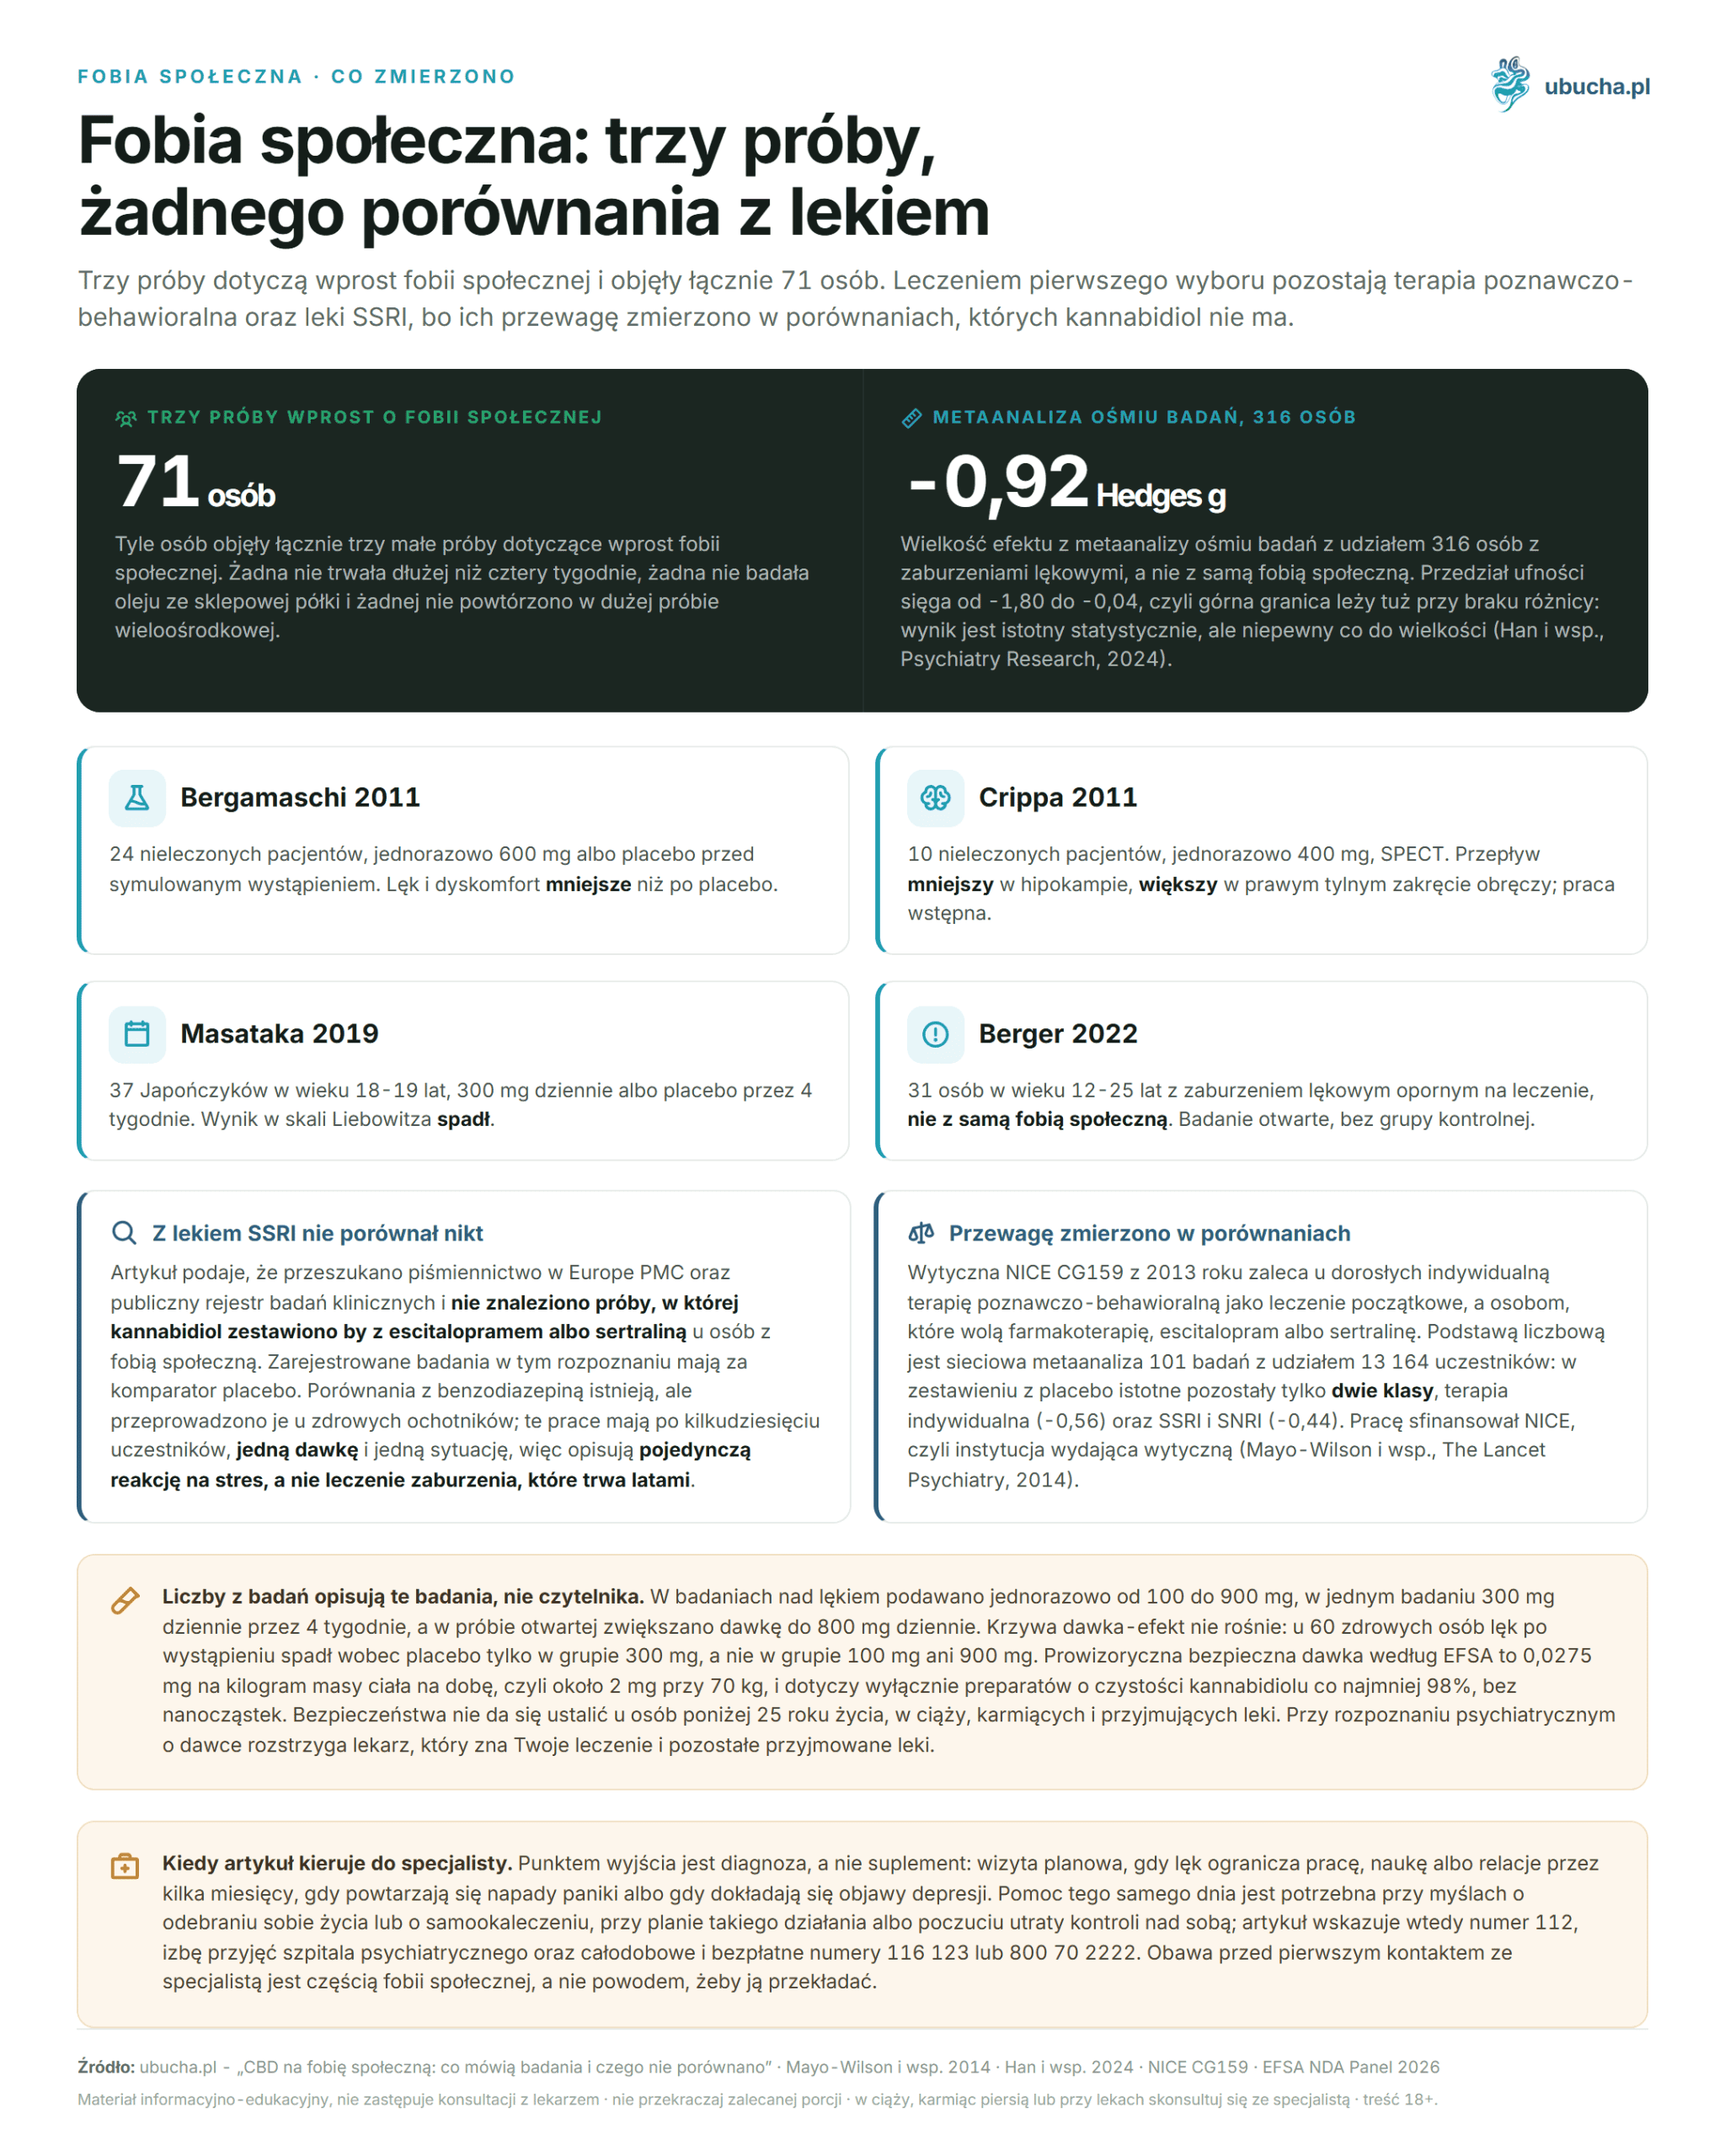
- Bergamaschi 2011: 24 untreated patients with social phobia, single dose 600 mg CBD or placebo before simulated public speaking, lower anxiety than placebo group (Neuropsychopharmacology, 2011).
- Meta-analysis of eight studies with 316 participants: Hedges g effect size was -0.92 with confidence interval from -1.80 to -0.04 (Han et al., Psychiatry Research, 2024).
- We found no study comparing CBD with SSRI medication in patients with social phobia.
- Provisional safe dose according to EFSA is 0.0275 mg per kilogram of body weight per day, about 2 mg for 70 kg, and safety cannot be established for people under 25 years old, pregnant, breastfeeding, or taking medications (EFSA Journal, 2026).
What is social phobia and what happens in the brain?
Social phobia is a persistent, disproportionate fear of being judged by others. In a review of 21 European population studies, the median lifetime prevalence was 6.65%, and the annual prevalence 2.0%; highest rates were noted in younger people, and women were more often affected than men (Fehm et al., European Neuropsychopharmacology, 2005). The same review describes it as a chronic disorder with a high rate of comorbid diagnoses and significant functional impairment.
A meta-analysis of neuroimaging studies published after 2007 confirmed hyperactivity of the fear circuit: amygdala, insular cortex, anterior cingulate gyrus, and prefrontal cortex. The authors also described weakened connectivity between parietal areas and the limbic network and proposed a new network model based on this (Brühl et al., Neuroscience and Biobehavioral Reviews, 2014). The measurement concerned groups of patients compared to control groups, so it is not a test that can be performed on a single person.
Social phobia is distinguished from shyness by the scale of impairment. Beesdo et al. observed 3021 people aged 14-24 from a population sample for ten years: cumulative incidence of social phobia was 11.0%, with cases concentrated between ages 10 and 19 (Archives of General Psychiatry, 2007). Symptoms are both physical and cognitive, so simply telling yourself “calm down” is not enough.
- Accelerated heart rate, sweaty palms, voice tremor, nausea, dizziness.
- Persistent thoughts about judgment, catastrophizing, difficulty concentrating, blanking out.
- Analyzing your performance afterward, often for hours.
- Avoidance: giving up promotions, avoiding phone calls, limiting contacts to a few people.
Why do psychotherapy and SSRIs remain first-line treatments?
Because the superiority of these methods has been measured in comparisons that CBD lacks. The NICE CG159 guideline from 2013 recommends individual cognitive-behavioral therapy as initial treatment for adults with social phobia, and for those preferring pharmacotherapy, escitalopram or sertraline.
The numerical basis of this guideline is a network meta-analysis of 101 studies involving 13,164 participants. Against a waiting list, individual cognitive-behavioral therapy showed the largest effect among all compared classes (standardized mean difference -1.19; confidence interval from -1.56 to -0.81), SSRIs and SNRIs -0.91 (from -1.23 to -0.60), monoamine oxidase inhibitors -1.01 (from -1.56 to -0.45), benzodiazepines -0.96 (from -1.56 to -0.36). Compared to appropriate placebo, only two classes remained significant: individual therapy (-0.56; from -1.00 to -0.11) and SSRIs and SNRIs (-0.44; from -0.67 to -0.22). The work was funded by NICE, the institution issuing the guideline (Mayo-Wilson et al., The Lancet Psychiatry, 2014).
The same guideline explicitly advises against routine use of benzodiazepines, anticonvulsants, tricyclic antidepressants, or antipsychotics in social phobia in adults. The full guideline justifies this by reluctance to long-term benzodiazepine use due to tolerance and dependence.
Untreated social phobia is associated with increased risk of later depression. In the same ten-year observation of 3021 people, the relative risk of depression after social phobia ranged from 1.49 to 1.85, regardless of age at onset (Beesdo et al., Archives of General Psychiatry, 2007). This is an argument for diagnosis, not for coping alone for years.
How does CBD affect anxiety and how was this measured?
The answer depends on whether you ask about test tubes, animals, or humans. The best-described pathway leads to the serotonin 5-HT1A receptor, but the measurement linking this receptor to behavior comes from rats. In humans, only changes in limbic area activity have been measured so far, not the mechanism itself.
| Mechanism | Measured on | What was shown |
|---|---|---|
| 5-HT1A agonism | Cell culture, cloned human receptor | Cannabidiol displaces agonist and acts as a moderate affinity agonist itself (Russo et al., Neurochemical Research, 2005) |
| 5-HT1A as cause of effect | Male Wistar rats, injection into periaqueductal gray | Effect blocked by receptor antagonist WAY-100635 (Soares et al., Behavioural Brain Research, 2010) |
| TRPV1 at higher doses | Male Wistar rats, injection into midbrain | TRPV1 antagonist restored effect of higher dose, explaining bell-shaped curve (Campos and Guimarães, Progress in Neuro-Psychopharmacology and Biological Psychiatry, 2009) |
| Effect on FAAH enzyme | Human and rodent enzyme in biochemical study | Cannabidiol does not inhibit human FAAH; increase of anandamide in humans explained by competition for FABP transport proteins (Elmes et al., Journal of Biological Chemistry, 2015) |
| Amygdala activity | 15 healthy men, functional imaging | After single 600 mg dose, signal in amygdala and cingulate gyrus decreased while viewing fearful faces (Fusar-Poli et al., Archives of General Psychiatry, 2009) |
The statement “CBD inhibits FAAH” circulates in guides and until recently was also in this text. For humans, it is false: the study that checked this showed that unlike the rodent enzyme, human FAAH is not blocked by cannabidiol.
Data on CBD’s effect on the hypothalamic-pituitary-adrenal axis in humans are limited. In a study with 32 high-risk psychosis individuals and 26 healthy controls, weekly administration of 600 mg daily produced cortisol reactivity during social stress testing intermediate between healthy and placebo groups, but the difference from placebo was not significant (p = 0.70; Appiah-Kusi et al., Psychopharmacology, 2020). This is a directional signal, not proof, and did not involve patients with social phobia.
What do clinical trials of CBD in social phobia show?
Three small trials directly addressed social phobia and included a total of 71 people. A fourth study, often cited in this context, concerned anxiety disorders in general and had no control group. None have been replicated in a large multicenter trial.
| Study | Who and how many | Study design | Result |
|---|---|---|---|
| Bergamaschi 2011, Neuropsychopharmacology | 24 untreated patients with social phobia and 12 healthy untreated controls | Randomized, double-blind; single 600 mg dose (12 people) or placebo (12 people) 1.5 hours before simulated public speaking | Lower anxiety, discomfort, and cognitive impairment than placebo; results similar to healthy group |
| Crippa 2011, Journal of Psychopharmacology | 10 untreated patients with social phobia | Double-blind, crossover; single 400 mg dose, SPECT imaging | Reduced blood flow in left parahippocampal gyrus, hippocampus, and inferior temporal gyrus; increased in right posterior cingulate gyrus; authors call it preliminary work |
| Masataka 2019, Frontiers in Psychology | 37 Japanese aged 18-19 with social phobia and avoidant personality | Double-blind; 300 mg daily (17 people) or placebo (20 people) for 4 weeks | Decrease in Liebowitz Social Anxiety Scale and Fear of Negative Evaluation questionnaire scores |
| Berger 2022, The Journal of Clinical Psychiatry | 31 people aged 12-25 with treatment-resistant anxiety disorder, not just social phobia | Open-label, no control group; CBD added to existing treatment, dose increased to 800 mg daily over 12 weeks | OASIS score decreased from 10.8 to 6.3, a 42.6% reduction (p below 0.0001); adverse effects in 25 of 31 people |
The last row requires caution. The Berger study had no placebo arm, and placebo response in anxiety disorders can be high, so the 42.6% reduction should not be read as a measure of cannabidiol’s efficacy alone. CBD was added to ongoing treatment, which participants did not discontinue.
A quantitative summary is provided by a meta-analysis of eight studies with 316 people with anxiety disorders: Hedges g effect size was -0.92 with confidence interval from -1.80 to -0.04 (Han et al., Psychiatry Research, 2024). The upper bound of this interval is just near zero, so the result is statistically significant but uncertain in magnitude.
How much CBD was given in studies and why is this not a recommendation for you?
The numbers below describe specific clinical trials and only that. In anxiety studies, single doses ranged from 100 to 900 mg, in one study 300 mg daily for four weeks, and in an open trial doses were increased to 800 mg daily. None of these numbers is a guideline for the reader.
The dose-effect curve is not increasing. Zuardi et al. randomly assigned 60 healthy people aged 18-35 into five groups of twelve: placebo, 1 mg clonazepam, and CBD at 100, 300, or 900 mg, then each participant gave a speech before the others. Anxiety after the speech decreased compared to placebo only in the 300 mg group, not in the 100 mg or 900 mg groups (Frontiers in Pharmacology, 2017). Participants were healthy, so the result should not be directly transferred to diagnosed individuals.
The same numbers show why transferring studies to a store-bought bottle is not straightforward. The provisional safe dose set by the EFSA panel is 0.0275 mg per kilogram of body weight per day, about 2 mg per day for 70 kg (EFSA Journal, 2026). The doses in described trials are hundreds of times higher, administered under researcher supervision and in pharmaceutical-grade preparations. The EFSA threshold applies only to preparations with at least 98% cannabidiol purity, without nanoparticles, so it does not directly translate to any oil on the shelf.
If you are looking for a specific dose for yourself, this text will not provide it and no text should. For a psychiatric diagnosis, the dose is decided by a doctor who knows your treatment, results, and other medications.
Has anyone compared CBD with medications used in social phobia?
No one with SSRIs. We searched literature in Europe PMC and the public clinical trial registry and found no trial comparing CBD with escitalopram or sertraline in people with social phobia. Registered CBD studies in this diagnosis use placebo as comparator.
Comparisons with benzodiazepines exist but in a different population. In a 1993 study, four groups of ten healthy volunteers received placebo, 300 mg CBD, 10 mg diazepam, or 5 mg ipsapirone before simulated public speaking. Diazepam had anxiolytic effects before and after the speech but did not prevent anxiety increase caused by the speech itself; cannabidiol reduced anxiety only after the speech; sedation was noted only after diazepam (Zuardi et al., Journal of Psychopharmacology, 1993).
In a 2017 study, the comparator was 1 mg clonazepam, also in healthy people. Both studies had a few dozen participants, one dose, and one situation, so they describe a single stress reaction, not treatment of a disorder lasting years.
We noticed during editing that the question “CBD or SSRI” regularly returns in reader messages, but the literature simply has no answer. Comparisons in guides, including earlier versions of this text, were made by combining two separate literatures, not by a study placing both options side by side in the same patients. The comparative table then looked convincing, though no trial supported it.
A systematic review of eleven randomized studies on cannabidiol in anxiety disorders summarizes this state frankly: studies differ in diagnosis, dose, and design so results are sometimes contradictory (Coelho et al., Life, 2024). Comparison with first-line medication would require a study no one has conducted yet.
What are CBD interactions and what does EFSA say about safety?
The risk mainly concerns people already taking medications, i.e., exactly the reader with diagnosed social phobia. Cannabidiol affects cytochrome P450 enzymes, mainly CYP3A4 and CYP2C19, and P-glycoprotein, so it can alter blood concentrations of other drugs (Brown and Winterstein, Journal of Clinical Medicine, 2019).
| Drug or group | What was measured | Source |
|---|---|---|
| Clobazam | In 13 children with refractory epilepsy, active metabolite norklobazam concentration increased on average by 500%, confidence interval 90% to 610% in the fourth week | Geffrey et al., Epilepsia, 2015 |
| Warfarin | Case report: after adding cannabidiol, warfarin dose had to be reduced and INR monitored more frequently | Grayson et al., Epilepsy and Behavior Case Reports, 2018 |
| Drugs metabolized by CYP3A4 and CYP2C19 | Review of CBD product characteristics: adverse effects in nearly half of users, increasing with dose | Brown and Winterstein, Journal of Clinical Medicine, 2019 |
| Sertraline, escitalopram | No interaction studies in humans found; warning based on shared metabolic pathway, not measurement | no measurement |
The regulator is more cautious than the market. The EFSA panel set a provisional safe dose of 0.0275 mg per kilogram per day and specified it applies only to supplements with at least 98% cannabidiol purity, without nanoparticles. Safety cannot be established for people under 25, pregnant or breastfeeding women, or those taking medications. The panel also noted insufficient neurological and psychiatric safety data, and potential liver damage in humans, especially with concomitant drug use (EFSA Journal, 2026).
A separate question is addiction. A single abuse potential test in 43 healthy recreational users of multiple substances showed that 750 mg dose did not differ from placebo in liking scale, and higher doses performed clearly weaker than 2 mg alprazolam (Schoedel et al., Epilepsy and Behavior, 2018). The study was funded by GW Research, manufacturer of the tested preparation. This is a single dose measurement in healthy people, so it says nothing about long-term use.
Before combining CBD with prescription medication, talk to your treating doctor. We collected a full list of drug groups with reported cannabidiol interactions separately: CBD interactions with medications.
When is a specialist needed and when is immediate help required?
Immediate, meaning the same day, when thoughts of suicide or self-harm appear, plans for such actions, or a feeling of loss of control. Then call 112, go to a psychiatric hospital emergency room, or call the free 24/7 numbers 116 123 or 800 70 2222.
Do not postpone this because of anxiety about talking. Fear of first contact with a specialist is part of social phobia, not a reason to delay it. A phone call can be easier at such a moment than a visit and is enough as a first step.
A planned visit is needed when anxiety limits work, study, or relationships for several months, when panic attacks recur, when depressive symptoms add up, or when you use alcohol to calm down. Social phobia increases the risk of later depression (Beesdo et al., Archives of General Psychiatry, 2007), so delaying diagnosis has its cost. In the same sample, cumulative incidence of depression over ten years was 27.0%.
- Suicidal or self-harm thoughts: 112, emergency room, 116 123 or 800 70 2222.
- Panic attacks more frequent than once a week.
- Avoidance of daily situations: shopping, public transport, phone calls.
- Social isolation lasting more than two months.
- Drinking alcohol to endure meetings or presentations.
A referral to a psychiatrist is not required, also within public health care: just make an appointment at a mental health clinic. Certified cognitive-behavioral therapists can be found in the registry maintained by the Polish Society of Cognitive and Behavioral Therapy. How to prepare for a conversation about cannabis with a doctor is described separately: how to talk to a doctor about CBD.
What to look for in a CBD oil certificate?
Batch number, how THC content is presented, and who performed the test. An analysis certificate from a laboratory independent of the manufacturer is the only document telling what is really in the bottle. You can check the laboratory accreditation in the public registry of the Polish Centre for Accreditation.
The law sets one number here but counts it differently than most certificates. Hemp plants are those in which the sum of delta-9-THC and tetrahydrocannabinolic acid does not exceed 0.3% dry weight, rounded to one decimal place (art. 4 point 5 of the Act of July 29, 2005 on counteracting drug addiction, Journal of Laws 2023 item 1939, as amended by Journal of Laws 2022 item 763). The certificate’s “Total THC” converts tetrahydrocannabinolic acid by factor 0.877, while the law sums both values without conversion, so the legal number is higher than that on the certificate.
A separate issue is the status of the ingredient itself. Cannabidiol is not on the EU list of authorized novel food ingredients, and EFSA’s 2026 opinion is a safety assessment with conditions, not a marketing authorization. You are therefore buying a product whose food status remains unresolved.
| Oil type | THC | When it matters |
|---|---|---|
| Broad spectrum | Removed | When you are subject to drug testing |
| Full spectrum | Trace, from hemp | When such tests do not concern you |
| Isolate | None | When you react to other hemp components |
- Batch number on the bottle matches the certificate.
- Test date not older than one year.
- Laboratory with accreditation, independent of the manufacturer.
- THC result given together with tetrahydrocannabinolic acid, not just delta-9-THC.
- Tests for pesticides, heavy metals, and solvent residues.
Summary: what to remember about CBD for social phobia?
Social phobia has an established first-line treatment: individual cognitive-behavioral therapy, and if pharmacotherapy is preferred, escitalopram or sertraline. Cannabidiol is not a registered medication for this indication, and we found no studies placing it alongside SSRI medication in the same patients.
The existing evidence is real but narrow. Three trials in social phobia included a total of 71 people; a fourth study concerned anxiety disorders in general and had no control group. A meta-analysis of eight studies shows an effect size of -0.92 with a confidence interval reaching -0.04, the boundary of no difference.
All these trials used pure cannabidiol, at doses hundreds of times higher than the provisional EFSA safety threshold, under researcher supervision. This is not the same situation as a store-bought oil bottle, and that is why no dose to measure is given in this text.
The honest answer to the question posed in the title is therefore more cautious than in earlier versions of this text. In three small trials, pure cannabidiol reduced anxiety measured by subjective scales in diagnosed individuals, but none studied store-bought oil, none lasted longer than four weeks, and none compared it with first-line treatment.
If anxiety limits your work, study, or relationships, the starting point is diagnosis, not a supplement. And if suicidal thoughts appear, help is needed the same day: 112, emergency room, 116 123, or 800 70 2222.
Frequently Asked Questions
Does CBD help with social phobia according to clinical studies?
The data are preliminary. In a randomized study by Bergamaschi, 24 untreated patients with social phobia received a single dose of 600 mg cannabidiol or placebo before a simulated public speaking; in the CBD group, anxiety, discomfort, and cognitive impairment were less than in the placebo group (Neuropsychopharmacology, 2011).
How much CBD was given to participants in social anxiety studies?
Single doses ranged from 100 to 900 mg, in one study 300 mg daily for four weeks in 37 eighteen- and nineteen-year-olds, and in an open trial up to 800 mg daily for 12 weeks in 31 people. This is a description of studies, not a recommendation: the dose for a psychiatric diagnosis is determined by a doctor.
Does CBD replace SSRI medications in treating social phobia?
No. The NICE CG159 guideline recommends individual cognitive-behavioral therapy for adults, and if pharmacotherapy is chosen, escitalopram or sertraline. Cannabidiol is not registered as a medication for this indication. Antidepressants should not be discontinued without consulting the treating physician.
Has anyone compared CBD with SSRIs in patients with social phobia?
We found no such study either in the literature in Europe PMC or in the public clinical trial registry. Registered CBD trials in this diagnosis compare it with placebo. There are comparisons with benzodiazepines, but these were conducted in healthy volunteers.
Does CBD interact with medications used for anxiety?
Yes. Cannabidiol affects CYP3A4 and CYP2C19 enzymes and P-glycoprotein, so it can alter the concentrations of other drugs (Brown and Winterstein, Journal of Clinical Medicine, 2019). The best documented interaction is with clobazam, measured in 13 children with refractory epilepsy (Geffrey et al., Epilepsia, 2015).
Does CBD inhibit the FAAH enzyme in humans?
No. In a biochemical study, cannabidiol inhibited the rodent enzyme but not the human one, so the increase of anandamide in humans is not explained by FAAH inhibition; the authors indicated competition for intracellular FABP transport proteins (Elmes et al., Journal of Biological Chemistry, 2015). This is a common error in Polish guides.
Is CBD addictive like benzodiazepines?
In a single abuse potential test in 43 healthy recreational users of multiple substances, a 750 mg dose did not differ from placebo, and higher doses performed significantly weaker than alprazolam (Schoedel et al., Epilepsy and Behavior, 2018). The study was funded by the manufacturer of the tested preparation, and there is a lack of long-term use studies, so no conclusion about full safety can be drawn from this.
When does social anxiety require immediate help?
When thoughts of suicide or self-harm appear, plans for such actions, or a feeling of loss of control. Then call 112, go to a psychiatric hospital emergency room, or use the free 24/7 numbers 116 123 and 800 70 2222.
This article is for informational and educational purposes and does not constitute medical advice. Before starting cannabis or CBD for therapeutic purposes, consult a doctor, especially if you take other medications, are pregnant, or breastfeeding. In a mental health crisis, help is available 24/7 and free of charge: 116 123, 800 70 2222, and in life-threatening situations 112.
Author: Michał Waluk · Published: 2026-04-27 · Updated: 2026-08-16