
5-HTP properties - serotonin precursor for sleep and mood 2026
The Cochrane review found 108 studies on 5-HTP in depression and only two were suitable for evaluation. Mechanism, risk of serotonin syndrome, and the history of EMS.
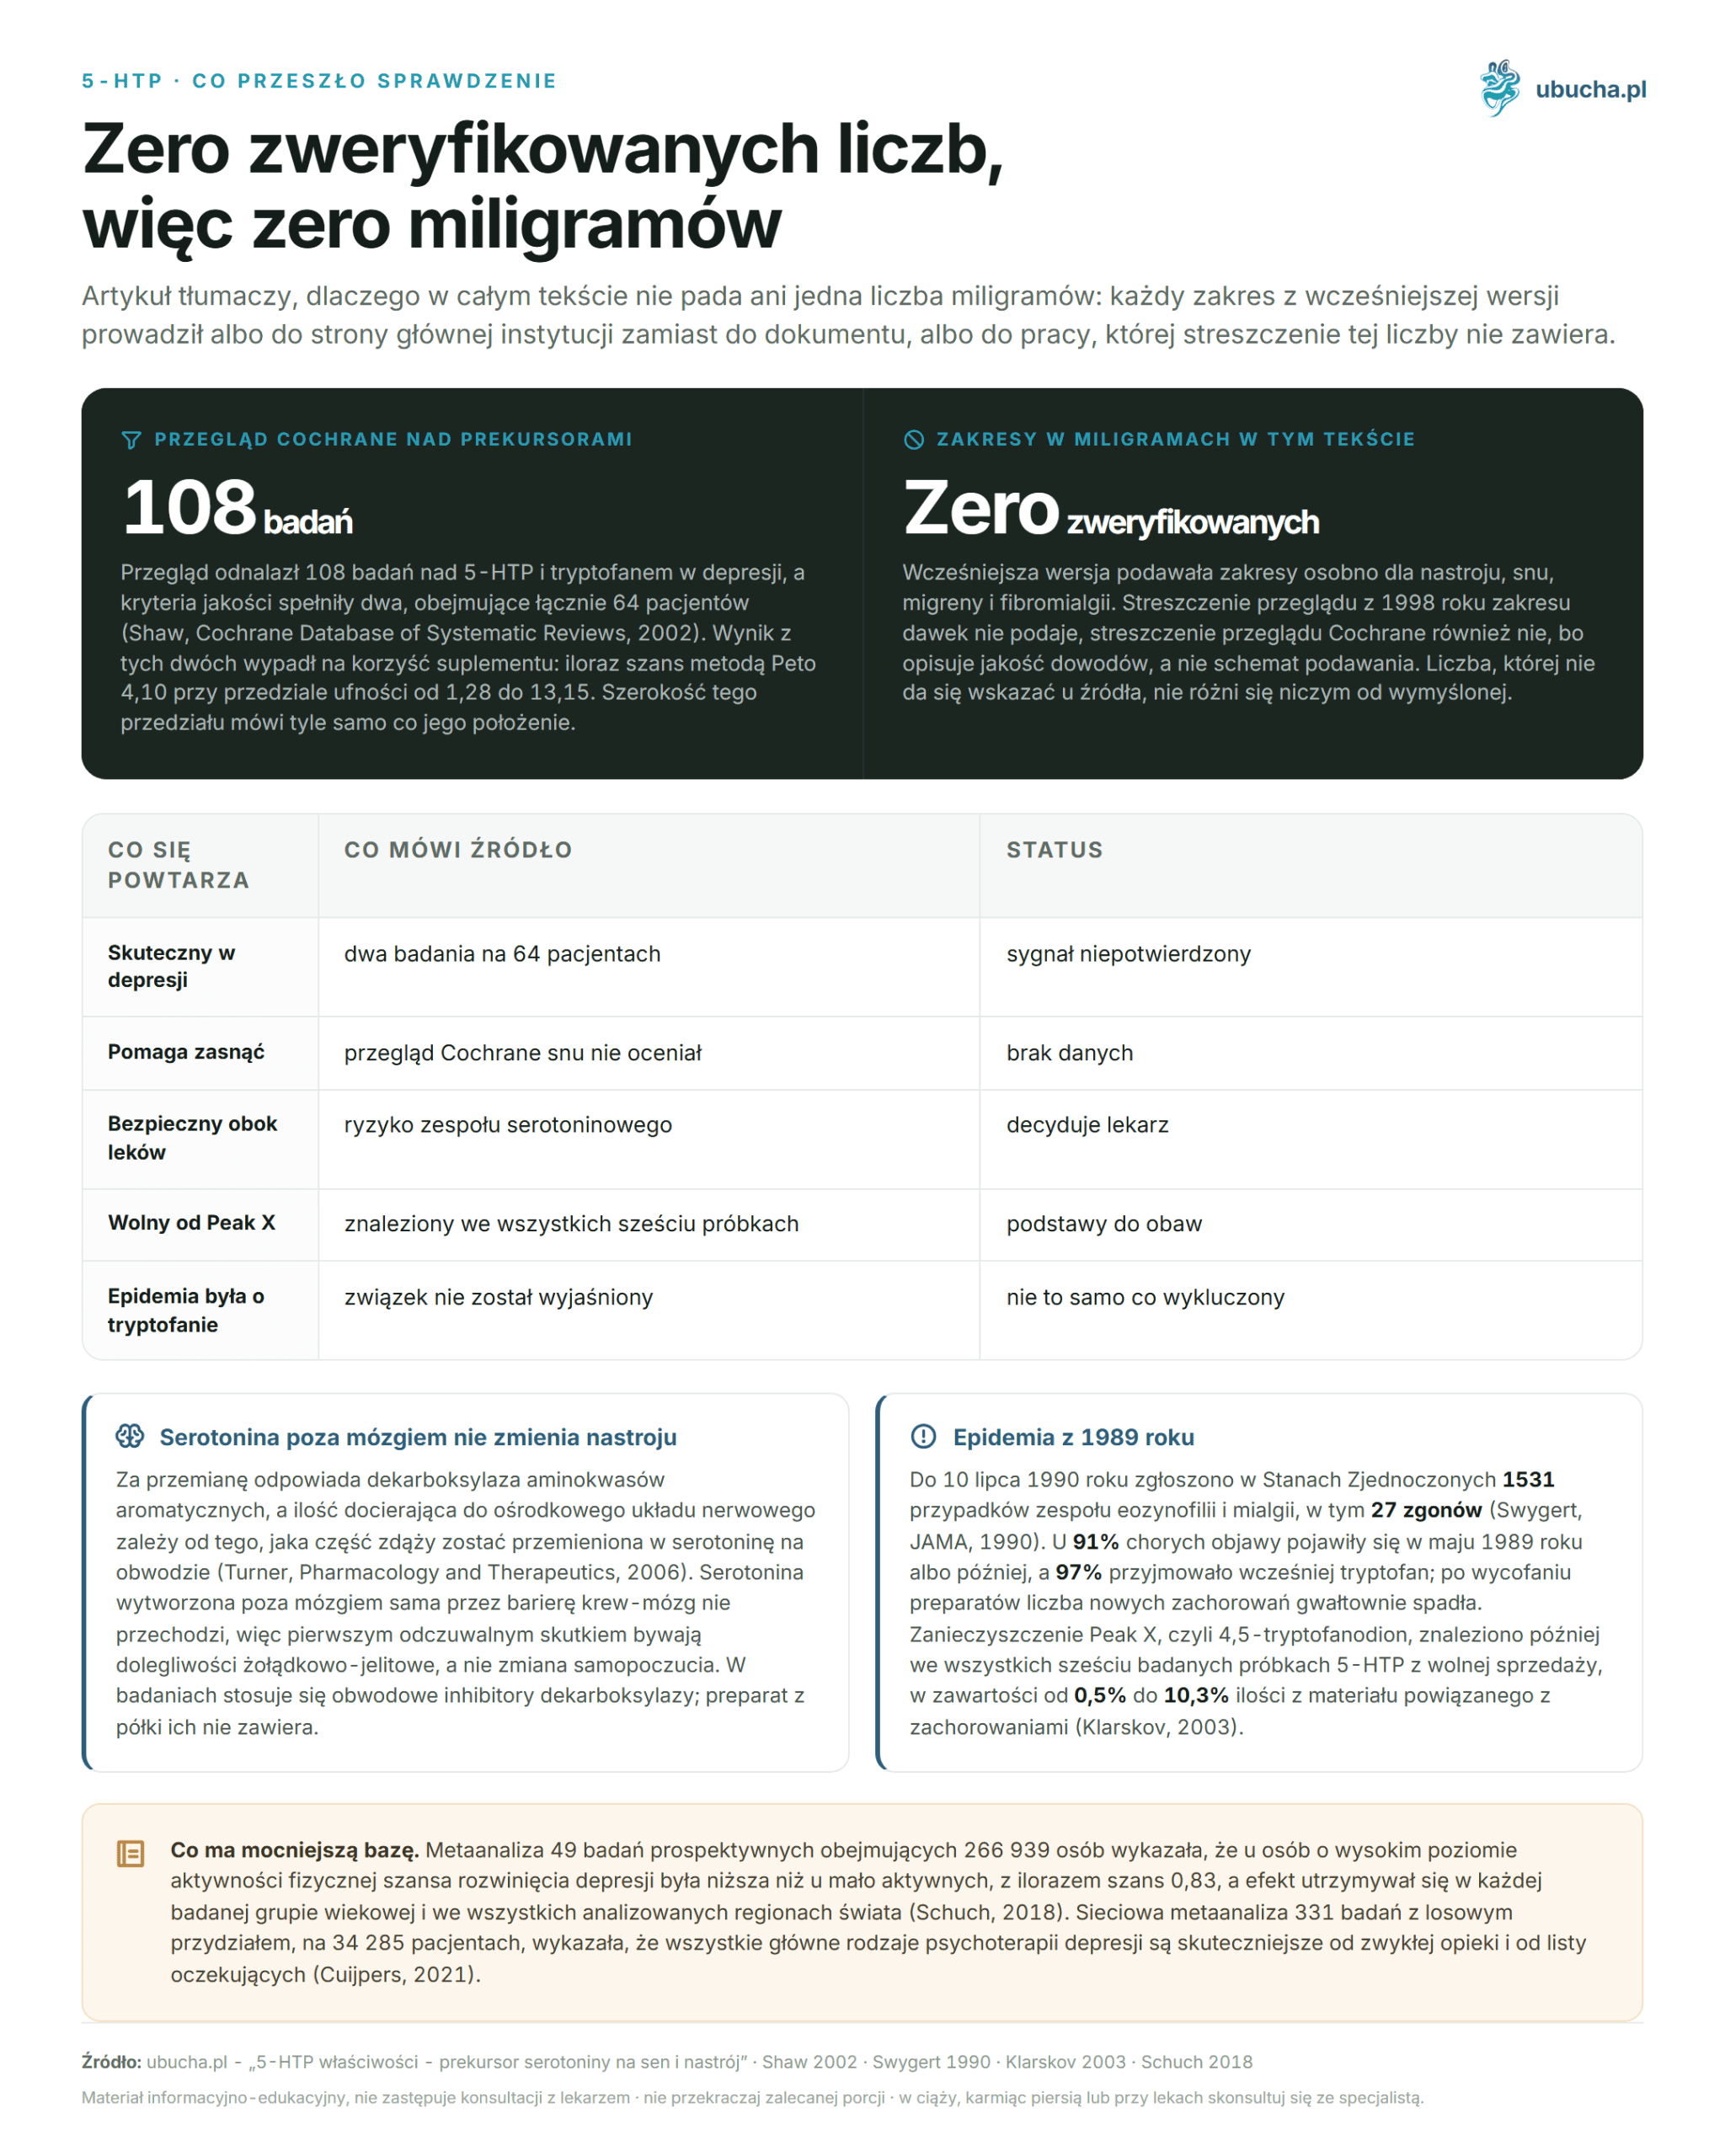
5-HTP, or 5-hydroxytryptophan, is sold as a natural support for mood and sleep because it is a direct precursor to serotonin. The mechanism is indeed simple and well described. The evidence base looks much worse: the Cochrane review found 108 studies on 5-HTP and tryptophan in depression, and only two met methodological quality criteria, involving a total of 64 patients. Additionally, there is a risk that cannot be overlooked in consumer text: combining 5-HTP with serotoninergic drugs risks serotonin syndrome, and the history of this molecule touches on an epidemic caused by contaminated raw material, which in 1989 cost the lives of dozens of people. Below, we separate what has been measured from what is repeated, and explain why we do not provide a recommended dose. Milligrams are mentioned in this text only where we describe the protocol of a specific study.
KEY INFORMATION
- The Cochrane review found 108 studies on 5-HTP and tryptophan in depression, but only two met quality criteria, involving a total of 64 patients (Shaw, Cochrane Database of Systematic Reviews, 2002).
- The authors of this review state directly that since there are drugs with proven efficacy and safety, the clinical utility of 5-HTP remains limited today.
- Serotonin syndrome is a potentially life-threatening condition caused by excessive stimulation of serotoninergic receptors, classically through the combination of two drugs with different mechanisms (Volpi-Abadie, Ochsner Journal, 2013).
- In 1989, an epidemic of eosinophilia-myalgia syndrome due to contaminated tryptophan involved 1531 reported cases, including 27 deaths (Swygert, JAMA, 1990).
- This text does not provide a recommended dose to the reader. The only milligrams mentioned come from the protocol of the cited study, and below we explain why we have no source for a recommended number.
What is 5-HTP and where does it come from?
5-HTP is an intermediate product of the conversion of the amino acid L-tryptophan to serotonin. It is formed from tryptophan by the addition of a hydroxyl group and then undergoes decarboxylation to serotonin. As a supplement, it bypasses the first step of this pathway, which is the reaction catalyzed by tryptophan hydroxylase, which limits the rate of the entire pathway (Birdsall, Alternative Medicine Review, 1998).
Two features distinguish it from tryptophan itself, and these are behind the popularity of this molecule. The absorption of 5-HTP from the intestine does not require a transport molecule and does not depend on the presence of other amino acids, so the preparation can be taken with a meal without loss of effectiveness. Tryptophan, on the other hand, can be directed towards the production of niacin or incorporated into protein, and 5-HTP does not have that possibility.
The commercial raw material comes from the seeds of the African shrub Griffonia simplicifolia. Chemical analysis of the seeds using HPLC with mass detection confirms that 5-HTP is the most abundantly represented compound in them, followed by the beta-carboline alkaloid griffonine and other alkaloids (Vigliante, Molecules, 2019).
This same work describes why it was created: to provide a method for unequivocal identification of commercial seeds. The authors combined chemical analysis with DNA profiling, obtaining a restriction pattern that allows confirmation that the raw material comes from the correct plant. The existence of such a tool speaks for itself about the state of the herbal raw materials market.
How does the body convert 5-HTP into serotonin?
Through a single enzymatic reaction, but the location where it occurs determines everything. The conversion is carried out by aromatic amino acid decarboxylase, and the amount of 5-HTP reaching the central nervous system depends on how much of it has been converted to serotonin in the periphery before crossing the blood-brain barrier (Turner, Pharmacology and Therapeutics, 2006).
This distinction has a consequence that is lost in product descriptions. Serotonin produced outside the brain does not affect mood because it cannot cross the blood-brain barrier. It acts in the gastrointestinal tract and in the circulatory system, which explains why the first noticeable effect of 5-HTP may be gastrointestinal discomfort rather than a change in mood.
In studies on this phenomenon, peripheral decarboxylase inhibitors, such as carbidopa, are used, which block the conversion outside the brain and thus increase the pool reaching the central nervous system. A supplement bought off the shelf does not contain such an inhibitor, so part of the dose taken never reaches where it should act.
How much of it reaches is not precisely known. A review from 1998 states that about 70% of the oral dose reaches the bloodstream and that 5-HTP easily crosses the blood-brain barrier, increasing serotonin production in the central nervous system. Serotonin itself regulates sleep, mood, anxiety, appetite, body temperature, and pain perception, so raising its pool is not a pinpoint action.
It is also worth knowing what happens to tryptophan before it even becomes 5-HTP. Besides tryptophan hydroxylase, two other enzymes compete for the same amino acid: 2,3-dioxygenase of indoleamine and 2,3-dioxygenase of tryptophan. They direct tryptophan down a completely different metabolic pathway, and their activity increases, among other things, in inflammatory states.
This is where the argument for supplementing 5-HTP instead of tryptophan comes from. Administering ready 5-HTP bypasses all this competition. However, it does not bypass the peripheral decarboxylation described above, so one bottleneck replaces another, and a review discussing the factors influencing each of these enzymes points this out as an area requiring attention.
What do studies on 5-HTP in depression really show?
That there is a signal, but the evidence base beneath it is crumbling. The Cochrane review searched databases for randomized studies comparing 5-HTP or tryptophan with placebo in people with unipolar depression and dysthymia. It found 108 studies. Only two had sufficient quality to meet inclusion criteria, involving a total of 64 patients (Shaw, Cochrane Database of Systematic Reviews, 2002).
The result from these two studies favored the supplement: the odds ratio using the Peto method was 4.10 with a confidence interval from 1.28 to 13.15, and the number of patients needed to treat for one additional effect was 2.78. The width of this interval says as much as its position. With 64 people, the estimate is shaky.
The authors’ conclusions are two, and both are worth knowing. The first: a large number of studies seemingly relates to the posed question, but few are reliable enough to depend on. The second, sharper: since there are antidepressants with proven efficacy and safety, the clinical utility of 5-HTP and tryptophan remains limited today.
So where does the optimism circulating in the market come from? From Birdsall’s review from 1998, describing 5-HTP as a clinically effective serotonin precursor and listing depression, fibromyalgia, binge eating in obesity, chronic headaches, and insomnia as conditions in which administering 5-HTP proved effective. These two sources are not contradictory. Birdsall shows a signal, Cochrane shows that the signal has not been confirmed by modern-class studies.
There is one more detail in this review that rarely makes it into market summaries and changes the interpretation of the result. Due to the small number of included studies, the authors had to combine the analysis for 5-HTP and tryptophan into one. The favorable result therefore does not pertain solely to 5-HTP, but to both precursors treated together.
The review was conducted rigorously, making its result harder to dismiss. Studies were sought in general and specialized databases, bibliographies of related works were reviewed, industry journals were manually searched, and authors were contacted, with publications sought in all languages. The quality of the studies was assessed for the risk of systematic error. With such effort, filtering down to two works is not a result of oversight but a state of the literature.
Does 5-HTP help with sleep?
The honest answer is: we do not have good data on this. The Cochrane review, which is the sharpest available filter here, concerned only depression, so it did not assess sleep at all. Insomnia does appear on the list of conditions mentioned by Birdsall as those in which administering 5-HTP proved effective, and that is all the material we have here (Birdsall, Alternative Medicine Review, 1998).
That is too little to make a statement about effectiveness. The 1998 review summarizes older literature, mostly from before the era of rigorous double-blind studies, and in the same field, a newer Cochrane review showed how small a portion of such contributions withstands stricter criteria. Assuming that it would be different for sleep has no basis.
It is worth understanding how 5-HTP differs from melatonin, as these two substances are often compared as substitutes. Melatonin is produced from serotonin in the pineal gland and is a ready signaling molecule acting on its own receptors. 5-HTP is a substrate, lying two steps earlier in the transformation, and its effect on sleep depends on what the body does with that substrate. We discuss this separately in the text about how melatonin works for sleep.
If you are looking for sleep support, this distinction is practical. A substance with a documented mechanism and studies on a specific application ranks higher than a substance whose mechanism is described, but application is poorly studied. Persistent insomnia for months is, after all, a reason to visit a doctor, not to shop.
What is known about 5-HTP in fibromyalgia?
This is the best-documented area, although here too we are talking about two works from the same team over thirty years ago. The first was a double-blind placebo-controlled study involving 50 patients with primary fibromyalgia syndrome and showed significant improvement in all assessed clinical parameters with only mild and transient adverse effects. The authors themselves concluded that further controlled studies are needed (Caruso et al., 1990).
The second work is often misquoted, and it is worth correcting this because the difference is fundamental. It was not a placebo trial on two hundred patients, but an open-label study on 50 individuals lasting 90 days. All assessed variables, including the number of tender points, anxiety, pain intensity, sleep quality, and fatigue, improved significantly compared to baseline values. Improvement rated as good or sufficient was noted in nearly half of the patients, and adverse effects were reported by 15 individuals, or 30% of the group (Sarzi Puttini and Caruso, 1992).
The lack of a control group in this second work changes the weight of the result. In chronic pain, the response to placebo can be high, so improvement from baseline does not prove the action of the substance. The percentages of pain reduction circulating online from comparisons with placebo come from a study that did not include such a comparison.
Does 5-HTP prevent migraines and reduce appetite?
In migraine prevention, there is one large comparative study. It involved 124 individuals with migraines, randomly assigned to 5-HTP or methysergide, a drug used for prophylaxis at that time. Significant improvement was noted in 75% of patients on methysergide and 71% on 5-HTP, with fewer adverse effects in the latter group. An important detail that usually gets lost in summaries: the benefit from 5-HTP primarily concerned the severity and duration of attacks, not their frequency (Titus et al., Eur Neurol, 1986).
Regarding appetite, the work from the American Journal of Clinical Nutrition is most often cited. Twenty obese patients were randomly assigned to 5-HTP at a dose of 900 mg per day or to placebo, in a double-blind setup, over two consecutive six-week periods. In the first, no diet was recommended, while in the second, a diet of 5040 kJ per day was recommended. Significant weight loss was observed in the 5-HTP group during both periods, along with reduced carbohydrate intake and consistently reported early feelings of satiety (Cangiano et al., 1992).
This is the dose from the protocol of the obesity study, not a guideline for someone reaching for a preparation for mood or sleep. The authors of this study noted good tolerance. However, the group consisted of only twenty individuals, and the study is over thirty years old and has not seen large replication. It is a promising result, not a settled one.
Why should 5-HTP not be combined with antidepressants?
Because it risks serotonin syndrome, a potentially life-threatening condition. It is caused by excessive stimulation of peripheral and central postsynaptic 5-HT1A receptors, and primarily 5-HT2A. A characteristic picture emerges: disturbances in mental state, excessive neuromuscular excitability, and hyperactivity of the autonomic nervous system (Volpi-Abadie, Ochsner Journal, 2013).
The authors of this review describe three pathways to serotonin syndrome. It can occur with therapeutic use of serotoninergic drugs alone, from intentional overdose, but classically arises from the complex interaction of two serotoninergic substances acting through different mechanisms. The last scenario precisely describes the situation where someone adds a supplement to ongoing pharmacotherapy.
This risk is explicitly mentioned in the literature on 5-HTP itself. A pharmacological review dedicated to supplementation with this molecule discusses safety issues with particular emphasis on two: eosinophilia-myalgia syndrome and serotonin syndrome (Turner, Pharmacology and Therapeutics, 2006). This is not excessive caution, but two of the most frequently discussed hazards of this substance.
The practical rule is short and does not require a list of brand names. If you are taking any medication affecting serotoninergic transmission, the decision about 5-HTP is made by the attending physician or clinical pharmacist, not an internet forum. Do not stop taking your medication on your own to make room for the supplement. We discuss this group of interactions more broadly in the text about contraindications and serotonin syndrome.
The authors of the review point out something that speaks for this caution more strongly than a list of prohibitions. Many commonly used medications are responsible for serotonin syndrome, and the number of possible combinations that can trigger it is large. It is therefore difficult to assume in advance that our set of preparations is safe, as recognizing this threat can be difficult even for doctors.
The goal the authors set for their review is, in fact, to alert doctors to this syndrome, as it is potentially fatal yet avoidable. Proper knowledge and vigilance improve diagnostic accuracy and allow for early treatment implementation. For the reader, this means one thing: discussing the supplement with someone who knows the entire list of medications they are taking is not a formality.
Does chronic use deplete dopamine?
This is a hypothesis, not a determination, but based on real biochemistry. The enzyme converting 5-HTP to serotonin, namely aromatic amino acid decarboxylase, is the same enzyme that converts L-DOPA to dopamine. Saturating it with one substrate may theoretically limit the processing of the other, and the result would be a decrease in drive and motivation, i.e., symptoms resembling what the supplement was supposed to improve.
Concrete ratios have grown around this hypothesis, such as the recommended ratio of 5-HTP to tyrosine. They have no basis in clinical studies in humans, so we do not provide them. This is biochemical speculation that some authors transfer to practice faster than the data allow, and the reader receives it in the form of a ready number, without seeing that reasoning, not measurement, stands behind it.
The practical conclusion is unequivocal and does not require resolving this hypothesis. Chronic intake of a substance interfering with monoaminergic transmission requires medical supervision, especially in individuals with Parkinson’s disease and those taking dopaminergic medications. We discuss the other side of the same pathway in the article about mucuna and dopamine.
What was the eosinophilia-myalgia syndrome?
An epidemic from 1989 that permanently changed the status of serotonin precursors in the supplement market. Eosinophilia-myalgia syndrome was diagnosed based on debilitating muscle pain and an absolute eosinophil count of at least one billion cells per liter of blood. By July 10, 1990, 1531 cases had been reported in the United States, including 27 deaths (Swygert, JAMA, 1990).
The disease picture was multi-organ. The most common symptoms included joint pain in 73% of patients, rash in 60%, cough or shortness of breath in 59%, and peripheral edema in 59%. Elevated aldolase levels were noted in 46%, abnormal liver function tests in 43%. Neuropathy or nerve inflammation occurred in 27%, leading to paralysis and death in some patients. In 21% of those undergoing chest radiography, abnormalities were found.
Cases were not evenly distributed. The highest rates were recorded in western states, and 68% of patients were white women of non-Latino descent, aged 35 and older. Such a profile, clearly deviating from the distribution in the general population, itself directed suspicion towards a specific product consumed by a defined group.
The link to the preparation was clear. In 91% of patients, symptoms appeared in May 1989 or later, and 97% had previously taken tryptophan. After the withdrawal of tryptophan products from free sale in November 1989, the number of new cases dropped sharply, which in itself is a strong argument for causality.
This story concerns tryptophan, not 5-HTP, and this distinction is often used in marketing materials as an argument that 5-HTP is not related to the episode. The Cochrane review from 2002 states this more cautiously: a possible link between these substances and the potentially fatal eosinophilia-myalgia syndrome has not been clarified. However, unclarified is not the same as excluded.
Are today’s 5-HTP preparations free from contamination?
The study that checked this answered alarmingly. Researchers determined the chemical structure of a contaminant labeled as Peak X, previously found in 5-HTP preparations associated with cases of eosinophilia-myalgia syndrome. It turned out to be 4.5-tryptophanodione, a compound considered a potential neurotoxin (Klarskov, The Journal of Rheumatology, 2003).
However, the second part of this result is the most important. The substance was found not only in materials associated with illnesses but in all six tested samples of 5-HTP available for free sale. Its content in these samples ranged from 0.5% to 10.3% of the amount present in materials associated with disease cases.
The authors’ conclusion is stated plainly: this gives some basis for concern regarding the safety of such commercial 5-HTP preparations. We have noticed that in Polish-language descriptions of this issue, this statement is often reversed into a reassuring message, such as “today reputable suppliers test the raw material for the presence of Peak X.” The work they refer to does not say anything like that.
The methodology of this work deserves attention because it explains why the result is difficult to dispute. Samples were subjected to high-precision mass spectrometry coupled with liquid chromatography and electrochemical detection, a reaction with reduced glutathione was performed, and the obtained spectra were compared with the spectra of the standard 4.5-tryptophanodione. Identification is therefore not based on retention time similarity but on comparison with a standard substance.
What this work does not resolve? It studied samples available at the time of its creation, so it does not answer the question about today’s supply chains. This is a real gap, not an evasion: we did not find a newer study that repeated this measurement on the current market. An analysis certificate for a specific batch is in this situation not so much an addition as the only information the buyer can receive.
Why won’t you find a recommended dose in this text?
Because after checking the sources, not a single one could be recommended. An earlier version of this article provided several ranges in milligrams, separately for mood, sleep, migraine, and fibromyalgia, along with a detailed starting protocol. Each of these ranges led either to the homepage of the institution given instead of a specific document or to a work whose summary does not contain any of those numbers.
We checked this sequentially. The summary of Birdsall’s 1998 review does not provide a range of doses. The summary of the Cochrane review from 2002 also does not provide them, as it describes the number of studies and the quality of evidence, not the administration scheme. So there are zero verified ranges that could be recommended to anyone. The dose used in a study is different from the dose recommended to the reader. The former is provided along with the work in which it appeared. A recommended number without confirmation from the source is no different from an invented one.
The second reason is more serious than the lack of data. A dose given to a reader who is concurrently taking a serotoninergic medication is an invitation to exactly the interaction this article warns against. With a substance whose main documented risk is a reaction to a combination with a drug, a number in the text works against the intention.
What to do about this in practice? If you are considering 5-HTP, determine the portion size with your doctor or pharmacist, having with you a list of everything you take regularly, including over-the-counter preparations. This is the same conversation that will also catch contraindications, so it is not an additional obstacle but the only sensible first step.
What else affects mood and sleep?
Things with a clearly stronger evidence base than any serotoninergic supplement. A meta-analysis of 49 prospective studies involving 266,939 individuals observed for a total of over 1.8 million person-years showed that individuals with high levels of physical activity had a lower chance of developing depression than those with low activity, with an odds ratio of 0.83 (Schuch, The American Journal of Psychiatry, 2018).
The protective effect persisted in every age group studied: among youth, adults, and older individuals, as well as in all analyzed regions of the world. The authors did not identify any factor that modified it. This is a rare situation in epidemiology and says more than a single interventional study.
The authors also checked the robustness of their result. The relationship persisted separately for positive screening results for depressive symptoms and separately for the diagnosis of severe depression, and the quality of the included studies was assessed as moderate to high. A significant publication bias was detected, but after accounting for it, the strength of the association did not change.
On the treatment side, the picture is equally clear. A network meta-analysis of 331 studies with random assignment, involving 34,285 patients, showed that all major types of psychotherapy for depression are more effective than usual care and waiting lists, and individual methods do not differ significantly from each other, with one exception (Cuijpers, World Psychiatry, 2021). Most of them maintained a significant effect even after twelve months of follow-up.
The range of effect size compared to usual care ranged from 0.81 standard deviations for life review therapy to 0.32 for nondirective supportive counseling, and the results did not change after limiting the analysis to studies with low risk of systematic error. With one exception, the methods did not differ from each other, so the choice may depend on availability and patient preference.
A supplement will not replace either of these two things, and it is worth stating this clearly before adding another jar to the shelf. If you are still looking for preparations supporting the nervous system, you can find their review in the supplements category, but treat them as a complement to approaches that have stronger evidence.
What does this mean?
5-HTP has a simple mechanism and a weak evidence base, and this combination fosters promises. The molecule indeed bypasses the rate-limiting step of serotonin synthesis and indeed crosses the blood-brain barrier. However, this does not imply a clinical effect, as the question of whether there is a clinical effect lies between a correct mechanism and proven action, and studies answer that question, not a pathway scheme.
The answer from studies is known and uncomfortable. Of the 108 works found by the Cochrane review, only two passed the quality assessment, involving 64 patients. The result was favorable, the confidence interval very wide, and the authors’ conclusion unequivocal: given the existence of drugs with proven efficacy, the clinical utility of this substance remains limited today.
On the risk side, we have two positions, and both are concrete. Combining with a serotoninergic drug risks serotonin syndrome, which can be life-threatening. Contamination with Peak X was found in all six tested samples from free sale, and the authors of this work called it a basis for concern, not a historical curiosity.
The practical conclusion is therefore less flashy than a dose table, but it is true. If you are struggling with low mood or insomnia lasting for weeks, the first step leads to a doctor, not a store. If you still want to try 5-HTP, do so after discussing it with your doctor or pharmacist, with a complete list of medications you are taking in hand. In case of suicidal thoughts, call 116 123, and in an emergency, call 112.
Frequently asked questions
What is 5-HTP and why is it called a serotonin precursor?
It is an intermediate product of the conversion of L-tryptophan to serotonin. As a supplement, it bypasses the first step of this pathway, which is the reaction catalyzed by tryptophan hydroxylase, which limits the rate of the entire pathway, and provides a ready substrate for aromatic amino acid decarboxylase (Birdsall, Alternative Medicine Review, 1998).
Can 5-HTP be combined with antidepressants?
Not on your own. Serotonin syndrome classically arises from the interaction of two serotoninergic substances acting through different mechanisms and is a potentially life-threatening condition (Volpi-Abadie, Ochsner Journal, 2013). The decision to combine them is made by the attending physician or clinical pharmacist.
Does 5-HTP work for depression?
The Cochrane review found 108 studies, of which only two met quality criteria, involving 64 patients. The result favored the supplement, but the authors deemed the evidence insufficient to be conclusive and pointed to the existence of drugs with proven efficacy (Shaw, Cochrane Database of Systematic Reviews, 2002).
How much 5-HTP should be taken?
We do not provide a recommended dose because we have no source for it. Summaries of both main reviews on which knowledge about this molecule is based do not provide a range of doses, and a recommended number without confirmation from the source is no different from an invented one. Milligrams mentioned in this article describe the protocol of the cited study and are not a guideline for the reader. Determine the portion size with your doctor or pharmacist.
What was the eosinophilia-myalgia syndrome?
An epidemic from 1989 due to contaminated tryptophan. By July 10, 1990, 1531 cases had been reported, including 27 deaths, and after the withdrawal of products from free sale in November 1989, the number of new cases dropped sharply (Swygert, JAMA, 1990).
Are commercial 5-HTP preparations pure?
The study that checked this found contamination with Peak X, or 4.5-tryptophanodione, in all six tested samples available for free sale, in amounts ranging from 0.5% to 10.3% of the content in materials associated with illnesses. The authors considered this a cause for concern (Klarskov, The Journal of Rheumatology, 2003).
How does 5-HTP differ from melatonin?
Melatonin is produced from serotonin and is a ready signaling molecule acting on its own receptors. 5-HTP is a substrate lying two steps earlier in the transformation, so its effect depends on what the body does with that substrate. This is the difference between a final product and a raw material.
This article is for informational and educational purposes only and does not constitute medical advice. Before starting supplementation, consult your doctor, especially if you are taking medications regularly, are pregnant or breastfeeding, or have chronic illnesses.
Author: Michał Waluk · Published: 2026-05-11 · Updated: 2026-09-22