
Acetyl-L-Carnitine ALCAR - benefits, dosage and risks 2026
ALCAR for memory, energy, and regeneration. We check what studies confirm about depression, neuropathy, and dementia, and what the supplement does not do.
Acetyl-L-carnitine, abbreviated ALCAR, is sold in Poland as a supplement for memory, mental energy, and nervous system regeneration. Each of these three claims has a different level of evidence, and two look quite different when examining the studies cited by product descriptions. This text was created after verifying all six scientific identifiers that were in the previous version of the article. Three led to studies in completely different fields, and one to a publication unknown to the Europe PMC database. Below you will find what remains after this verification: four studies and two meta-analyses, described with the actual numbers they contain, and one study that ends with a warning.
KEY INFORMATION
- A meta-analysis of 12 studies with 791 participants showed a significant reduction in depression symptoms compared to placebo, and a comparable result to antidepressants with fewer side effects (Veronese, Psychosomatic Medicine, 2018).
- In a study on diabetic neuropathy with 1257 people, nerve fiber regeneration and vibration sensation improved, but nerve conduction velocity did not improve at all (Sima, Diabetes Care, 2005).
- A Cochrane review found no evidence of cognitive function improvement in dementia (Hudson, Cochrane, 2003).
- In a study of 409 women treated with taxanes, ALCAR worsened neuropathy after 24 weeks, and the authors advise against supplements without proven efficacy (Hershman, JCO, 2013).
- Carnitine inhibits thyroid hormone entry into the cell nucleus, which is relevant when treated with levothyroxine (Benvenga, Thyroid, 2000).
What is ALCAR and how does it differ from L-carnitine?
ALCAR is L-carnitine with an attached acetyl group. Carnitine itself is a natural compound present in all mammalian tissues at millimolar concentrations, and the body obtains it by two routes: endogenous synthesis and from food, mainly meat and dairy (Longo, Biochim Biophys Acta, 2016).
The practical difference between the two forms concerns where they go and why. Carnitine in free form or bound to tartaric acid is mainly used in the context of muscles and physical effort. Researchers studying the nervous system choose ALCAR because the molecule is widely distributed in mammalian tissues, including the brain, the blood-brain barrier, neurons, and astrocytes (Sergi, Aging Clin Exp Res, 2018).
The acetyl group is not just decoration. After detachment, it enters cellular metabolism as an acetate residue, serving as material for energy transformations and neurotransmitter synthesis. That is why all the studies below on mood, memory, and peripheral nerves use this form, not the common carnitine tartrate known from sports stores.
One terminological note that saves money when purchasing. The names L-carnitine, L-carnitine tartrate, propionyl-L-carnitine, and acetyl-L-carnitine denote different molecules with different uses. If the reason for purchase is anything discussed in this article, the label must say acetyl-L-carnitine. None of the described studies tested the other forms for these indications.
How does the carnitine pendulum work?
Carnitine is responsible for one strictly defined task: transporting long-chain fatty acids across the inner mitochondrial membrane so they can be burned in beta-oxidation (Longo, Biochim Biophys Acta, 2016). Without this transport, fat will not enter the site where energy is produced, regardless of how much is in the blood.
Carnitine enters the cell via the OCTN2 transporter, a high-affinity protein specialized in this single task. The kidneys reclaim it from urine by the same mechanism, saving the body a resource whose synthesis is costly. At pharmacological doses, carnitine enters cells additionally via an amino acid transporter called B0 plus, and this observation has clinical significance, as explained below.
This description reveals an important limitation rarely found on packaging. Transport is a necessary condition for fat oxidation but not its regulator in a healthy person. If there is no carnitine deficiency in the cell, adding more will not speed anything up because the bottleneck is not transport but energy demand.
Therefore, the statement about increased mitochondrial energy after supplementation is a shortcut that misleads. It only makes sense where carnitine is truly deficient. When that is the case, the next section describes it.
When is carnitine deficiency real?
Primary carnitine deficiency is a genetic disease, not a dietary state. It is caused by mutations in the OCTN2 transporter encoded by the SLC22A5 gene, inherited autosomal recessively. The result is reduced carnitine accumulation in cells, increased loss in urine, and low serum concentration (Longo, Biochim Biophys Acta, 2016).
The clinical picture depends on age. In young children, the disease manifests as hypoglycemia without ketone bodies and hepatic encephalopathy. Later, skeletal and cardiac myopathy or sudden death due to arrhythmia may occur, usually triggered by fasting or catabolic state. Diagnosis is based on low free carnitine concentration in newborn screening and confirmed by uptake measurement in fibroblasts or gene sequencing.
The disease responds to oral carnitine, and this is the situation where supplementation has documented sense. It is managed by a metabolic specialist based on tests, not a decision made in an online store. Diagnoses in adults sometimes occur only after a healthy child’s screening shows very low carnitine levels.
For the average reader, the conclusion is simple and worth remembering. Fatigue, brain fog, and reduced exercise tolerance almost never result from carnitine deficiency. Much more often, anemia, vitamin B12 or iron deficiency, hypothyroidism, sleep apnea, and depression are responsible. All these causes can be checked by tests, and each has treatment more effective than any supplement.
What does ALCAR do in the nervous system?
Several mechanisms have been described, and it is worth noting that they come from preclinical studies, not patient measurements. ALCAR shows cytoprotective, antioxidant, and anti-apoptotic effects in the nervous system. It also acts analgesically by lowering glutamate concentration in synapses (Sergi, Aging Clin Exp Res, 2018).
The second group of effects concerns nerve repair. ALCAR facilitates regeneration and repair after primary injury, influences neuronal membrane synthesis and their fluidity and function, increases protein synthesis, and improves axonal transport of neurofilament and tubulin proteins. It also enhances the response to nerve growth factor, promoting neurite outgrowth.
The third group concerns cognitive functions and is the least established. A review on dementia mentions membrane and synaptic function restoration, cholinergic activity enhancement, support of mitochondrial energy metabolism, protection against toxins, and neurotrophic effects. However, the authors conclude that ALCAR’s role in dementia remains controversial (Pennisi, Nutrients, 2020).
This distinction between mechanism and effect is more important here than usual. The list of mechanisms looks impressive and is exactly how product descriptions present it. By itself, it does not say whether a patient will notice a difference. Clinical studies answer that, and they are much more modest.
Does ALCAR improve memory in dementia?
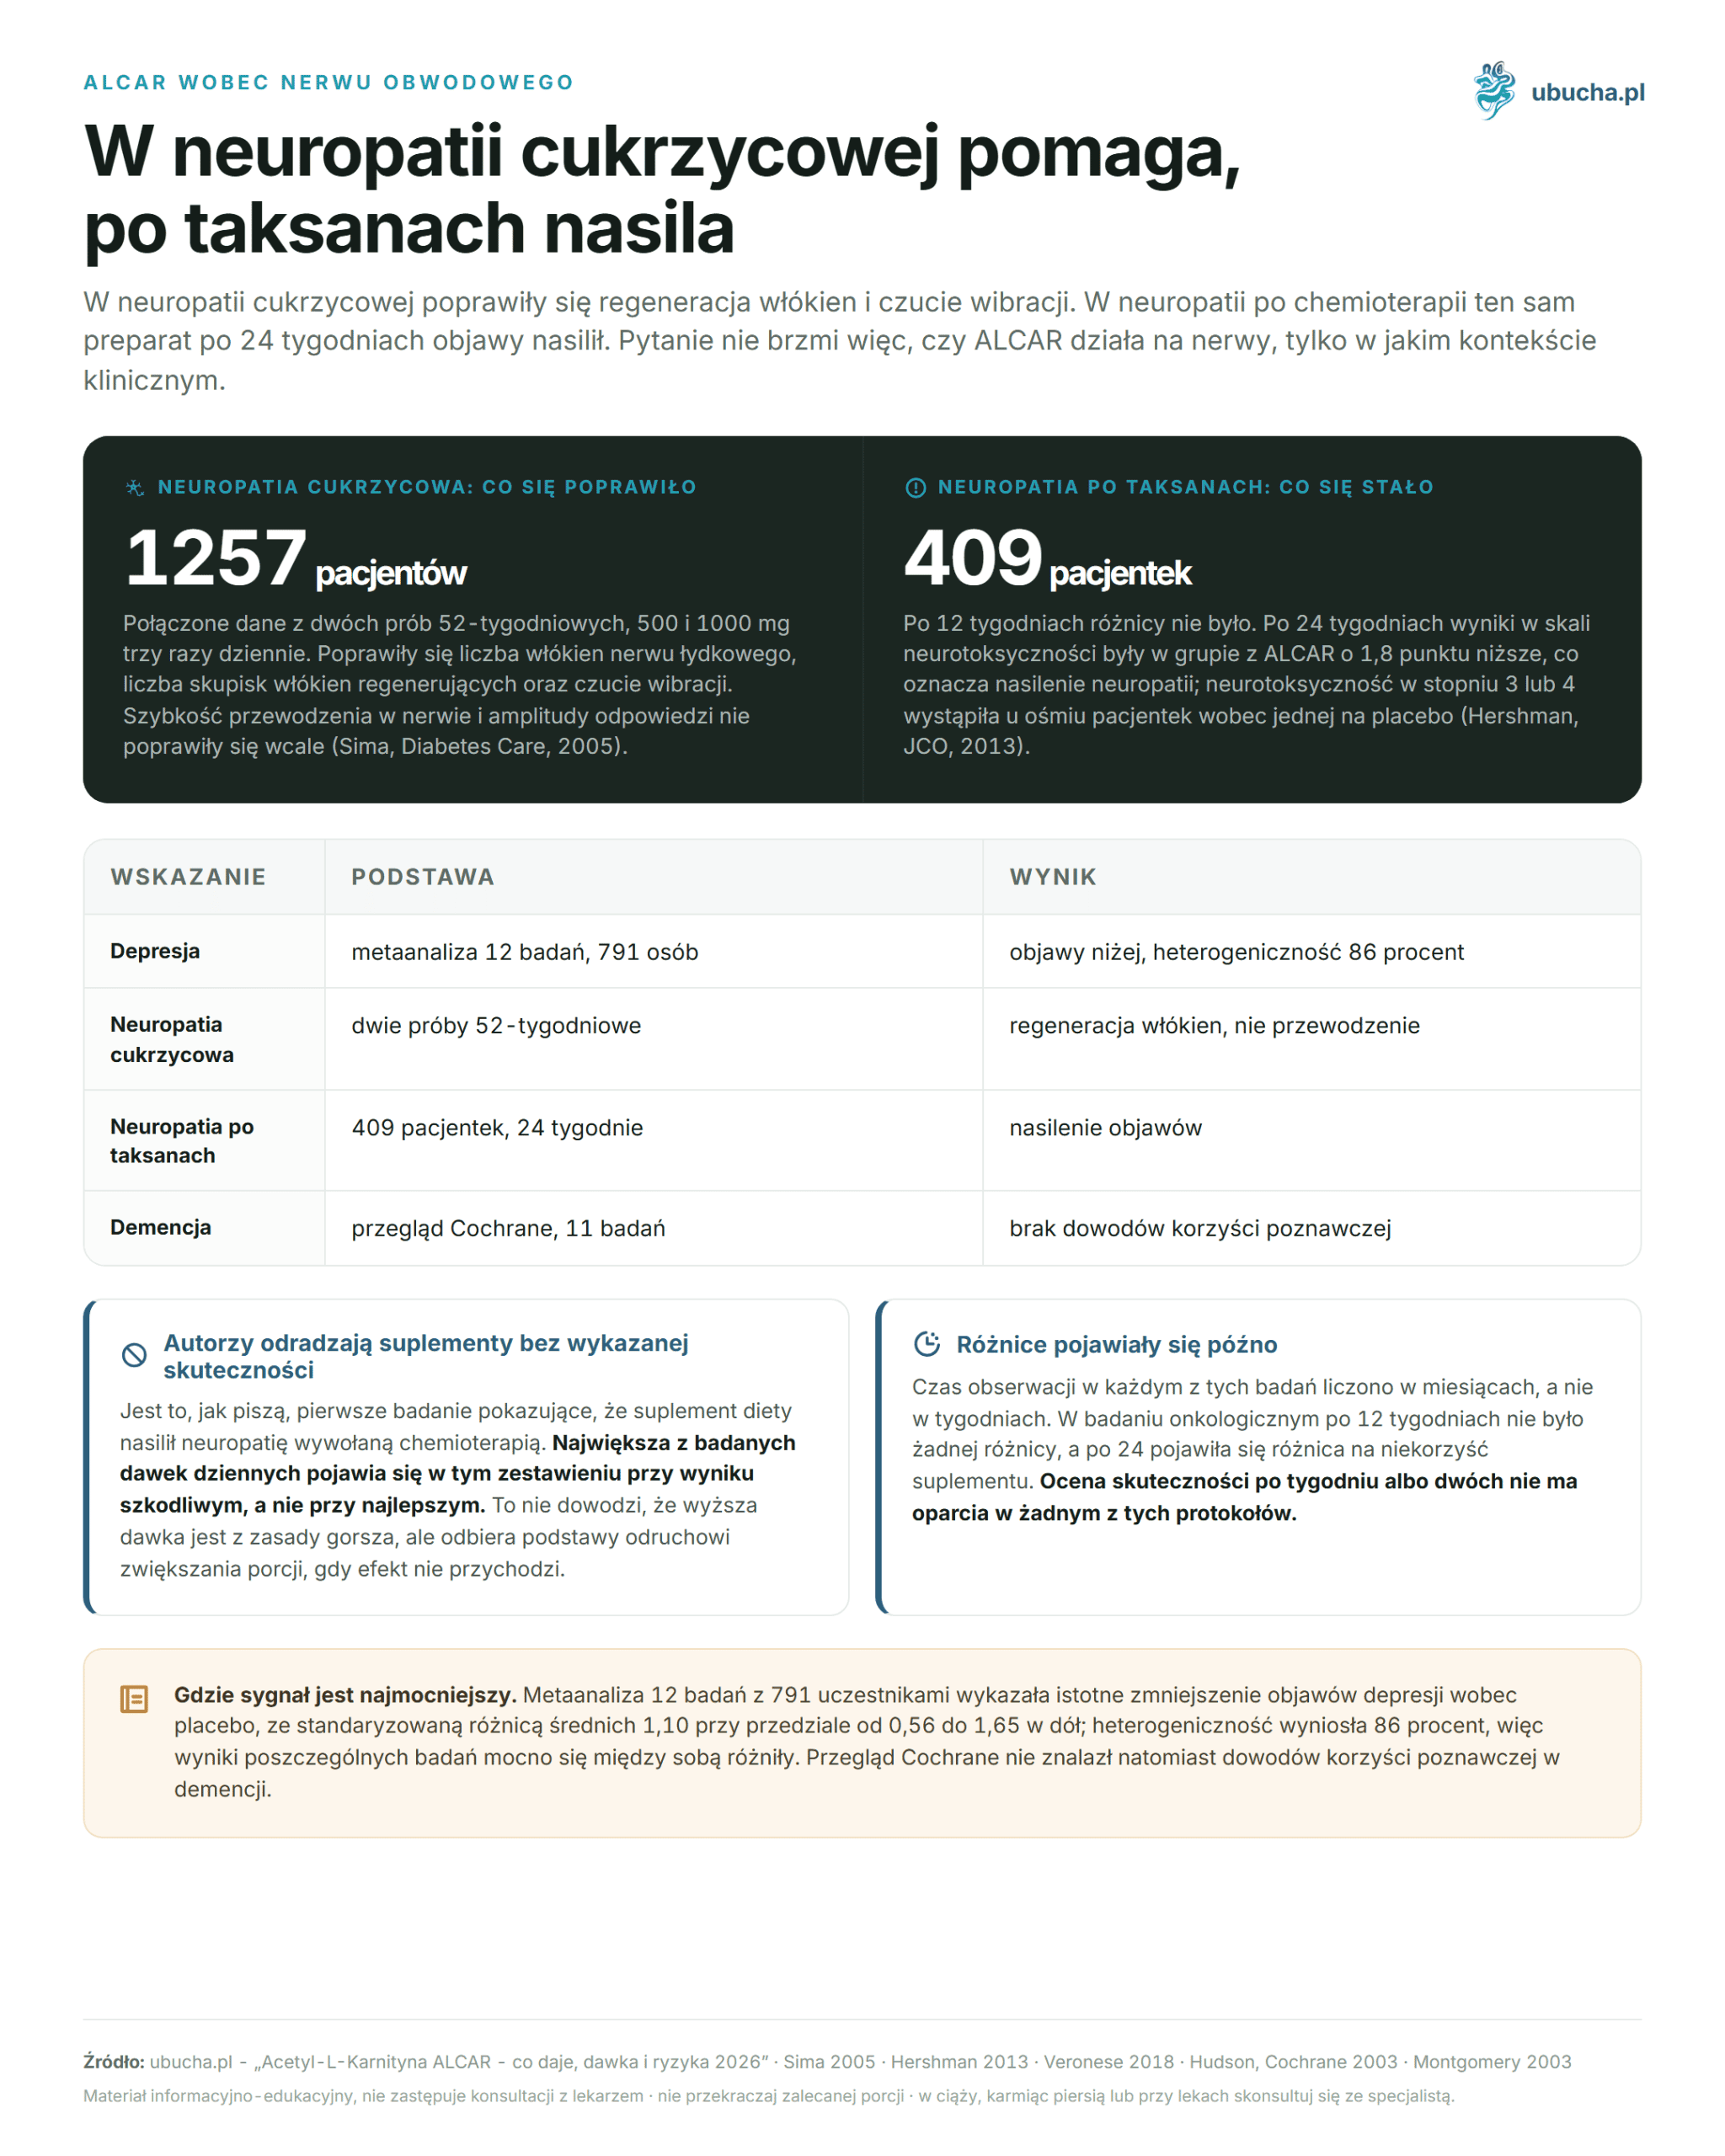
The best answer comes from a Cochrane systematic review covering 11 double-blind studies, all conducted in people with Alzheimer’s disease (Hudson, Cochrane, 2003). The result is much more cautious than supplement descriptions suggest.
Statistically significant differences favoring ALCAR appeared in the number of people rated as improved in global clinical assessment after 12 and 24 weeks. After 52 weeks, the difference disappeared. In other areas - cognitive functions, dementia severity, functional ability, and global clinical assessment treated as a continuous variable - no evidence of benefit was found.
The authors add a caveat worth quoting in full because it rarely spreads further. Given the large number of comparisons, the statistically significant result may be due to chance. Their final conclusion is that there is no evidence to justify routine ALCAR use in clinical practice and that available data do not suggest it will become an important drug.
Adverse events were reported variably, but the pooled analysis showed no significant differences between treated and placebo groups. This is the only good news from this review and concerns safety, not efficacy. The previous version of this article attributed moderate benefits on ADAS-Cog and MMSE scales to this review. That conclusion is not present in it.
Why did two 2003 analyses reach different conclusions?
Because they measured different things and calculated differently. In the same year the Cochrane review appeared, a meta-analysis of double-blind studies in people with mild cognitive impairment and early Alzheimer’s was published. Studies lasted 3, 6, or 12 months, and doses ranged from 1.5 to 3 g daily (Montgomery, Int Clin Psychopharmacol, 2003).
This analysis showed ALCAR’s advantage over placebo: the integrated effect size was 0.201 with a confidence interval from 0.107 to 0.295, and for global clinical change assessment 0.32 with a range from 0.18 to 0.47. Benefit was visible already at the first assessment after three months and increased over time. The preparation was well tolerated in all studies.
Where does the discrepancy come from? The Cochrane review included only Alzheimer’s patients and treated individual scales separately, analyzing data only from completers for some scales. The Montgomery meta-analysis also included mild cognitive impairment, an earlier stage, and combined different scales into one composite indicator. An effect size around 0.2 is small, less than usually considered noticeable by patients.
The practical conclusion is not that one analysis is right and the other wrong. It is that a signal exists but is weak, clearer in earlier stages and in composite clinical measures than in cognitive tests. A critical 2020 review ends in the same place, pointing to the need for studies with homogeneous samples before ALCAR enters systematic use (Pennisi, Nutrients, 2020).
Does ALCAR help with depression?
This is the strongest efficacy signal in the entire body of this molecule. A systematic review with meta-analysis covered 12 randomized controlled trials with a total of 791 participants averaging 54 years old, 65% of whom were women (Veronese, Psychosomatic Medicine, 2018). In eleven of these studies, ALCAR was given as monotherapy.
Data from nine studies including 231 people taking ALCAR versus 216 taking placebo and 20 without intervention showed a significant reduction in depression symptoms. The standardized mean difference was minus 1.10 with a confidence interval from minus 1.65 to minus 0.56. Heterogeneity was very high at 86%, meaning results varied greatly between studies.
Three studies compared ALCAR directly with antidepressants, with 162 people in each group. Efficacy was comparable, and adverse event frequency was significantly lower in the ALCAR group. Subgroup analysis indicated the preparation worked best in older people. The authors conclude that large studies are needed to confirm or refute these findings.
The previous version of this article attributed this meta-analysis to an author named Wang and the British Journal of Psychiatry, giving an effect size of minus 0.67 and faster action than reference drugs visible after a week or two. The number of participants and studies matched, but the rest did not. The work appeared in Psychosomatic Medicine, the effect size is clearly larger, and the meta-analysis says nothing about speed of action.
Is ALCAR deficiency a marker of depression?
This is a hypothesis explaining why supplementation works in some people and not in others. Researchers measured acetyl-L-carnitine levels in patients with major depression and in age- and sex-matched healthy controls at two independent centers (Nasca, PNAS, 2018).
Acetyl-L-carnitine levels were reduced in patients, while free carnitine levels remained unchanged. This distinction is important because it shows the issue concerns a specific form, not the overall carnitine pool in the body. Additional analyses showed that the depth of deficiency reflected both depression severity and age of onset.
The greatest reduction was found in treatment-resistant depression. In this group, low levels were predicted by childhood trauma, especially emotional neglect, and female sex. The authors propose this as a candidate biomarker identifying a depression subtype with earlier onset and greater severity.
However, it must be said clearly what this study does not show. It did not demonstrate that supplementing the deficiency improves patient condition, nor that measuring levels is available in routine diagnostics. It is a study about mechanism and direction for further research, not a basis for self-treatment. Depression remains a disease treated by psychiatrists, and medications should not be stopped in favor of supplements.
What did the largest study on diabetic neuropathy show?
Peripheral neuropathy is a common complication of diabetes, affecting up to 50% of older patients with the disease (Sergi, Aging Clin Exp Res, 2018). The largest study on ALCAR in this indication combined data from two 52-week placebo-controlled trials testing two doses, 500 and 1000 mg three times daily. The analysis included 1257 patients, 93% of those enrolled (Sima, Diabetes Care, 2005).
Two things measured directly in the nerve improved: the number of sural nerve fibers and the number of clusters of regenerating fibers. Vibration sensation also improved in both studies. Pain, the most troublesome symptom, decreased significantly in one study and in the combined group receiving the higher dose.
One thing did not improve, and this sentence is lost in product descriptions. Nerve conduction velocity and response amplitudes did not improve. The previous version of this article claimed the opposite, giving a 39% pain reduction versus 8% in placebo and greater benefits in people with shorter diabetes history. None of these numbers appear in the paper.
The conclusion for patients is moderately positive but requires honesty. The study suggests an effect on fiber regeneration and sensory symptoms, not on conduction efficiency. The primary treatment remains diabetes control managed by a diabetologist. If you seek comparison with other methods of neuropathic pain relief, we described them in the text on neuropathic pain treatment with cannabis.
Why is ALCAR discouraged during chemotherapy?
Because the only large study in this indication ended with a result opposite to intended. A 24-week double-blind trial included women receiving adjuvant taxane-based chemotherapy. 409 patients were evaluated, 208 receiving 3000 mg ALCAR daily and 201 placebo (Hershman, JCO, 2013).
After 12 weeks, there was no difference. After 24 weeks, neurotoxicity scores were 1.8 points lower in the ALCAR group, indicating worsened neuropathy, with statistical significance. Patients taking ALCAR more often experienced a score drop greater than 5 points, and grade 3 or 4 neurotoxicity occurred in eight patients versus one in placebo.
The authors summarize this clearly. There was no evidence of ALCAR effect on neuropathy after 12 weeks, but after 24 weeks it significantly worsened it. This is, as they write, the first study showing a dietary supplement worsened chemotherapy-induced neuropathy, and they conclude by recommending against supplements without proven efficacy.
This result should be considered alongside the diabetic neuropathy result because together they say something neither says alone. The same molecule, in the same tissue and for a similarly sounding symptom, gave a beneficial effect in one context and a harmful one in another. A person undergoing oncological treatment should not take ALCAR without oncologist approval.
What doses were used in studies?
In this article, doses are given only as descriptions of specific studies, not as recommendations for readers. The reason is practical: each indication is a disease, and dose selection belongs to the doctor who knows the study results and other medications taken.
The depression meta-analysis did not specify a single dose because protocols varied. In the cognitive impairment meta-analysis, doses ranged from 1.5 to 3 g daily, and studies lasted 3, 6, or 12 months (Montgomery, Int Clin Psychopharmacol, 2003). The diabetic neuropathy study compared 500 and 1000 mg three times daily for 52 weeks. The oncology study with an unfavorable result used 3000 mg daily for 24 weeks.
One pattern worth noting emerges. Observation time in each study was measured in months, not weeks, and differences appeared late. In the oncology study, no difference was seen after 12 weeks, but after 24 weeks a difference unfavorable to the supplement appeared. Assessment after a week or two is therefore unsupported by any of these protocols.
The second pattern concerns dose thinking. The highest daily dose studied appears in this list with a harmful result, not the best one. This does not prove that a higher dose is inherently worse but undermines the popular reflex to increase the portion when the effect does not come.
Does ALCAR help with weight loss?
Not to a degree justifying purchase for this purpose, and available data concern carnitine in general, not ALCAR itself. A meta-analysis of randomized trials included 9 methodologically adequate studies with a total of 911 participants (Pooyandjoo, Obesity Reviews, 2016).
People receiving carnitine lost significantly more weight than controls: the mean difference was 1.33 kg with a confidence interval from 0.57 to 2.09 kg. Body mass index decreased by 0.47 units. Meta-regression analysis showed something more important than the mean: weight loss magnitude significantly decreased with supplementation duration.
The purchasing decision translation is simple. A difference of about one kilogram, fading over time, is practically indistinguishable from daily weight fluctuations. None of these studies tested ALCAR as a form dedicated to weight loss, and the fat burner claim has no basis here.
If you seek supplements described in the context of concentration and motivation rather than body weight, we compiled data on another amino acid in the text on tyrosine properties for concentration and motivation. The principle remains the same: effect size matters, not the mechanism described on the packaging.
When does ALCAR require a doctor’s consultation?
The first area is the thyroid. Carnitine inhibits thyroid hormone entry into the cell nucleus, with nuclear transport inhibition clearly stronger than cell entry inhibition. In cell line studies at carnitine concentrations much higher than physiological, triiodothyronine uptake reduction into the nucleus reached 25% in nerve cells and 35% in liver cells, and at higher concentrations about 60% and 70%, respectively (Benvenga, Thyroid, 2000).
The effect was later confirmed in humans, though in a situation opposite to typical. In a randomized placebo-controlled study of 50 women receiving levothyroxine at a dose suppressing TSH secretion, carnitine prevented and reversed hyperthyroid symptoms and additionally positively affected bone mineralization (Benvenga, J Clin Endocrinol Metab, 2001). For a person treated for hypothyroidism, the same property acts undesirably by weakening the drug effect.
The second area is situations where carnitine deficiency is secondary to disease. It has been described in liver and kidney diseases, diabetes, sepsis, cardiomyopathy, malnutrition, and endocrine disorders, and supplementation is sometimes part of treatment managed by a doctor (Flanagan, Nutrition and Metabolism, 2010). This reverses the usual purchase logic: carnitine makes sense here because a doctor diagnosed deficiency, not because the patient felt fatigue.
The third area is medications, and here the reader deserves clarification. The previous version of this article included two warnings here: about increased INR in people taking coumarin derivatives and about seizure worsening after carnitine in epilepsy patients. No source was found for these, and authors of the randomized study in women treated with levothyroxine write directly that carnitine has no known drug interactions (Benvenga, J Clin Endocrinol Metab, 2001). We therefore leave only the recommendation for caution without assigning a mechanism.
The fourth area is pregnancy, breastfeeding, developmental age, and advanced kidney disease, where supplementation is part of nephrological treatment. In all these situations, the decision is made by the attending physician. Over-the-counter availability says nothing about safety in a specific clinical situation, and if you take chronic medications, consultation with a doctor or pharmacist should precede purchase.
What did we remove from this entry and why?
Three groups of content. The first is identifiers leading elsewhere. The number labeled as depression meta-analysis led to a study on coronary artery fistulas, the number labeled as weight loss meta-analysis to an article on halophilic fungi, and the number labeled as oncology study to a paper on inflammasomes. The fourth number, labeled as Pettegrew 2002 study in Journal of the Neurological Sciences, is unknown to Europe PMC.
The last item carried three separate paragraphs in the previous version: about 12 weeks of supplementation, about increased neuron integrity marker in hippocampus and prefrontal cortex, and about stabilization of results in 41% of patients versus 17% on placebo. The real works by this author look different. The 1995 study included 7 Alzheimer’s patients taking ALCAR, 5 taking placebo, and 21 healthy people, lasted a year, and measured phosphorus compounds, not the marker mentioned. The 2002 paper is an observation of two elderly depression patients.
The second group is statistics without verifiable sources. The percentage of people making typical purchase mistakes, shares of individual packages in sales, median price per 100 grams, adverse event percentages given to the nearest percentage point, and percentage of users feeling stimulation. None of these numbers can be assigned a source, so none were left.
The third group is prices. The article does not provide amounts for specific products because the store catalog changes faster than the text, and a price given in the content becomes misleading within weeks of publication.
Summary: what remains of ALCAR’s promises
Of the three slogans under which ALCAR is sold, mood holds up best. A meta-analysis of 12 studies with 791 participants shows a significant reduction in depression symptoms compared to placebo and efficacy comparable to antidepressants with fewer side effects, apparently in older people. High heterogeneity calls for caution, and the authors themselves ask for large confirming studies.
Second place goes to peripheral nerves, but with a caveat. In diabetic neuropathy, fiber regeneration and vibration sensation improved, but nerve conduction did not. In chemotherapy neuropathy, the same preparation worsened symptoms, so the question is not whether ALCAR works on nerves but in which clinical context.
Memory fares worst, the promise under which ALCAR most often ends up in the cart. The Cochrane review found no evidence of benefits in cognitive function, functional ability, or dementia severity, and a meta-analysis from the same year showed a small effect visible mainly in composite clinical assessments. Weight loss closes the list with a difference of about one kilogram, decreasing over time.
If you still want to try, order matters. First, exclude common causes of fatigue and memory decline with a doctor, then check thyroid and medications, and only then choose a preparation with a certificate of analysis and plan a trial measured in months. A supplement bought before these steps usually does no harm but delays diagnosis of what really causes symptoms.
Frequently Asked Questions
How does ALCAR differ from regular L-carnitine?
ALCAR is L-carnitine with an acetyl group. Both forms participate in transporting fatty acids to mitochondria, but ALCAR is widely distributed in nervous tissue, including the brain, the blood-brain barrier, neurons, and astrocytes (Sergi, Aging Clin Exp Res, 2018). That is why mood and nerve studies use this form.
Does ALCAR help with depression?
The data are promising but require confirmation. A meta-analysis of 12 studies with 791 participants showed a significant reduction in symptoms compared to placebo, and a comparable result to antidepressants with fewer side effects (Veronese, Psychosomatic Medicine, 2018). Do not stop psychiatric medications in favor of the supplement.
Does ALCAR improve memory?
A Cochrane review covering 11 studies in people with Alzheimer’s disease found no evidence of benefits in cognitive function, dementia severity, or functional ability, and the authors do not recommend routine use (Hudson, Cochrane, 2003). A meta-analysis from the same year showed a small effect.
Does ALCAR work for diabetic neuropathy?
Partially. In a combined analysis of two one-year studies with 1257 patients, the number of sural nerve fibers, clusters of regenerating fibers, and vibration sensation improved, and pain decreased in some analyses. Nerve conduction velocity did not improve at all (Sima, Diabetes Care, 2005).
Can I take ALCAR during chemotherapy?
Not without oncologist approval. In a study of 409 women treated with taxanes, ALCAR significantly worsened neuropathy after 24 weeks, and grade 3 or 4 neurotoxicity occurred in eight patients versus one on placebo (Hershman, JCO, 2013). The authors advise against supplements without proven efficacy.
Is ALCAR safe with thyroid diseases?
It requires consultation with an endocrinologist. Carnitine inhibits thyroid hormone entry into the cell nucleus, and inhibition of nuclear transport is stronger than entry into the cell itself (Benvenga, Thyroid, 2000). In a person treated with levothyroxine for hypothyroidism, this may weaken the drug’s effect.
Does ALCAR help with weight loss?
Very little, and the data concern carnitine in general. A meta-analysis of 9 studies with 911 participants showed a difference of 1.33 kg favoring carnitine, and the amount of weight loss decreased with supplementation duration (Pooyandjoo, Obesity Reviews, 2016). This effect is indistinguishable from daily weight fluctuations.
How long is the trial before I can assess the effect?
Study protocols are measured in months. Cognitive function analyses included trials lasting 3, 6, or 12 months; the diabetic neuropathy study lasted 52 weeks; and in the oncology study, the difference appeared only after 24 weeks. Assessment after a week or two is not supported by any of these protocols.
If after consulting your doctor you seek a preparation with known composition and a certificate of analysis, available items can be found in the supplements category.
This article is for informational and educational purposes and does not constitute medical advice. Before starting supplementation, consult a doctor, especially if you take medications regularly, are pregnant or breastfeeding, or have chronic illness.
Author: Michał Waluk · Published: 2026-05-11 · Updated: 2026-08-10