
Bacopa monnieri: properties for memory and concentration and how to dose
Bacopa monnieri (brahmi) for memory and concentration. What studies involving humans really showed, how long it takes to see the effect, and what they did not show.
Bacopa monnieri, known as brahmi in Ayurveda, is one of the few herbs studied in healthy adults, not just in individuals with diagnosed cognitive disorders. The studies that form the basis of most claims about this plant, however, speak more cautiously than they are usually quoted: the improvement concerns the memorization of new information and processing speed, not short-term memory or attention in every dimension. The effect appears after weeks, not days. This article breaks down these studies into their components: who participated, how long the study lasted, what improved, and what remained unchanged. You will also find a list of things that studies did not show, because with bacopa, this second list is as important as the first.
KEY INFORMATION
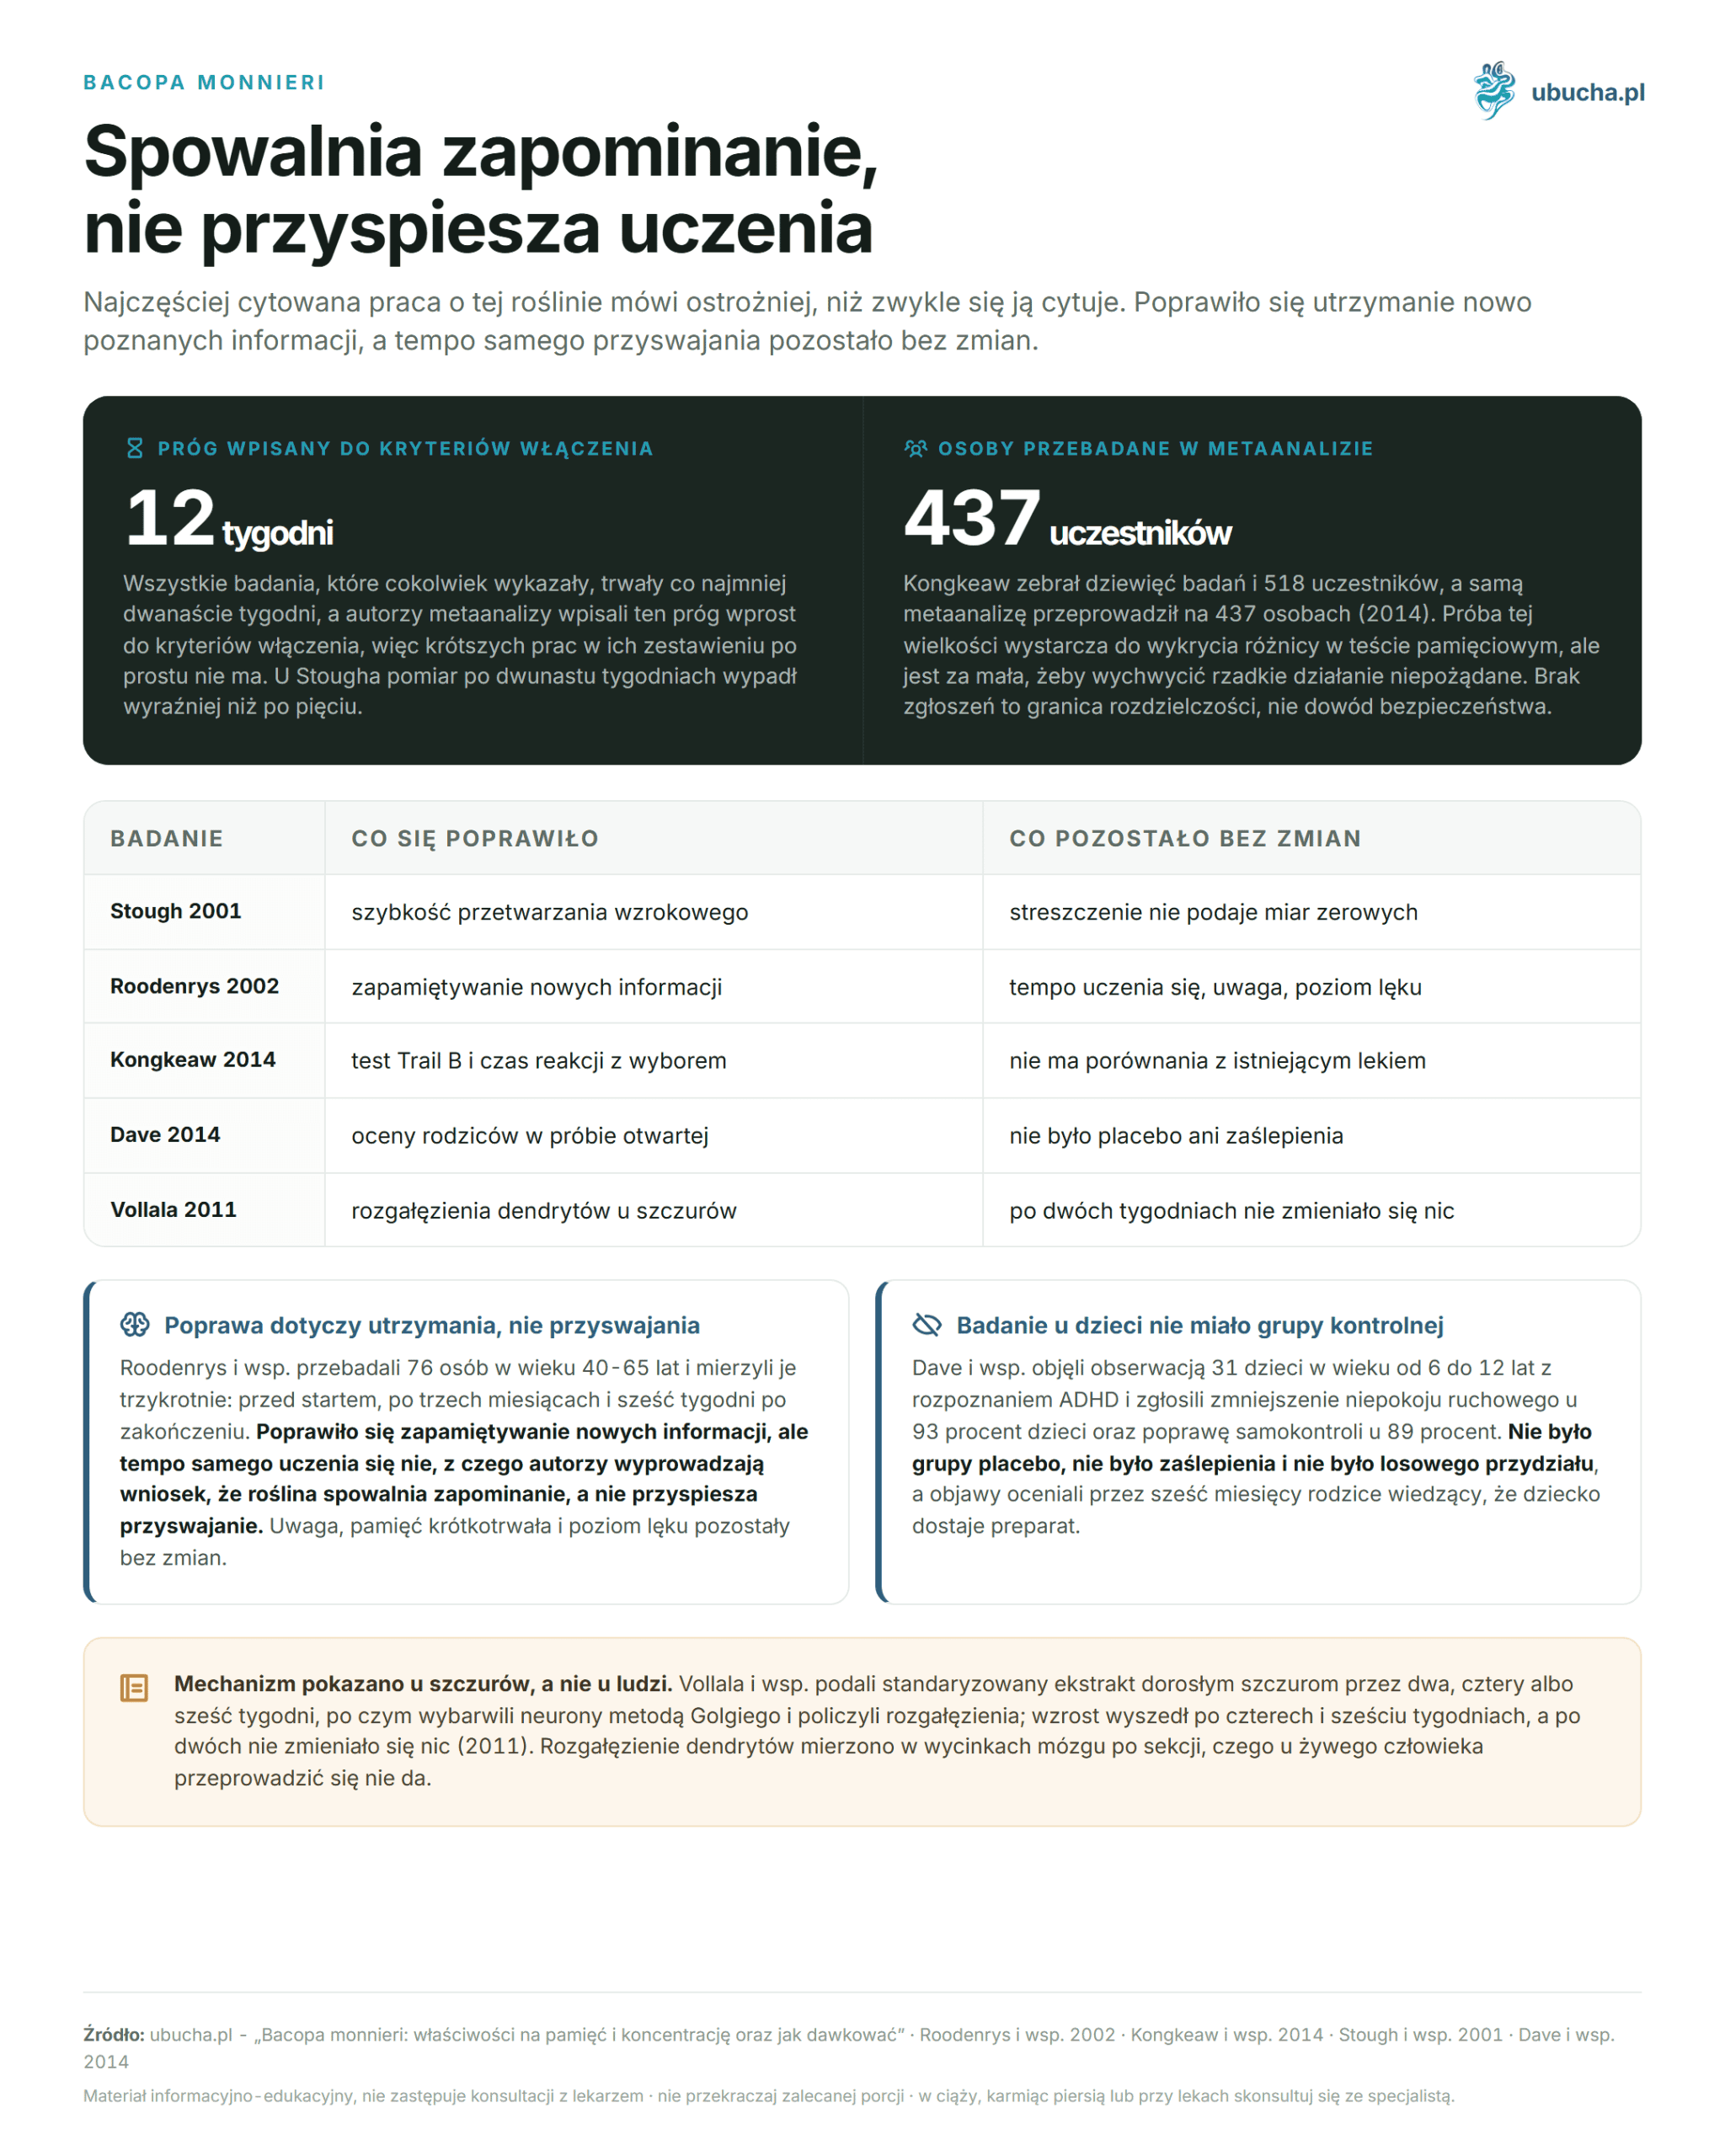
• Roodenrys et al. (Neuropsychopharmacology, 2002) studied 76 individuals aged 40-65 for three months in a double-blind placebo-controlled design. Memorization of new information improved, while attention, short-term memory, and anxiety levels remained unchanged.
• Kongkeaw et al. (Journal of Ethnopharmacology, 2014) gathered nine studies and 518 participants. The effect is visible in the Trail B test and in reaction time with choice, i.e., in attention speed.
• The authors of this meta-analysis caution that the matter will only be resolved by a large study comparing bacopa directly with an existing drug. Such a study is still lacking.
• Bacopa is not a drug. This text describes doses used in studies but does not provide a portion to measure at home.
How does bacopa monnieri affect the brain?
The best-documented mechanism is the stimulation of dendritic growth of neurons, i.e., the branches through which nerve cells exchange signals. However, this has been shown in rats, not in humans, and it is worth remembering this with every statement about “brain remodeling”.
Vollala et al. administered a standardized extract of bacopa to adult Wistar rats in three doses per kilogram of body weight for two, four, or six weeks, and then stained the neurons using the Golgi method and counted the branches. In two independent studies from 2011, one concerning the amygdala (Clinics), the other CA3 neurons of the hippocampus (Romanian Journal of Morphology and Embryology), the result was the same: a significant increase in the number of branches and dendrite length at the two higher doses after four and six weeks. After two weeks, nothing changed. The animals learned faster in the T maze and better maintained the learned avoidance response.
This is a real premise, but not proof in humans. The doses were administered here based on the body weight of the rodent, the extract was standardized differently than pharmaceutical preparations, and dendritic branching was measured in brain slices after dissection. Such measurements cannot be conducted in a living human. Thus, we have a coherent story: a change in the structure of neural connections in rodents, and in humans, a change in memory test results after a similarly long time. These two observations fit together but have not yet been connected by a single study.
What did studies involving humans show?
Three studies carry most of what is known about bacopa in humans: better retention of newly learned information, faster reaction in some attention tests, and, in one study, reduced situational anxiety. Each also lists an equally long list of measures that did not change.
Stough et al. (Psychopharmacology, 2001) administered 300 mg of bacopa extract (Keenmind preparation) or placebo to healthy adults in a double-blind design, conducting neuropsychological tests at the start and after five and twelve weeks. The speed of visual information processing improved, the rate of learning, and memory consolidation measured by a word learning test, while situational anxiety levels decreased.
Roodenrys et al. (Neuropsychopharmacology, 2002) studied 76 individuals aged 40-65 and measured them three times: before the start, after three months, and six weeks after completion. Memorization of new information improved, but the rate of learning itself did not, from which the authors conclude that bacopa slows forgetting rather than speeds up acquisition. Attention, short-term verbal and visual memory, and recall of knowledge from before the study remained unchanged. The level of anxiety also remained unchanged.
Kongkeaw et al. (Journal of Ethnopharmacology, 2014) gathered nine studies and 518 participants, conducting the meta-analysis on 437 individuals. Only studies with placebo lasting at least twelve weeks and conducted without concomitant medications were included in the review. Improvement was noted in the Trail B test and in reaction time with choice, which the authors summarize as an effect on attention speed. They add that only a large study comparing bacopa with an existing drug will resolve the matter.
| Study | Who and for how long | What improved | What remained unchanged |
|---|---|---|---|
| Stough 2001 | healthy adults, 300 mg, 12 weeks, placebo | speed of visual processing, rate of learning, memory consolidation, situational anxiety | no data in the available summary |
| Roodenrys 2002 | 76 individuals aged 40-65, 3 months, placebo | memorization of new information, i.e., slower forgetting | rate of learning, attention, short-term memory, level of anxiety |
| Kongkeaw 2014 | meta-analysis of 9 studies, 518 participants, analysis on 437 | Trail B test, reaction time with choice, i.e., speed of attention | no studies comparing bacopa with a drug |
The areas of improvement only partially overlap, and the effect on anxiety measured in Stough’s study was not replicated in Roodenrys’ study. This is an herb with moderate effects, not a substance that is felt by the individual concerned.
How long do you have to wait for the effect and why so long?
All studies that showed any effect lasted at least twelve weeks. Kongkeaw et al. included this threshold directly in the inclusion criteria of the meta-analysis, so there are simply no shorter studies in their dataset. This is the strongest practical information from all this material.
In Stough’s study, measurements were taken after five and twelve weeks, and the difference between these two points clearly tilts in favor of the latter. In Roodenrys’ study, the first measurement after the start occurred only after three months, so this work says nothing about the earlier course. In rats, Vollala’s boundary lay between the second and fourth weeks: after two weeks, dendritic branching did not differ from control, but after four and six, it did.
The practical conclusion is inconvenient for someone looking for support before a session or presentation. Bacopa has no documented immediate effect. There is also no study that would check what happens after discontinuation, except for one measurement in Roodenrys’ study six weeks after the study ended. If someone promises you an effect after a week, they are not basing it on these works. A comparison of bacopa with other plants with similar promises can be found in the entry about supplements for concentration and memory in light of research.
Does bacopa help children with ADHD?
There is one study that is cited in this context by almost everyone, and it is much weaker than it might seem from how it is described. It is worth knowing it in detail, as it is a good example of the difference between a clinical study and a clinical study with a control group.
Dave et al. (Advances in Mind-Body Medicine, 2014) observed 31 children aged 6 to 12 diagnosed with ADHD according to DSM-IV criteria, at a center in Mumbai, from 2008 to 2010. The children received 225 mg of standardized extract (BacoMind preparation) daily for six months, and the severity of symptoms was assessed by parents using an observational scale before and after the treatment. A reduction in motor restlessness was reported in 93 percent of children, improvement in self-control in 89 percent, and a decrease in attention deficit symptoms in 85 percent. Learning difficulties improved in 78 percent, impulsivity in 67 percent, and psychiatric problems in 52 percent of the subjects.
These numbers look impressive, and that is why it is necessary to add a caveat that the authors themselves provide in the methodology description. The study was open. There was no placebo group, no blinding, and no random assignment. Symptoms were assessed by parents who knew that the child was receiving the preparation for six months, at an age when ADHD symptoms change over time anyway. In such a setup, it is impossible to separate the effect of the extract from the passage of time and the expectations of the person filling out the questionnaire. This study is a premise for designing a proper trial with a placebo, not a basis for giving anything to a child. More broadly about what has and has not been supported by research, we write in the entry about herbs and supplements for ADHD alongside treatment.
How to choose an extract and what to look for on the label?
The most important information on the packaging is the standardization for bacosides, i.e., the declaration of what percentage of the extract consists of compounds considered active. Without this number, it is unclear how much raw material is hidden behind the declared weight of the capsule, and differences between preparations can be multiple.
The second tip comes directly from the discussed studies. In Stough’s work, a preparation described as Keenmind was used, while in Dave et al.’s study, it was BacoMind produced in Bangalore. These are not purchase recommendations, just information that the results pertain to specific, defined extracts, not any powder from bacopa leaves. Kongkeaw et al. included only studies on standardized extracts in their meta-analysis, so all the material discussed here pertains to this specific form of the raw material.
The third thing concerns the form. Powdered dried leaves and extract are not the same product, and they cannot be converted one to another at home, as the content of bacosides in the dried material depends on the plant’s origin and harvest time. If you have dried material in your hands and not a standardized extract, none of the numbers from this article apply to it.
We consciously do not provide a daily portion here. The doses mentioned above describe what was given to participants in specific studies, and only that. Whether and how much bacopa makes sense in your situation is determined by a doctor or pharmacist, especially if you are taking medications regularly.
Where does the name brahmi come from and what does Ayurveda say about it?
In traditional Ayurvedic medicine, bacopa is classified as a medhya rasayana, i.e., plants described as regenerating intellect and memory. This classification appears in scientific works on bacopa as a starting point, as it prompted researchers towards memory tests, not the other way around.
It is worth noting how accurately this traditional category matched what later emerged in studies, and how much it simultaneously diverged from them. Ayurveda spoke of intellect and memory as a whole. Studies involving humans showed a narrow slice: better retention of newly learned information and faster reaction in some attention tests, with no effect on short-term memory and no effect on recalling knowledge that the participant already had. Tradition pointed to the plant and the area, but not the resolution of the effect.
Caution in such comparisons is justified for another reason. The convergence between the ancient description and the modern result is easy to notice when the result is positive, and easy to overlook when it is zero. Ayurveda also attributed effects in epilepsy and mental disorders to brahmi, and these applications are not covered by the studies discussed here at all. Tradition can be a good guide to pose a question, but the answers to it are only provided by research. How bacopa fares against other plants with a similar tradition is described in the comparison of natural nootropics for concentration and memory.
Safety and interactions: who should be cautious?
The most commonly reported side effects of bacopa concern the gastrointestinal tract: discomfort in the upper abdomen, nausea, bloating, and loose stools. They usually worsen when taken on an empty stomach. These are observations described in the literature, not results from a study designed to count complications.
However, much more important is what the discussed studies could not detect by design. Roodenrys et al. studied 76 individuals, and Kongkeaw’s meta-analysis included 437 participants. A sample of this size is sufficient to detect a difference in memory test results, but it is too small to catch rare adverse effects. The lack of reports in these works is therefore not evidence of safety, but a limit of their resolution.
The second gap concerns medications. Kongkeaw et al. included only studies conducted without concomitant medications in their meta-analysis, which is methodologically correct and simultaneously means that we have no data on combining bacopa with pharmacotherapy from this material. Individuals undergoing chronic treatment, particularly neurologically and psychiatrically, should discuss bacopa with their treating physician, rather than infer from results obtained on individuals not taking medications.
Separately: there are no studies on bacopa in pregnant and breastfeeding women, and studies in children are limited to the open trial described above on 31 individuals. In both groups, the available material does not allow for any certain statements, and this is a different situation than demonstrating safety.
Frequently asked questions
Does bacopa monnieri really improve memory?
In a narrow scope, yes. Roodenrys et al. (2002) demonstrated better memorization of new information in 76 individuals with no effect on the rate of learning, attention, and short-term memory. A meta-analysis by Kongkeaw (2014) with 518 participants adds to this the improvement in attention speed in reaction time tests.
How long does it take for bacopa to start working?
All studies that showed an effect lasted at least twelve weeks, and this threshold was included in the inclusion criteria of Kongkeaw’s meta-analysis. In Stough’s study, the measurement after twelve weeks was clearer than after five. No one has demonstrated an immediate effect of bacopa, so it is not a support for one evening.
What dose of bacopa was used in studies?
Stough et al. administered 300 mg of standardized extract to healthy adults for twelve weeks, while Dave et al. gave 225 mg daily to children for six months. This describes research protocols, not recommendations. The appropriate dose for you is determined by a doctor or pharmacist.
Does bacopa monnieri have side effects?
The most commonly reported issues are gastrointestinal discomfort, exacerbated when taken on an empty stomach. However, the largest meta-analysis included 437 participants, so the sample is too small to detect rare complications. The lack of reports in these studies does not equate to demonstrating safety.
Does bacopa help children with ADHD?
The only widely cited study is an open trial by Dave et al. (2014) on 31 children, without placebo, without blinding, and without random assignment, with symptom assessment by parents. In such a setup, it is impossible to separate the effect of the preparation from the passage of time and expectations. This is too little to give anything to a child without consultation.
How does bacopa differ from caffeine?
Caffeine acts within minutes and its effect is self-reported. In the case of bacopa, none of the discussed studies measured immediate effects, and changes only appeared in tests after weeks. Therefore, one should not expect a clear subjective feeling of stimulation or evaluate the preparation after the first few days.
Herbal extracts and herbal powders, including bacopa monnieri, can be found in the herbs category.
This article is for informational and educational purposes and does not constitute medical advice. Before starting supplementation, consult a doctor, especially if you are taking medications regularly, are pregnant or breastfeeding, or have a chronic illness.
Author: Michał Waluk · Published: 2026-05-29 · Updated: 2026-08-15