
5-HTP for Sleep and Mood: How the Serotonin Precursor Works and Is It Safe
5-HTP is a serotonin precursor with a serious contraindication: it should not be combined with serotonin medications. What studies have really shown and where the evidence ends.
5-HTP tempts with simplicity: one step from serotonin, in a capsule from the extract of an African plant, on the supplement shelf. However, this same simplicity is the reason it has one of the most serious contraindications among supplements. Combining it with medications that act on serotonin can trigger a life-threatening condition. Moreover, the evidence of effectiveness is much thinner than sales descriptions suggest: a Cochrane review that examined over a hundred trials deemed only two sufficiently reliable. Some of the numbers circulating in sales descriptions have been attributed to studies that do not contain them, and one of the most frequently cited studies on fibromyalgia did not have a placebo group at all. In this article, we show what individual studies really demonstrated, where evidence ends and misinterpretation begins, and for whom this supplement is simply prohibited.
KEY INFORMATION
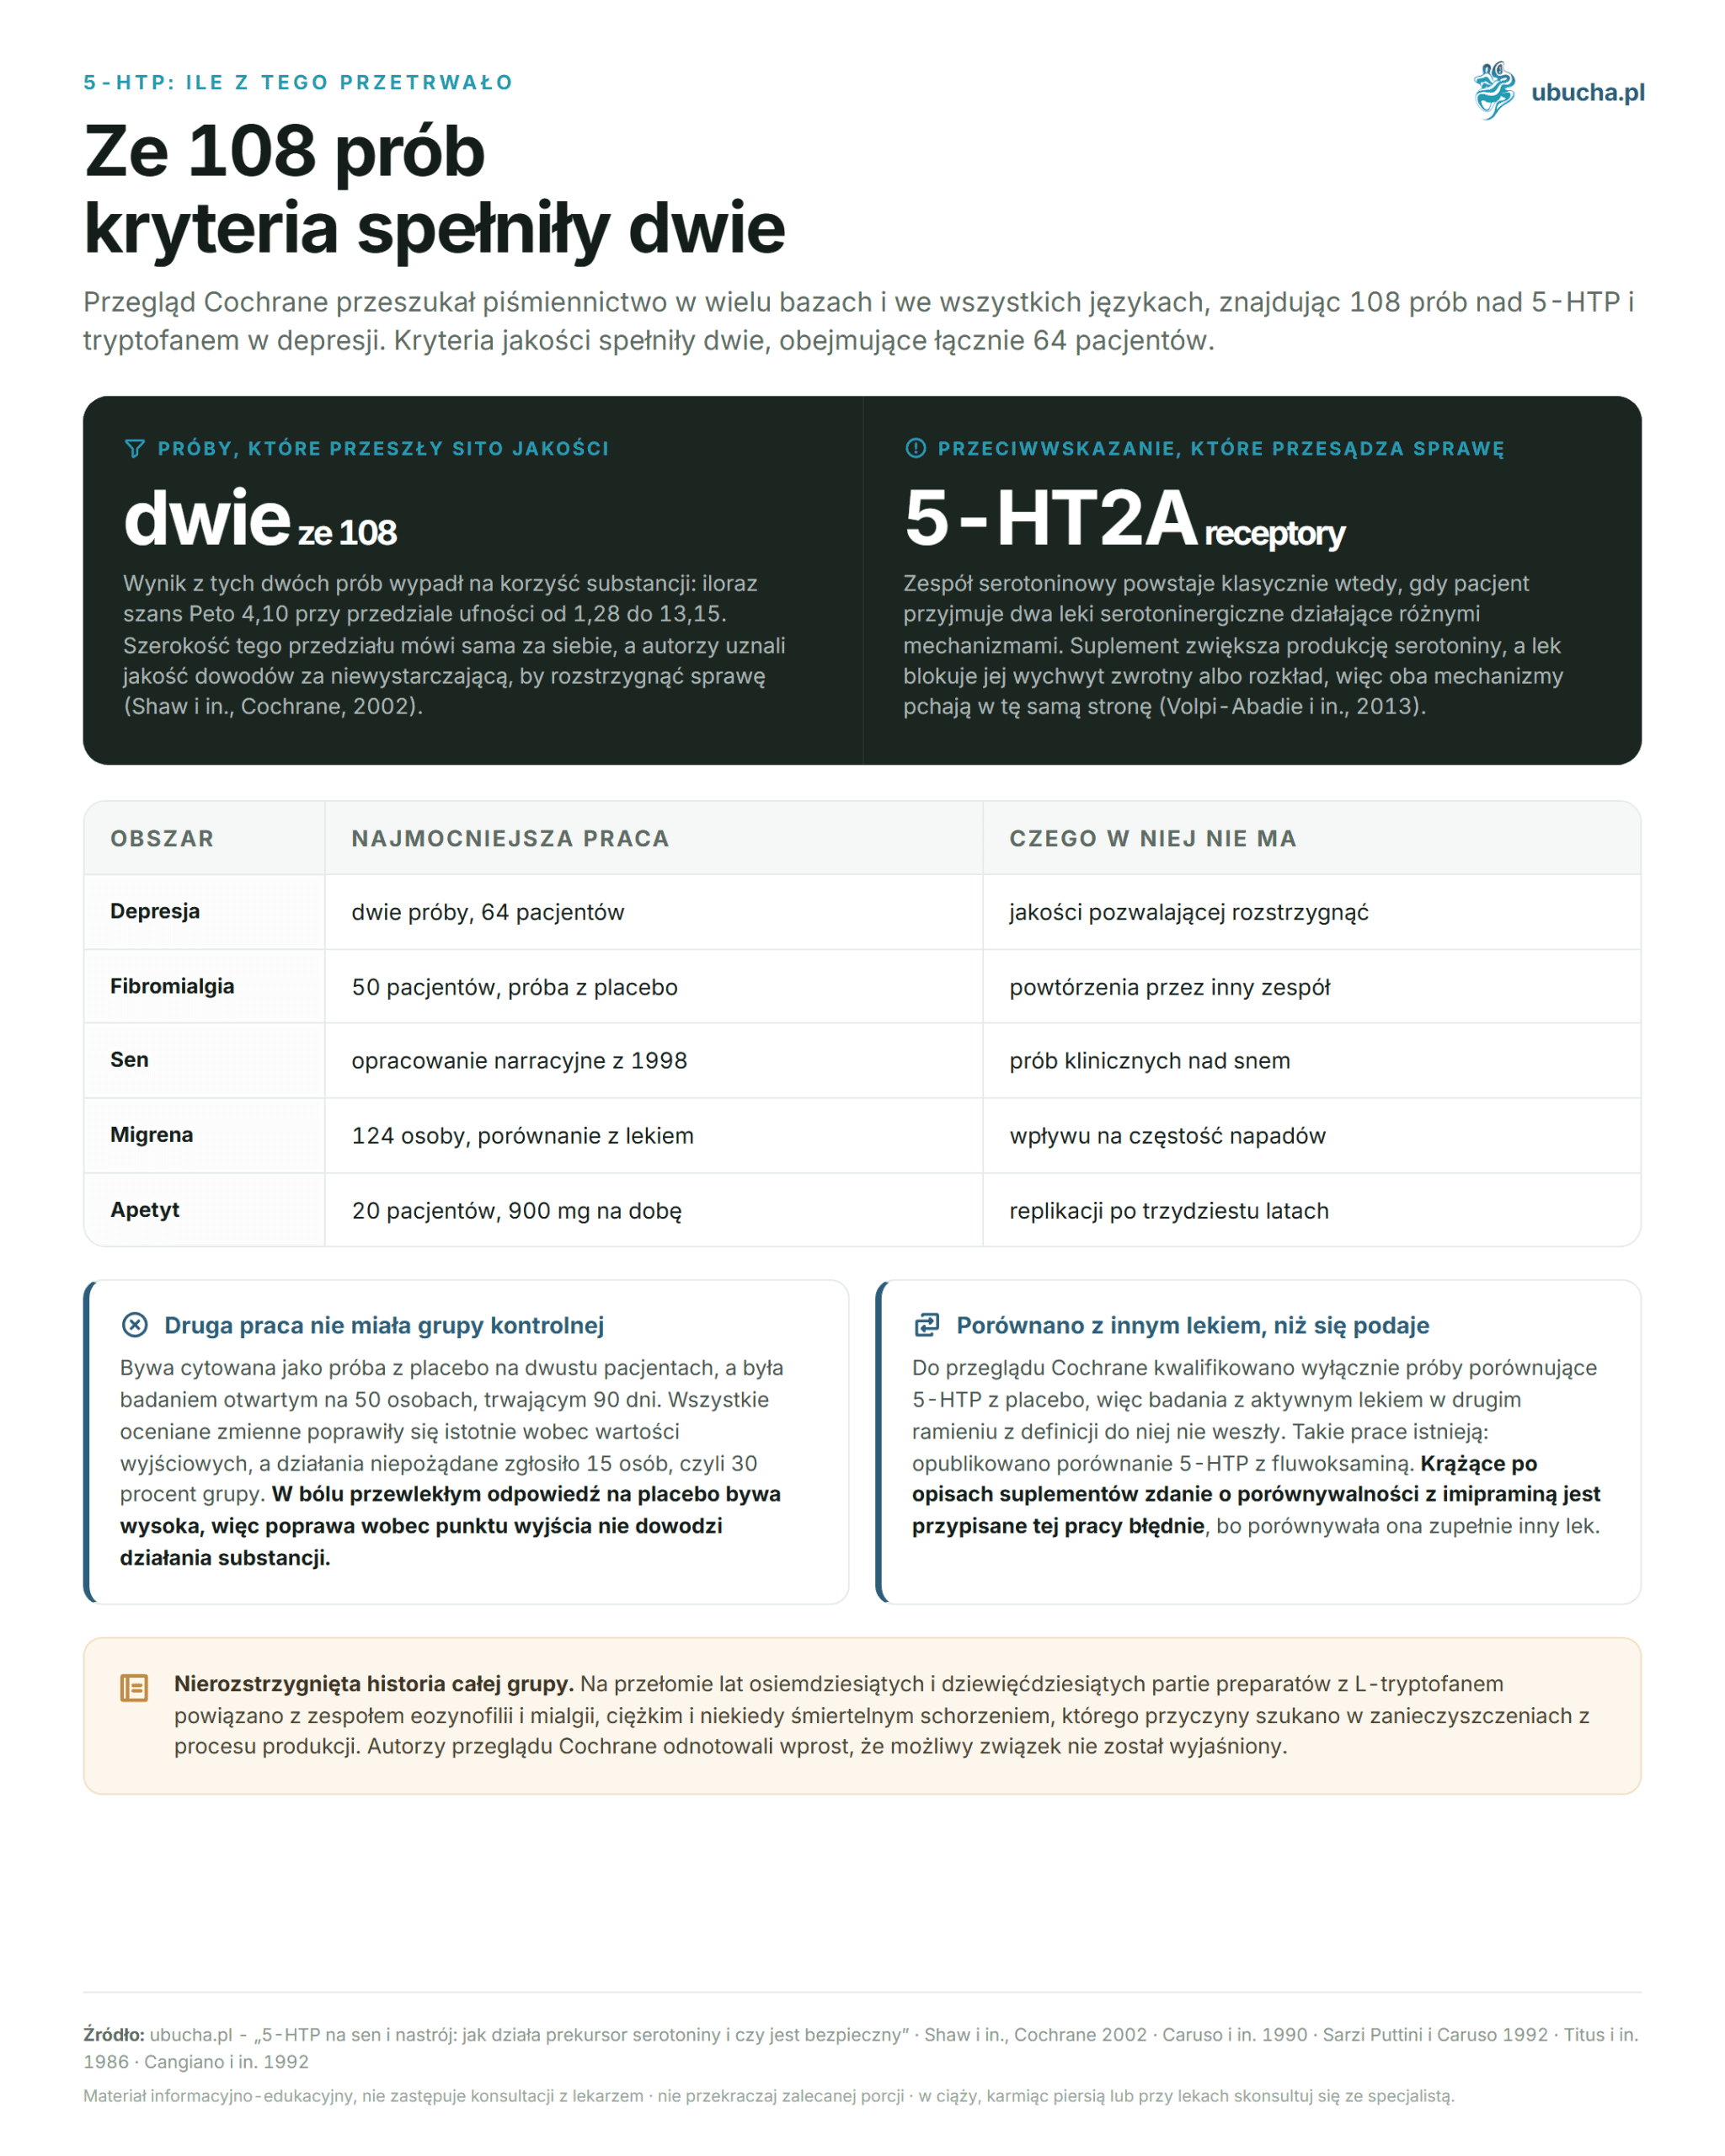
• The Cochrane review found 108 trials on 5-HTP and tryptophan in depression, but only two, involving a total of 64 patients, met quality criteria (Shaw et al., Cochrane Database Syst Rev, 2002).
• 5-HTP does not require a transport protein and does not compete with other amino acids, and about 70% of the oral dose reaches the bloodstream (Birdsall, Altern Med Rev, 1998).
• Combining 5-HTP with serotonergic drugs risks serotonin syndrome, which can be life-threatening.
• The best-documented area is fibromyalgia: a double-blind placebo-controlled study involved 50 patients (Caruso et al., J Int Med Res, 1990).
What is 5-HTP and how does it differ from tryptophan?
5-hydroxytryptophan is an intermediate metabolite on the path from tryptophan to serotonin. The body converts tryptophan into 5-HTP with the help of tryptophan hydroxylase, and then 5-HTP into serotonin with the help of aromatic amino acid decarboxylase. The first of these stages is slower and limits the rate of the entire synthesis, so administering ready-made 5-HTP bypasses this bottleneck.
The second difference concerns absorption. Tryptophan competes for a transporter across the blood-brain barrier with other large neutral amino acids, so a protein meal can limit its entry into the central nervous system. The author of the review from Alternative Medicine Review describes 5-HTP differently: its absorption from the intestine does not require a transport molecule and does not depend on the presence of other amino acids, so it can be taken with a meal without losing effectiveness. About 70% of the oral dose reaches the bloodstream, and the molecule easily crosses the blood-brain barrier (Birdsall, 1998).
The third difference is practical: unlike tryptophan, 5-HTP cannot be redirected to niacin production or incorporated into protein. Serotonin in the brain is involved in regulating sleep, mood, appetite, and pain perception, and in the pineal gland, it additionally serves as a substrate for melatonin synthesis. This explains why one substance is marketed for both mood and sleep.
Why should 5-HTP not be combined with antidepressants?
Because it risks serotonin syndrome. This is a potentially life-threatening condition caused by excessive stimulation of serotonin receptors, primarily 5-HT2A. It manifests simultaneously with changes in mental state, excessive neuromuscular activity, and stimulation of the autonomic nervous system, meaning confusion and anxiety alongside tremors, heightened reflexes, fever, and increased heart rate. The authors of a review from Ochsner Journal emphasize that it classically occurs when a patient takes two serotonergic drugs acting through different mechanisms (Volpi-Abadie et al., 2013).
This exact setup is created by adding 5-HTP to an antidepressant. The supplement increases serotonin production, while the drug blocks its reuptake or breakdown, so both mechanisms push in the same direction. The groups for which this risk is real include selective serotonin reuptake inhibitors and serotonin-norepinephrine reuptake inhibitors, monoamine oxidase inhibitors, tramadol, triptans used in migraines, and dextromethorphan present in cough medications.
This is not a list that one can check independently and consider the matter closed. Many commonly used medications can cause this syndrome, and when discontinuing some of them, there is a waiting period due to their long elimination time. If you are taking any psychotropic, pain-relieving, or migraine medications, the decision about 5-HTP should be made with a doctor or pharmacist, not based on an article. We discuss this mechanism more broadly in the text about interactions with SSRI medications and serotonin syndrome.
Does 5-HTP work for depression?
Here the answer is the most disappointing of all. The Cochrane review searched the literature in many databases and in all languages, and found 108 trials concerning 5-HTP and tryptophan in unipolar depression and dysthymia. Only two trials, involving a total of 64 patients, met quality criteria.
The result from these two trials favored the substance: the Peto odds ratio was 4.10 with a confidence interval from 1.28 to 13.15. However, the width of this interval speaks for itself. The authors summarized that the available data suggest an advantage over placebo, but their quality does not allow for a definitive conclusion, and since there are drugs with proven efficacy and safety, the practical applicability of 5-HTP remains limited (Shaw et al., Cochrane, 2002).
It is worth knowing what this review did not cover. Only trials comparing 5-HTP with placebo were eligible for analysis, so studies with an active drug in the second arm were by definition excluded. Such studies do exist: Pöldinger and colleagues published a comparison of 5-HTP with fluvoxamine in Psychopathology (Pöldinger et al., 1991). However, the statement circulating in supplement descriptions about comparability with imipramine is incorrectly attributed to this work, as it compared 5-HTP with a completely different drug.
Does 5-HTP help with sleep?
The evidence here is weaker than one might expect from the popularity of this use. A review from 1998 lists insomnia among the conditions in which 5-HTP administration proved effective, alongside depression, fibromyalgia, and chronic headaches. However, this is not a systematic review with quality assessment of studies, but a narrative review from over a quarter of a century ago.
The mechanism sounds credible and is likely the source of its popularity. Serotonin is a substrate for melatonin synthesis in the pineal gland, so raising its concentration should indirectly facilitate falling asleep. Serotonin itself also affects mood regulation, which is important in insomnia driven by anxiety and recurring thoughts.
The problem is that there are practically no modern clinical trials on sleep after 5-HTP, and those historical ones date back to the 1970s and were conducted on small groups of healthy volunteers. Specific numbers regarding the extension of the REM phase that circulate in supplement descriptions cannot be attributed to any study we managed to find and verify. Other, better-studied approaches to sleep disorders are gathered in the article on insomnia in adults.
What is known about 5-HTP in fibromyalgia?
This is the best-documented area, although here we are also talking about two studies from the same team over thirty years ago. The first was a double-blind placebo-controlled study involving 50 patients with primary fibromyalgia syndrome and showed significant improvement in all clinical parameters with only mild and transient adverse effects. The authors themselves concluded that further controlled studies are needed (Caruso et al., 1990).
The second work is often cited incorrectly, and it is worth clarifying this, as the difference is fundamental. It was not a placebo trial with two hundred patients, but an open-label study with 50 individuals lasting 90 days. All assessed variables, including the number of tender points, anxiety, pain intensity, sleep quality, and fatigue, improved significantly compared to baseline values. Improvement rated as good or sufficient was noted in nearly half of the patients, and 15 individuals, or 30% of the group, reported adverse effects (Sarzi Puttini and Caruso, 1992).
The lack of a control group in this second study changes the weight of the result. In chronic pain, the response to placebo can be high, so improvement from baseline does not prove the substance’s action. The percentages of pain reduction circulating online from comparisons with placebo come from a study that did not contain such a comparison.
Does 5-HTP prevent migraines and reduce appetite?
In migraine prevention, there is one large comparative study. It involved 124 individuals with migraines, randomly assigned to 5-HTP or methysergide, a drug used at that time for prophylaxis. Significant improvement was noted in 75% of patients on methysergide and 71% on 5-HTP, with fewer adverse effects in the latter group. An important detail that usually gets lost in summaries: the benefit from 5-HTP primarily concerned the severity and duration of attacks, not their frequency (Titus et al., Eur Neurol, 1986).
Regarding appetite, the work from the American Journal of Clinical Nutrition is most often cited. Twenty obese patients were randomly assigned to 5-HTP at a dose of 900 mg per day or to placebo, in a double-blind setup, over two consecutive six-week periods. In the first, no diet was recommended, while in the second, a diet of 5040 kJ per day was recommended. Significant weight loss in the 5-HTP group was observed in both periods, along with reduced carbohydrate intake and consistently reported early satiety (Cangiano et al., 1992).
The dose used in this study was many times higher than that sold in supplements for mood or sleep, and is associated with a higher risk of nausea. The group consisted of twenty individuals, and the study is over thirty years old and has not seen large replication. This is a promising result, but not established.
Does chronic use deplete dopamine?
This is a hypothesis, not a finding, but based on real biochemistry. The enzyme converting 5-HTP to serotonin, namely aromatic amino acid decarboxylase, is the same enzyme that converts L-DOPA to dopamine. Saturating it with one substrate could theoretically limit the processing of the other, and the result would be a decrease in drive and motivation, i.e., symptoms resembling what the supplement was supposed to improve.
Concrete ratios have grown around this hypothesis, such as the recommended ratio of 5-HTP to tyrosine. They have no basis in clinical studies in humans, so we do not provide them. This is biochemical speculation, which some authors transfer to practice faster than the data allow, and the reader receives it in the form of a ready number, without seeing that it is based on reasoning rather than measurement.
The practical conclusion is unequivocal and does not require resolving this hypothesis. Chronic intake of a substance that interferes with monoaminergic transmission requires medical supervision, especially in individuals with Parkinson’s disease and those taking dopaminergic medications. We discuss the other side of the same pathway in the article on mucuna and dopamine.
Where does 5-HTP come from and what about the safety of preparations?
Supplements containing 5-HTP are produced from the seeds of Griffonia simplicifolia, a West African legume with a naturally high content of this compound. When purchasing, a reasonable criterion is the stated source of the raw material and a certificate of analysis confirming the declared content and absence of contaminants.
This requirement is not excessive and has historical background. In the late 1980s and early 1990s, batches of L-tryptophan preparations were linked to eosinophilia-myalgia syndrome, a severe and sometimes fatal condition, the causes of which were sought in contaminants from the production process. The authors of the Cochrane review directly noted that the possible link between these substances and the potentially fatal eosinophilia-myalgia syndrome has not been clarified.
This unresolved issue places 5-HTP in a different position than most supplements. It is not a neutral substance, where the worst-case scenario is a lack of effect. It has a real impact on serotonergic transmission, one serious drug contraindication, and an unresolved safety history for the entire group. The basic part of what is known today about the molecule itself is also gathered in the text about the properties of 5-HTP.
Frequently Asked Questions
Can 5-HTP be combined with antidepressants?
No. The supplement increases serotonin production, while drugs from the SSRI, SNRI, and monoamine oxidase inhibitor groups block its reuptake or breakdown, so both mechanisms work in the same direction. This combination classically triggers serotonin syndrome, a potentially life-threatening condition. This also applies to tramadol, triptans, and dextromethorphan.
Does 5-HTP work for depression?
The evidence is weak. A Cochrane review found 108 trials, but only two met quality criteria, involving a total of 64 patients. The result favored 5-HTP, with a very wide confidence interval. The authors deemed the quality of evidence insufficient to draw a conclusion and pointed to limited practical applicability.
How does 5-HTP differ from tryptophan?
5-HTP is one step closer to serotonin and bypasses the slowest stage of synthesis. Its absorption does not require a transport molecule and does not depend on the presence of other amino acids, so a protein meal does not hinder it. About 70% of the oral dose reaches the bloodstream, and the molecule easily crosses the blood-brain barrier.
Does 5-HTP help with fibromyalgia?
The strongest study is a double-blind placebo-controlled trial with 50 patients, in which all clinical parameters improved significantly. However, the second often-cited work from the same team was an open-label study without a control group, so its comparisons to placebo are unwarranted.
Does 5-HTP help with weight loss?
One double-blind study on 20 obese patients showed significant weight loss, reduced carbohydrate intake, and early satiety in two six-week periods. The dose was 900 mg per day, which is many times higher than in typical supplements, and is associated with a higher risk of nausea.
Who should not use 5-HTP?
Primarily anyone taking medications that affect serotonin, including antidepressants, tramadol, triptans, and dextromethorphan. Caution is also required for individuals with Parkinson’s disease and those taking dopaminergic medications. Due to a lack of data, 5-HTP has not been studied in pregnant or breastfeeding women or in children, and the decision should always be made by a doctor.
This article is for informational and educational purposes and does not constitute medical advice. Before starting supplementation, consult a doctor, especially if you are taking medications regularly, are pregnant or breastfeeding, or have a chronic illness.
Author: Michał Waluk · Published: 2026-05-19 · Updated: 2026-08-16