Cannabis Microdosing 2026: What Has Really Been Measured and What Has Not
Cannabis microdosing: what has been measured in studies on sleep, anxiety, and pain, where the provisional EFSA ceiling lies, and the legal status in Poland in 2026.
Cannabis microdosing is one of the fastest-growing strategies in cannabinoid phytotherapy. The term describes taking sub-perceptual amounts, meaning doses that do not cause intoxication but still modulate the endocannabinoid system (MacCallum and Russo, European Journal of Internal Medicine, 2018). Patients with anxiety, chronic pain, and insomnia increasingly seek a gentler alternative to high THC doses. This article describes the mechanism of action, what has actually been measured in clinical studies, the safety threshold set by EFSA, and the legal status in Poland in 2026. You will not find a ready dosing protocol here because the literature has not established one, and a separate section explains exactly why this gap exists.
KEY INFORMATION
- Microdosing is taking sub-perceptual amounts, i.e., below the intoxication threshold; no numerical definition from dose-response studies has been established (MacCallum and Russo, European Journal of Internal Medicine, 2018).
- Most common goals: anxiety, insomnia, chronic pain, post-exercise recovery.
- Noticeable effect stabilization usually requires 2-4 weeks of regular use.
- In Poland, CBD is legal without a prescription; THC requires a prescription for medical marijuana.
- The only number with backing goes the other way: EFSA’s provisional ceiling (2026) is 0.0275 mg/kg body weight per day, about 2 mg for 70 kg.
What is cannabis microdosing and why is it gaining interest?
Cannabis microdosing is the practice of using sub-perceptual amounts of cannabinoids to modulate the endocannabinoid system without causing intoxication. The term itself comes from a practical review of cannabinoid dosing, not from a dose-response study that would numerically define its boundaries (MacCallum and Russo, European Journal of Internal Medicine, 2018). This distinction is practically important: the review collects clinical experience of the authors rather than measurement results from participant groups.
Sub-perceptual means below the threshold of conscious perception: a person taking such an amount does not feel euphoria or slowed thinking, and effects appear mainly in long-term assessment, for example as better sleep or more stable mood. That is why numbers circulating online as “microdose definitions” are doubly misleading. First, the perception threshold depends on the individual, administration route, and whether they regularly take cannabinoids. Second, none of these numbers were derived from studies comparing several dose levels to show where the effect begins. A table comparing microdose to therapeutic dose, which stood here, promised precision that sources do not provide and was removed.
Cannabinoids have a nonlinear dose-effect curve described by pharmacologists as an “inverted U”: beyond the optimal range, the effect does not increase but weakens, and side effects typical of higher doses, such as drowsiness or dry mouth, may appear. Therefore, microdosing is not about the maximum amount of substance but hitting a narrow therapeutic window.
Interest in this strategy grows for several reasons simultaneously: concerns about psychoactive effects of full THC doses, decreasing acceptance of long-term benzodiazepine and opioid use in chronic pain, and better availability of precise administration forms such as dropper oils or sublingual sprays with 1 mg gradation. Microdosing is not a “magic pill” - it requires patience and regularity, and the effect does not appear within an hour like a classic painkiller but builds gradually over several weeks.
How does microdosing affect the endocannabinoid system?
The endocannabinoid system (ECS) includes CB1 and CB2 receptors and enzymes responsible for synthesis and breakdown of endocannabinoids. Its discovery in the 1990s, when anandamide was identified as the first endogenous ligand, opened a new pharmacology direction (Lu and Mackie, Biological Psychiatry, 2016). Microdosing uses the fact that this system responds to minimal ligand concentrations, not only full receptor saturation.
| ECS Element | Main Location | Role in Microdosing |
|---|---|---|
| CB1 Receptor | brain: cortex, hippocampus, cerebellum | THC gently activates it without full psychoactivity |
| CB2 Receptor | immune cells, peripheral tissues | involved in inflammation regulation |
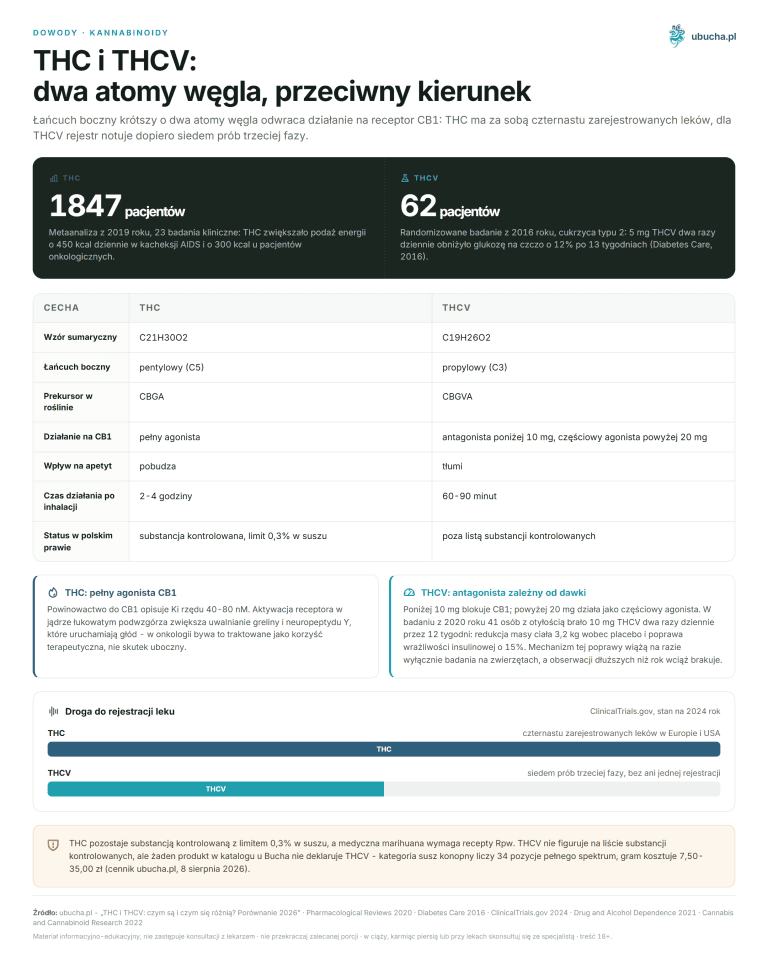
| Anandamide and 2-AG | whole body | CBD slows anandamide removal by competing for FABP transport proteins |
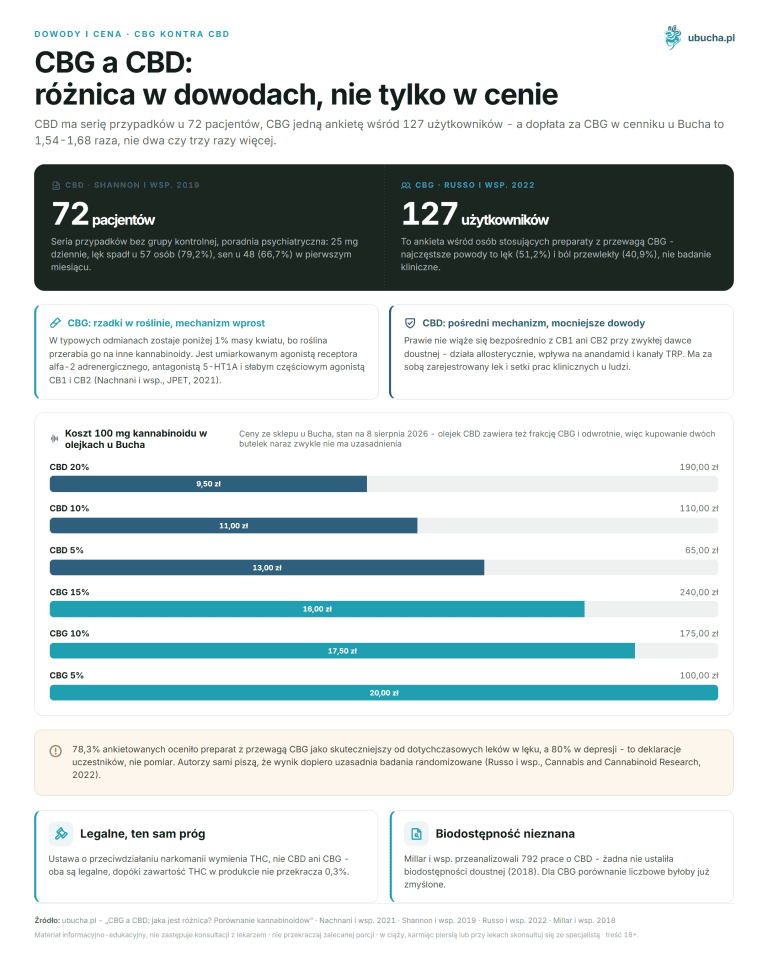
Low-dose THC gently activates CB1, raising pain threshold slightly and stabilizing mood. CBD does not bind directly to CB1 but modulates its activity indirectly and slows anandamide removal (Britch et al., Psychopharmacology, 2021). Not via FAAH enzyme: human FAAH is not inhibited by cannabidiol; the increase in anandamide in humans is explained by competition for FABP transport proteins (Elmes, J Biol Chem, 2015). Ben-Shabat and Mechoulam described the “entourage effect” in 1998, synergy of cannabinoids and terpenes (European Journal of Pharmacology, 1998), and Russo proposed this synergy as a hypothesis to investigate in 2011, not as a result (Russo, British Journal of Pharmacology, 2011). Therefore, microdosing protocols more often rely on broad spectrum or full spectrum oils than isolates.
Thus, microdosing often combines THC and CBD in a ratio where CBD clearly dominates, e.g., 1:5 or 1:10, utilizing both central and peripheral signaling.
Anandamide and 2-arachidonoylglycerol (2-AG) are the two main endocannabinoids produced by the body. They are synthesized and degraded via separate enzymatic pathways, giving them different physiological roles despite chemical similarity. Deficiency of these ligands correlates with the clinical endocannabinoid deficiency (CECD) hypothesis described by Russ in 2008 (Neuro Endocrinology Letters, 2008). Microdosing CBD, by prolonging anandamide half-life through competition for FABP transport proteins, may theoretically raise endocannabinoid tone with lower tolerance risk than full THC doses, which flood receptors externally instead of enhancing signaling already present in the body.
Which cannabis microdosing protocols have scientific support?
None have studies comparing them to others. Names circulating in literature describe strategies, not verified regimens: the most cited, “start low, go slow,” comes from a practical review of cannabinoid dosing, i.e., collected clinical experience of the authors (MacCallum and Russo, European Journal of Internal Medicine, 2018). The review is not a randomized trial and does not resolve which scheme works better or at what dose to start.
The table below shows what these names mean and how strong the evidence is beneath them. It is not guidance on which scheme to choose, as literature does not provide such an answer today.
| Scheme | Description | Evidence Status |
|---|---|---|
| Start low, go slow | smallest reasonable amount initially, slow increase | recommendation from practical review, no comparative study |
| Fixed dose twice daily | set amount morning and evening after finding threshold | described in clinical practice, not compared to others |
| Cyclic scheme | several days on, several days off | no rigorous studies; rationale is CB1 down-regulation |
| As needed (PRN) | only when symptoms intensify, no fixed time | no studies; often a transitional phase before fixed scheme |
The cyclic scheme is sometimes controversial: no rigorous clinical studies confirm its superiority over fixed dosing, and some clinicians fear breaks reduce ECS modulation continuity. Breaks are supported by lower risk of CB1 receptor down-regulation with regular THC use. The PRN scheme works as a transitional phase when establishing an optimal fixed protocol.
The common denominator of all these schemes is the same assumption: there is a narrow window where the effect appears, and outside it weakens. This assumption sounds reasonable and matches the dose-effect curve shape described above, but no one has measured where this window lies for a specific person. This is why this text does not provide numbers: dose and whether it is worth trying at all are discussed with a doctor familiar with cannabinoid pharmacology rather than read from a table.
What therapeutic benefits do clinical studies document?
The richest evidence base concerns anxiety, insomnia, and chronic pain. Shannon’s 2019 study included 72 outpatients with anxiety and sleep disorders: after a month of CBD supplementation, 79.2% reported anxiety reduction and 66.7% improved sleep (Permanente Journal, 2019).
In social anxiety, Bergamaschi’s 2011 study showed a single 600 mg CBD dose reduced anxiety induced by simulated public speaking in patients with social phobia to levels comparable to healthy participants (Neuropsychopharmacology, 2011). A later study from the same group showed the dose-effect relationship has an inverted U shape: 57 healthy men received 150, 300, or 600 mg CBD before the same public speaking test, and only the middle dose reduced anxiety; both extremes did not differ from placebo (Linares et al., Revista Brasileira de Psiquiatria, 2019). This shows more is not always stronger, even beyond microdose ranges.
In chronic pain, an observational cohort study of 367 fibromyalgia patients treated with medical marijuana showed pain intensity decreased from median 9 to 5 on a 0-10 scale, with 81.1% responding to treatment (Sagy et al., Journal of Clinical Medicine, 2019). A smaller study on 26 fibromyalgia patients noted improvement in all FIQ questionnaire domains, and half discontinued other fibromyalgia medications (Habib and Artul, Journal of Clinical Rheumatology, 2018). In migraine, a retrospective review of 121 patients showed a decrease in average attack frequency from 10.4 to 4.6 per month after introducing medical marijuana (Rhyne et al., Pharmacotherapy, 2016).
What do data say about microdosing’s impact on mood and concentration?
The mechanism on anxiety and mood partly involves the serotonin 5-HT1A receptor, which CBD modulates - this is a different pharmacological target than classic anxiolytics, but the effect is weaker and requires several weeks of regular use like other indications. Microdosing does not replace pharmacotherapy for clinical depression nor has solid confirmation in randomized studies for this indication - it is a supportive tool, not an alternative to psychiatrist-led treatment.
The clinical endocannabinoid deficiency hypothesis, described earlier regarding mechanism, has practical relevance in migraine and fibromyalgia: both belong to conditions where some researchers suspect insufficient baseline endocannabinoid tone as a factor. This remains a working hypothesis, not an established mechanism, but explains why these two indications appear more often in cannabinoid research than other chronic pain types.
Data on cognitive functions are much scarcer than for sleep, anxiety, and pain: high THC doses impair short-term memory, but microdose effects on concentration lack solid confirmation in controlled studies and rely mainly on survey observations. It is advisable to approach such reports cautiously and verify effects individually by keeping a diary rather than assuming concentration improvement. People noticing better focus at low doses should treat this as an individual observation, not a population-confirmed rule.
How to choose the form and method of microdosing?
Form choice depends on dosing precision, onset speed, and convenience. Sublingual oils remain the most recommended form in microdosing protocols due to ease of precise dose differentiation drop by drop.
| Form | Onset | Advantage | Disadvantage |
|---|---|---|---|
| Sublingual oil | 15-45 minutes | dose precision per drop | requires holding under tongue |
| Capsules | 60-120 minutes | convenience, dose repeatability | lower bioavailability, slower onset |
| Vaporization | 5-15 minutes | fastest action, good for PRN | difficult milligram precision, equipment needed |
| Edibles | 60-120 minutes | long duration, convenient at night | risk of uneven cannabinoid distribution in product |
A standard 10 ml bottle with a 0.05 ml dropper contains about 200 drops, and how much cannabidiol per drop depends directly on concentration and is stated on the product label. This is product arithmetic, not dosing guidance: drop volume depends on pipette calibration and carrier density, so two pipettes can differ by several tens of percent. Forms also differ significantly in bioavailability: sublingual oil held under the tongue for 60-90 seconds usually achieves the highest bioavailability among oral forms, capsules lose some substance during first-pass liver metabolism, and vaporization has the highest bioavailability of all forms, at the cost of more difficult dose precision.
When choosing a form, check the certificate of analysis (COA), as products without it may have concentrations differing from the label, complicating precise microdosing regardless of how carefully drops or milligrams are counted. This especially concerns gummies and other edibles: uneven cannabinoid distribution in the product mass means one piece from the same package may contain noticeably different doses than another, so products with dose confirmed per piece, not just per package, are better for microdosing.
What about safety and tolerance of microdosing?
EFSA in 2026 set a provisional safe dose of CBD at 0.0275 mg per kilogram of body weight per day, about 2 mg for 70 kg, exclusively for preparations with purity of at least 98%. Amounts described in practice as microdoses fall around or exceed this value, so it is not a margin to ignore. This is the only number in this article related to body weight, and it is a limit, not a starting point for effect.
Most common side effects of CBD microdosing are dry mouth, mild drowsiness, and at higher doses, diarrhea. For THC microdoses, mild dizziness and increased appetite may occur. THC tolerance develops with regular use over several weeks, so some schemes introduce periodic tolerance breaks, i.e., several days without THC to reset CB1 receptor sensitivity - a mechanism similar to that described earlier with the cyclic scheme.
CBD affects cytochrome P450 enzymes, including CYP3A4, which can alter metabolism of concurrently taken drugs, e.g., some anticoagulants, antiepileptics, or immunosuppressants (Brown and Winterstein, Journal of Clinical Medicine, 2019). Risk increases with drugs having a narrow therapeutic window, where the difference between effective and harmful dose is small - thus, consultation with a doctor or pharmacist before starting microdosing is not a formality but a real safety element of therapy.
Absolute contraindications to THC microdosing include pregnancy, breastfeeding, active psychosis or schizophrenia, and age under 18. Relative contraindications are family history of psychosis and severe depression with suicidal thoughts. CBD has far fewer contraindications, mainly severe liver diseases and possible drug interactions. People with unstable coronary disease should be cautious, as THC microdoses may temporarily raise heart rate, usually harmless in healthy individuals but requiring consultation before therapy in unstable heart disease.
How does microdosing CBD differ from microdosing THC?
Microdosing CBD and THC are two different tools with distinct legal and pharmacological profiles. CBD does not require a prescription in Poland; THC does - the number of medical marijuana prescriptions grows yearly: about 313,000 were issued in Poland in 2023, and another 115,000 in the first quarter of 2024 alone, compared to only 11,400 filled in 2020.
CBD works well as the first line of microdosing: no psychoactive effects, no legal restrictions, good safety profile. It is a good option for people sensitive to psychotropic drugs, professional drivers, or athletes for whom any uncertainty about psychomotor state is problematic. If after 4-8 weeks CBD alone is satisfactory, adding THC is usually unnecessary - many patients remain on CBD alone for years.
THC is added mainly when chronic pain, severe insomnia, or neuropathy do not respond sufficiently to CBD alone, as THC modulates pain perception centrally in a way CBD does not provide alone. In Poland, adding THC requires a prescription and a visit to a doctor managing medical marijuana therapy, available mainly as dried flower or oil on prescription in pharmacies conducting such trade, where the doctor selects a strain with an appropriate THC to CBD ratio together with the patient.
Practiced ratios are 1:1 (equal THC and CBD amounts, stronger pain effect but higher subtle psychoactivity risk) and variants from 1:5 to 1:20 with CBD dominance, where THC mainly enhances the entourage effect. The only official reference point is Sativex, a registered drug for spasticity in multiple sclerosis: 1:1 ratio and about 2.7 mg THC and 2.5 mg CBD per spray. This is information about a medicinal product whose dosing is set by a doctor, not a starting point for personal calculations.
Why won’t you find a ready dosing protocol here?
Because there is no basis to create one. A fixed schedule with weekly breakdown and milligram start doses was removed because no study established these numbers. It looked precise, but the precision came from table format, not measurement.
This is best seen by comparing numbers actually measured. Shannon gave cannabidiol to 72 outpatients for a month and noted sleep improvement in two-thirds. Linares compared single doses of 150, 300, and 600 mg in 57 healthy men. Sativex, the only registered drug here, has 2.7 mg THC per spray. EFSA’s provisional supplement ceiling is about 2 mg cannabidiol per day for 70 kg. These values differ by dozens of times and come from completely different situations: supervised clinical trial, prescription drug therapy, and daily use of a store product. One schedule cannot be built from them.
What remains sensible regardless of numbers: first step is consultation with a doctor familiar with cannabinoid pharmacology, especially important in chronic diseases, polypharmacy, and psychiatric history. Second step is product choice: for CBD, a good broad spectrum oil with a certificate of analysis (COA); for THC, a prescription. Third step is keeping a dose and well-being diary, as subtle changes are visible only when comparing weeks, not days.
In microdosing, it is easy to confuse lack of immediate effect with lack of efficacy. Microdoses act like course correction, not an emergency brake: after several weeks, patients rarely say they felt a sudden change; more often they notice they have been sleeping better or feeling less anxious for some time without pinpointing the exact moment of improvement. This is a typical sign that the endocannabinoid system is stabilizing, not proof of no effect.
What is the legal status of cannabis microdosing in Poland in 2026?
In Poland, hemp in which the sum of delta-9-THC and tetrahydrocannabinolic acid (THCA) does not exceed 0.3% dry weight is a legal source of CBD, available without prescription (art. 4 point 5 of the Act of July 29, 2005 on Counteracting Drug Addiction, Dz.U. 2005 no. 179 item 1485, as amended by the Act of March 24, 2022, Dz.U. 2022 item 763). The threshold counts as the sum of both compounds, not delta-9-THC alone, which matters when reading lab test results. Microdosing CBD alone is therefore fully legal for adults, and the Polish CBD market is worth about 130 million euros (Fakty Konopne, 2024).
Microdosing THC requires a prescription and medical marijuana. The Act of July 7, 2017 allowed use of Indian cannabis as a pharmaceutical raw material in Poland (Dz.U. 2017 item 1458), and any doctor can issue a prescription without special authorization. The amendment to the Act on Counteracting Drug Addiction, effective August 27, 2026, does not change the THC threshold, substance classification, or retail rules for cannabis products - it concerns substitution treatment and laboratory reporting, so the legal status described here remains valid after that date.
- Allowed: buying, possessing, and using CBD products in stores and pharmacies, and buying medical marijuana on prescription in pharmacies conducting such trade.
- Not allowed: driving under the influence of THC regardless of dose - tests detect THC even after microdoses for 24-72 hours post intake; CBD is not detected as a drug.
- Not allowed: importing medical marijuana for personal use without a prescription issued in Poland or sharing it with others, even family, even if the prescription is valid.
- Not allowed: cultivating Indian cannabis for medical purposes on your own - the possession of a valid medical marijuana prescription does not change this prohibition.
In sports, WADA removed CBD from the banned substances list in 2018, so CBD microdosing is safe for professional athletes, including during competition periods. THC remains banned during competition periods, so patients taking microdoses should be cautious during competitions and doping controls. Recreational athletes have no formal restrictions.
What mistakes and pitfalls most often spoil microdosing effects?
Microdosing requires discipline and patience, which many patients lack in the first weeks. Lack of immediate effect is often the main reason people quit the protocol before it works - some abandon microdosing in the first weeks before ECS modulation stabilizes noticeably.
| Mistake | Why It Harms | How to Avoid |
|---|---|---|
| Increasing dose too quickly | skips the narrow therapeutic window | consult every dose change with treating doctor |
| No diary | subtle improvement hard to assess from memory | note dose, time, and well-being daily |
| Irregular use | ECS responds to steady, repeatable doses | set fixed alarm or reminder for dose time |
| Wrong product choice | concentration without COA may differ from label | product with current certificate of analysis |
| Combining with alcohol | may unpredictably enhance THC effects | avoid combining, consult if on regular meds |
The common denominator of most mistakes is expecting effects within hours, like with classic drugs. Microdosing works differently: comparing week one to week four usually shows a clear difference not visible day to day.
What microdosing development directions appear in 2026?
Three directions dominate current cannabinoid research. First is development of nanoemulsions and liposomal forms that break oil into much smaller droplets, increasing oral bioavailability compared to regular sublingual oil - in Poland, such products are still rare, but first premium items are appearing on the market. In practice, this means the same microdose acts stronger or the dose can be lowered while maintaining effect.
Second is research on polymorphisms of enzymes metabolizing cannabinoids, e.g., CYP2C9 and FAAH, which could in the future allow dose selection tailored to individual patient metabolism instead of a universal recommendation - people with slower metabolism may achieve higher cannabinoid blood levels at the same nominal dose than those with faster metabolism. These studies are experimental but indicate a direction toward more precise cannabinoid phytotherapy.
Third is growing interest in the “low-dose” and “wellness” segment in the global medical marijuana market, which according to Grand View Research was worth about 21 billion USD in 2023, with a forecast growth to 102.2 billion USD by 2030 at an average annual growth rate of 25.4% (Grand View Research, 2024). This shows microdosing is ceasing to be a niche practice and increasingly enters mainstream cannabinoid phytotherapy.
Is cannabis microdosing a good choice for you?
Cannabis microdosing is a strategy with partial research support, requiring patience and discipline. Sub-perceptual amounts aim to modulate the endocannabinoid system without intoxication, and studies cited here document cannabinoid potential in anxiety, insomnia, chronic pain, and migraine. None, however, established how much a specific person should take.
In Poland, microdosing CBD alone is fully legal and available without prescription. THC microdosing requires a prescription and medical marijuana available in pharmacies conducting such trade. The most important remain: consultation with a doctor, choosing a verified product with a certificate of analysis, keeping a diary, and patience for at least 4-8 weeks before drawing conclusions about effectiveness.
Not everyone will benefit from microdosing, but for many it is a gentler alternative or complement to classic therapies. The most sensible starting point is a broad spectrum oil with a current certificate of analysis, and the amount set with a doctor, not a ready and rigid milligram number prescribed to everyone.
Remember realistic expectations: microdosing is not a “magic pill” but a tool for subtle, gradual modulation of the endocannabinoid system. If you start, keep a diary and consult a specialist familiar with cannabinoid pharmacology before changing anything in your regimen - it is one decision that most protects against accidentally skipping the narrow therapeutic window.
Frequently Asked Questions
What is cannabis microdosing?
It is the intake of sub-perceptual amounts of cannabinoids, meaning doses that do not cause psychoactive effects. The term comes from a practical review of cannabinoid dosing, not from a dose-response study, so no numerical boundary has been established (MacCallum and Russo, European Journal of Internal Medicine, 2018). The goal is to modulate the endocannabinoid system without intoxication.
Is microdosing CBD alone legal in Poland in 2026?
Yes. Hemp in which the sum of delta-9-THC and THCA does not exceed 0.3% dry mass is a legal source of CBD (art. 4 point 5 of the Act on Counteracting Drug Addiction, Dz.U. 2022 item 763). Microdosing THC requires a prescription and medical marijuana prescribed by a doctor. The Polish CBD market is worth about 130 million euros (Fakty Konopne, 2024).
How quickly are the effects of cannabis microdosing seen?
Sublingual forms act within 15-45 minutes, capsules and edibles within 60-120 minutes, and vaporization within 5-15 minutes. Noticeable stabilization of effects usually requires 2-4 weeks of regular use (MacCallum and Russo, European Journal of Internal Medicine, 2018). Subtle effects appear gradually, not suddenly.
Does microdosing cause tolerance or addiction?
At sub-perceptual doses, the risk is much lower than with classical dosing. EFSA in 2026 set a provisional safe dose of CBD at 0.0275 mg per kilogram of body weight per day, about 2 mg for 70 kg, and noted that safety cannot be established for people under 25 years old, pregnant and breastfeeding women, and those taking medications. Tolerance to THC develops with regular use over several weeks.
What do studies say about microdosing for insomnia?
The most frequently cited study is Shannon’s 2019 research: 72 outpatients with anxiety and sleep disorders took cannabidiol for a month, and 66.7% reported improved sleep (Permanente Journal, 2019). It was not a randomized trial and did not establish a dosing regimen. The effect builds gradually over 2-4 weeks.
Does microdosing affect the ability to drive?
Sub-perceptual doses of CBD do not impair psychomotor functions and are not detected as drugs in tests. THC can be detected in drug tests 24-72 hours after intake, even in very small amounts. In Poland, driving under the influence of THC is punishable regardless of dose.
Can cannabis microdosing be combined with medications?
With caution. CBD affects cytochrome P450 enzymes, including CYP3A4, which can alter the metabolism of many concurrently taken drugs (Brown and Winterstein, Journal of Clinical Medicine, 2019). Consultation with a doctor or pharmacist is essential, especially with drugs having a narrow therapeutic window.
After how long is the effectiveness of a microdosing protocol assessed?
A minimum of 2-4 weeks of regular use allows preliminary assessment of effects on sleep, anxiety, and pain. A fuller symptom evaluation is usually observed after 6-8 weeks (Shannon et al., Permanente Journal, 2019). Keeping a dose and well-being diary facilitates objective protocol assessment.
Learn more about the method and who it really works for in the article Microdosing CBD and THC: Trend or Effective Method, and if you wonder how much of microdose effect is real and how much placebo, check Microdosing and Placebo - What Controlled Studies Really Say. For those still seeking their optimal dose, the article Dr Dustin Sulak on CBD Dosing may help, and for regular THC use, it is worth knowing the signals described in Tolerance Break - How to Lower THC/CBD Tolerance. Sublingual oils used in most protocols described here can be found in the oils category.
This article is for informational and educational purposes and does not constitute medical advice. Cannabis microdosing, especially involving THC, requires consultation with a doctor familiar with cannabinoid pharmacology. Before starting cannabis or CBD for therapeutic purposes, consult a doctor, especially if you take other medications, are pregnant, breastfeeding, or have psychiatric conditions in your history. THC microdosing in Poland is possible only based on a prescription for medical marijuana.
Author: Michał Waluk · Published: 2026-05-11 · Updated: 2026-08-17