
CBD for Parkinson’s and Hand Tremors: What Neurology Says and Is It Safe
Does CBD help with Parkinson's and hand tremors? A review of clinical studies: how many people, for how long, what improved, and what did not, as well as interactions with medications.
Parkinson’s disease is progressive and currently incurable. This makes patients and their families a grateful target for promises that have not been verified. CBD often appears in such promises, usually accompanied by statements about hand tremors. However, there are few clinical studies involving people with Parkinson’s, they are small, and their results are far from conclusive. Some of the most cited works, referred to by sellers, are descriptions of a few cases without a control group. Below you will find what has really been measured: how many people participated in each study, for how long, what improved, and what did not. You will also find the most commonly overlooked aspect, which is interactions with Parkinson’s medications.
KEY INFORMATION
• In the study by Chagas et al. (J Psychopharmacol, 2014), 21 people with Parkinson’s received placebo, 75 mg, or 300 mg of CBD per day for 6 weeks. Motor symptoms on the UPDRS scale did not change.
• Improvement was noted in the quality of life score PDQ-39 at a dose of 300 mg, at the borderline of statistical significance, with seven people in the group.
• Essential tremor is a separate disease. A pilot crossover study from 2025, with a preparation containing 5 mg of THC and 100 mg of CBD, showed no effect on tremor amplitude.
• CBD inhibits CYP enzymes, so it may increase the concentration of ropinirole, rasagiline, or clozapine. Any changes in treatment are decided by a neurologist.
• Studies on neuroprotection have been conducted in animals. There are no human studies showing that CBD slows disease progression.
How does Parkinson’s disease differ from essential tremor?
These are two different diseases, and mixing them up is the most common mistake in texts about CBD. In Parkinson’s disease, dopaminergic neurons in the substantia nigra die, and tremors occur at rest and diminish with purposeful movement. Essential tremor is not associated with dopamine loss and behaves oppositely: it intensifies during activities, such as lifting a cup or writing.
The difference also pertains to treatment. In Parkinson’s, the basis of therapy is levodopa and medications acting on the dopaminergic system, and the clinical picture includes bradykinesia, muscle rigidity, and postural disturbances. In essential tremor, propranolol or primidone is used, there is no bradykinesia, and the disease often runs in families and starts earlier.
For evaluating CBD, this has very practical implications. Studies on cannabinoids have been conducted separately in both diseases, on different groups and with different endpoints. The result obtained in a person with Parkinson’s does not transfer to essential tremor and vice versa. A sales page that simply writes about “hand tremors” combines two unrelated sets of data.
In Parkinson’s, non-motor symptoms can be more burdensome than tremors themselves. Depression, anxiety, sleep disturbances, and psychosis occur in a large portion of patients, and they are treated worse than motor symptoms. This is where most research on CBD focuses, not on tremors.
What exactly did the Chagas study from 2014 show?
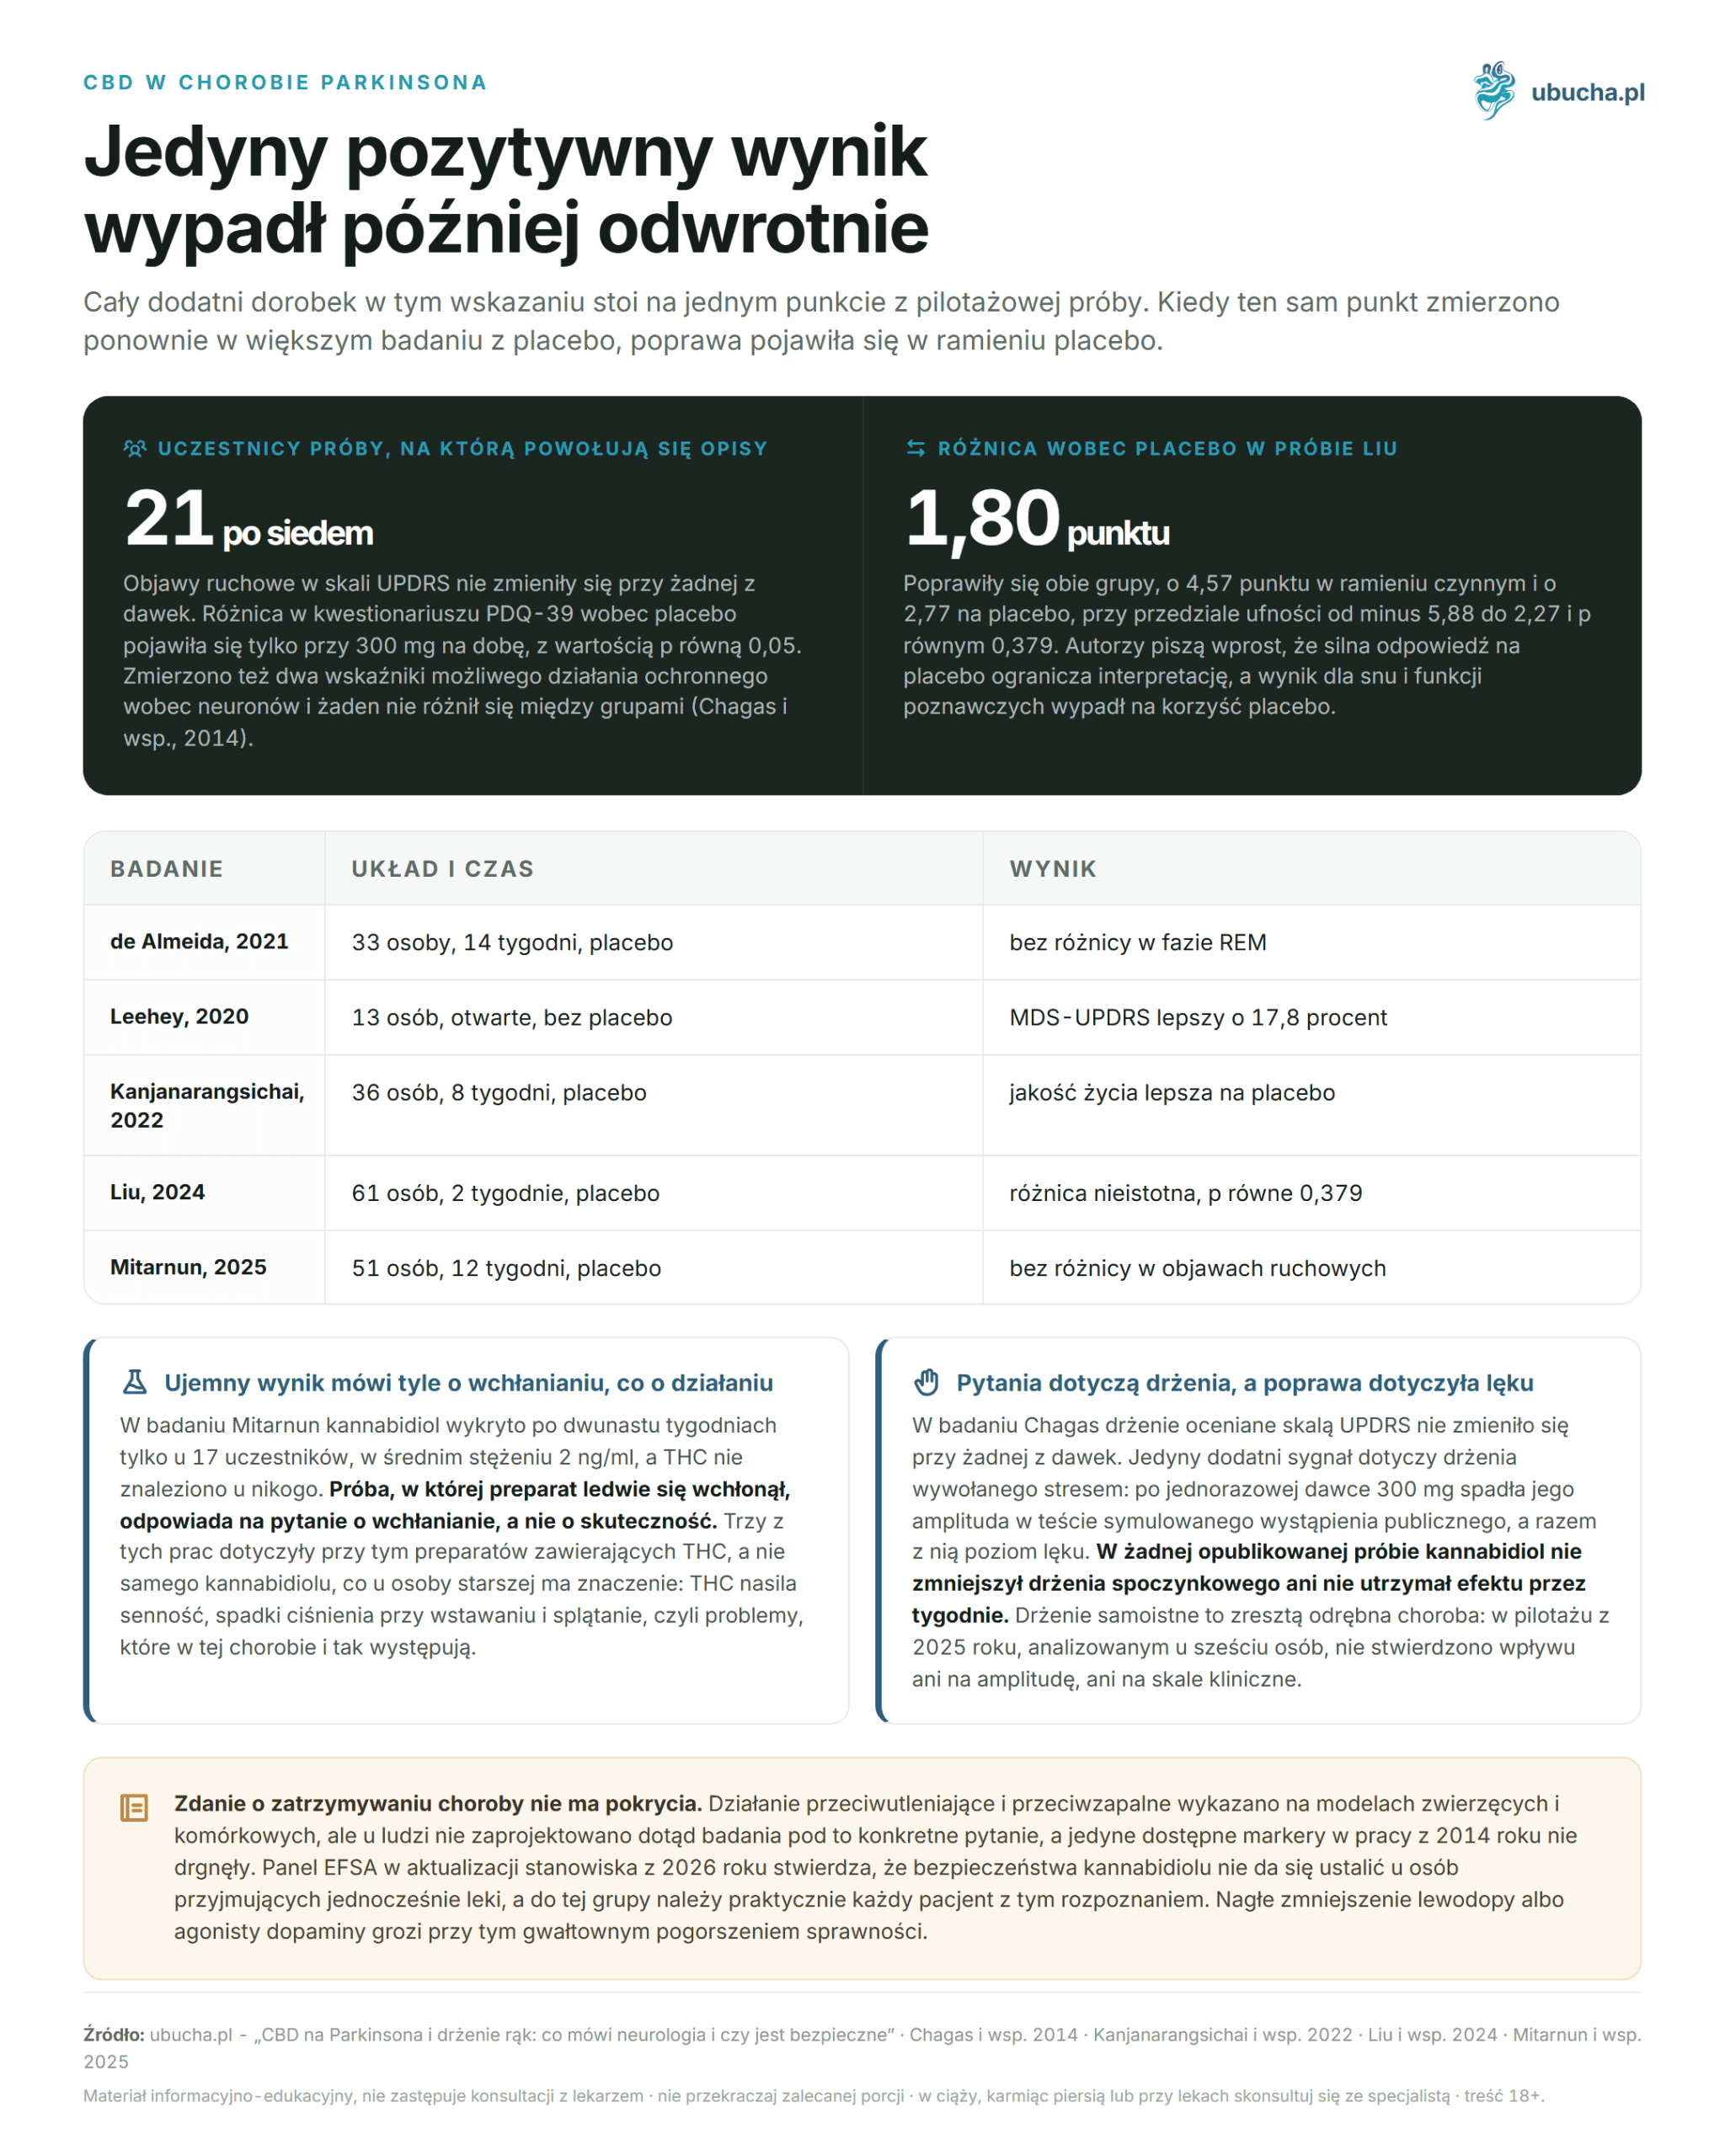
It showed improvement in one quality of life indicator and no changes in everything else. It involved 21 people divided into three groups of seven, treated for 6 weeks. Motor symptoms measured on the UPDRS scale did not improve, and the difference in the PDQ-39 questionnaire compared to placebo appeared only at a dose of 300 mg per day, with a p-value of 0.05.
Participants were selected from 119 people assessed in a movement disorders clinic. Only patients without dementia and without coexisting psychiatric disorders were qualified for the study by Chagas et al. (J Psychopharmacol, 2014), which in itself narrows the conclusions to a narrow group of patients. Placebo, CBD 75 mg per day, and CBD 300 mg per day were compared.
Besides the scales, the authors measured two indicators of possible neuroprotective action: BDNF concentration in plasma and magnetic resonance spectroscopy results. Neither differed between groups. The researchers themselves wrote in the conclusion that the result indicates a possible impact on quality of life and that further studies on larger samples are needed before any conclusions can be drawn.
How to read this? PDQ-39 is a questionnaire in which the patient assesses their well-being and functioning. If the preparation reduces anxiety or improves mood, the score increases, even though the disease progresses the same way. Seven people in the group is a pilot scale, where a single participant shifts the average. This study cannot lead to the conclusion that CBD works on Parkinson’s.
Does CBD reduce hand tremors?
There is no convincing evidence for this. In the Chagas study, tremors assessed on the UPDRS scale did not change at any dose. The only positive result concerned stress-induced tremors: after a single dose of 300 mg, its amplitude decreased in a simulated public speaking test. This is a laboratory situation, not daily functioning.
In the study by de Faria et al. (J Psychopharmacol, 2020), 24 people with Parkinson’s underwent two sessions in a crossover design with placebo. After CBD, anxiety levels decreased on the VAMS scale, and an accelerometer recorded a smaller amplitude of tremors during a stressful task. The simplest explanation is that an anxiolytic effect occurred, as Parkinsonian tremors intensify under stress. In no published trial did CBD reduce resting tremors or maintain the effect for weeks.
Essential tremor was checked separately. In a pilot crossover study by Longardner et al. (Tremor Other Hyperkinet Mov, 2025), a pharmacy preparation containing 5 mg of THC and 100 mg of CBD was used, meaning not just CBD. Seven people were qualified, analysis was conducted for 6, one withdrew after a serious adverse event. No effect was found on tremor amplitude in a digital spiral test or on clinical scales. The authors stated directly that their data do not support the claims circulating on the internet.
What have newer clinical studies from 2020-2025 shown?
Most have not confirmed earlier hopes. Four studies with a control group, conducted on 33, 61, 60, and 40 people, showed no advantage over placebo in the main endpoints. The only study with a clear improvement in motor function was open and without placebo.
| Study | Design and Duration | Participants and Dose | Outcome |
|---|---|---|---|
| de Almeida et al., Movement Disorders, 2021 | Double-blind with placebo, 14 weeks | 33 people, CBD 75-300 mg per day | No difference in the number of nights with REM phase symptoms. Transient improvement in sleep satisfaction |
| Leehey et al., Cannabis Cannabinoid Res, 2020 | Open, no placebo, 10-15 days at target dose | 13 people, pharmacy preparation 5 to 20-25 mg per kg of body weight | MDS-UPDRS improved by 17.8 percent in 10 completers. Elevated liver enzymes in 5 out of 13, only at the highest dose |
| Kanjanarangsichai et al., J Neurosci Rural Pract, 2022 | Randomized with placebo, 8 weeks | 36 people in analysis, sublingually averaged 15.6 mg CBD and 0.6 mg THC per day | No difference in UPDRS scale, gait tests, or anxiety and depression. Quality of life improved in the placebo group |
| Liu et al., Movement Disorders, 2024 | Randomized with placebo, 2 weeks | 61 people, cannabis extract, averaged 191.8 mg CBD and 6.4 mg THC per day | Difference from placebo not significant. Sleep and cognitive functions performed better in the placebo group |
| Mitarnun et al., Parkinsonism Relat Disord, 2025 | Randomized with placebo, 12 weeks | 51 people in analysis, sublingually averaged 26 mg CBD and 1.2 mg THC per day | No difference in delayed memory, motor symptoms, and mood. Improvement in one subtest of MoCA |
Three of these studies involved preparations containing THC, not just CBD. This distinction is important for older individuals: THC increases drowsiness, blood pressure drops upon standing, and confusion, which are exactly the problems that already occur in Parkinson’s. The most instructive result is from the trial by Kanjanarangsichai et al. (2022): quality of life in the EQ-5D-5L scale improved significantly in the placebo group, not in the active group. The point where the only positive result in Chagas occurred later turned out to be the opposite.
Why are these results so difficult to interpret?
Because in each of these trials, something disturbs the reading: sometimes it is a strong placebo response, sometimes a preparation that barely absorbed, sometimes a dose incomparable to anything on the shelf. A negative result does not always mean “does not work”, just as a positive does not always mean “works”.
In the study by Liu et al. (2024), both groups improved, by 4.57 points in the active arm and by 2.77 in placebo, with a difference of 1.80 points at a confidence interval from minus 5.88 to 2.27 and p equal to 0.379. The authors state directly that a strong placebo response limits interpretation, and the result for sleep and cognitive functions favored placebo.
It is also worth looking at what actually reached the blood in these trials. In the study by Mitarnun et al. (2025), cannabidiol was detected after twelve weeks in only 17 participants, at an average concentration of 2 ng/ml, and THC was not found in anyone. A negative result from such a trial says as much about absorption as it does about action.
Doses remain. In the study by Leehey et al. (2020), doses of up to 20-25 mg per kilogram of body weight were used, which for a person weighing 75 kg is about one and a half thousand milligrams per day. This is the dose of the registered drug Epidiolex, administered under the supervision of a researcher. Three out of thirteen participants withdrew due to intolerance, and all reported adverse effects, most commonly diarrhea in 85% and drowsiness in 69%. Elevation of liver enzymes occurred in five people and only at the level of 20-25 mg per kilogram, with symptoms occurring in one.
For balance: a systematic review of thirteen clinical studies (Varshney et al., Cannabis and Cannabinoid Research, 2023) mentions improvement in motor symptoms over placebo. However, it also includes nabilone and cannabis, not just cannabidiol, and was published before the trials from 2024 and 2025.
Does CBD help with psychosis and sleep disorders in Parkinson’s?
These are two of the best mechanistically justified applications, but the evidence remains weak. Psychosis was studied in six people in an open study, without placebo. REM phase behavior disorders were described in four patients, and a later study with a control group of 33 people did not confirm this result. No published trial with placebo has yet verified the result for psychosis.
In the work by Zuardi et al. (J Psychopharmacol, 2009), six patients with psychosis lasting at least three months received CBD at a flexible dose, starting from 150 mg per day, for 4 weeks, alongside their existing treatment. Scores on the BPRS scale and the Parkinsonian psychosis questionnaire decreased, and the total UPDRS score not only did not worsen but decreased. No adverse effects were reported. Mechanistically, this makes sense: typical antipsychotic medications increase rigidity in Parkinson’s, which is why clozapine and pimavanserin are mainly used there. However, six people without blinding and without a comparison group is a hypothesis, not a resolution.
Sleep illustrates this problem even more clearly. Chagas et al. (J Clin Pharm Ther, 2014) described four patients treated for six weeks, three with a dose of 75 mg per day and one with a dose of 300 mg, in whom the number of episodes of dream enactment quickly decreased. Seven years later, de Almeida et al. (Movement Disorders, 2021) examined 33 people for 14 weeks in a placebo design and found no difference in any of the main endpoints. Only subjective sleep satisfaction improved, temporarily, between the fourth and eighth weeks.
What interactions with Parkinson’s medications are a real risk?
A real risk is the increase in the concentration of drugs metabolized by cytochrome P450, which CBD inhibits: most strongly on the CYP2C19 pathway, less so on CYP3A4 and CYP1A2. A person with Parkinson’s usually takes several preparations at once, so the potential for such interaction is wide. Levodopa does not belong to this list, but the rest do.
Levodopa with carbidopa or benserazide goes through decarboxylase and COMT, not through cytochrome P450, so a metabolic interaction with CBD is unlikely there. Ropinirole is mainly metabolized by CYP1A2, the same enzyme responsible for rasagiline, while selegiline is broken down by CYP2B6 and CYP3A4. Inhibition of these pathways increases the concentration of the drug in the blood, which manifests as drowsiness, nausea, and blood pressure drops upon standing. Pramipexole is an exception, as it is excreted by the kidneys in practically unchanged form.
Medications used for Parkinsonian psychosis require separate attention. Clozapine is a substrate of CYP1A2. Quetiapine and pimavanserin go through the CYP3A4 pathway. These are precisely the preparations for which advertising often presents CBD as a “natural alternative”. In a review by Brown and Winterstein (J Clin Med, 2019), nearly half of those using CBD reported dose-dependent adverse effects, including elevated aminotransferases and drowsiness. However, this number comes from the characteristics of registered drugs with cannabidiol, meaning from patients on therapeutic doses, not from supplement buyers.
By how much does CBD increase the concentration of drugs in human studies?
The scale of this inhibition has been measured, and it reveals something that warnings regarding Parkinson’s usually remain silent about: the enzyme that takes the biggest hit is the one that these warnings do not mention. Bansal et al. (Clinical Pharmacology and Therapeutics, 2023) administered to eighteen healthy adults, in a crossover design, a cookie with an extract containing 640 mg of CBD and 20 mg of THC, and half an hour later a set of marker drugs. Exposure to omeprazole, a marker for CYP2C19, increased by 207%. For losartan (CYP2C9) it was 77%, for midazolam (CYP3A) 56%, for caffeine (CYP1A2) 39%, and for dextromethorphan (CYP2D6) there was no change at all. An extract with just THC did not inhibit any of the five enzymes. CYP1A2, on which most warnings regarding Parkinson’s medications are based, is therefore the weakest inhibited of this quartet, while CYP2C19, which is the pathway for proton pump inhibitors and clopidogrel, takes the biggest hit. One caveat: 640 mg is a dose many times higher than what is found in a shelf supplement, so do not directly transfer percentages to a few milligrams.
One principle is non-negotiable: do not stop or reduce any Parkinson’s medication on your own. Sudden reduction of levodopa or a dopamine agonist risks a rapid decline in function, and with agonists, also withdrawal syndrome. Doses are determined by the treating neurologist, who sees the entire history of the disease.
What should you ask your neurologist before trying CBD?
About three things: whether any of your medications go through the CYP2C19, CYP3A4, or CYP1A2 pathways, how often to monitor liver enzymes, and how to recognize that a drug has started to work too strongly. Have the conversation before starting treatment, not after. CBD is not a neutral addition to therapy. The EFSA panel in its 2026 position update states that the safety of cannabidiol cannot be established in individuals under 25 years of age, in pregnant and breastfeeding women, and in those taking medications simultaneously, and practically every patient with Parkinson’s falls into this last group.
Establish with your doctor what specifically should improve and how you will check it. If the goal is sleep, anxiety, or mood, the data at least partially supports such expectations. If the goal is tremors, studies do not support it, and it is better to know this right away. Keep a record of the dose, time of administration, sleep quality, and any decline in function, because without notes, you will not distinguish the effect of the preparation from the natural fluctuations of the disease.
Our observations from conversations with patients’ families: questions almost always concern tremors, as this is a symptom visible to others and the most embarrassing for the patient. Meanwhile, studies that have turned out somewhat positive have concerned anxiety, sleep, and well-being, which are things that are not visible in a picture. This discrepancy is the biggest source of disappointment here.
Finally, the issue of neuroprotection. Antioxidant and anti-inflammatory effects of CBD have been shown in animal and cellular models, but no study has yet been designed in humans to address this specific question, and the only available markers in the 2014 study did not budge. The statement “CBD stops Parkinson’s” has no backing in the data. More about the safety profile in older individuals can be found in the article CBD for seniors, and about its effects on the nervous system in the article CBD and the brain and nervous system.
Frequently Asked Questions
Does CBD help with Parkinson’s disease?
The data is preliminary and mostly negative. In the study by Chagas et al. (2014), motor symptoms on the UPDRS scale did not change in 21 people, and improvement was only noted in the quality of life score at a dose of 300 mg per day. CBD does not cure the disease and does not replace levodopa.
Does CBD reduce hand tremors?
There is no convincing evidence for this. The UPDRS scale did not show any change in tremors in the 2014 study. The only positive signal concerned stress-induced tremors after a single dose of 300 mg. Essential tremor is a separate disease, and a pilot study from 2025 showed no effect there.
Is CBD safe with Parkinson’s medications?
It requires supervision by a neurologist. In humans, CBD inhibits CYP2C19 most strongly and CYP1A2 least, thus increasing the concentration of not only ropinirole, rasagiline, or clozapine, but also proton pump inhibitors. Levodopa does not pass through cytochrome P450. High doses have been associated with elevated liver enzymes.
What doses were used in studies on CBD in Parkinson’s?
Chagas et al. administered 75 mg or 300 mg per day for 6 weeks to 21 people. Leehey et al. used a pharmacy preparation at a dose of 5 to 20-25 mg per kilogram of body weight in 13 people for 10-15 days. These are research doses, not recommendations. Treatment decisions are made by a neurologist.
Does CBD help with psychosis in Parkinson’s?
There is one open study involving six people, in which after 4 weeks, psychosis scale scores decreased without worsening motor function. There was no control group or blinding, and no subsequent placebo trial to verify this result has been published yet. This is a hypothesis for further research, not proof of efficacy.
Does CBD slow the progression of Parkinson’s disease?
There is no data on this in humans. Protective effects on neurons have been shown in animal and cellular models. In the 2014 study, two neuroprotection markers, BDNF in plasma and magnetic resonance spectroscopy, were measured, and no differences were found compared to placebo.
If after talking to your neurologist you decide to try, look for a product with a certificate of analysis issued for a specific batch. You can find such products in the oils section of the store at Bucha.
This article is for informational and educational purposes and does not constitute medical advice. Before starting to use cannabis or CBD for therapeutic purposes, consult your doctor, especially if you are taking other medications, are pregnant, or breastfeeding.
Author: Michał Waluk · Published: 2026-05-28 · Updated: 2026-08-15