
Berberine vs Metformin: The Depth of Scientific Evidence
Berberine vs metformin: what original studies show, where evidence ends, and why a supplement should not be replaced with a prescription drug without a doctor.
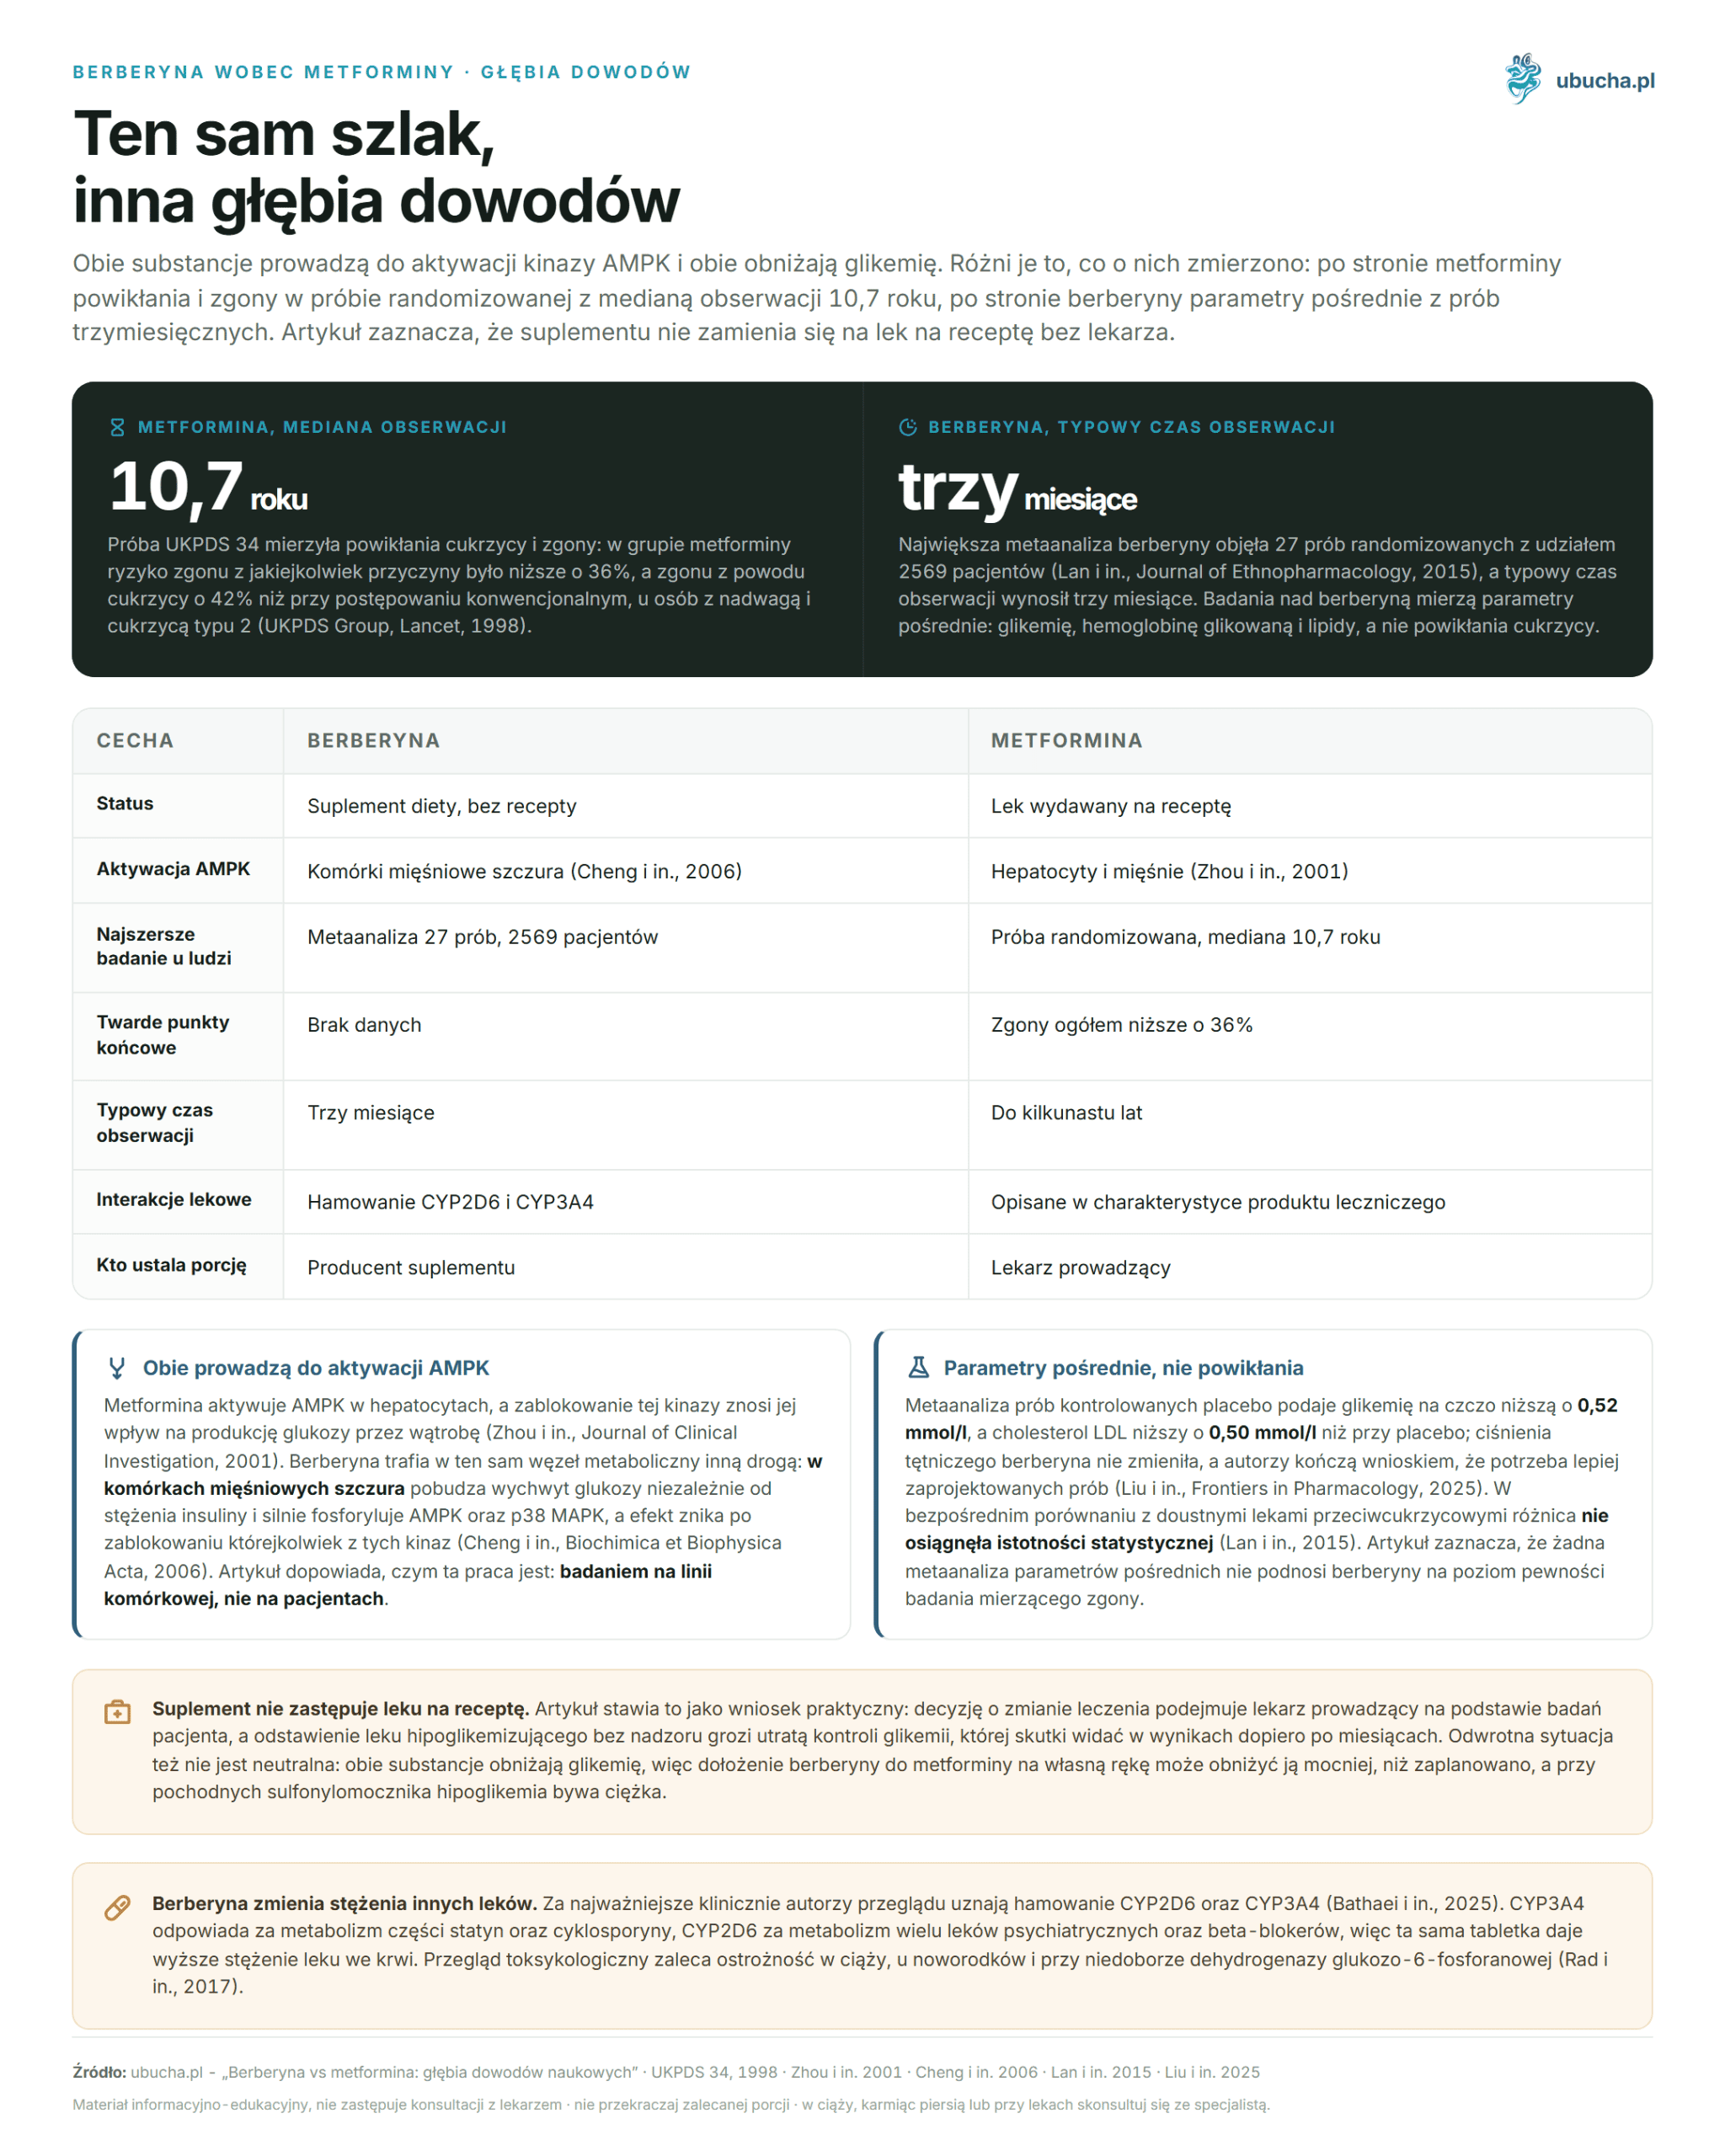
Berberine is sometimes called natural metformin, and this comparison sells it better than any description of its composition. There is indeed a common point: both substances lead to the activation of AMPK and both lower glycemia. The rest of the picture looks different. Metformin has undergone a randomized trial with a median follow-up of 10.7 years, during which it reduced all-cause mortality by 36% in overweight individuals with type 2 diabetes (UKPDS 34, Lancet, 1998). Berberine has a set of short trials, most often three months long. Does this mean it does not work? It does not. It means we know much less about it and that we know different things. Below we show what exactly the original works say about both substances and where the evidence ends and marketing begins.
KEY INFORMATION
• In the UKPDS 34 trial, metformin reduced all-cause mortality by 36% with a median follow-up of 10.7 years (UKPDS Group, Lancet, 1998).
• In the European Union, berberine is sold as a dietary supplement, not as a diabetes drug.
• Berberine inhibits CYP2D6 and CYP3A4, thus altering the concentrations of many drugs in the blood.
• Never stop taking metformin on your own.
Can berberine replace metformin?
No. Metformin is a prescription drug, tested in a randomized trial with a median follow-up of 10.7 years: in the metformin group, the risk of death from any cause was 36% lower, and death from diabetes was 42% lower than with conventional treatment (UKPDS 34, Lancet, 1998). Berberine does not have a study of this class.
The difference is not that one substance works and the other does not. It is about what is known about the effects of their use over the years. Studies on berberine measure glycemia, glycated hemoglobin, and lipids, which are intermediate parameters. UKPDS measured diabetes complications and deaths. These are two different levels of certainty, and no meta-analysis of intermediate parameters elevates berberine to the second.
The practical conclusion is short: if you are taking metformin, do not stop it on your own and do not reduce the dose after reading an article on the internet, including this one. Stopping a hypoglycemic drug without supervision risks losing glycemic control, and the effects are only visible in the results after months. The decision to change treatment is made by your doctor based on your tests. The opposite situation, adding berberine to metformin on your own, is also not neutral: both lower glycemia, so together they may lower it more than you planned.
How do berberine and metformin act on the AMPK pathway?
Both lead to the activation of AMPK, but they enter it from different sides. Metformin activates AMPK in hepatocytes, and blocking this kinase abolishes its effect on glucose production by the liver (Zhou et al., Journal of Clinical Investigation, 2001). This is the first coherent description of the mechanism of this drug.
Berberine hits the same metabolic node through a different route. In rat muscle cells, it stimulates glucose uptake independently of insulin concentration, strongly phosphorylating AMPK and p38 MAPK, and the effect disappears after blocking either of these kinases (Cheng et al., Biochimica et Biophysica Acta, 2006). It should be added what this work is: a cell line study, not on patients.
The second mechanism of berberine has no equivalent on the metformin side. The oral bioavailability of berberine is very low, so a significant part of its action takes place in the intestine, interacting with the microbiota, which itself changes under its influence (Cheng et al., Journal of Pharmaceutical Analysis, 2022). The authors of this review treat this interaction as a condition for understanding the mechanism, not as a proven benefit for the patient.
Overlapping mechanisms explain the similar direction of action. They do not explain the similar certainty of the outcome, as this comes from studies on humans, not from the description of the signaling pathway.
What does the comparison of berberine and metformin show point by point?
The table below compares both substances by legal status, mechanism, and quality of evidence. The numbers come from the works cited in this article, not from the materials of supplement manufacturers.
| Feature | Berberine | Metformin |
|---|---|---|
| Status | Dietary supplement, over the counter | Prescription medication |
| AMPK Activation | Demonstrated in rat muscle cells (Cheng et al., 2006) | Demonstrated in hepatocytes and muscles (Zhou et al., 2001) |
| Largest human study | Meta-analysis of 27 trials, 2569 patients (Lan et al., 2015) | Randomized trial, median 10.7 years (UKPDS 34) |
| Hard endpoints | No data | Overall deaths lower by 36%, deaths from diabetes by 42% |
| Fasting glycemia | 0.52 mmol/l lower than placebo (Liu et al., 2025) | Glycated hemoglobin 7.4% vs 8.0% in the control group |
| LDL cholesterol | 0.50 mmol/l lower than placebo (Liu et al., 2025) | No hypolipidemic indication |
| Typical follow-up time | Three months | Up to several years |
| Drug interactions | Inhibition of CYP2D6 and CYP3A4 (Bathaei et al., 2025) | Described in the product characteristics |
| Who determines the dose | Supplement manufacturer | Attending physician |
The columns of this table are not symmetrical, and that is its content. On the side of berberine are laboratory parameters from short trials, on the side of metformin are complication numbers from a decade-long study. Comparing them side by side does not equate both substances, it only shows how much the former still lacks to reach the status of the latter.
What have clinical studies on berberine really shown?
The most frequently cited work is the pilot study by Yin et al. from 2008. In its first part, 36 people with newly diagnosed type 2 diabetes were randomly assigned to berberine or metformin at 0.5 g three times a day for three months. Glycated hemoglobin dropped in the berberine group from 9.5% to 7.5% (Yin et al., Metabolism, 2008).
The authors described the hypoglycemic effect of berberine as similar to that of metformin, and this one sentence underpins all subsequent marketing. The rest of the work looks more modest: in the second part, 48 people with poorly controlled diabetes received berberine as an adjunct to their existing treatment, glycated hemoglobin dropped from 8.1% to 7.3%, and transient gastrointestinal complaints occurred in 34.5% of participants. The authors themselves called their work a pilot study.
A broader picture is provided by a meta-analysis of 27 randomized trials involving 2569 patients. Berberine added to lifestyle changes lowered fasting glycemia, postprandial glycemia, and glycated hemoglobin more than lifestyle changes alone, but in direct comparison with oral antidiabetic drugs, the difference did not reach statistical significance (Lan et al., Journal of Ethnopharmacology, 2015).
A newer meta-analysis of placebo-controlled trials confirms the direction and provides magnitudes: fasting glycemia lower by 0.52 mmol/l, triglycerides by 0.37 mmol/l, LDL cholesterol by 0.50 mmol/l, waist circumference smaller by 3.3 cm. Berberine did not change blood pressure. The authors conclude that it may be a valuable supplement and that better-designed trials are needed (Liu et al., Frontiers in Pharmacology, 2025).
What drug interactions does berberine have?
Berberine alters the work of enzymes that metabolize most drugs. A review of data on barberry and berberine indicates an effect on isoforms CYP3A4/5, CYP2D6, CYP2C9, CYP2E1, and CYP1A1/2, with the authors considering the inhibition of CYP2D6 and CYP3A4 to be the most clinically significant (Bathaei et al., Naunyn-Schmiedeberg’s Archives of Pharmacology, 2025).
What does this mean for your home medicine cabinet? CYP3A4 is responsible for the metabolism of some statins and cyclosporine, while CYP2D6 is responsible for the metabolism of many psychiatric drugs and beta-blockers. Inhibition of these enzymes means that the same tablet results in higher drug concentrations in the blood. The authors of the review conclude with a recommendation to ask the patient about possible interactions before recommending berberine.
We have noticed in conversations with customers that those who ask about berberine are often people who are already taking something regularly: a statin, a blood pressure medication, or an antidepressant. This is exactly the group for whom self-purchasing is the most risky. Berberine does not behave like herbal tea, but like a substance with a measurable impact on drug metabolism.
The practical rule is simple. Show your doctor or pharmacist a list of everything you are taking before adding berberine to it. Interactions through cytochrome P450 do not give warning symptoms that could be recognized at home.
Who should not use berberine?
A toxicological review of barberry and berberine recommends caution in three situations directly: during pregnancy, in newborns, and with glucose-6-phosphate dehydrogenase deficiency. The same work lists dose-dependent side effects, including gastrointestinal irritation and jaundice (Rad et al., Iranian Journal of Basic Medical Sciences, 2017).
Additionally, there is a group that texts about berberine often overlook: people already treated with hypoglycemic drugs. Adding another substance that lowers glycemia to metformin or a sulfonylurea derivative increases the risk of hypoglycemic episodes, and with sulfonylurea derivatives, hypoglycemia can be severe.
Caution is also required for people with liver disease. Berberine is metabolized with the involvement of cytochrome P450, and impaired liver function alters its fate in the body. If you have elevated liver tests, the topic of berberine starts with a visit to the doctor, not a purchase.
Breastfeeding is a separate issue. There is too little data on the transfer of berberine into milk to recommend anything, and regarding newborns, the cited toxicological review recommends caution. Lack of data is not evidence of safety, but a lack of evidence in both directions.
What is known about berberine in polycystic ovary syndrome?
A meta-analysis of 10 randomized trials involving 713 women with PCOS showed that berberine added to conventional treatment improved the ovulation rate (RR 1.41) and clinical pregnancy rate (RR 1.96), and also lowered luteinizing hormone and total testosterone (Ha and Song, 2024).
Note the word “added.” In this meta-analysis, berberine was an adjunct therapy compared to conventional treatment alone, not a replacement for it. This is a completely different research question than “does berberine replace metformin in PCOS,” and the answer to the latter is not provided by this work.
The authors themselves caution that further clinical studies are needed before definitive conclusions can be drawn. In practice, this means a conversation with a gynecologist or endocrinologist, not a self-purchase, especially since hormonal preparations are often used concurrently in PCOS, which berberine may alter the metabolism of.
We have noticed that those who ask about berberine in the context of PCOS are often people who poorly tolerate metformin from a gastrointestinal perspective. The motive is understandable, but berberine also causes gastrointestinal complaints: in the pilot study by Yin et al., they occurred in 34.5% of participants. Switching one substance for another for this reason is not an obvious win.
Which products at Bucha contain barberry?
The Bucha store does not have a product with berberine and does not pretend to have one. In the entire catalog, checked on August 8, 2026, no product has berberine or barberry in its name. Barberry appears as one of the ingredients in three oil macerates from the Aura Care line.
| Product | What distinguishes it | Price | Cost per 1 ml |
|---|---|---|---|
| Aura Care Adaptogens Sugar in Norm 15 ml | Barberry 300 mg per serving, alongside gymnema, chaga, white mulberry, and cinnamon | 99.00 PLN | 6.60 PLN |
| Aura Care Snacking STOP 15 ml | Indian barberry 200 mg per serving, alongside gymnema and lion’s mane | 99.00 PLN | 6.60 PLN |
| Aura Care Healthy Liver 15 ml | Barberry 75 mg per serving, formula built around milk thistle | 99.00 PLN | 6.60 PLN |
The conversion factor here is the cost of one milliliter, as the manufacturer provides the serving in drops, and the number of drops in the bottle is only given for some products. Prices are from the store API and are valid as of August 8, 2026.
Three disclaimers to avoid misunderstanding. None of these preparations is a drug or a standardized extract of berberine; the manufacturer declares oil macerates at a ratio of DER 1:1. None has an indication in diabetes. None is an alternative to pharmacotherapy conducted by your doctor.
Frequently Asked Questions
Can berberine replace metformin?
No. Metformin is a prescription medication, tested in a randomized trial with a median follow-up of 10.7 years, during which it reduced all-cause mortality by 36% (UKPDS 34, 1998). Berberine is a dietary supplement and there is no study measuring hard endpoints. Never stop taking metformin without your doctor’s decision.
How does berberine lower glucose levels?
In rat muscle cells, berberine stimulates glucose uptake independently of insulin concentration, strongly phosphorylating AMPK and p38 MAPK; blocking either of them abolishes the effect (Cheng et al., 2006). This is a cell line study, so it describes the mechanism, not efficacy in patients.
How many studies does berberine have compared to metformin?
The largest meta-analysis of berberine included 27 randomized trials involving 2569 patients (Lan et al., 2015), and the typical follow-up time was three months. Metformin has the UKPDS 34 trial with a median follow-up of 10.7 years and measurement of deaths and complications. This is a difference in depth, not in direction of results.
What side effects does berberine have?
In the pilot study by Yin et al., transient gastrointestinal complaints occurred in 34.5% of participants (Metabolism, 2008). A toxicological review also lists dose-dependent gastrointestinal irritation and jaundice and recommends caution in pregnancy, in newborns, and with glucose-6-phosphate dehydrogenase deficiency.
What dose of berberine was used in studies?
In the pilot study by Yin et al., patients received 0.5 g of berberine three times a day for three months (Metabolism, 2008). This is not a dose approved by any regulatory body, as berberine is not a drug. The supplement dose is determined by the manufacturer, and with ongoing pharmacotherapy, it is established with a doctor.
Does berberine work in polycystic ovary syndrome?
A meta-analysis of 10 randomized trials involving 713 women with PCOS showed that berberine added to conventional treatment improved the ovulation rate and clinical pregnancy rate and lowered total testosterone (Ha and Song, 2024). Berberine was an adjunct therapy there, not a replacement for treatment.
Herbal and vitamin preparations from the Bucha shelf can be found in the Supplements category; discuss the choice of a specific preparation with your doctor before chronic treatment.
This article is for informational and educational purposes and does not constitute medical advice. Before starting supplementation, consult your doctor, especially if you are taking medications regularly, are pregnant or breastfeeding, or have a chronic illness.
Author: Michał Waluk · Published: 2026-08-05 · Updated: 2026-08-08