
Alpha-lipoic acid ALA: a strong antioxidant for nerves, sugar, and skin
Alpha-lipoic acid has one indication with strong data and many weaker ones. We examine studies on neuropathy, glycemia, and skin, as well as those from animals.
Alpha-lipoic acid occupies an unusual position in supplements. It is a molecule that the body produces itself, and at the same time, one of the few antioxidants studied in a large, multicenter placebo-controlled trial. It is produced in the mitochondria and works there as a cofactor for two enzyme complexes of the Krebs cycle. When administered externally, it behaves like a scavenger of reactive oxygen species and reacts with vitamin C and glutathione. The strongest data concern one indication: symptoms of diabetic neuropathy. The rest of the applications, from glycemia to skin to multiple sclerosis, are based on evidence of very varying quality, some of which comes from animal studies. Below, we separate these layers and provide information on who studied, on whom, and with what results for each.
KEY INFORMATION
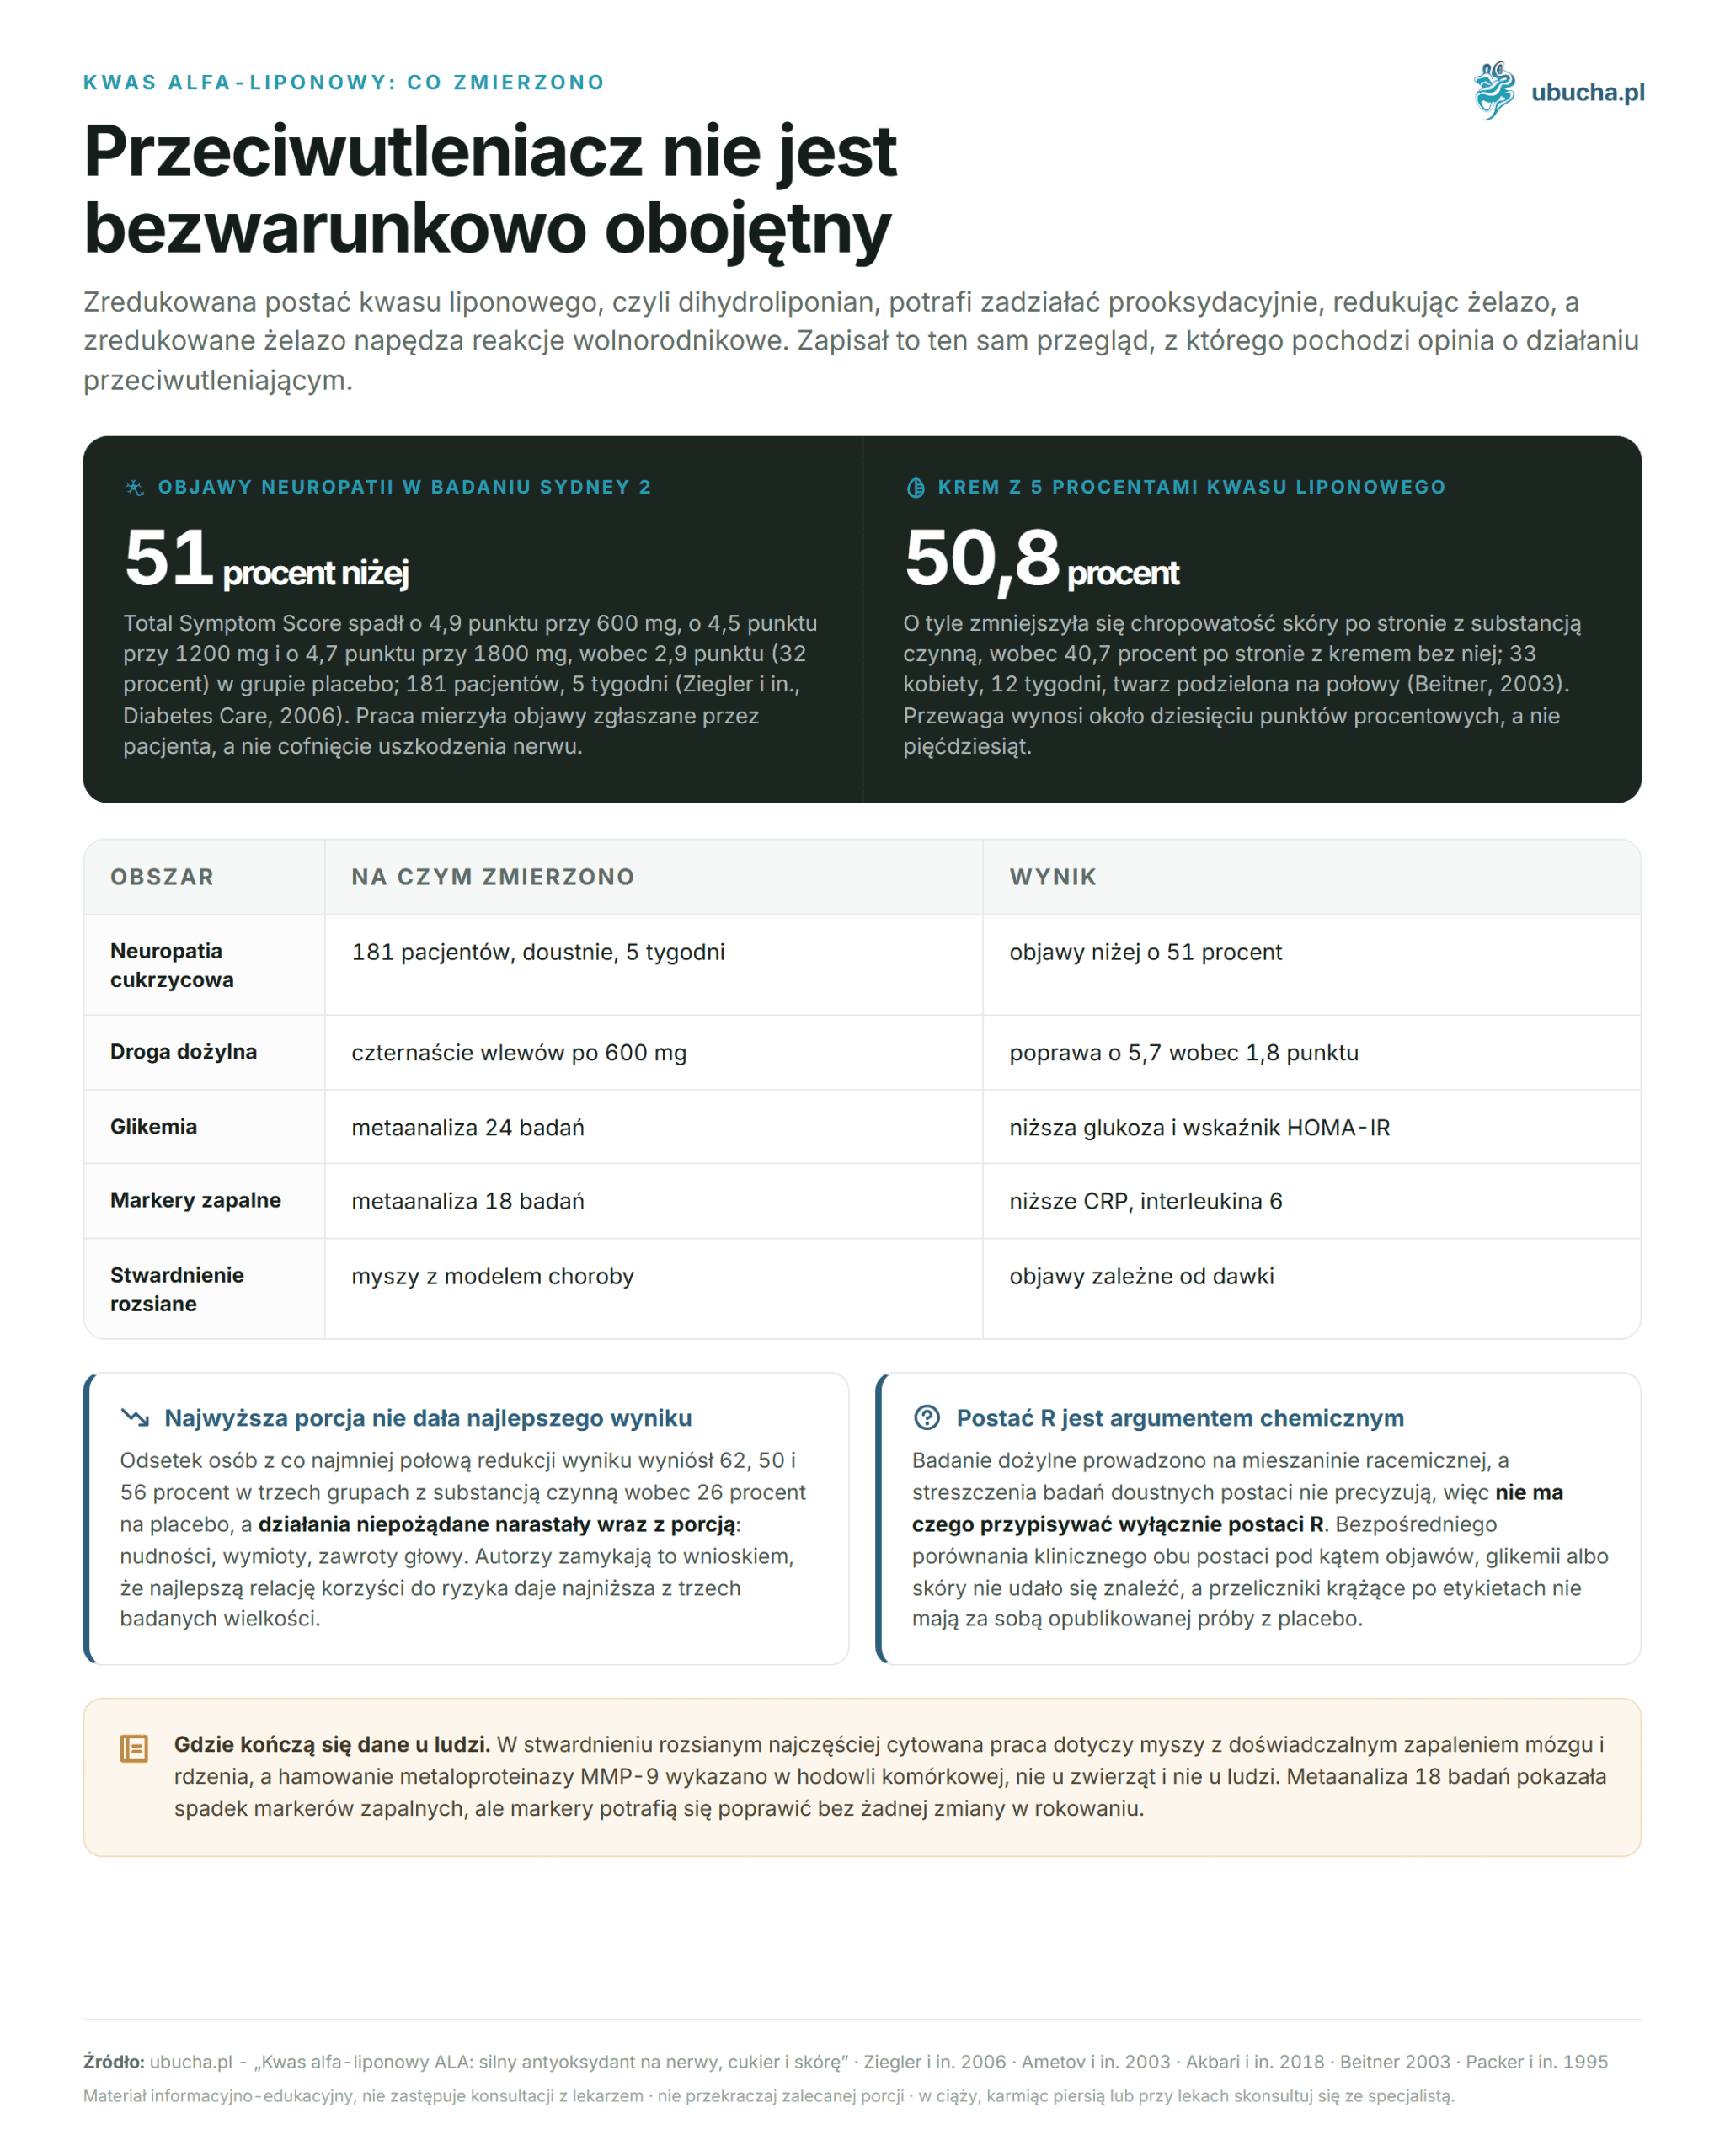
• SYDNEY 2: oral alpha-lipoic acid reduced the Total Symptom Score by 51 percent compared to 32 percent after placebo (181 patients, 5 weeks; Ziegler et al., Diabetes Care, 2006).
• Meta-analysis of 24 studies: lower fasting glucose and lower HOMA-IR index (Akbari et al., Metabolism, 2018).
• Cream with 5 percent alpha-lipoic acid: skin roughness reduced by 50.8 compared to 40.7 percent after cream without the active substance (Beitner, 2003).
• Reduced form of alpha-lipoic acid may act pro-oxidatively by reducing iron.
What is alpha-lipoic acid and where does its reputation come from?
It is an organic sulfur compound produced in the mitochondria, where it serves as a cofactor for two enzyme complexes of the Krebs cycle: pyruvate dehydrogenase and alpha-ketoglutarate dehydrogenase. Without it, both cease to function. The reputation as an antioxidant came later and concerns what the molecule does when administered externally, in amounts greater than physiological.
Packer’s review from 1995 gathered what it reacts with. Lipoic acid and its reduced form, dihydrolipoate, scavenge reactive oxygen species, including superoxide anion and hydroxyl radical. They also protect cell membranes by interacting with vitamin C and glutathione, which in turn can regenerate vitamin E (Packer et al., Free Radical Biology and Medicine, 1995).
This same review notes something that advertising materials omit. Dihydrolipoate can act pro-oxidatively by reducing iron, and reduced iron drives free radical reactions. Therefore, the antioxidant is not unconditionally neutral in every amount and in every biochemical environment.
Why is this molecule particularly popular? It is a combination of two features. The body knows it from its own metabolism, and at the same time, it has behind it randomized placebo-controlled studies in a specific indication. Most antioxidant preparations have only one of these things. The broader context of the antioxidant network itself is described in the text about glutathione, its forms, and dosing.
Does alpha-lipoic acid help with diabetic neuropathy?
This indication has the strongest data. In a multicenter study SYDNEY 2, 281 patients with diabetic sensorimotor polyneuropathy in Russia and Israel received 600, 1200, or 1800 mg of alpha-lipoic acid or placebo orally once a day for 5 weeks, after a one-week placebo run-in period.
The endpoint was the Total Symptom Score, which is the sum of the severity of stabbing pain, burning pain, paresthesia, and numbness in the feet. The score decreased on average by 4.9 points (51 percent) at 600 mg, by 4.5 points (48 percent) at 1200 mg, and by 4.7 points (52 percent) at 1800 mg compared to 2.9 points (32 percent) in the placebo group, and each of the three differences was statistically significant. The percentage of people with at least a 50 percent reduction in the score was 62, 50, 56, and 26 percent respectively (Ziegler et al., Diabetes Care, 2006).
Note that the highest studied dose did not yield the best result, while adverse effects increased with it: nausea, vomiting, dizziness. The authors conclude that the best benefit-to-risk ratio is provided by the lowest of the three studied doses.
An earlier study from the same series, SYDNEY, examined the intravenous route. One hundred and twenty patients were equally divided into alpha-lipoic acid 600 mg administered intravenously five days a week, for a total of fourteen times, and placebo. The Total Symptom Score improved by an average of 5.7 points compared to 1.8 points in the placebo group (Ametov et al., Diabetes Care, 2003). Both studies measured patient-reported symptoms, not the reversal of nerve damage.
What does alpha-lipoic acid do to glycemia and insulin resistance?
It lowers fasting glucose and the insulin resistance index, although the scale of the effect is moderate. Akbari’s meta-analysis included 24 randomized studies in patients with metabolic diseases. Supplementation with alpha-lipoic acid significantly reduced fasting glucose, insulin, HOMA-IR index, and glycated hemoglobin.
This same analysis showed a decrease in triglycerides and total cholesterol and LDL fractions, with no adverse effect on HDL fraction (Akbari et al., Metabolism, 2018). The results were presented as a standardized mean difference, not in milligrams per deciliter, so they do not directly translate to how much a specific measurement will drop for a specific person.
The proposed mechanism is described as stimulation of the glucose transporter GLUT4 and AMPK kinase and reduction of oxidative stress, which disrupts insulin signaling. This explanation comes from laboratory studies, not from measurements in humans included in this meta-analysis, and should be read as such.
The practical consequence follows directly from the above. If a preparation lowers glucose, then when added to insulin or oral medications, it may lower it more than the doctor planned. A conversation before, not after, saves trouble. A comparison of other substances studied in this area can be found in the text about supplements for insulin resistance.
Does alpha-lipoic acid work on the skin?
One controlled study says yes, with local application. Beitner divided the faces of 33 women with an average age of 54.4 years into two halves: one half was smeared twice daily with a cream containing 5 percent alpha-lipoic acid, while the other half received an identical cream without this substance for 12 weeks.
All four assessment methods, from self-assessment by participants to clinical and photographic evaluation, favored the side with alpha-lipoic acid. The most objective of them, laser profilometry, showed a reduction in skin roughness of 50.8 percent on the side with the active substance compared to 40.7 percent on the control side (Beitner, British Journal of Dermatology, 2003).
These two numbers are worth seeing side by side because the difference between them is smaller than the fifty percent suggests. The cream without the active substance also smoothed the skin by over forty percent, which is a common effect of regular moisturizing. The advantage of alpha-lipoic acid is about ten percentage points and comes from one measurement in 33 participants.
Oral supplementation regarding skin appearance does not have a similarly controlled study that we could refer to. Mechanisms cited in cosmetology, such as inhibiting tyrosinase or metalloproteinases that break down collagen, have been described in laboratory conditions, and we could not find confirmation in a placebo trial in humans.
What is the difference between R-ALA and the racemic form?
Chirality. Alpha-lipoic acid has a stereogenic center, so it exists in two mirror-image forms. The body produces only the R form, and only it serves as a cofactor for mitochondrial enzymes. Synthetic lipoic acid is produced as a racemic mixture, meaning half of the R form and half of the S form.
This distinction matters when reading a label, but not when reading evidence. The study that established the effect via the intravenous route was conducted on a racemic form: Ametov describes this directly in the abstract. Oral studies from the SYDNEY series do not specify in the summary which form was administered, so there is nothing to attribute solely to the R form here either.
Manufacturers of preparations with the pure R form usually state that less is needed. We could not find a direct clinical comparison of both forms regarding symptoms of neuropathy, glycemia, or skin, and the ratios circulating on labels do not have a published placebo trial behind them. Until there is one, the advantage of the R form remains a chemical argument, not a clinical one.
The practical conclusion is simple. If you want to rely on what has been measured, look for preparations corresponding to what was administered in studies and discuss this with the doctor managing your diabetes. The choice of form is not a decision worth making based solely on the description on the package.
With which medications can alpha-lipoic acid interact?
The best-documented caution concerns diabetes treatment. A meta-analysis of 24 studies showed that alpha-lipoic acid lowers fasting glucose and insulin, so when added to insulin or oral medications, it may deepen this decrease. This is a reason to talk to a doctor and to monitor glycemia more frequently, not to self-adjust medication doses.
Adverse effects of the preparation itself were counted in SYDNEY 2. Nausea, vomiting, and dizziness occurred more frequently with higher doses, and at the lowest of the studied doses, they were the least common. This is one of those situations where more does not mean better, as the effectiveness between the three studied levels was almost indistinguishable.
A separate note arises from chemistry, not from clinical study. The reduced form of alpha-lipoic acid may act pro-oxidatively by reducing iron, as noted in Packer’s review. In supplementation with iron or in diseases related to its overload, this is an argument for discussion with a specialist.
Other interactions mentioned in advertising materials, including effects on thyroid treatment and mineral absorption, do not have confirmation in available summaries that we could cite here. This does not mean they do not exist, only that they should not be presented as established facts. For medications taken regularly, make decisions with your doctor, not with the supplement’s leaflet.
What is known about alpha-lipoic acid beyond diabetes?
Less than descriptions suggest, and much of it comes from animals. The closest to humans is the second meta-analysis from the same team: 18 studies in patients with metabolic syndrome and related disorders showed a decrease in C-reactive protein, interleukin 6, and tumor necrosis factor alpha after supplementation.
This is a result on inflammatory markers, not on hard endpoints like heart attack or death (Akbari et al., Nutrition and Metabolism, 2018). Markers can improve without any change in prognosis, and with such data, this must be stated directly.
In multiple sclerosis, the most frequently cited work concerns mice. Marracci and colleagues administered alpha-lipoic acid to SJL strain mice with experimental autoimmune encephalomyelitis, an animal model of this disease. The cumulative result of symptom severity decreased depending on the dose, and inhibition of metalloproteinase MMP-9 was shown in cell culture, not in animals and not in humans (Marracci et al., Journal of Neuroimmunology, 2002).
A similar situation exists with aging. Hagen’s work, sometimes cited in relation to Alzheimer’s disease, concerns old rats that were given acetyl-L-carnitine along with R-lipoic acid for a month. Mitochondrial function in hepatocytes and the animals’ motor activity improved, but not cognitive functions and not in humans (Hagen et al., PNAS, 2002). We have separately written about another precursor of antioxidants in the text about N-acetylcysteine.
Frequently asked questions
Does alpha-lipoic acid alleviate symptoms of diabetic neuropathy?
In the SYDNEY 2 study, oral alpha-lipoic acid reduced the Total Symptom Score by 51 percent in the group with the lowest studied dose compared to 32 percent after placebo, over 5 weeks. This is the best-documented use of this substance, but it concerns symptoms, not the reversal of nerve damage.
Is R-ALA better than regular lipoic acid?
The R form is produced by the body, while synthetic preparations are usually a mixture of both forms in equal parts. The intravenous study from the SYDNEY series was conducted on a racemic mixture, and summaries of oral studies do not specify. We could not find a direct clinical comparison of both forms, so the advantage of the R form remains a chemical argument.
Does alpha-lipoic acid lower glucose levels?
A meta-analysis of 24 randomized studies in patients with metabolic diseases showed a significant decrease in fasting glucose, insulin, HOMA-IR index, and glycated hemoglobin. The results were presented as a standardized mean difference, so they do not directly translate to a specific number for a specific person (Akbari et al., 2018).
Does cream with lipoic acid smooth the skin?
In a split-face study involving 33 women, a cream with 5 percent alpha-lipoic acid reduced skin roughness by 50.8 percent over 12 weeks, while an identical cream without the active substance reduced it by 40.7 percent. The advantage is real, but smaller than the first of these numbers suggests.
Does alpha-lipoic acid interact with medications?
The best-documented caution concerns diabetes treatment: since alpha-lipoic acid lowers fasting glucose, when added to insulin or oral medications, it may deepen this decrease. Other interactions mentioned in advertisements do not have confirmation in available summaries that could be cited here.
Does alpha-lipoic acid help with multiple sclerosis?
The most frequently cited work concerns mice with experimental autoimmune encephalomyelitis, an animal model of the disease. Inhibition of metalloproteinase MMP-9 was additionally shown in cell culture. Translating these results to human treatment currently lacks support from clinical studies with placebo.
This article is for informational and educational purposes and does not constitute medical advice. Before starting supplementation, consult with a doctor, especially if you are taking medications regularly, are pregnant or breastfeeding, or have a chronic illness.
Author: Michał Waluk · Published: 2026-06-22 · Updated: 2026-08-16