
CBD Dosage: How Many Drops of Oil to Take, When to Take It, and How to Start (2026)
How many milligrams of CBD are in a drop of oil, what doses were used in clinical studies, and where EFSA set a provisional safety limit.
The question “how many drops of CBD to take” is asked more often than any other question about cannabis, and the answers circulating online share a common flaw: they assign specific milligram numbers supported by studies that never used such doses. Anxiety studies administered single doses of 300 mg. That is about 120 drops of 5% oil, not three drops before bedtime. This scale difference determines what can be expected from supplementation. Here you will find something different than the title promises: the math of converting concentration to milligrams, descriptions of doses from specific clinical studies with participant numbers and results, a provisional safety limit set by EFSA, and a list of what data simply do not show. There is no and will be no dosing table in this text.
KEY INFORMATION
• EFSA set a provisional safe dose of 0.0275 mg CBD per kilogram of body weight per day, about 2 mg per day for a 70 kg person (EFSA Journal, 2026).
• CBD safety cannot be established for people under 25 years old, pregnant and breastfeeding women, and those taking medications.
• 23 of 35 clinical studies reported significant improvement at doses from below 1 to 50 mg per kilogram of body weight per day (Millar et al., British Journal of Clinical Pharmacology, 2019).
• 1 drop of 5% oil contains about 2.5 mg CBD, 10% about 5 mg, 20% about 10 mg.
• A fatty meal increased the area under the curve of CBD concentration about 4-fold and the maximum concentration 14-fold in eight patients (Birnbaum et al., Epilepsia, 2019).
• No proven effective supplemental dose has been established for anxiety, sleep, or pain.
How does CBD work and what does the dose actually affect?
Cannabidiol does not bind strongly to CB1 and CB2 receptors through which THC acts. Instead, it affects a broad group of other targets: ion channels, transporters, and enzymes. The dose determines which of these targets will be reached at all, as some respond only at concentrations difficult to achieve in the body.
The endocannabinoid system is a network of receptors present in the brain, nervous system, immune system, and peripheral tissues, responsible for maintaining the body’s internal balance. CB1 receptors are mainly in the central nervous system, modulating pain, mood, and appetite. CB2 receptors dominate in immune tissues. CBD influences this system indirectly by modulating endogenous cannabinoids, not by directly binding to receptors.
It is worth seeing what happens to the list of mechanisms when seriously examined. A systematic review of molecular pharmacology of CBD by Ibeas Bih et al. (Neurotherapeutics, 2015) counted over 65 separate molecular targets attributed to this compound in the literature, then critically evaluated them. Most were discarded. Some effects were described only at concentrations unlikely to be reached in living organisms due to poor CBD bioavailability, and some were shown in systems demonstrating correlation with a target but not causal proof. After this sieve, mainly targets related to intracellular calcium metabolism remained, including the VDAC1 channel, GPR55 receptor, and T-type calcium channels. The authors add a conclusion you won’t see in marketing materials: in neurological diseases, CBD almost certainly does not act through the endocannabinoid system alone. Long lists of mechanisms come from before this sieve, not after it.
How many milligrams of CBD are in one drop of oil?
One drop of 5% oil contains about 2.5 mg CBD, 10% about 5 mg, and 20% about 10 mg. The formula is simple: multiply the percentage concentration by the volume in milliliters and by 10, then divide by the number of drops in the bottle. A standard dropper gives roughly 20 drops per milliliter.
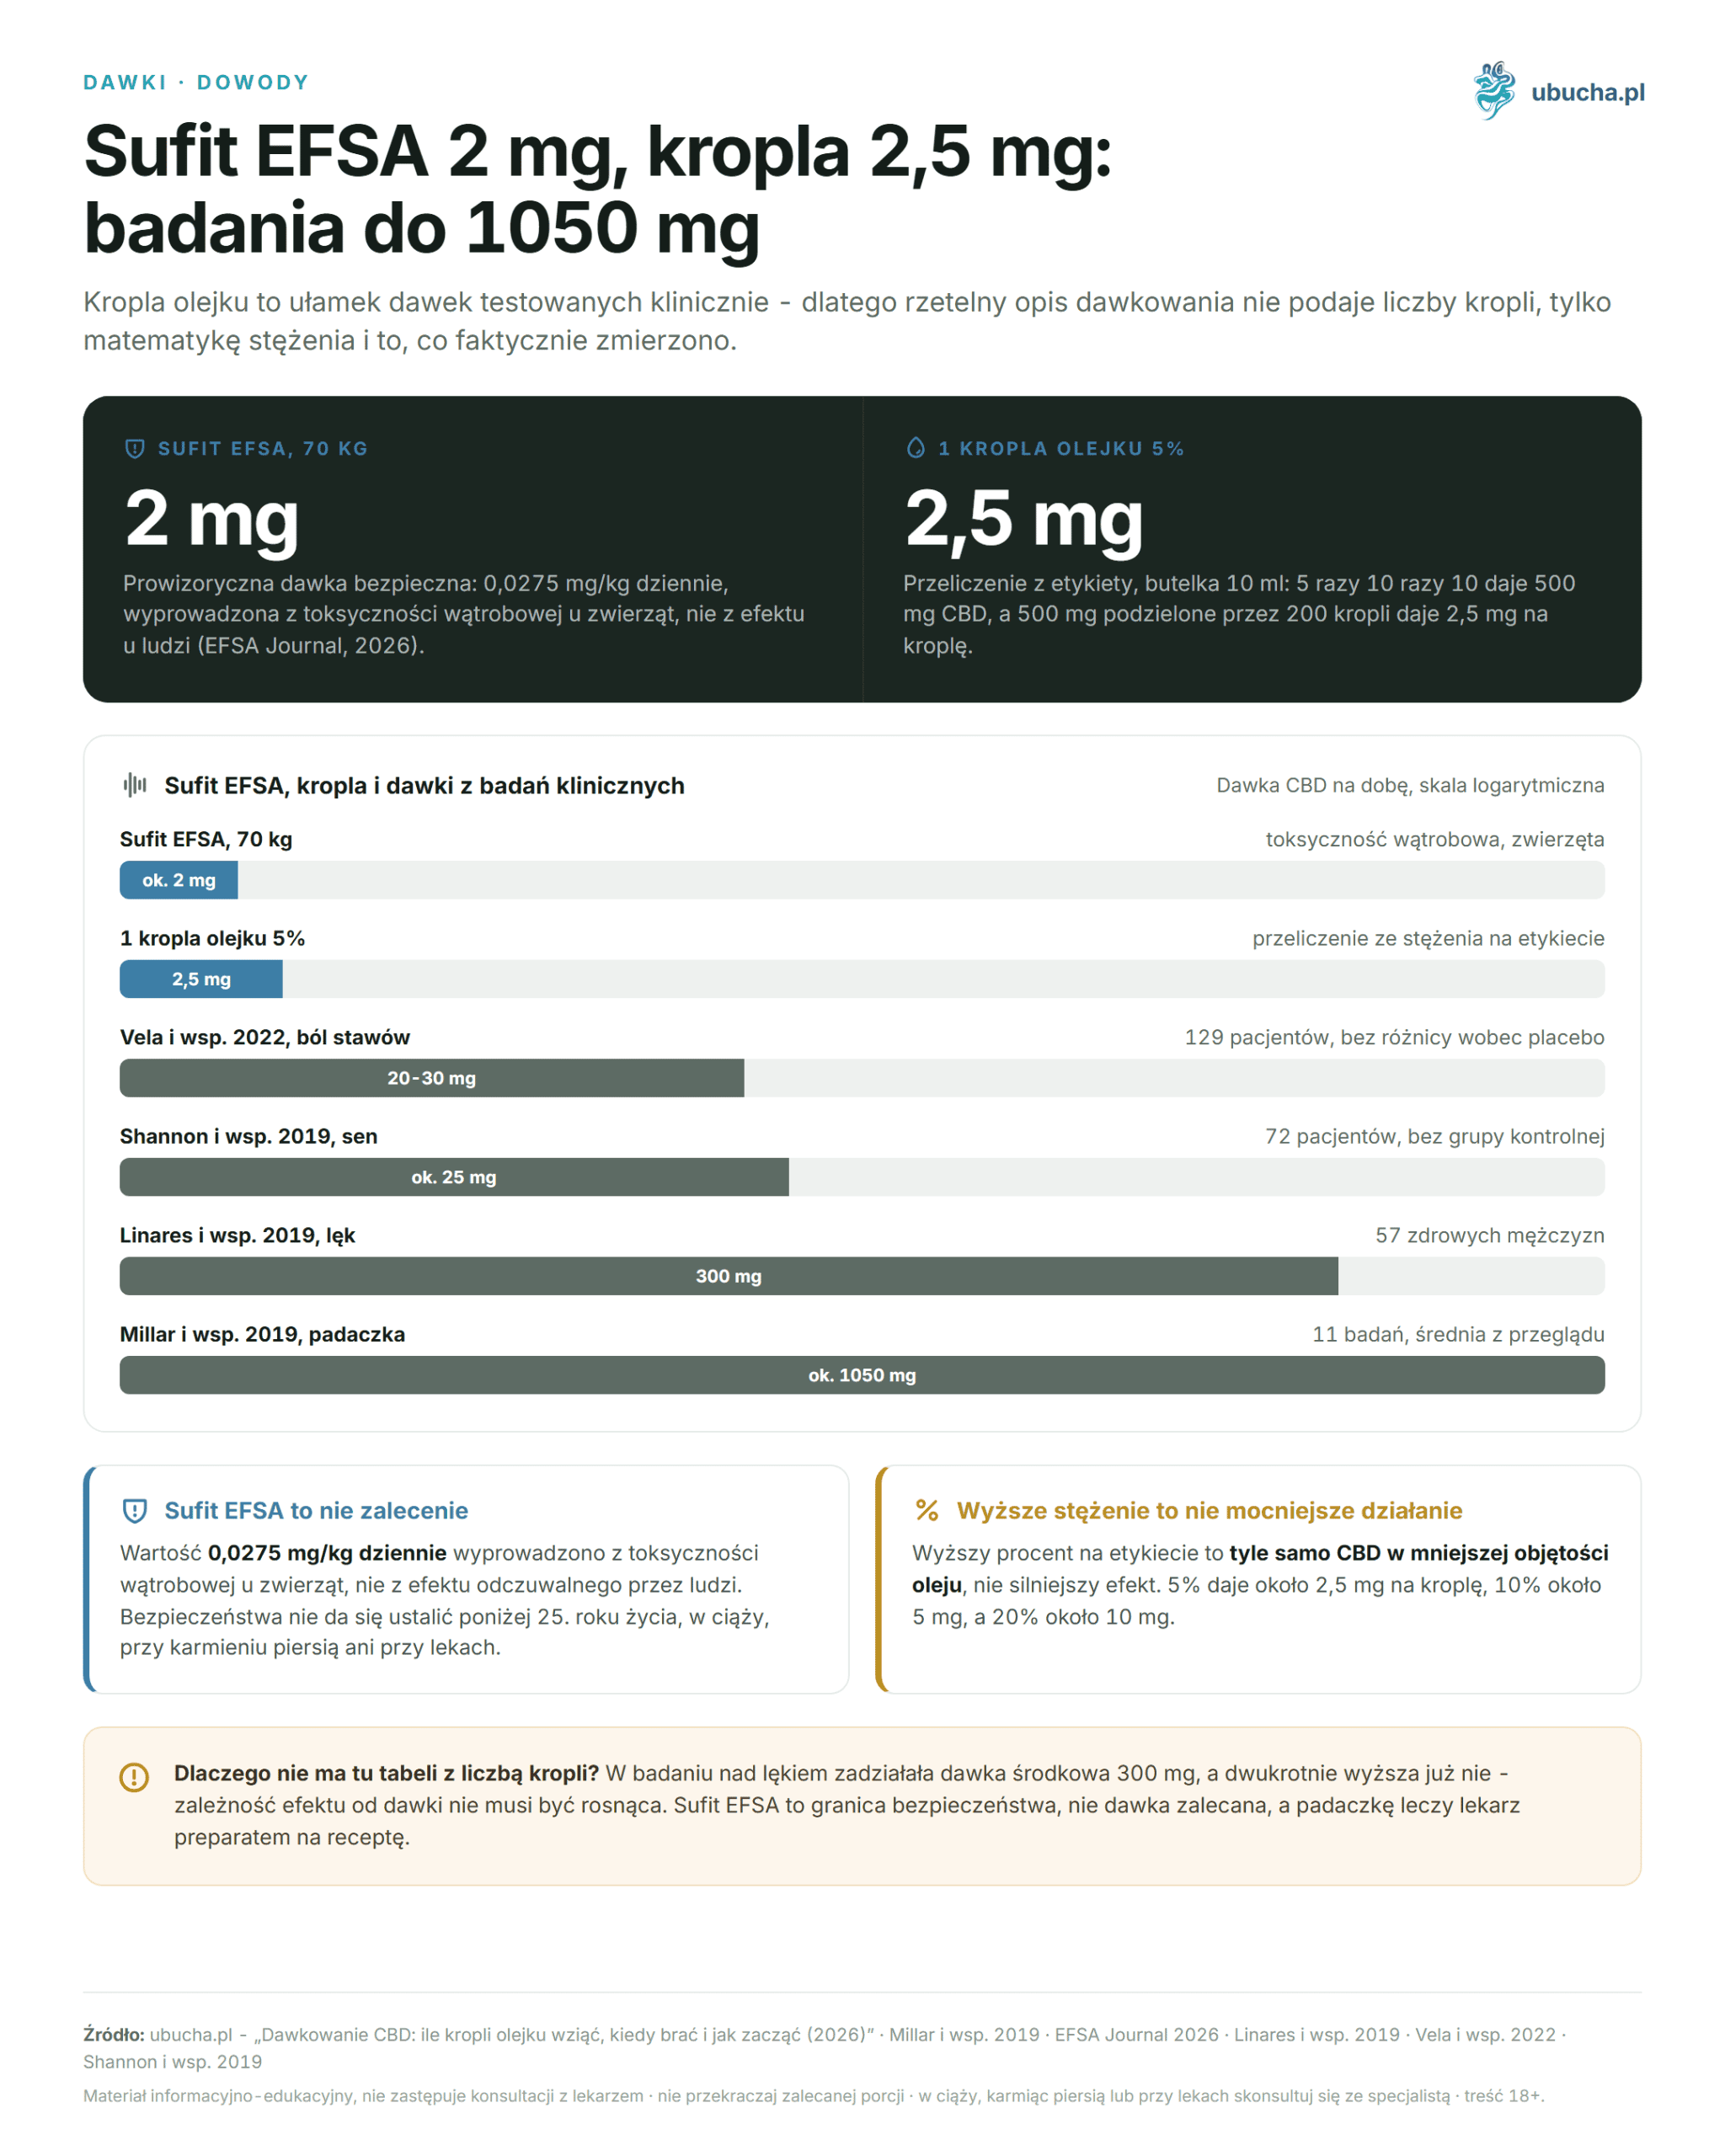
For 5% oil in a 10 ml package, the calculation is: 5 times 10 times 10 equals 500 mg CBD in the bottle, and 500 mg divided by 200 drops gives 2.5 mg per drop. The same method works for any volume. In a 12 ml bottle with 600 mg content, there are 240 drops and again about 2.5 mg per drop, as the concentration has not changed.
| Concentration | CBD in 10 ml bottle | CBD per drop |
|---|---|---|
| 5% | 500 mg | approx. 2.5 mg |
| 10% | 1000 mg | approx. 5 mg |
| 15% | 1500 mg | approx. 7.5 mg |
| 20% | 2000 mg | approx. 10 mg |
Values are approximate because the number of drops depends on the viscosity of the carrier oil and the diameter of the dropper. This arithmetic serves one purpose here: to compare the content of drops with doses actually studied. It is also useful as a quality control check of the label. We noticed when comparing packages that the simplest test is to match the declared percentage concentration with the stated milligram content. If a producer writes 10% and 500 mg in a 10 ml bottle, one of these numbers is false.
Why won’t you find a CBD dosing table here?
Because no such table is supported by data. The only number that can be honestly given is an upper limit, not a recommendation: the European authority set a safe dose, not an effective one, derived from liver toxicity observed in animals, not from any effect felt by humans.
The Panel on Nutrition and Novel Foods of the European Food Safety Authority (EFSA Journal, 2026) recalculated subchronic toxicology studies using the benchmark dose method and applied an uncertainty factor of 400 to derive a provisional safe dose of 0.0275 mg per kilogram of body weight per day. For a 70 kg person, this is about 2 mg per day, less than one drop of 5% oil. This value applies only to supplements with at least 98% pure CBD and no nanoparticles. The panel adds a caveat that settles the matter for many readers: CBD safety cannot be established for people under 25 years old, pregnant and breastfeeding women, and those taking medications.
From the efficacy side, a table cannot be built either, because the dose-effect relationship need not be increasing. In the anxiety study described below, the middle dose worked, but the double dose did not. MacCallum and Russo (European Journal of Internal Medicine, 2018) in a practical dosing discussion write that one should start at modest levels and increase slowly, even over two weeks, precisely because individual response differences are large. This is guidance for the treating physician, not a schedule to write down in your notebook.
What CBD doses were used in clinical studies?
Much higher than what fits in a dropper. A systematic review by Millar et al. (British Journal of Clinical Pharmacology, 2019) covered 35 studies in 13 indications. Significant improvement was reported in 23 of them at doses from below 1 to 50 mg/kg per day. For 70 kg, the lower bound of this range is already 70 mg daily.
The same review contains an observation to place next to any drop table. In small trials on diabetes, Crohn’s disease, fatty liver, or chronic pain, no efficacy signal was detected, and the average dose there was 2.4 mg/kg per day, about 170 mg daily at 70 kg. In eleven epilepsy studies where effect was seen, the average in randomized trials was 15 mg/kg per day.
| Study | Participants and duration | Dose | Result |
|---|---|---|---|
| Linares et al., 2019, anxiety | 57 healthy men, single administration | 150, 300, or 600 mg | only 300 mg worked |
| Vela et al., 2022, joint pain | 129 patients, 12 weeks | 20-30 mg per day | no difference vs placebo |
| Shannon et al., 2019, sleep and anxiety | 72 clinic patients, several months | approx. 25 mg per day | case series, no control group |
| Millar et al., 2019, epilepsy | 11 studies in review | average 15 mg/kg per day | reduced seizure frequency or severity |
The conclusion for the reader is inconvenient but honest. Moore et al. (The Journal of Pain, 2024) collected 16 randomized CBD trials with pain endpoints, using doses from 6 to 1600 mg and durations from single administration to 12 weeks. Fifteen showed no advantage over placebo.
When to take CBD oil: morning or evening?
There is no study comparing the time of CBD administration at the same dose and with the same endpoint. The choice is therefore based on observing your own reaction, not on data. A sensible practical rule is: take it when you notice an effect and stick to that time throughout the observation period.
Pharmacokinetics offers one hint. Millar et al. (Frontiers in Pharmacology, 2018) collected 24 human studies and reported CBD half-life from 1.4 to 10.9 hours after mucosal administration, and from 2 to 5 days with chronic oral dosing. The range is huge, so no clear hourly schedule emerges. If you use CBD daily, the substance accumulates anyway, and a single time point matters less than regularity.
For evening use, remember where popular recommendations come from. A retrospective case series Shannon et al. (The Permanente Journal, 2019) included 72 adult psychiatric clinic patients, 47 with anxiety and 25 with poor sleep. Sleep improvement in the first month was noted in 48 people (66.7%), but results fluctuated in subsequent months. Anxiety decreased in 57 and persisted throughout observation. There was no control group or blinding, so this is an observation, not proof, and for sleep the study itself shows the effect can be transient.
How to take CBD oil for better absorption?
The best documented way to improve absorption is to take CBD with a fatty meal. Other popular tips, including holding drops under the tongue, are based on pharmacological reasoning, not measured numbers.
Birnbaum et al. (Epilepsia, 2019) gave eight patients with refractory epilepsy the same dose of pure CBD in a capsule on an empty stomach and after a high-fat meal. Maximum concentration was on average 14 times higher in the fed state, and area under the curve 4 times higher. Look at confidence interval extremes, not just means: the 90% interval for maximum concentration ranged from 7.5 to 31.9 times, and for area under the curve from 3.4 to 7.8. Differences between patients are huge. A regression meta-analysis Moazen-Zadeh et al. (Cannabis and Cannabinoid Research, 2024), covering 112 arms from 39 studies, confirmed this trend for all available literature.
Sublingual administration is different from popular belief. Millar et al. in their 2018 review stated that the only measured absolute bioavailability of CBD in humans is 31% after smoking, and no such value exists for oral or sublingual routes. Numbers circulating online like 13-19% versus 4-8% have no source. In the 2024 meta-analysis, mucosal administration was even associated with lower exposure than oral. Holding drops under the tongue for a minute won’t hurt but don’t expect it to multiply the amount of CBD reaching the blood several times.
Does body weight affect the CBD dose?
In medicine, yes; in supplementation, no confirmation. Dosing in mg per kilogram is used in refractory epilepsy, where Millar et al.’s review showed an average of 15 mg/kg per day in randomized trials. For doses around a dozen milligrams daily, no one has shown that adjusting for body weight improves anything.
Body weight conversions circulating in marketing materials lack verification studies, so we do not provide them here even for order. It is known that CBD is lipophilic and accumulates in fat tissue, but translating this property into a simple conversion rule remains unproven. Millar et al.’s 2019 review shows that even in clinical studies, doses expressed per kilogram ranged over two orders of magnitude, from below 1 to 50 mg/kg.
The practical conclusion is that body weight may be a starting point in discussion with a doctor but does not replace observation. MacCallum and Russo emphasize that dose is determined by individual response, not a conversion table. If you respond well to a dose you already take, the conversion formula is no reason to increase it. If you feel nothing, converting to kilograms also explains nothing, as it is not a variable that resolves anything in available data.
What are the side effects and interactions of CBD with medications?
The most commonly described adverse effects are drowsiness, diarrhea, and changes in appetite or body weight. A more serious problem is drug interactions, as CBD inhibits liver enzymes metabolizing many prescription drugs and can increase their blood concentration.
The safety profile of CBD itself in the short term is good. WHO’s 2018 report found no signs of addiction potential in humans and no public health problems related to pure CBD use. A summary of adverse effects from clinical data was prepared by Iffland and Grotenhermen (Cannabis and Cannabinoid Research, 2017), indicating fatigue, diarrhea, and appetite changes as most frequently reported. For chronic perspective, EFSA’s 2026 finding applies: safety cannot be established for people taking medications, pregnant and breastfeeding women, and those under 25 years old.
Interactions are a separate story and have a measured scale. Geffrey et al. (Epilepsia, 2015) observed thirteen children with refractory epilepsy taking clobazam simultaneously. Clobazam concentration increased on average by 60%, but the confidence interval ranged from -2 to 91%, so the increase itself is uncertain. The active metabolite, norklobazam, concentration increased by 500% with a range from 90 to 610%, which is a clear signal. Ten of thirteen required clobazam dose reduction. A review by Bergamaschi et al. (Current Drug Safety, 2011) points to the same mechanism pharmacologically: inhibition of hepatic drug metabolism and reduction of P-glycoprotein and other transporter activity. Antiepileptics, anticoagulants, immunosuppressants, some statins, and benzodiazepines require caution. If you take anything regularly, talking to a doctor or pharmacist before adding CBD is the minimum, not excessive caution.
How to assess if the dose is appropriate?
An appropriate dose is the smallest at which you see a change in a recorded log, not just in your impression. Assessment requires at least four weeks of a stable dose, as shorter periods do not distinguish preparation effects from natural mood fluctuations.
Time scale should be taken from studies. The Vela et al. trial (Pain, 2022) treated for 12 weeks before comparing results, and the 2018 Cochrane review (Mücke et al.) on cannabis preparations in neuropathic pain included 16 studies with 1750 participants lasting 2 to 26 weeks. Assessment after three days only tells if you tolerate the preparation.
A simple journal suffices: date, time, dose in milligrams, oil concentration, what you ate before taking it, sleep and symptom rating on a 1 to 10 scale. Two weeks of records before dose change and two after provide a comparison memory cannot supply. Signs the dose is too high include daytime drowsiness, feeling slowed down, and stomach discomfort. In that case, return to the previous level and wait two weeks. If after eight weeks of observation nothing changes, it is wiser to stop increasing and discuss the problem with a doctor. For concentration choice, see the guide which CBD concentration to choose.
Does full spectrum require a different dose than isolate?
Data suggesting full spectrum extract works at lower doses than pure isolate come from one area and observational studies. Applying them to any use has no basis, though the direction is interesting.
An observational data meta-analysis Pamplona et al. (Frontiers in Neurology, 2018) collected 670 patients with refractory epilepsy. Seizure frequency improvement was reported by 71% of those taking CBD-rich extracts versus 46% taking pure CBD, with average doses of 6.0 and 25.3 mg/kg per day respectively. However, the authors add a rarely mentioned caveat: using the standard criterion of at least 50% seizure reduction, the difference between preparations disappears, 37% versus 42%. The entourage effect remains a hypothesis requiring controlled studies, not an established dosing rule.
One more thing matters when choosing oil type. Full spectrum products contain trace amounts of THC. The Polish threshold for industrial hemp is 0.3%, counted as the sum of delta-9-THC and tetrahydrocannabinolic acid (THCA) converted to dry weight, rounded to one decimal place; based on Article 4 point 5 of the Act of July 29, 2005 on counteracting drug addiction (consolidated text Journal of Laws 2023 item 1939), as amended by the Act of March 24, 2022 (Journal of Laws 2022 item 763). The national threshold corresponds to the EU threshold but is not derived from EU regulation. At high daily doses, the amount of THC taken increases proportionally. This will not cause intoxicating effects but may matter for people tested at work with sensitive immunochemical tests. In such cases, isolate or broad spectrum THC-free products are a safer choice.
How to dose CBD in seniors, women, and athletes?
The biggest difference concerns seniors and results not from different physiology but from the number of medications taken simultaneously. After 65 years, both interaction risk and sensitivity to side effects increase, so slower dose escalation under medical supervision is practically justified.
A prospective observation Abuhasira et al. (Journal of Clinical Medicine, 2019) included 184 patients over 65 years old with an average age of 81.2, treated with medical cannabis, i.e., products also containing THC, not pure CBD. After six months, 58.1% continued therapy, 84.8% reported general improvement, and 33.6% adverse effects, most often dizziness, drowsiness, and fatigue. The authors recommend special caution due to polypharmacy and age-related pharmacokinetic changes.
For women, there is a thesis about dose dependence on cycle phase. Cannabinoid receptor modulation by estrogens is described in preclinical studies, but no clinical study has translated this into dosing recommendations. Those who notice differences between phases can record them in a journal, but hard numbers lack support so far. The topic is developed in the text on CBD for menstrual pain. Athletes face a regulatory, not dosing, problem: the WADA prohibited list excludes CBD from the ban, but other cannabinoids, including THC, remain prohibited. Therefore, isolate is safer for anti-doping controlled competitions.
How to plan observation for the first 8 weeks?
The plan has three elements: one defined goal, a stable dose maintained for at least two weeks, and a journal. Without a goal, you cannot assess if anything changed, and without a record, assessment reduces to a memory from a month ago. The dose is a variable you set with a doctor or pharmacist, not from the article.
Start by naming the problem measurably. Instead of “I want to feel better,” write “I want to fall asleep faster than in 30 minutes” or “I want to reduce knee pain from 6 to 4 on a ten-point scale.” For the first two weeks, keep a record without any change to establish a baseline. Without this point, any later assessment compares to memory, which is unreliable in such matters.
In weeks three and four, change nothing except what you agreed with the specialist and keep recording. If you feel drowsy after the morning dose, move it to evening instead of stopping observation. In weeks five and six, decide with your doctor whether to change anything or stay with what works. In weeks seven and eight, compare average ratings from the last two weeks with the baseline. An improvement of two points on a ten-point scale signals to keep the dose. No change after eight weeks means further increases probably won’t help and it’s better to discuss the problem with a doctor. More on applications is in texts about CBD for back and joint pain and CBD for anxiety and neurosis.
Frequently Asked Questions
Is it possible to give a number of CBD drops to start with?
Not in a way supported by research, which is why you won’t find that number here. EFSA has only set a provisional safe dose of 0.0275 mg per kilogram of body weight per day, which is about 2 mg per day for a 70 kg person. This is an upper limit derived from liver toxicity, not a dose with confirmed efficacy.
How to convert CBD content from milligrams to drops?
Multiply the percentage concentration by the volume in milliliters and by 10, then divide the result by the number of drops in the bottle. For a 5% oil in a 10 ml package, this gives 500 mg over about 200 drops, or roughly 2.5 mg per drop. For 10% it’s about 5 mg, for 20% about 10 mg.
Can you overdose on CBD?
Acute toxicity of CBD is low, and WHO in its 2018 report found no potential for addiction or public health problems with pure CBD. Chronic safety is a separate matter. EFSA in 2026 concluded that safety cannot be established for people taking medications, pregnant women, and those under 25 years old.
How long do you need to take CBD to assess the effect?
Count in weeks, not days. The Vela et al. trial (Pain, 2022) lasted 12 weeks, and the 2018 Cochrane review collected 16 studies lasting from 2 to 26 weeks. Assessment after three days only tells you if you tolerate the preparation well.
Does CBD interact with medications?
Yes. CBD inhibits CYP3A4 and CYP2C19 enzymes, so it can increase the concentration of drugs metabolized by the same pathway. Geffrey et al. (Epilepsia, 2015) observed thirteen children whose norklobazam concentration increased by 500%. Consult your doctor before combining CBD with prescription medications.
Should the oil be held under the tongue or swallowed immediately?
Holding drops under the tongue for about a minute is common practice, but a numerical advantage over swallowing has not been measured. Millar et al. (Frontiers in Pharmacology, 2018) stated that the only measured absolute bioavailability of CBD in humans is 31% after smoking. No such value exists for oral or sublingual routes.
Can doses from anxiety studies be replicated with oil?
Not in practice. Linares et al. (Revista Brasileira de Psiquiatria, 2019) gave 57 healthy men a single dose of 150, 300, or 600 mg, and only the middle dose reduced anxiety. 300 mg corresponds roughly to 120 drops of 5% oil, so applying this result to a few drops daily has no basis.
Does a higher oil concentration mean stronger effects?
No. A higher concentration means the same amount of CBD in a smaller volume of oil, not a stronger effect of the substance. Changing concentration only affects the number of drops needed to measure the same dose, so it is a matter of convenience and price per milligram, not product efficacy.
We collected the full offer on this topic in the hemp oils category.
This article is for informational and educational purposes and does not constitute medical advice. Before starting cannabis or CBD for therapeutic purposes, consult a doctor, especially if you take other medications, are pregnant, or breastfeeding.
Author: Michał Waluk · Published: 2026-06-22 · Updated: 2026-08-11