
Colostrum: what is it, properties and is it worth supplementing beyond infancy?
Bovine colostrum under the microscope of research: how much IgG really survives digestion, what trials showed in athletes, whether it raises IGF-1, and who should not use it.
Colostrum, in Polish siara, is the first secretion of the mammary gland after childbirth. For a calf, it is the only source of antibodies, as immunoglobulins do not pass through the placenta in cows. Hence the simple marketing shortcut: since colostrum builds the immunity of a newborn, it should also build yours. This shortcut does not withstand the collision with data. Supplements contain only bovine colostrum, and the adult intestine does not absorb antibodies from it like the intestine of a newborn. Below you will find what has really been measured in adults: how many immunoglobulins survive the journey through the stomach, how trials went with athletes, what measurements of gut barrier and IGF-1 levels showed, and who should not use colostrum. Each number has a reference to the source work.
KEY INFORMATION
• Bovine colostrum: 34 to 87 g IgG1 and 1.5 to 5 g lactoferrin per liter (Playford and Weiser, 2021).
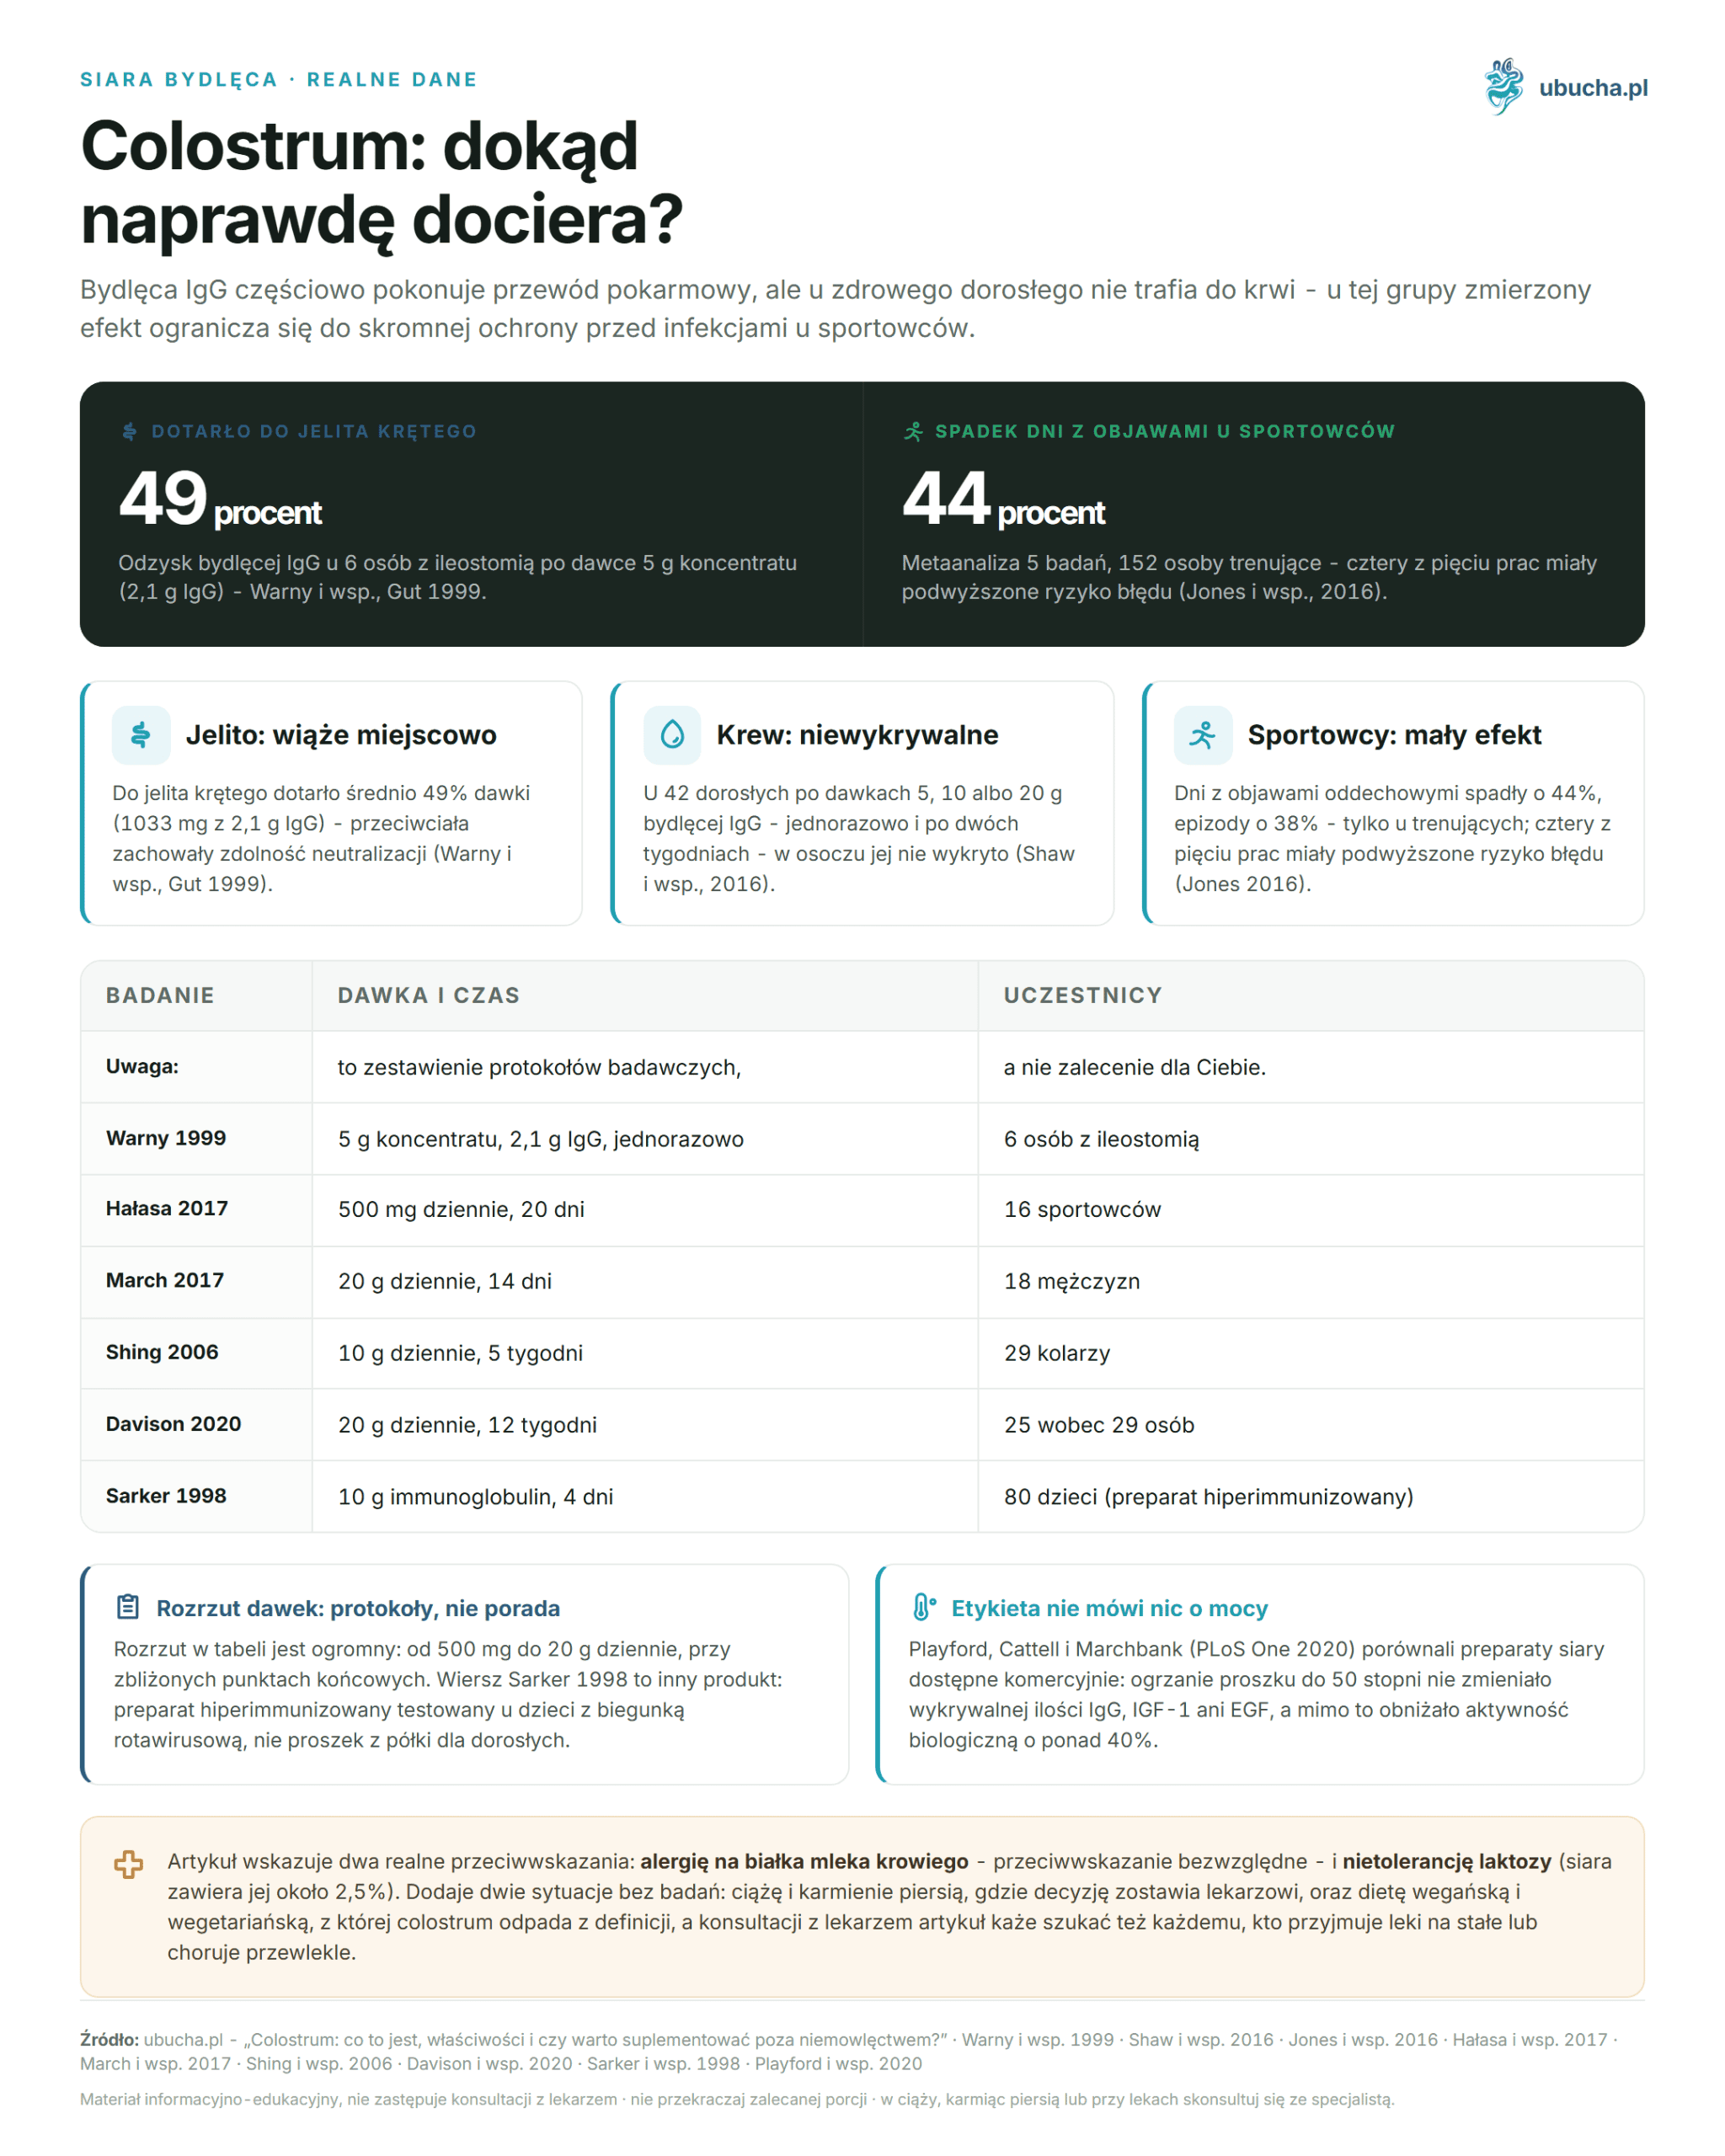
• In 6 individuals with ileostomy, 49% of the administered bovine IgG reached the end of the small intestine (Warny et al., 1999).
• Meta-analysis of 5 studies, 152 training individuals: fewer days with respiratory symptoms (Jones et al., 2016).
• 20 g daily for 12 weeks did not raise IGF-1 in plasma (Davison et al., 2020).
• Contraindications: allergy to cow’s milk proteins and lactose intolerance.
What is colostrum and is human colostrum found in supplements?
Colostrum is the secretion of the mammary gland from the first hours after childbirth. In supplements, there is only bovine colostrum, obtained after calving. No one sells human colostrum in capsules, so observations from feeding newborns with breast milk do not transfer to a preparation for adults.
The difference between the two fluids works both ways. Bovine colostrum has significantly more immunoglobulins than human, as a calf is born without any antibodies from its mother. However, it has about ten times less lactoferrin, as noted by Playford and Weiser in their 2021 review. Citing studies on human colostrum as an argument for cow colostrum capsules is therefore a substitution of subjects.
The composition changes dramatically within the first day. The table compares the concentrations provided by Playford and Weiser for bovine colostrum and for mature cow’s milk.
| Component | Bovine colostrum | Mature milk |
|---|---|---|
| IgG1 (g/l) | 34.0 to 87.0 | 0.31 to 0.40 |
| IgG2 (g/l) | 1.6 to 6.0 | 0.03 to 0.08 |
| IgA (g/l) | 3.2 to 6.2 | 0.04 to 0.06 |
| IgM (g/l) | 3.7 to 6.1 | 0.03 to 0.06 |
| Lactoferrin (g/l) | 1.5 to 5 | 0.02 to 0.75 |
| Lactoperoxidase (mg/l) | 11 to 45 | 13 to 30 |
| Lysozyme (mg/l) | 0.14 to 0.7 | 0.07 to 0.6 |
| Lactose | about 2.5% | 4.7 to 5.0% |
Do antibodies from colostrum reach the blood and strengthen immunity?
No, they do not. Bovine IgG acts in the intestinal lumen, where it binds pathogens and their toxins, but does not penetrate into the bloodstream in adults. The statement “antibodies from colostrum strengthen your immunity” therefore confuses two different phenomena: local neutralization in the gastrointestinal tract and systemic immunity.
How much of it survives the stomach? Warny et al. (Gut 1999) administered 5 g of a concentrate containing 2.1 g of bovine IgG to six volunteers with ileostomy and collected intestinal contents. On average, 1033 mg was recovered, which is 49% of the dose, and the antibodies retained their ability to neutralize toxins. Recovery depended on transit time: 68% with a transit shorter than two hours versus 36% with a slower one. Administration with an antacid or omeprazole did not improve anything.
The second part of the answer concerns the blood. Shaw et al. (2016) administered a single dose of 5, 10, or 20 g of bovine immunoglobulin preparation to 42 healthy adults, and then divided doses for two weeks. Bovine IgG was detected in stool. It was not found in measurable amounts in plasma after either a single dose or two weeks. Thus, half the dose reaches further than the duodenum but remains in the digestive tract.
Does colostrum reduce respiratory infections in athletes?
This is an area where data actually exist, although modest. A meta-analysis by Jones et al. (BMC Sports Science, Medicine and Rehabilitation 2016) included 5 randomized studies and 152 participants, all regularly training, with an observation period of 8 to 12 weeks.
Results: the number of days with upper respiratory symptoms decreased by 44% (incidence rate 0.56, confidence interval 0.43 to 0.72), and the number of episodes decreased by 38% (0.62, interval 0.40 to 0.99). The authors add a caveat that is not present in advertisements: due to incomplete reporting of methods, four out of five studies were rated as having moderate or high risk of error.
A frequently cited study by Crooks et al. (International Journal of Sport Nutrition and Exercise Metabolism 2006) measured something else. It involved 35 long-distance runners aged 35 to 58, the supplementation lasted 12 weeks, and the endpoint was secretory IgA in saliva. It increased by 79%. The authors themselves warn against extrapolating this to health, as the sample was small and the variability of results was large.
We noted when compiling the literature that this work is sometimes cited as evidence of fewer infections. It is not, as infections were not counted in it. The endpoint was the concentration of the antibody in saliva, which is a surrogate marker, and the authors themselves advise against extrapolating it to health.
What do studies say about intestinal permeability during exercise?
Let’s start with the terminology. “Leaky gut” is not a clinical diagnosis and there are no diagnostic criteria. Studies on colostrum measured surrogate markers: the ratio of lactulose to rhamnose or mannitol, zonulin in stool, and I-FABP protein, released upon damage to enterocytes.
In the study by Marchbank et al. (2011), twelve volunteers took colostrum or placebo for 14 days before standardized exercise that raised internal temperature by an average of 1.4 degrees. In the placebo arm, permeability increased 2.5-fold, while with colostrum the increase was 80% less. March et al. (2017) repeated the observation in 18 men with 20 g daily for 14 days: after exercise, the ratio of lactulose to rhamnose and I-FABP concentration were lower than in the placebo group.
A Polish study by Hałasa et al. (Nutrients 2017) involved 16 athletes and a dose of 500 mg daily for 20 days. After the intervention, results were within normal limits, and the difference from placebo also concerned zonulin in stool. The second model involves anti-inflammatory drugs: Playford et al. (Clinical Science 2001) administered indomethacin to 7 volunteers for 5 days, and in the control arm permeability increased threefold, while with simultaneous administration of colostrum it did not increase significantly.
The numbers of participants speak for themselves: 7, 12, 16, and 18 individuals. These are laboratory indicators in very small trials, not treatment of a disease.
Does colostrum improve sports performance and body composition?
The effects are small and mainly occur during periods of high training load. Shing et al. (British Journal of Sports Medicine 2006) divided 29 trained road cyclists into a group taking 10 g of colostrum protein concentrate daily and a whey group.
After five weeks of normal training, the effect on the time for a 40 km ride was deemed unclear. Only after five days of high-intensity training did the colostrum group achieve a 1.9% improvement from baseline and maintained starting heart rate. That is the entire measured effect.
Body composition was studied by Antonio et al. (Nutrition 2001): 20 g daily for 8 weeks in individuals training at least three times a week. The colostrum group increased lean mass without bone by an average of 1.49 kg, while the whey group gained 2.11 kg of body mass. Strength and time to exhaustion did not change in either group. A newer trial by Durkalec-Michalski et al. (European Journal of Sport Science 2025) after 12 weeks in men training for endurance showed support for aerobic capacity but no effect on body composition.
The popular online figure of “plus 1.5 kg of lean mass in cyclists” combines two different studies. The gain comes from Antonio et al., while the cyclists are from Shing et al.
Does colostrum raise IGF-1 and is this a problem for athletes?
In studies, it does not raise. The question is relevant because the World Anti-Doping Agency advises athletes against colostrum due to concerns about increased IGF-1, and there is also a question about long-term safety.
This was checked by Davison, Jones, Marchbank, and Playford (European Journal of Nutrition 2020) in three protocols. The first: 40 g of colostrum once in 16 healthy men with moderate exercise for 4.5 hours. The second: 20 g daily for 4 weeks, with 10 people per arm. The third: 20 g daily for 12 weeks, with 25 on colostrum and 29 on placebo. The baseline IGF-1 concentration was 130 ng/ml and did not differ between groups after intervention in any of the protocols.
Earlier Finnish studies reported an increase in IGF-1 in serum after colostrum, but the same group provided an explanation. In the second part of the study Mero et al. (Journal of Applied Physiology 2002) orally administered isotopically labeled recombinant human IGF-1 and after an hour found mainly fragments weighing 0.6 kDa, accounting for 96% of radioactivity. The authors’ conclusion was clear: the data do not support the absorption of IGF-1 from bovine colostrum. Therefore, the hormonal panic surrounding this component has no basis in measurements.
How does lactoferrin differ from colostrum in studies?
These are two different interventions, and the results of one should not be attributed to the other. Lactoferrin is a single iron-binding protein, studied in isolated form in doses of hundreds of milligrams. Colostrum is a matrix in which lactoferrin is only one of the components.
The scale is important here. In bovine colostrum, lactoferrin is present at 1.5 to 5 g per liter, which is about one-tenth the concentration found in human colostrum (Playford and Weiser, 2021). Powder manufacturers rarely declare its content, so you cannot read from the label whether the portion approaches the doses studied separately.
How does lactoferrin itself perform? In a randomized study Oda et al. (Nutrients 2023) assigned 157 healthy adults to bovine lactoferrin at a dose of 200 mg daily or to placebo for 12 weeks, analyzing 145 individuals. Overall respiratory and systemic symptom scores were lower in the lactoferrin group, and researchers also noted higher expression of activation markers on plasmacytoid dendritic cells. This is an interesting signal for the isolated protein. It is not evidence that colostrum powder does the same, and labels combining both ingredients should be read accordingly.
What is known about colostrum in infectious diarrhea?
The strongest data in this area come from hyperimmunized preparations, i.e., from cows deliberately vaccinated against a specific pathogen. This is not the same product as the powder from the shelf, although both are called colostrum.
In a study by Sarker et al. (Pediatric Infectious Disease Journal 1998), eighty children with rotavirus diarrhea received 10 g of immunoglobulins isolated from colostrum of cows immunized against four serotypes of rotavirus for 4 days, including 3.6 g of specific antibodies. The volume and frequency of stools were lower, the need for rehydration fluids was less, and the virus disappeared from stool on average in 1.5 days compared to 2.9 days on placebo. A similar scheme was used by Mitra et al. (Acta Paediatrica 1995), also in rotavirus diarrhea in children.
The third group includes patients with severe immune deficiency. Rump et al. (Clinical Investigator 1992) used immunoglobulins from bovine colostrum in HIV-infected patients with chronic diarrhea. All these works concern the treatment of ongoing infections in individuals at increased risk, conducted with a preparation of known antibody titer. Transferring them to prevention in healthy adults is an abuse.
Who should not use colostrum?
Two contraindications are real and common. The first is an allergy to cow’s milk proteins: colostrum contains casein and beta-lactoglobulin, which is indicated in the literature as the main immunogen for individuals allergic to cow’s milk. A colostrum preparation is not safer in this regard than milk.
The second is lactose intolerance. Colostrum contains about 2.5% lactose, which is less than mature milk, but with portions of several grams, as used in sports studies, the lactose load ceases to be symbolic. Some manufacturers remove lactose during processing, and such information should be on the packaging.
There are situations without data. Pregnancy and breastfeeding have not been the subject of studies on colostrum supplementation, so the decision should be left to the doctor. For vegans and vegetarians avoiding animal products, colostrum is excluded by definition.
A separate issue is the quality of the raw material. Playford, Cattell, and Marchbank (PLoS One 2020) examined commercially available colostrum preparations for humans and compared twenty preparations, finding a sixfold difference in biological activity among them, large enough to hinder the comparison of clinical studies. The same team showed where part of this variability comes from: heating the powder to 50 degrees did not change the detectable amount of IgG, IGF-1, or growth factors such as EGF, yet it reduced biological activity by over 40%. Standard processing includes pasteurization, usually about 15 seconds at 72 degrees, followed by drying to powder (Playford and Weiser, 2021). A manufacturer providing the origin of the raw material gives you more than one promising immunity.
What doses and times were used in studies?
The table below collects what was actually administered to participants in the works cited in this article. This is a summary of research protocols, not a recommendation for you. The range is enormous: from 500 mg to 20 g daily, with similar endpoints.
| Study | Dose | Time | Participants |
|---|---|---|---|
| Warny 1999 | 5 g concentrate, 2.1 g IgG | once | 6 individuals with ileostomy |
| Hałasa 2017 | 500 mg daily | 20 days | 16 athletes |
| March 2017 | 20 g daily | 14 days | 18 men |
| Shing 2006 | 10 g daily | 5 weeks | 29 cyclists |
| Antonio 2001 | 20 g daily | 8 weeks | active adults |
| Davison 2020 | 20 g daily | 12 weeks | 25 versus 29 individuals |
| Sarker 1998 | 10 g immunoglobulins daily | 4 days | 80 children |
| Oda 2023 (lactoferrin) | 200 mg daily | 12 weeks | 145 adults |
From our observations of this market, it appears that labels are silent on two things described precisely in studies: the content of IgG in dry mass and the time from birth when the raw material was collected. Without these numbers, comparing the price per gram says nothing. When rebuilding the gut after antibiotic therapy, a comparison with the entry on supplements after antibiotics is useful, and when training loads are concerned, a comparison with L-glutamine is helpful.
Frequently asked questions
Six questions that come up most often regarding bovine colostrum in adults.
Should colostrum be taken on an empty stomach?
None of the discussed studies compared the timing of intake. An indirect hint is provided by the work of Warny et al. (Gut 1999): recovery of bovine IgG was higher in individuals with shorter transit to the ileum, 68% versus 36%. Antacid or omeprazole did not improve recovery.
Is colostrum safe for lactose intolerance?
Bovine colostrum contains lactose, about 2.5% according to the review by Playford and Weiser (2021), which is less than mature milk. Small portions may be tolerated, but several grams of powder daily can cause bloating and loose stools. Allergy to cow’s milk proteins is an absolute contraindication.
Does colostrum heal leaky gut?
No, because leaky gut is not a clinical diagnosis. Studies measured surrogate markers: the ratio of lactulose to rhamnose, zonulin in stool, and I-FABP protein. Trials ranged from 7 to 18 participants and concerned barriers stressed by exercise or anti-inflammatory drugs.
Does colostrum raise IGF-1 in the blood?
In the study by Davison et al. (European Journal of Nutrition 2020) it did not raise. 40 g was tested once in 16 men, 20 g daily for 4 weeks, and 20 g daily for 12 weeks. In none of the protocols did the plasma concentration differ from placebo.
How does colostrum differ from lactoferrin in capsules?
Lactoferrin is a single protein, colostrum is a whole matrix. In bovine colostrum, lactoferrin is present at 1.5 to 5 g per liter, about one-tenth the concentration found in human colostrum. Results from studies on isolated lactoferrin are not evidence of the effects of colostrum powder.
Will colostrum help someone who does not train?
It is unknown, as no one has properly tested this. A meta-analysis by Jones et al. (2016) included 5 studies and 152 participants, all regularly training. Studies on gut barrier were also conducted in athletes. Data for a less active person is lacking.
Bovine colostrum and other immune support can be found in the supplements category.
This article is for informational and educational purposes and does not constitute medical advice. Before starting supplementation, consult your doctor, especially if you are taking medications regularly, are pregnant or breastfeeding, or have chronic illnesses.
Author: Michał Waluk · Published: 2026-06-15 · Updated: 2026-08-11