
Medical Marijuana and CBD for Insomnia: Can Cannabis Treat Sleep Disorders? Can CBD and THC Help with Sleep?
CBD and THC and sleep: what polysomnography really showed, how to dose, what interactions with medications exist, what the Polish legal status is, and when to see a doctor.
Insomnia is one of the most common reasons people turn to cannabis on their own. The question is whether the evidence keeps pace with this practice. The answer is less impressive than product descriptions suggest: a systematic review of 14 preclinical studies and 12 clinical studies states outright that the evidence is currently insufficient to recommend cannabinoids in the routine treatment of any sleep disorder (Suraev i wsp., 2020). This does not mean that nothing is known. Enough is known to separate THC from CBD, describe what each does to the architecture of the night, and show where supplementation ends and sleep medicine begins. This text organizes the mechanisms, numbers from studies, dosing, interactions with medications, and the Polish legal status.
KEY INFORMATION
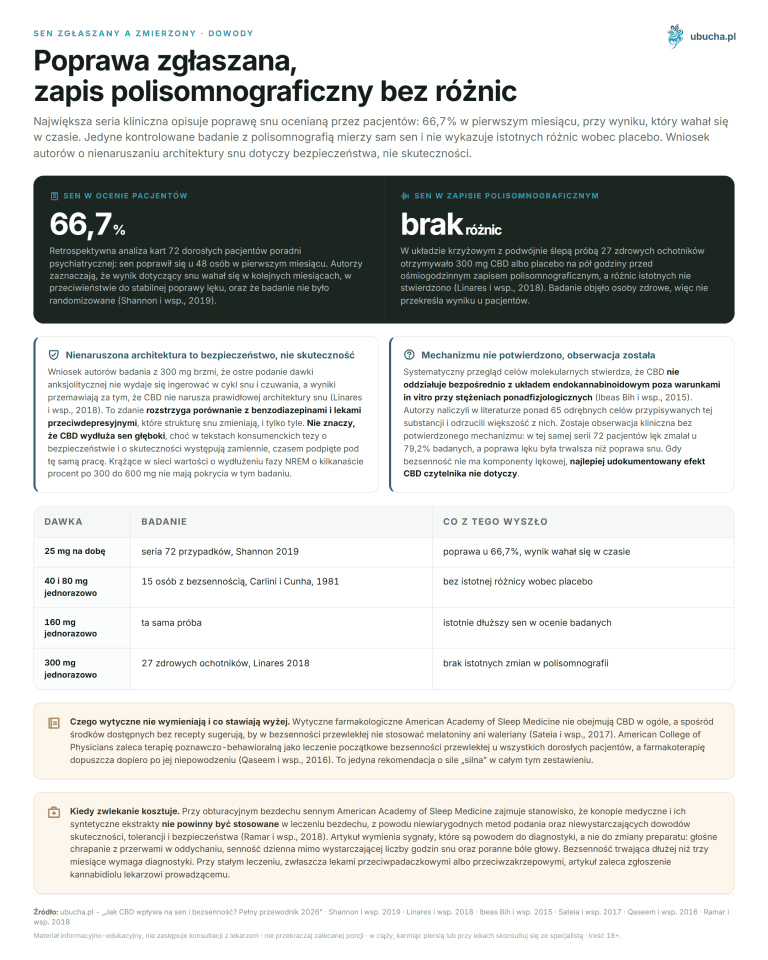
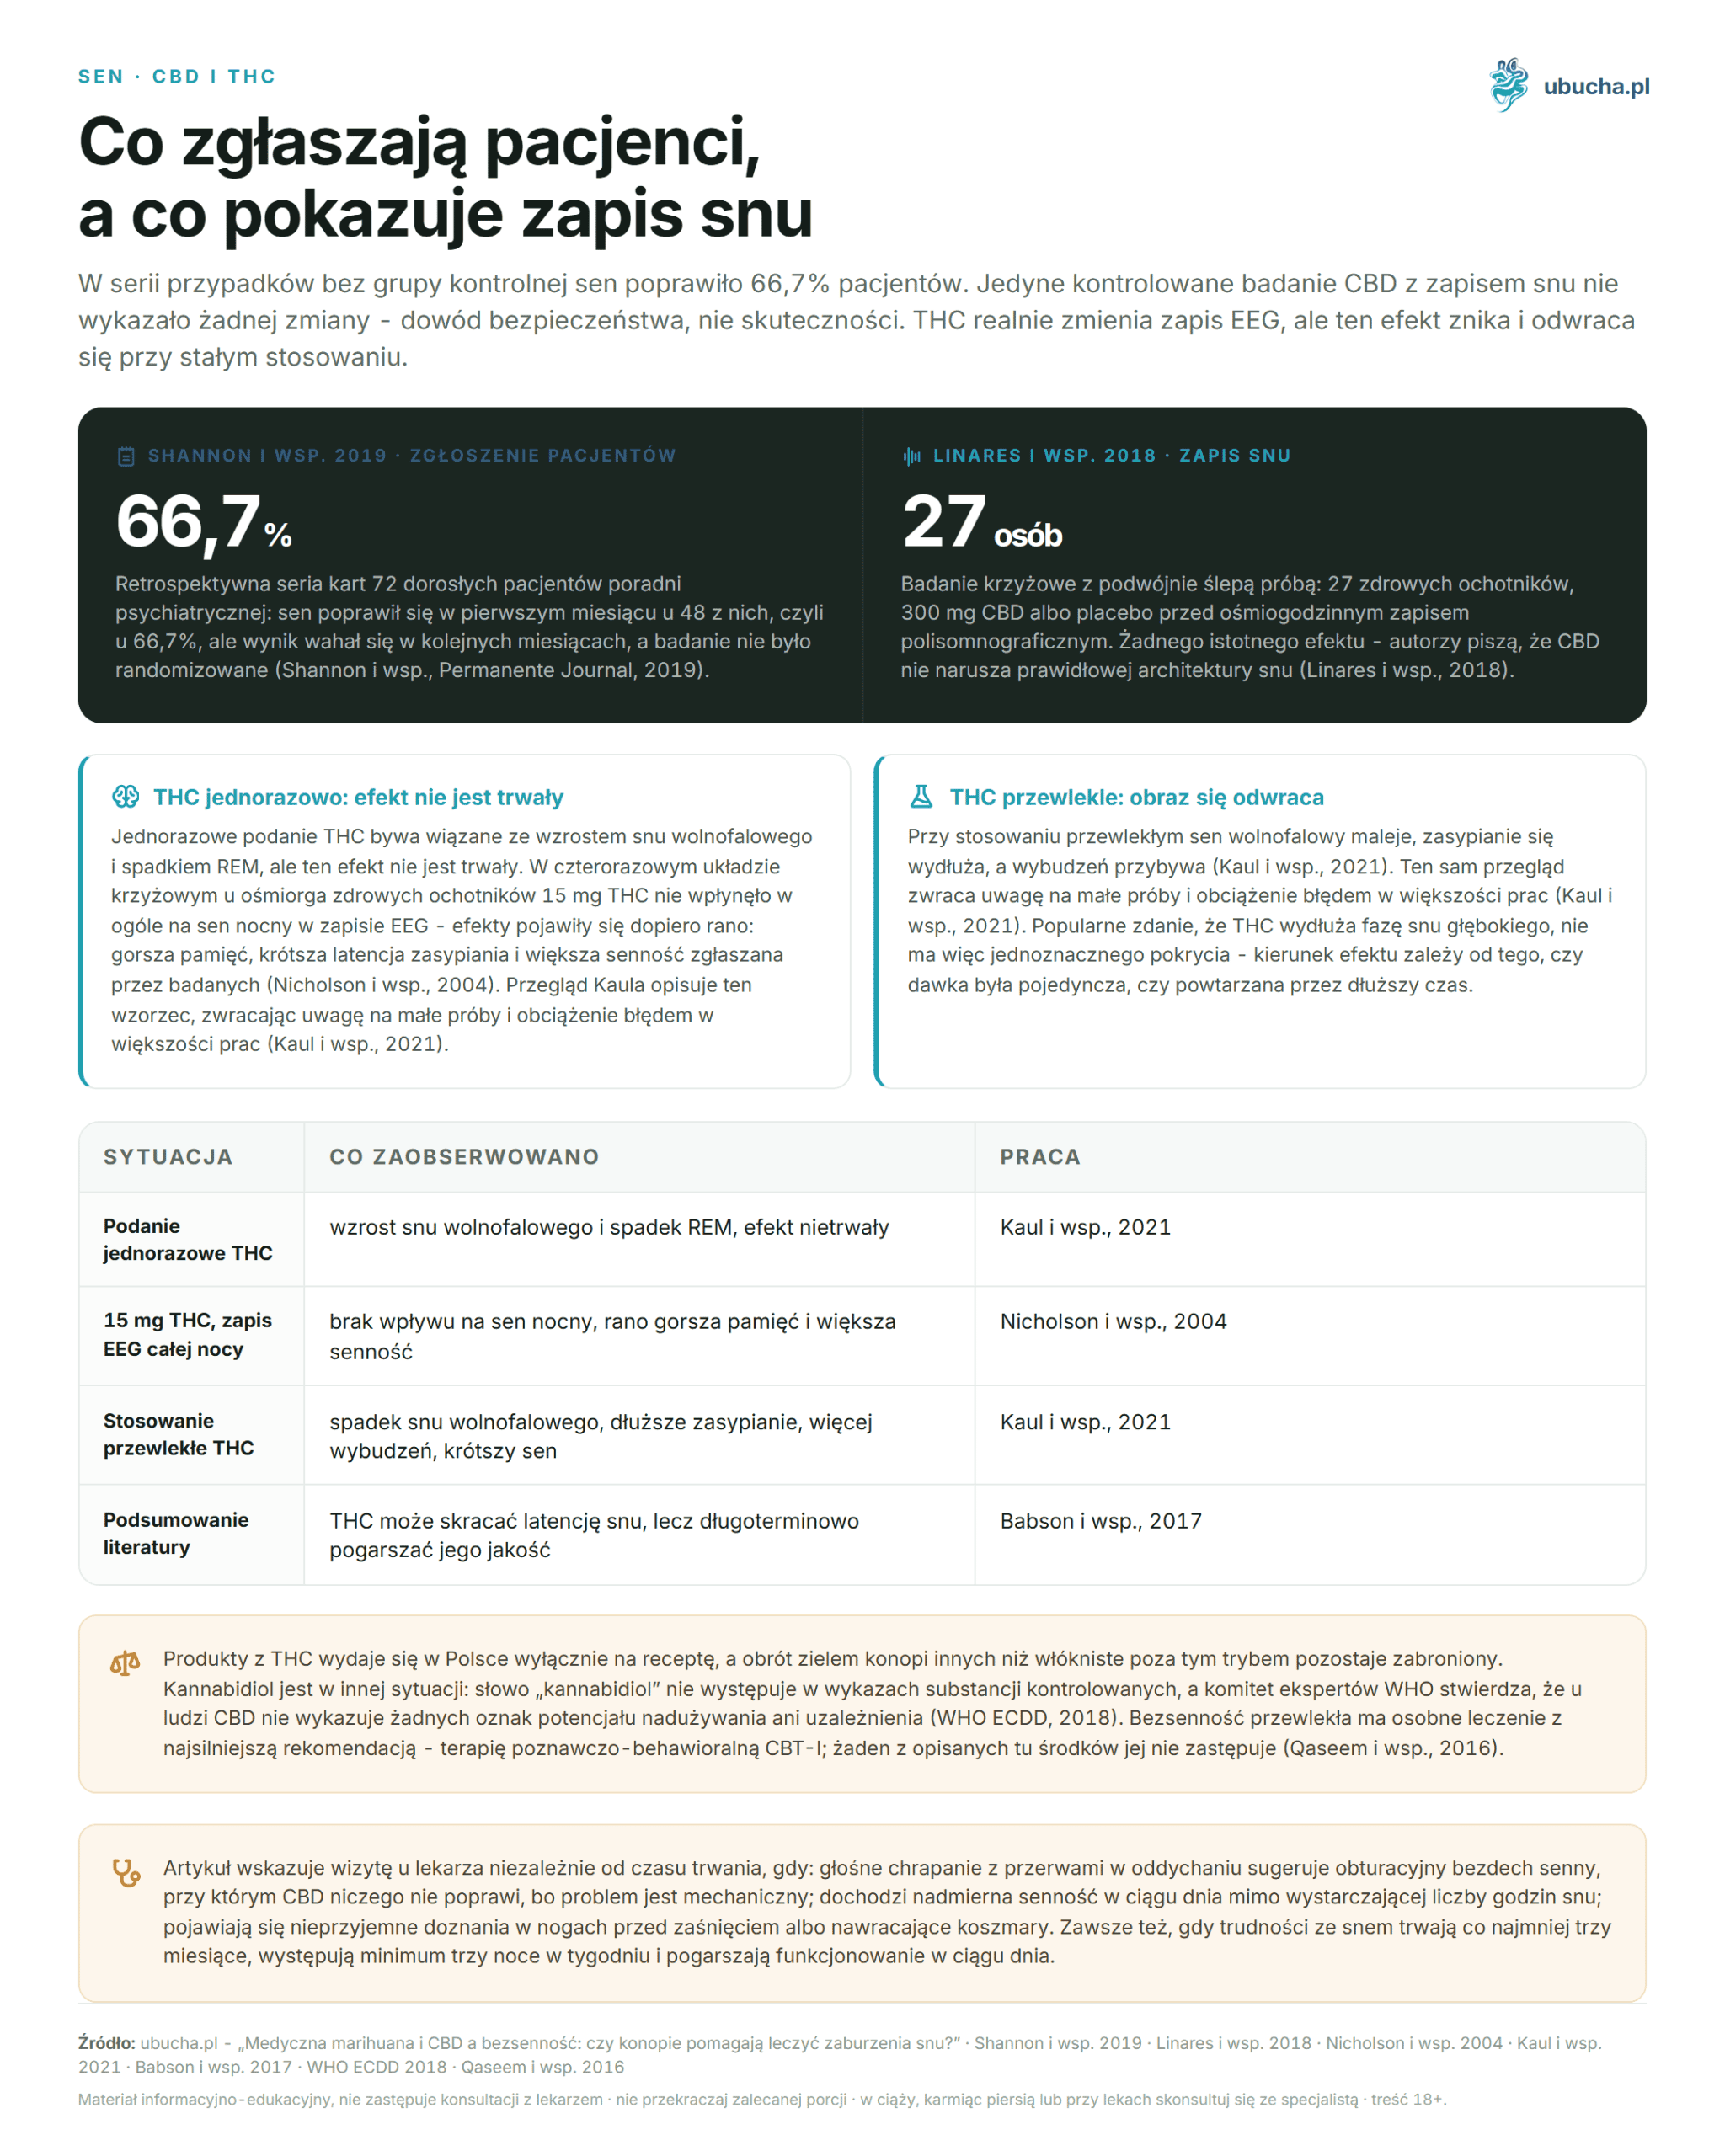
• In a retrospective series of 72 patients, sleep improved in 48 individuals, or 66.7%, in the first month, but the results fluctuated over time (Shannon et al., 2019).
• Polysomnography in 27 healthy volunteers showed no significant effect after 300 mg of CBD; the authors write that CBD does not disrupt the normal architecture of sleep (Linares i wsp., 2018).
• THC administered once is associated with an increase in slow-wave sleep and a decrease in REM, but the effect does not persist with chronic use (Kaul i wsp., 2021).
• CBT-I therapy is the initial treatment for chronic insomnia with a strong recommendation from the American College of Physicians (Qaseem i wsp., 2016).
• WHO states that in humans, CBD shows no signs of potential for abuse or addiction (WHO ECDD, 2018).
Do CBD and THC help with sleep?
Cautiously and differently. CBD has a series of cases suggesting improvement in sleep with insomnia that has an anxiety component, while in a controlled study with polysomnography, it did not change anything measurable. THC can act faster, but its impact on the structure of the night diminishes with chronic use.
The most frequently cited clinical work is a retrospective analysis of the records of 72 adult patients from a psychiatric clinic. Sleep improved in the first month for 48 of them, or 66.7%, anxiety decreased for 57 people, or 79.2%. However, the authors note that the sleep results fluctuated in the following months, and the study was not randomized (Shannon et al., 2019). This is an observation from practice, not proof of efficacy.
On the other side is a crossover study with a double-blind design, in which 27 healthy volunteers received 300 mg of CBD or a placebo half an hour before an eight-hour polysomnographic recording. The drug did not produce any significant effect, and the authors conclude that CBD does not disrupt the normal architecture of sleep (Linares i wsp., 2018). This statement conveys something different than 'improves sleep,' yet it is often quoted as if it meant the same.
The difference between these results is not a contradiction. The first study involved patients with anxiety and disrupted sleep, while the second included healthy individuals, for whom there was nothing to improve. Babson's review summarizes this state in one sentence: research on cannabis and sleep is in its infancy and yields mixed results (Babson et al., 2017).
When does insomnia stop being just a bad night?
When difficulties in falling asleep or maintaining sleep occur at least three times a week for at least three months and lead to consequences during the day. This second condition is often overlooked, and without it, there is no diagnosis.
Diagnostic guidelines list among the daytime consequences fatigue, decreased energy, poorer attention, concentration and memory, as well as mood changes such as irritability and depression (Drager i wsp., 2023). The mere number of hours slept does not determine anything. A person sleeping six hours and functioning well does not have insomnia; a person sleeping seven and waking up groggy may have it.
This distinction has practical implications. Situational insomnia, triggered by a specific event, usually resolves on its own within a few weeks and rarely requires pharmacology. Chronic insomnia is a separate diagnosis with its own treatment, and a supplement is not that treatment. Guidelines place cognitive-behavioral therapy at this point, not an evening preparation.
It is also worth separating primary insomnia from secondary insomnia. The latter accompanies another illness: depression, anxiety disorders, chronic pain, sleep apnea, or thyroid diseases. If the cause lies beneath, working on falling asleep gives a false effect and delays proper diagnosis. You can find more about natural ways to sleep in the post on insomnia in adults and methods without sleeping pills.
How is the night structured and why does the body need sleep phases?
Sleep is not a uniform state. In healthy adults, it sequentially passes through NREM stages from N1 to N3, after which the REM phase appears, roughly in the ninetieth minute of sleep (Edwards i wsp., 2010). With seven or eight hours of sleep, the cycle repeats four to five times.
The distribution of phases during the night is not uniform. The first cycles are richer in deep sleep N3, while the last ones are richer in REM. Therefore, shortening the night by two hours does not equally take away everything; it mainly cuts REM, and going to bed earlier at the same wake-up time adds primarily deep sleep.
| Phase | What happens in it | Kiedy dominuje |
|---|---|---|
| N1 | transition from wakefulness to sleep, easy awakening | at the beginning of each cycle |
| N2 | stabilization of sleep, sleep spindles, decreased reactivity to stimuli | largest part of the night |
| N3, sen wolnofalowy | somatic regeneration, deepest awakening threshold | first half of the night |
| REM | dreams, consolidation of emotional memory, muscle atonia | second half of the night, early morning |
Why this breakdown in a text about cannabinoids? Because the question 'does something help with sleep' is incomplete. A substance may shorten the time to fall asleep while simultaneously impoverishing the phase responsible for memory. The assessment differs when looking at the subjective feeling of being well-rested versus the polysomnographic recording. The rest of this text adheres to the latter criterion wherever the data allows.
How does the endocannabinoid system participate in sleep regulation?
CB1 receptors are distributed in the central nervous system, including in structures involved in regulating wakefulness, and they are the direct target of THC. The situation with CBD looks different and is one of the most frequently misrepresented points in consumer texts.
A systematic review of the molecular targets of cannabidiol states that CBD does not interact directly with the endocannabinoid system outside of in vitro conditions at supraphysiological concentrations, and that it is very unlikely that its effects in neurological diseases occur through this system (Ibeas Bih i wsp., 2015). The literature describes over 65 distinct molecular targets for CBD, and the authors of the review dismissed most of them as unconvincing.
The statement "CBD inhibits the breakdown of anandamide and therefore induces sleep" is an oversimplification that functions as a fact in store texts. The inhibition of the FAAH enzyme has been described under laboratory conditions, but translating this into a sleep-inducing effect in humans has not been demonstrated. This is important because the entire mechanism is often presented as established, whereas it is merely a hypothesis.
What remains in practice? The fact that THC has a clear point of action, while CBD does not have one. Kaul's review describes the modulatory effect of cannabinoids on sleep physiology while also noting the small sample sizes and the risk of bias in most studies (Kaul i wsp., 2021). We discuss more about how cannabis interacts with the circadian rhythm in the post on the impact of cannabis on sleep.
How does THC affect sleep in the short and long term?
A single dose of THC is associated with an increase in slow-wave sleep and a decrease in REM sleep, but the effect on slow-wave sleep and total sleep time is not lasting. With chronic use, the picture reverses: slow-wave sleep decreases, falling asleep takes longer, and awakenings increase (Kaul i wsp., 2021).
The controlled study version is even more cautious. In a four-way crossover design with eight healthy volunteers, 15 mg of THC had no effect on nighttime sleep in EEG recordings. Effects only appeared the next morning: worse memory, shorter sleep latency, and increased sleepiness reported by the participants (Nicholson i wsp., 2004). The popular statement that THC prolongs N3 phase does not have unequivocal support.
| Situation | Co zaobserwowano | Work |
|---|---|---|
| podanie jednorazowe | increase in slow-wave sleep and decrease in REM, a transient effect | Kaul i wsp., 2021 |
| 15 mg THC, EEG recording throughout the night | no effect on nighttime sleep, worse memory and increased sleepiness in the morning | Nicholson i wsp., 2004 |
| Chronic use | decrease in slow-wave sleep, longer time to fall asleep, more awakenings, shorter sleep | Kaul i wsp., 2021 |
| podsumowanie literatury | THC may shorten sleep latency but worsen its quality in the long term | Babson et al., 2017 |
Sleep is a common theme in self-medication. In a study of 170 patients at a California clinic dispensing medical cannabis, individuals with high PTSD scores used cannabis more frequently specifically to improve sleep and reached for it more often than others (Bonn-Miller et al., 2014). The authors question at the end whether alternative methods of improving sleep could reduce this dependency.
What does polysomnography say about CBD and sleep architecture?
It states a very specific thing, and it is not a promise of effectiveness. After 300 mg of CBD, which is an anxiolytic dose, the eight-hour polysomnographic recording in healthy volunteers did not differ significantly from placebo. The authors conclude: CBD does not change the normal architecture of sleep (Linares i wsp., 2018).
This is a statement about safety, not about efficacy. It distinguishes CBD from benzodiazepines and antidepressants, which alter sleep structure, but does not prove that CBD will help anyone fall asleep. The study involved healthy individuals and measured one night after one dose.
The oldest clinical data comes from the 1970s and 1980s. In a trial with fifteen individuals suffering from insomnia, 40, 80, and 160 mg of CBD were compared with placebo and with 5 mg of nitrazepam. Only the group receiving 160 mg reported significantly longer sleep than the placebo group; at all three doses, participants remembered dreams less frequently (Carlini and Cunha, 1981). Remember the ratio: the dose at which something changed was many times higher than the typical supplemental dose.
Separately, there is a case report of a ten-year-old girl with post-traumatic stress disorder, in whom CBD oil resulted in a sustained decrease in anxiety and a gradual improvement in the quality and quantity of sleep (Shannon and Opila-Lehman, 2016). This is one patient, so the weight of evidence is low, although the direction aligns with a series of 72 cases. We expand on the research on sleep and cannabis in the post on CBD in the treatment of insomnia and other sleep disorders.
Do CBN and terpenes really induce sleep?
The thesis of cannabinol as a "sleep cannabinoid" currently lacks support in clinical research on humans. CBN is formed from the oxidation of THC in aging raw material, and the belief in its sleep-inducing power stems from observations of aged cannabis, not from controlled trials.
A systematic review of the literature on cannabinoids in sleep disorders finds no basis for the routine use of any of them, and most of the included studies are assessed as having moderate to high risk of bias (Suraev i wsp., 2020). CBN is not an exception in this picture, but rather a particularly poorly studied fragment.
The situation with terpenes is similar, though more interesting. Russ's review describes myrcene, linalool, and beta-caryophyllene as compounds with real pharmacological activity, present in the diet and considered safe, and posits a hypothesis of synergy with cannabinoids. However, the author explicitly writes about synergy "if proven," not about a confirmed phenomenon (Russo, 2011).
The practical conclusion is inconvenient for labels. The declaration "sleep oil with CBN" describes the composition, not confirmed effects. If the producer provides a terpene profile in the certificate of analysis, you get more information about the product, but you still do not get proof that this mixture will extend your night.
How does CBD compare to sleeping pills and melatonin?
It stands out as a substance with a good safety profile and poorly documented sleep-inducing effectiveness. Sleeping pills have the opposite arrangement of advantages and disadvantages, while melatonin provides a small but measurable effect in a meta-analysis. The choice depends on what exactly is disrupting your night.
| Agent | What do the data show | Disclaimer |
|---|---|---|
| CBD | no significant impact on polysomnographic recordings after 300 mg (Linares et al., 2018) | the evidence pertains to the safety of sleep structure, not effectiveness |
| melatonina | reduction in sleep onset by 7.06 minutes and an increase in sleep duration by 8.25 minutes in 19 studies involving 1683 people (Ferracioli-Oda et al., 2013) | the effect is modest, less than with sleeping pills |
| benzodiazepiny i leki Z | pharmacotherapy is only permitted after ineffective CBT-I (Qaseem et al., 2016) | weak recommendation, low-quality evidence, decision made jointly with a doctor |
| CBT-I | initial treatment of chronic insomnia, strong recommendation (Qaseem et al., 2016) | availability of therapists in Poland is limited |
The meta-analysis of melatonin included 19 studies and 1683 individuals with primary sleep disorders. A reduction in latency by seven minutes sounds disappointing, but the authors note that the effect does not diminish with continued use, unlike many sleeping pills (Ferracioli-Oda i wsp., 2013). Melatonin addresses a different problem than CBD: it regulates the clock, not alleviates tension.
So if your night is disrupted by jet lag or shift work, melatonin is a more sensible starting point. If the source is an evening flow of thoughts, neither of these substances can replace the work on stimuli and rhythm described by CBT-I.
What drugs interact with CBD?
Primarily those metabolized by the liver. A review of cannabinoid pharmacokinetics indicates the possibility of interactions through inhibition or induction of enzymes and transporters, with CBD inhibiting the metabolism of clobazam as an example (Lucas i wsp., 2018).
The same review warns of pharmacodynamic interactions. Administering cannabis alongside other central nervous system depressants compounds sedation, while combining it with sympathomimetics may add hypertension and tachycardia. Older adults are mentioned as a group at increased risk of adverse effects, despite potential symptomatic benefits.
Iffland's safety review confirms the favorable profile of CBD while indicating that CBD's impact on liver enzymes, drug transporters, and interactions requires further clinical research. The most commonly reported adverse effects are fatigue, diarrhea, and changes in appetite and body weight (Iffland and Grotenhermen, 2017).
The WHO report goes in the same direction, cautiously stating: CBD is generally well tolerated and has a good safety profile, and reported adverse effects may result from interactions with medications the patient is already taking (WHO ECDD, 2018). The practical conclusion is simple: if you are taking anything regularly, inform your primary care physician about introducing CBD instead of deciding on your own.
What adverse effects does CBD cause?
The best-documented symptom is diarrhea. In a meta-analysis of randomized placebo-controlled trials, involving 12 trials and 803 participants, after excluding studies on pediatric epilepsy, the only adverse effect significantly associated with CBD remained diarrhea (Chesney i wsp., 2020).
This distinction is worth understanding, as it changes the interpretation of the entire list. In the full compilation, CBD was also associated with drowsiness, sedation, decreased appetite, more frequent study dropouts, and abnormal liver function test results. However, the associations with drowsiness and abnormal liver function tests were limited to studies on pediatric epilepsy, where CBD was administered alongside clobazam or valproate, in doses not comparable to supplemental ones.
Iffland's safety review lists the most frequently reported symptoms as fatigue, diarrhea, and changes in appetite and body weight, noting that compared to medications used for the same indications, the profile of CBD is better (Iffland and Grotenhermen, 2017). However, the authors add that some toxicological parameters, such as the impact on hormonal balance, have not yet been studied.
The conclusions for someone wanting to take CBD in the evening for an extended period are twofold. First, the data from studies mainly come from short trials, and chronic administration in adults without epilepsy is poorly studied. Second, the most serious signals appeared where CBD was combined with other medications, so it is the combination, not the substance itself, that warrants caution.
How to dose CBD for insomnia?
The principle provided by the pharmacokinetic review is "start low and go slow," with careful observation of desired and undesired effects (Lucas i wsp., 2018). Specific daily doses for insomnia have not been established, as there are no studies that would determine them.
It is worth knowing the scale of doses from the studies referenced in consumer texts. In a series of 72 cases, almost all patients received 25 mg of CBD per day in capsules, a handful received 50 or 75 mg, and in one case, the dose was gradually increased to 175 mg (Shannon et al., 2019). The repeated "25 to 175 mg" mentioned online thus describes extremes, not a typical dose.
| Form | When to take it | What is known about absorption |
|---|---|---|
| sublingual oil | 30 do 60 minut przed snem | the half-life after oral spray is 1.4 to 10.9 hours; the absolute bioavailability of this route has not been measured in humans |
| capsule | 60 do 120 minut przed snem | maximum concentration achieved from zero to four hours after administration, higher after a meal |
| forma wziewna | rzadko sensowna wieczorem | the only route with calculated absolute bioavailability in humans, about 31% after smoking |
The numbers in the last column come from a systematic review of CBD pharmacokinetics in humans (Millar et al., 2018). The authors emphasize that the data is limited and can be inconsistent. Popular tables providing exact percentages of bioavailability for oral and sublingual routes are not supported in this work, as such measurements have simply not been conducted in humans.
Practically, this means one thing: keep a sleep diary and change one thing at a time. Without a record, you won't distinguish the effect of the preparation from the natural variability of the night, which can be significant in people with insomnia.
Why is CBT-I the first-line treatment?
Because this is the strongest recommendation in the guidelines. The American College of Physicians recommends that every adult patient with chronic insomnia receive cognitive-behavioral therapy as initial treatment; this is a strong recommendation based on moderate-quality evidence (Qaseem i wsp., 2016).
Pharmacotherapy appears in these guidelines only as a conditional second step. ACP recommends making decisions jointly with the patient, after discussing the benefits, harms, and costs of short-term medication use, in individuals for whom CBT-I alone has proven ineffective. The recommendation is weak, and the evidence is of low quality.
The Brazilian guidelines from 2023 formulate this even more strongly, calling multi-component CBT-I the gold standard for treating chronic insomnia (Drager i wsp., 2023). The therapy includes stimulus control, sleep restriction, relaxation techniques, working on sleep beliefs, and education.
This framework allows for a place for cannabinoids, and it is not the first place. A supplement may reduce evening tension enough to facilitate the implementation of behavioral techniques, but it will not replace either them or diagnostics. Reversing this order is the most common mistake made by those trying to cope with insomnia on their own.
When does insomnia require a doctor's visit?
Whenever it meets the criteria for chronic insomnia, meaning it persists for at least three months, occurs at least three nights a week, and worsens daytime functioning (Drager i wsp., 2023). Samodzielne leczenie takiego stanu suplementami odsuwa rozpoznanie przyczyny.
There are also symptoms that direct one to a specialist regardless of duration. Loud snoring with breathing pauses suggests obstructive sleep apnea, for which CBD will not improve anything, as the problem is mechanical. Excessive daytime sleepiness despite sufficient hours of sleep, unpleasant sensations in the legs before falling asleep, and recurring nightmares also require diagnostics.
It is worth knowing what the doctor will look for. The basis is an interview and a sleep diary kept for one to two weeks, supplemented by insomnia severity questionnaires. Polysomnography is not a routine test for insomnia; it is performed when sleep apnea, parasomnia, or other disorders requiring recording are suspected.
A separate category is secondary insomnia due to illness, which must be treated first. Depression, anxiety disorders, hypothyroidism or hyperthyroidism, iron deficiency, and chronic pain can fully explain disturbed sleep. In such situations, improvement in sleep comes with treating the underlying cause, not separately.
What is the legal status of medical marijuana and CBD in Poland?
Products containing THC seem to be available in Poland only by prescription, and apart from this mode, the trade in cannabis other than fiber remains prohibited. Cannabidiol is in a different situation: the word "cannabidiol" does not appear in the lists of controlled substances at all.
The threshold distinguishing fiber hemp from others is 0.3% dry mass and is calculated as the sum of delta-9-THC and tetrahydrocannabinolic acid, rounded to one decimal place. The basis is Article 4 point 5 of the Act of July 29, 2005, on counteracting drug addiction (t.j. Dz.U. 2023 poz. 1939), as amended by the Act of March 24, 2022 (Journal of Laws 2022, item 763), effective from May 7, 2022.
This distinction changes the result of the laboratory test, so it is not a formality. The threshold concerns the sum of two compounds, not just delta-9-THC, which in plant material gives values clearly higher than measuring one fraction. Until May 6, 2022, the national threshold was 0.20%, which is why older texts provide a different number.
It is worth correcting one more repeated statement. The Polish threshold corresponds to the EU threshold of 0.3% from Regulation (EU) 2021/2115, but it does not derive from it: these are two separate regulations with the same numerical value. The earlier Regulation 1307/2013, cited in many articles, established 0.2% and was repealed on January 1, 2023.
What does this mean for the reader
The picture is less clear-cut than product descriptions suggest, and this is the most honest conclusion of this text. A systematic review of the literature finds no basis for the routine use of cannabinoids in the treatment of sleep disorders, and most available studies are assessed as being at risk of bias (Suraev i wsp., 2020).
Three things are worth remembering. CBD at an anxiolytic dose does not disrupt the normal architecture of sleep, which is an argument for safety, not effectiveness. THC acts faster, but its impact on the structure of the night reverses with chronic use. Chronic insomnia has its own treatment with strong recommendations, and no evening preparation is it.
If you still want to try, do it methodically: one change at a time, the lowest reasonable dose, a sleep diary for at least two weeks, and a conversation with a doctor if you are taking anything regularly. Without this, you won't distinguish the effect of the preparation from the usual variability of the night.
Separately, it is worth monitoring the boundary between a supplement and a medication. Products with THC require a prescription in Poland, and CBD sold over the counter is not registered as a medicinal product for treating insomnia. If a seller describes a preparation as if it were a drug, it is a warning signal about the seller, not information about the product.
Finally, the most often overlooked point in texts about sleep supplements. The improvement you seek usually will not come from a single substance, but from changing several conditions at once: a fixed wake-up time, limiting time spent in bed without sleep, and giving up on catching up on sleep during the weekend. These are elements of cognitive-behavioral therapy, not lifestyle advice, and they have the strongest recommendation of everything described in this text.
Frequently Asked Questions
Does CBD help with insomnia?
The data is ambiguous. In a retrospective series of 72 patients, sleep improved in 66.7% in the first month, but the results fluctuated over time, and the study was not randomized (Shannon et al., 2019). A systematic review finds no basis for the routine use of cannabinoids in sleep disorders.
Jaka dawka CBD na sen ma pokrycie w badaniach?
There is no established dose. In a series of 72 cases, almost everyone received 25 mg per day, a handful 50 or 75 mg, and one person up to 175 mg (Shannon et al., 2019). In an older trial, longer sleep was reported only by the group taking 160 mg.
Does THC help you fall asleep?
Short-term, it is associated with an increase in slow-wave sleep and a decrease in REM, but the effect does not persist chronically, and with regular use, slow-wave sleep decreases and awakenings increase (Kaul i wsp., 2021). In Poland, products with THC are available only by prescription.
Does CBD change sleep phases like THC?
Not in the available polysomnographic record. After 300 mg of CBD in 27 healthy volunteers, no significant differences were found compared to placebo, and the authors write that CBD does not disrupt the normal architecture of sleep (Linares i wsp., 2018). This is a conclusion about safety, not efficacy.
Does CBD cause addiction?
The WHO Expert Committee report states that CBD does not show any signs of potential abuse or dependence in humans, and that it is generally well tolerated (WHO ECDD, 2018). Reported side effects may result from interactions with concurrently taken medications.
What drugs interact with CBD?
Primarily metabolized in the liver. A review of pharmacokinetics indicates possible interactions through the inhibition of enzymes and transporters, with an example being the inhibition of clobazam metabolism by CBD (Lucas i wsp., 2018). Combining with central nervous system depressants adds to sedation.
Can CBD be given to a child with insomnia?
Only under medical supervision. A case was described of a ten-year-old patient with post-traumatic stress disorder, in whom CBD oil reduced anxiety and gradually improved the quality and quantity of sleep (Shannon and Opila-Lehman, 2016). This is one case report, so it is not a basis for a parent's independent decision.
Does CBD replace CBT-I therapy?
Does not replace. The American College of Physicians recommends cognitive-behavioral therapy as the first-line treatment for chronic insomnia in all adult patients, with the highest strength recommendation (Qaseem i wsp., 2016). Pharmacotherapy is only considered after ineffective CBT-I.
If after reading you want to compare available products, check the section hemp oils.
This article is for informational and educational purposes only and does not constitute medical advice. Before starting to use hemp or CBD for therapeutic purposes, consult your doctor, especially if you are taking other medications, are pregnant, or breastfeeding.
Author: Michał Waluk · Opublikowano: 2026-05-11 · Aktualizacja: 2026-08-10