CBD for Migraine: What Research Says and What Is Unknown

The only randomized cannabis study in migraine attack showed no superiority of CBD over placebo. Check what was studied, what interactions exist, and when to see a doctor.
Migraine affects about 14 percent of adults worldwide, and daily headache is experienced by 15.8 percent of the population (Stovner et al., The Journal of Headache and Pain, 2022). Some of these people seek alternatives beyond triptans and topiramate, and CBD appears in search results as a ready answer. The problem is that the first randomized cannabis study in acute migraine attack tested a separate CBD-dominant arm and found no superiority over placebo. This text separates what has actually been studied from what is repeated in advertisements: it shows the basis of the endocannabinoid hypothesis, which works involved cannabis with THC instead of CBD alone, what drug interactions were measured, and when headache requires urgent diagnostics.
KEY INFORMATION
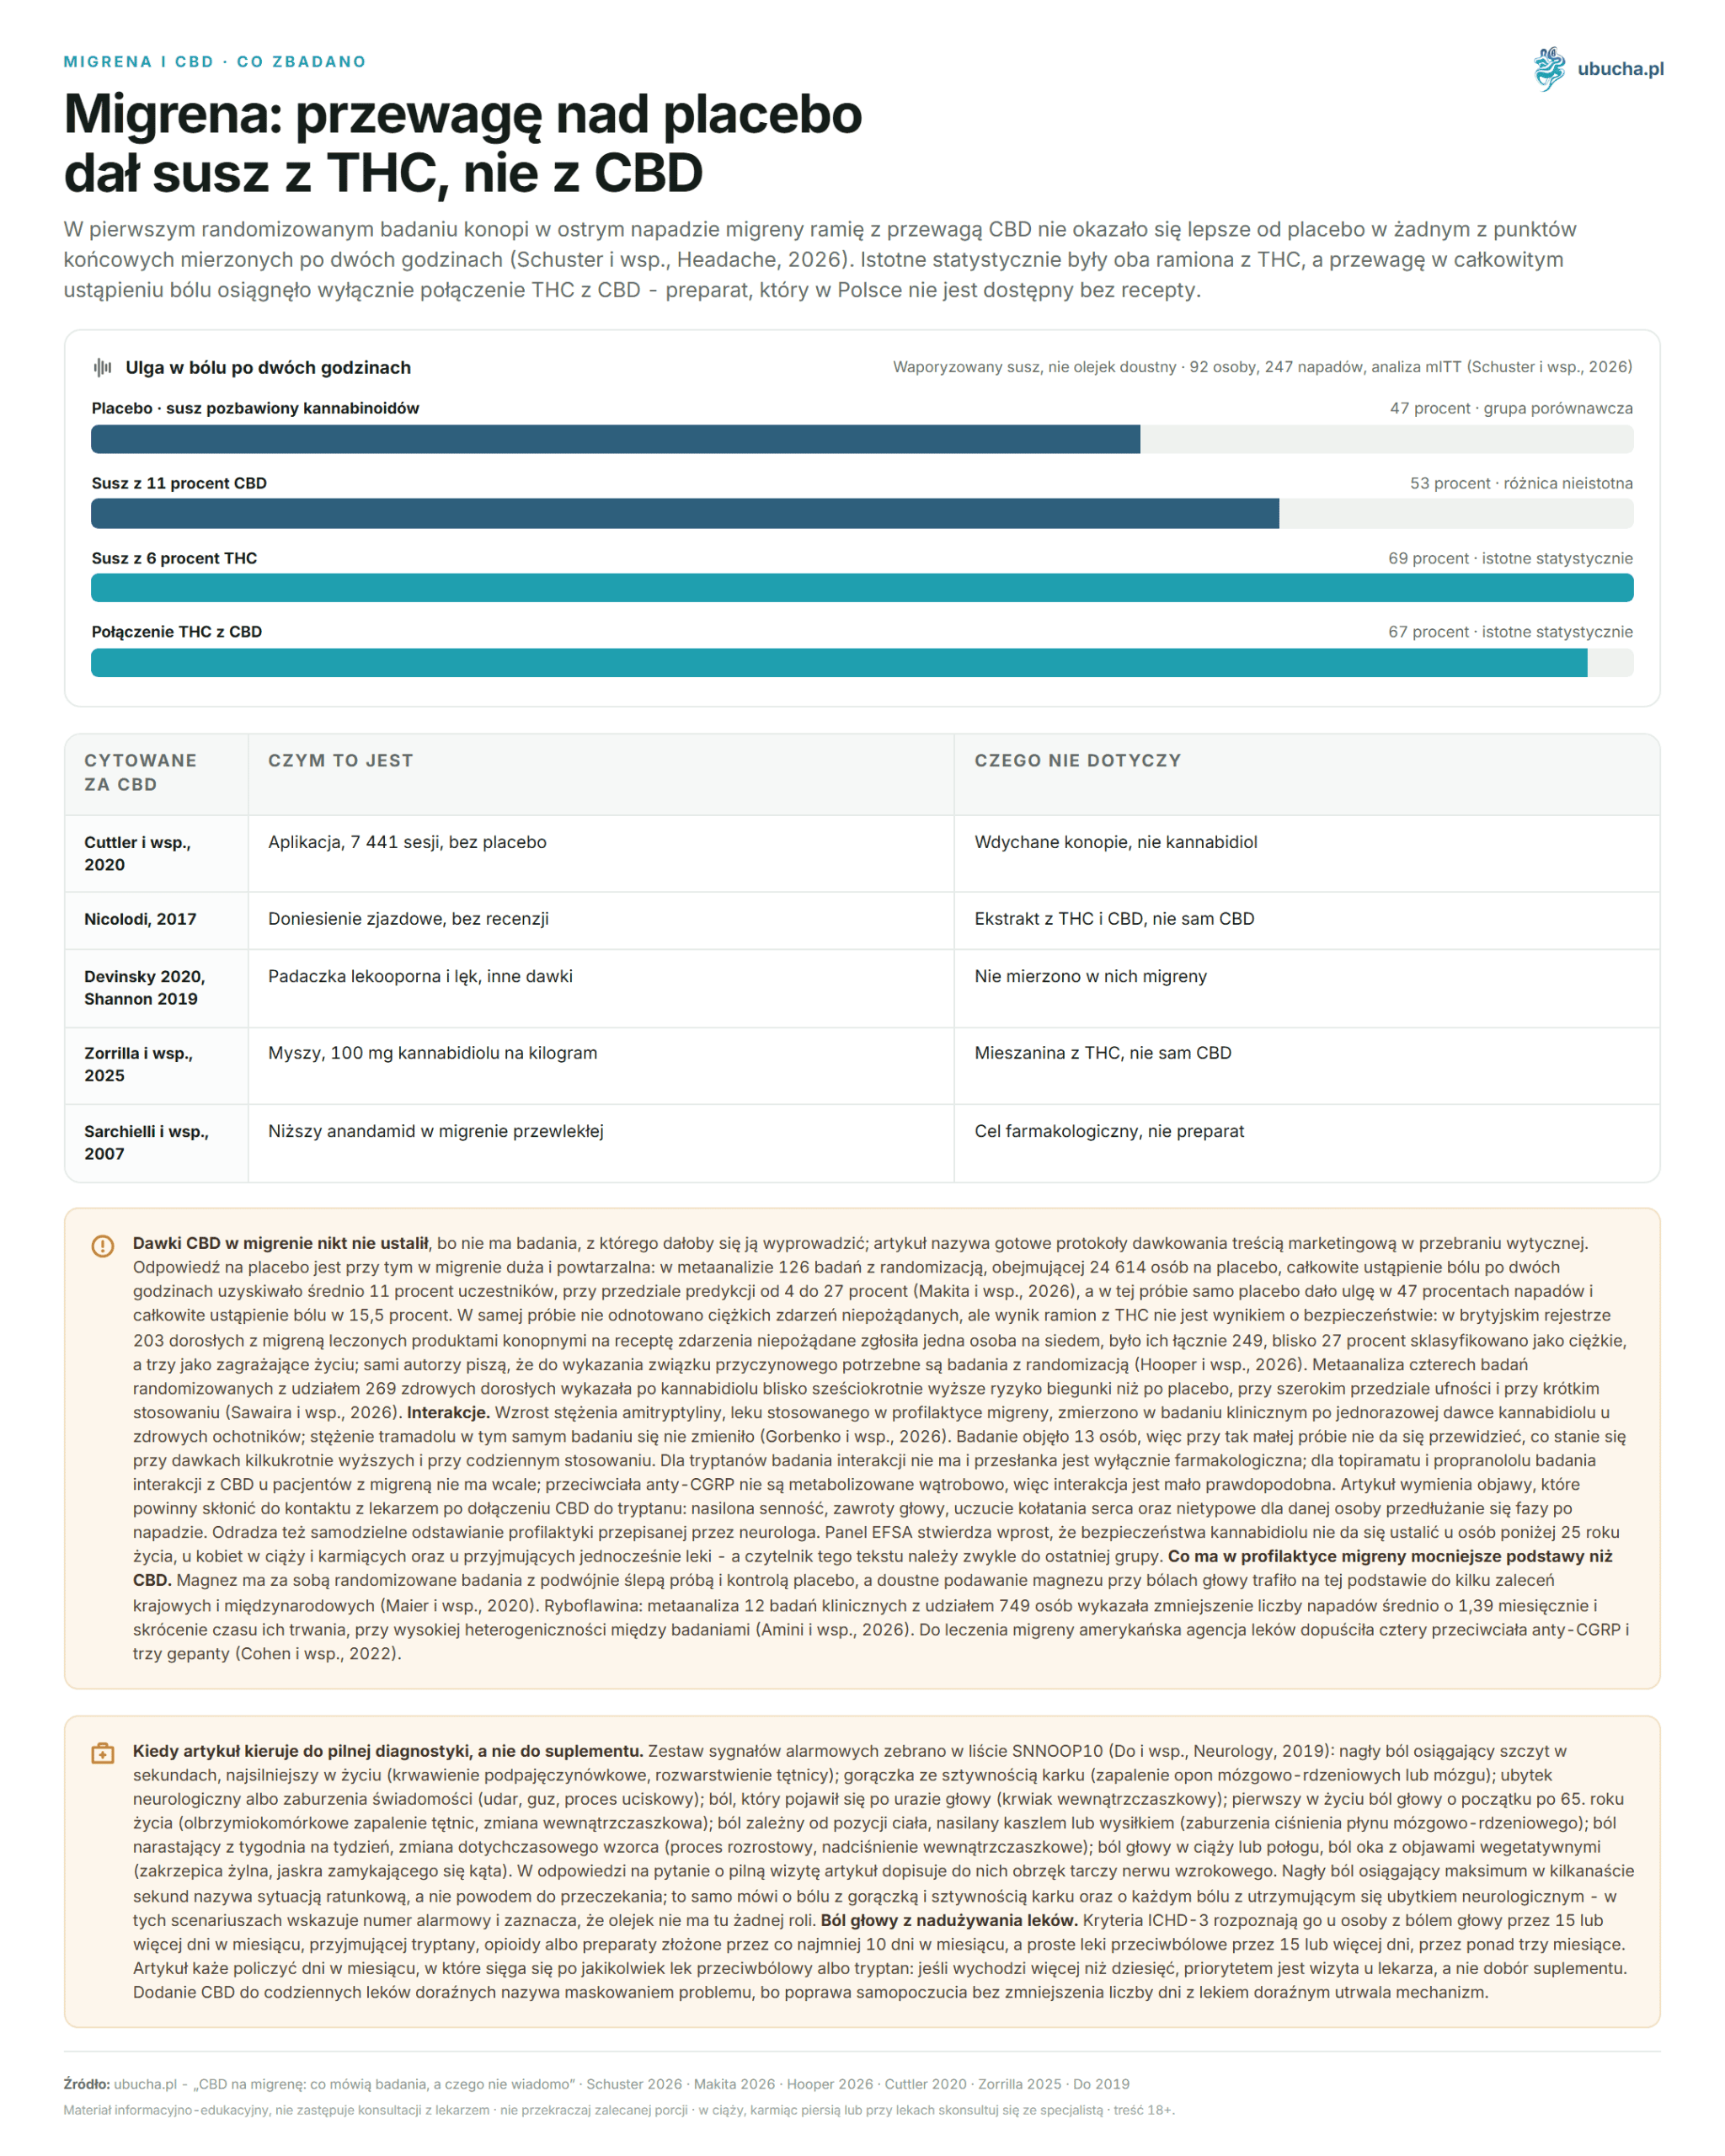
• The CBD-dominant arm showed no superiority over placebo in migraine attack: 53 versus 47 percent relief after two hours (Schuster et al., Headache, 2026).
• Only the combination of 6 percent THC with 11 percent CBD showed superiority over placebo, i.e., a substance other than cannabidiol alone.
• No one has established CBD doses in migraine because there is no study from which it could be derived.
• A single 30 mg dose of CBD increased plasma amitriptyline concentration in healthy volunteers (Gorbenko et al., British Journal of Clinical Pharmacology, 2026).
• Sudden, worst-in-life headache is a reason for urgent diagnostics, not supplementation.
Does CBD alone alleviate migraine?
There is no evidence for this. In the first randomized cannabis study in acute migraine attack, the CBD-dominant arm was not better than placebo in any endpoint measured after two hours (Schuster et al., Headache, 2026). Everything else is observations, cannabis containing THC, or animal studies.
This distinction determines the rest of the text. Cannabidiol and cannabis are not synonyms. Cannabis flower contains dozens of cannabinoids, terpenes, and primarily THC, a psychoactive substance with a different receptor profile. When a study shows that smoking or vaporizing cannabis reduces headache, it refers to cannabis with THC. Transferring such a result to a bottle of cannabidiol oil is a leap of thought, not a conclusion.
Lack of evidence of efficacy is not the same as evidence of lack of efficacy. For oral CBD in migraine prophylaxis, we have the first situation: no study has been conducted that could resolve the issue either way. For vaporized CBD-rich flower in acute attack, we approach the second situation, as one controlled study has already tested this variant and found no effect.
The argumentation you find on Polish internet usually rests on four pillars: studies on CBD in epilepsy and anxiety, observational analysis of cannabis users, a 2017 conference report, and animal pain models. Each pillar is discussed separately below and described for what it really is.
What is migraine and how to recognize it?
Migraine is a primary, episodic neurological disorder in which pain arises from abnormal activation of the trigeminovascular system, neurogenic inflammation, and sensitization of pain pathways, not from vasodilation alone as believed for decades (Cohen et al., BioDrugs, 2022).
According to the ICHD-3 classification by the International Headache Society, an untreated attack lasts from 4 to 72 hours. Pain is usually unilateral and pulsating, worsens with normal physical activity, and is accompanied by nausea or sensitivity to light and sound. Aura, i.e., transient neurological symptoms preceding pain, affects a minority of patients. This description distinguishes migraine from tension-type headache, which is bilateral, pressing, and does not worsen with movement.
The scale of the phenomenon is large. Global migraine prevalence is 14.0 percent, active headache disorder affects 52.0 percent of people, and headache on 15 or more days per month affects 4.6 percent (Stovner et al., The Journal of Headache and Pain, 2022). In Poland, this translates to several million people.
Why this distinction in a text about CBD? Because most advertising materials speak generally about “headaches” and lump together two diagnoses with completely different treatments. A study conducted in migraine says nothing about tension-type headache, and a study in tension-type headache says nothing about migraine. If you do not have a diagnosis from a doctor, the first step is to obtain it, not to choose a preparation. Without it, you cannot even determine if any attempt succeeded.
What type of headache do you have and why does it change the answer?
Because cannabis studies concerned migraine, and migraine is a minority of headaches. The most common diagnosis is tension-type headache, which globally affects 26 percent of people (Stovner et al., The Journal of Headache and Pain, 2022). The prevalence of other diagnoses is shown in the chart at the end of this section. The diagnosis determines whether cannabis data even apply to you.
| Type of Headache | How It Manifests | What Has Documented Efficacy |
|---|---|---|
| migraine | unilateral, pulsating, lasts 4 to 72 hours, worsens with movement, with nausea or photophobia | triptans in attack, drug prophylaxis, magnesium, riboflavin |
| tension-type headache | bilateral, pressing, non-pulsating, not worsened by movement | amitriptyline 100 mg, botulinum toxin in chronic form |
| medication overuse headache | 15 or more days with headache per month with frequent acute medications | withdrawal and prophylaxis under medical supervision |
| secondary headache | symptom of another disease, usually with alarm signs from urgent diagnostics section | cause diagnostics, often urgent |
In prophylaxis of chronic tension-type headache, a network meta-analysis of 35 randomized studies ranked amitriptyline 100 mg highest, reducing headache days by over six per month (Tao et al., Annals of Medicine, 2026). The authors themselves temper this result: evidence certainty was low to very low with high risk of bias and heterogeneity, and amitriptyline at this dose caused more adverse effects than placebo. Botulinum toxin type A, listed for tension-type headache, comes from the same analysis and concerns only the chronic form. Cannabidiol is not included at all due to lack of studies for inclusion.
What exactly did the first randomized cannabis study in migraine show?
The study included 92 people who treated up to four attacks, each time with a different preparation, in a crossover double-blind design. Vaporized flower with 6 percent THC, flower with 11 percent CBD, their combination, and placebo in the form of cannabinoid-free flower were compared. A total of 247 attacks were recorded.
Pain relief after two hours was achieved in 67 percent of attacks treated with THC and CBD combination, 69 percent with THC alone, 53 percent with CBD-rich flower, and 47 percent with placebo. Only the first two results were statistically significant. Complete pain relief and relief of the most bothersome symptom were achieved only by the THC and CBD combination, which maintained superiority also after 24 and 48 hours.
The authors checked whether the effect was simply due to participants recognizing the psychoactive effect of THC. After accounting for euphoria and subjective intoxication as covariates, results did not change. No serious adverse events were reported. The conclusion for someone considering oil: this study says nothing good about cannabidiol alone, and its positive result concerns a THC-containing preparation, which in Poland is not available without prescription.
Is CBD oil from the store the same as cannabis from studies?
No. They differ in composition, route of administration, and legal status, each of which changes study outcomes. In the randomized trial, participants inhaled vapor from cannabis flower. In the UK registry, patients took prescription cannabis products. In the app analysis, users smoked or vaporized cannabis from a medical program.
Store-bought oil is an extract dissolved in carrier oil, taken orally or sublingually, with trace THC content mandated by regulations. This is not the same intervention as vaporizing flower containing 11 percent cannabidiol, even if the molecule name matches. The difference is similar to that between inhaled and oral administration of an asthma drug.
The route of administration radically changes pharmacokinetics. Inhalation bypasses first-pass liver metabolism and reaches peak in minutes. Oral intake passes through the liver, with peak appearing within up to four hours (Millar et al., Frontiers in Pharmacology, 2018). Inhaled and swallowed preparations are practically two different drugs with the same name.
That is why the formula “studies confirm CBD efficacy” is so convenient in ads. It does not specify which preparation, route, or dose. When you add these three details for each cited study, most no longer fit the product they are cited for.
Why is the Cuttler analysis often cited as evidence for CBD?
Because it sounds impressive and few check what it concerned. Cuttler’s team analyzed data from the Strainprint app, where patients logged symptoms before and after cannabis use. It included 12,293 headache sessions and 7,441 migraine sessions (Cuttler et al., The Journal of Pain, 2020).
Reported pain intensity dropped by about half after cannabis use. This is substantial, but the material has three major limitations. There was no control or placebo group, so participant expectations fully influence results. Data came from self-assessment in a commercial app installed by people already convinced of cannabis. Finally, inhaled cannabis was studied, not cannabidiol.
The authors also checked whether THC or CBD content explained effect size. Factors that actually differentiated results included sex and preparation form: concentrates worked stronger than flower. Cannabinoid content did not appear in this set. They noted tolerance development, i.e., weakening effect and increasing doses over time.
Numbers circulating on Polish sites about this study are sometimes misattributed. You may see “1,306 migraine sessions and 47.3 percent pain reduction.” The paper has 7,441 migraine sessions, and 1,306 is the number of people reporting headache, not migraine. The 47.3 percent also describes headache; for migraine it was 49.6 percent. Both numbers exist but describe different things than attributed.
What was the Italian report by Nicolodi and how much is it worth?
It was a conference presentation, not a peer-reviewed publication. In 2017, at the European Academy of Neurology congress, a comparison of cannabis extract with amitriptyline in chronic migraine prophylaxis was presented. The report is not indexed in Europe PMC as a full paper, so methods and source data cannot be checked.
This does not mean the study did not exist. It means it was not peer-reviewed, no protocol was published, and no result tables are available. In the evidence hierarchy, a conference abstract ranks below a single observational study, as no independent party verified raw data. The scale is measured: in a review of 425 reports covering 307,028 conference abstracts, 37.3 percent reached full publication, and positive results were published more often (Scherer et al., Cochrane Database of Systematic Reviews, 2018).
Separately, the extract studied contained both THC and CBD. Even if results were confirmed in full publication, they would concern a THC-containing preparation. When you see this report cited under a headline about CBD oil, you are witnessing a topic substitution.
Treat this work as a signal that a proper study is worth designing, not as a basis for therapeutic decisions. Nine years after the presentation, such a study still does not exist.
This situation repeats throughout the topic and has a simple cause. Cannabidiol is a naturally occurring substance, so it is difficult to build patent protection justifying the cost of a phase 3 trial. It sells excellently without any studies because the promise works better than the result. The oil producer has no incentive to finance a trial that may end negatively, and without such a trial the product still sells.
What does the UK medical cannabis patient registry show?
It shows quality of life improvement and a simultaneous warning not to read it as proof of efficacy. The UK Medical Cannabis Registry included 203 adults with migraine treated with prescription medical cannabis products (Hooper et al., Brain and Behavior, 2026).
Improvements in headache impact on daily life, anxiety severity, sleep quality, and general health assessment persisted up to 24 months. Migraine disability improvement was visible up to 12 months. One detail spoils the pro-cannabidiol narrative: the lowest quartile of THC doses was a negative predictor of improvement. In other words, patients taking the least THC improved less often.
Safety also looks different than store descriptions suggest. One in seven reported adverse events, but there were 249 total, nearly 27 percent classified as serious, and three life-threatening. This is a registry of patients under medical supervision taking THC products, not people buying oil in a store.
The authors conclude that randomized studies are needed to demonstrate causality. The registry shows how patients who stayed in therapy feel. It does not show how they would feel if given placebo.
Also note a mechanism inflating all registry results. People for whom the preparation did not help or who poorly tolerated it leave the program and stop filling questionnaires. After two years, mainly those with some effect remain in data. The same effect makes online store reviews look better than reality, but at least the clinical registry describes it.
Why does CBD efficacy in epilepsy and anxiety not transfer to migraine?
Because these are different diseases, doses, and data reliability levels. CBD has strong evidence in two rare epilepsy syndromes: a meta-analysis of four randomized studies confirmed superiority over placebo in seizure reduction at doses of 10 and 20 mg per kilogram per day (Devinsky et al., Acta Neurologica Scandinavica, 2020).
For a 70 kg person, this equals 700 to 1,400 mg CBD daily, i.e., the content of one to two 10 percent oil bottles per day. No store dosing scheme approaches these values, yet all refer to “it works in epilepsy.” Efficacy in one indication and dose does not automatically transfer to another indication at a tenfold lower dose.
In anxiety, the evidence is much weaker than quotes suggest. The most cited work is a retrospective review of 72 adults in a psychiatric clinic, where anxiety severity dropped in the first month in 79.2 percent (Shannon et al., The Permanente Journal, 2019). This is a case series without control group, with concurrent standard treatment.
There is also a difference in symptom nature. Seizures can be counted and seen in brain bioelectrical activity, while headache severity is reported only by the patient. The more subjective the endpoint, the greater the expectation effect. Migraine is an extreme case in this regard, as discussed in the next section.
Why does placebo response complicate CBD assessment in migraine?
Because placebo works strongly and repeatedly in migraine, so without a control group you cannot distinguish drug from expectation. In a meta-analysis of 126 randomized studies including 24,614 placebo recipients, complete pain relief after two hours was achieved by an average of 11 percent, with a prediction interval from 4 to 27 percent (Makita et al., Neurology, 2026).
Partial relief after placebo can be even higher. In the vaporized cannabis study, the placebo group reported pain relief in 47 percent of attacks and complete pain relief in 15.5 percent. Nearly half of attacks treated with cannabinoid-free flower “responded” to treatment.
Now apply this percentage to product description. “Relief in almost half of users” sounds like a therapeutic result but is what happens simply by taking anything during an attack that naturally tends to resolve within hours. Any survey without a control group measures this effect combined with any substance effect and cannot separate them.
In cannabis studies, there is also the problem of unblinding. THC causes noticeable psychoactive effects, so participants may guess what they received, which itself increases response. The 2026 trial authors tested this directly and after accounting for euphoria and subjective intoxication as covariates, results did not change. Such a test rarely appears in observational works on which most CBD materials rely.
How does the endocannabinoid system participate in trigeminal nociception?
It participates genuinely and this is the best documented thread of the whole topic. Activation of the trigeminovascular system and release of mediators from trigeminal nerve endings near dura mater vessels is an established migraine attack mechanism. The endocannabinoid system modulates this activation at several levels (Greco et al., Frontiers in Neuroscience, 2018).
Anandamide, one of two main endocannabinoids, is produced on demand in inflammatory conditions and acts mainly via cannabinoid receptors. It is rapidly broken down by FAAH enzyme, fatty acid amide hydrolase. Blocking this enzyme raises anandamide concentration exactly where it is produced, e.g., in the trigeminal ganglion and meninges. That is why FAAH inhibitors are studied as potential antimigraine drugs.
It is worth separating two things that merge in advertising texts. Modulating the endocannabinoid system is a reasonable pharmacological target in migraine. This does not mean that oral cannabidiol is an effective way to achieve this in a person with migraine attack. The first sentence is supported by preclinical literature. The second awaits studies.
A broader context of anti-inflammatory cannabinoid action is described in the text on CBD mechanism in inflammatory states.
What is the clinical endocannabinoid deficiency hypothesis?
It is the assumption that in some patients baseline endocannabinoid system tone is reduced and that this explains treatment-resistant pain syndromes. The author calls it a theory and hypothesis, not a finding (Russo, Cannabis and Cannabinoid Research, 2016). Migraine, fibromyalgia, and irritable bowel syndrome are named as candidates.
There is a biochemical basis. Lower anandamide levels were found in cerebrospinal fluid of chronic migraine patients than in controls, with a negative correlation with CGRP peptide level (Sarchielli et al., Neuropsychopharmacology, 2007). Other works described abnormal endocannabinoid distribution in chronic migraine and medication overuse headache (Cupini et al., Neurobiology of Disease, 2008).
From here starts overinterpretation. The fact that a molecule concentration is lower in disease does not mean that administering another molecule from the same family externally will correct deficiency or improve symptoms. It is not even known if lowered anandamide is cause, effect, or epiphenomenon. Studies measured state in already ill persons.
Additionally, cannabidiol is not anandamide and does not directly stimulate cannabinoid receptors as endocannabinoids do. The deficiency hypothesis is thus used to justify CBD use, though logically it would lead rather to FAAH inhibitors or receptor agonists.
What do animal models show and what must not be inferred from them?
They show reasonable signals and simultaneously illustrate why a signal is not enough. In a mouse study, administration of a cannabidiol and THC mixture in a 100 to 1 ratio abolished photophobia induced by intracerebroventricular CGRP and partially alleviated spontaneous pain (Zorrilla et al., Cephalalgia, 2025).
Note the dose: 100 mg cannabidiol per kilogram intraperitoneally. For a 70 kg human, this corresponds to about seven grams of CBD injection, not a few drops of sublingual oil. Rodent doses do not scale linearly to humans, but the difference here is so large it invalidates comparison with store dosing.
The second preclinical research line concerns FAAH inhibitors, the enzyme breaking down anandamide. Such a compound reduced pain responses in a rat migraine model induced by nitroglycerin and lowered CGRP gene expression and inflammatory cytokines in the trigeminal ganglion, though tissue endocannabinoid levels did not change (Greco et al., International Journal of Molecular Sciences, 2023). This study concerns a completely different molecule than cannabidiol, though in the same system.
Animal migraine models measure surrogate behaviors: light avoidance, facial grimace, sensitivity to touch in the face. A mouse does not report unilateral pulsating pain, nausea, or aura. Pain pharmacology history is full of substances effective in rodents that failed in clinical trials.
Note one detail in the mouse study. The tested substance was a cannabidiol and THC mixture, not cannabidiol alone. Even in the preclinical work underlying advertising claims about CGRP inhibition, the tested substance is not what you find in an oil bottle. This pattern repeats at every evidence level, from rodent to randomized trial.
How much CBD is needed for migraine?
No one has established this and it cannot be derived from available data. No clinical study compares oral CBD doses in migraine, so every ready-made scheme like “start low and increase every three days” is invented by the author or seller. Below are doses actually given to study participants, with who and why studied.
| Study | What was given | Participants | Indication |
|---|---|---|---|
| Schuster et al., 2026 | vaporized flower 11 percent CBD, single dose in attack | 92 people, 247 attacks | acute migraine attack |
| Devinsky et al., 2020 | 10 and 20 mg CBD per kg per day, oral | 4 randomized studies | drug-resistant epilepsy |
| Shannon et al., 2019 | 25 to 175 mg CBD per day, oral | 72 adults | anxiety and sleep disorders |
| Gorbenko et al., 2026 | 30 mg CBD single dose, oral | 13 healthy volunteers | drug interaction study |
None of these specify how much CBD an episodic migraine patient needs. The only dose tested in migraine was inhaled, not swallowed, and did not beat placebo. If you search online for “CBD dosing protocol in migraine,” you are viewing marketing content disguised as guidelines.
The practical conclusion is inconvenient but honest: deciding to try CBD for migraine is a decision without data support on dose, duration, or non-response cutoff. This is a conversation to have with your doctor, especially if you take prophylaxis.
There is a number setting a ceiling, not a recommendation. The EFSA panel derived a provisional safe dose of 0.0275 mg cannabidiol per kilogram per day, about 2 mg for a 70 kg person, with an uncertainty factor of 400 and only for supplements of at least 98 percent purity without nanoparticles (EFSA NDA Panel, EFSA Journal, 2026). The same document states that cannabidiol safety cannot be established in people under 25, pregnant or breastfeeding women, or those taking medications. Readers of this text usually belong to the last group.
How much CBD from oil reaches the bloodstream?
It is not known exactly and this is not an excuse. A systematic review of cannabidiol pharmacokinetics in humans found only 24 studies with pharmacokinetic data out of 792 reviewed. Absolute bioavailability was measured only for one route, smoking, and was 31 percent (Millar et al., Frontiers in Pharmacology, 2018).
For oral and sublingual administration, no such value was established, although these are the most common ways to take CBD. Numbers “13 to 19 percent” circulating on Polish sites and sometimes attributed to this review do not appear in the original. The authors explicitly mention data scarcity and discrepancies between studies.
What is known for sure: half-life after buccal spray is 1.4 to 10.9 hours, after chronic oral dosing 2 to 5 days, and after smoking about 31 hours. Maximum concentration rises with dose, is higher after food and in fatty preparations, and peak appears within zero to four hours.
For a migraine patient, this has one practical consequence. With such a wide range of time to peak, it is impossible to plan oil intake “at attack onset” with reasonable precision. More about administration routes is in the text on how to take CBD.
What drug interactions with migraine medications are documented for CBD?
One was measured in a clinical study and concerns amitriptyline, used in migraine prophylaxis. A single 30 mg dose of CBD increased amitriptyline area under the curve by 13 percent and maximum concentration by 17 percent in healthy volunteers (Gorbenko et al., British Journal of Clinical Pharmacology, 2026).
The study included 13 people, 12 completed the protocol. The effect was moderate and with such a small sample it is impossible to predict what happens at higher doses and daily use. Tramadol concentration in the same study did not change, showing metabolism inhibition does not affect all drugs equally.
| Drug | Role in Migraine | Knowledge on CBD Interaction |
|---|---|---|
| amitriptyline | prophylaxis | interaction measured in clinical study, increased plasma concentration |
| tramadol | analgesic | no concentration change in same study |
| triptans | attack treatment | no interaction study, only pharmacological assumption |
| topiramate, propranolol | prophylaxis | no interaction study with CBD in migraine patients |
| anti-CGRP antibodies | prophylaxis | not metabolized hepatically, interaction unlikely |
The mechanistic background has been known for years: cannabidiol inhibits several cytochrome P450 isoenzymes and affects drug transporters, and safety reviews call for further research on this phenomenon (Iffland and Grotenhermen, Cannabis and Cannabinoid Research, 2017). When taking anticoagulants or migraine prophylaxis, talking to your doctor is not a formality.
Can CBD be combined with triptans?
No one has studied this combination, so any answer is inference from pharmacology, not result. Triptans do not share a single metabolic pathway. Some are mainly metabolized by monoamine oxidase A, some by cytochrome P450 isoenzymes, and one is largely excreted by kidneys.
This difference matters because cannabidiol inhibits cytochrome P450. Theoretically, it may increase concentrations of triptans metabolized by this system and not affect others. Theoretically, as no human study has measured this in people taking both.
There is a second layer rarely mentioned. If you take triptans more than ten days per month, adding another substance does not solve the situation but obscures it. This is an indication to review treatment with a neurologist, not to experiment with supplements.
Practical approach if you want to try anyway: tell your doctor before starting, not after symptoms appear. Record start date and dose so any new symptoms can be linked. Do not change two things in the same week.
Symptoms that should prompt doctor contact after adding CBD to triptan include increased drowsiness, dizziness, palpitations, and unusual prolongation of post-attack phase. None are specific but all fit expected effects of increased drug plasma concentration. Do not stop prescribed prophylaxis on your own.
What adverse effects of CBD are confirmed in studies?
Best documented are gastrointestinal complaints. A meta-analysis of four randomized studies with 269 healthy adults showed nearly sixfold higher diarrhea risk after CBD than placebo, with wide confidence intervals (Sawaira et al., Annals of Medicine and Surgery, 2026).
In the same analysis, abdominal pain and headache were slightly more frequent after CBD but differences were not statistically significant. Fatigue, dizziness, and upper respiratory infections did not differ between groups. Authors emphasize data concern short-term use in healthy people and do not answer about chronic supplementation in patients.
A broader safety review lists most common symptoms as drowsiness, diarrhea, appetite and weight changes, considering CBD profile more favorable than many drugs used in the same indications. The same review notes lack of data on long-term use, hormonal effects, and drug interactions.
In migraine context, one adverse effect deserves special attention. Drowsiness at higher doses overlaps with post-attack phase, dominated by fatigue and slowing. For someone returning to work after an attack, this may complicate assessment of whether improvement occurred.
When does headache require urgent help?
When it shows features suggesting secondary headache, i.e., symptom of another disease, not migraine. A set of such alarm signs is collected in the SNNOOP10 list, designed to increase chances of detecting headaches requiring urgent diagnostics (Do et al., Neurology, 2019).
| Alarm Sign | What It May Mean |
|---|---|
| sudden pain peaking in seconds, worst in life | subarachnoid hemorrhage, artery dissection |
| fever with neck stiffness | meningitis or encephalitis |
| neurological deficit or consciousness disturbance | stroke, tumor, mass effect |
| pain after head injury | intracranial hematoma |
| first-ever headache onset after age 65 | giant cell arteritis, intracranial lesion |
| position-dependent pain, worsened by cough or exertion | cerebrospinal fluid pressure disorder |
| pain increasing week by week, change in pattern | neoplasm, intracranial hypertension |
| headache in pregnancy or postpartum, eye pain with autonomic symptoms | venous thrombosis, angle-closure glaucoma |
Sudden pain peaking within seconds is an emergency, not a reason to wait it out. The same applies to pain with fever and neck stiffness and any pain with persistent neurological deficit. In these scenarios, emergency number is the right solution, and oil has no role.
What is medication overuse headache?
It is a secondary headache arising from treatment of attacks when acute drugs are taken too often. ICHD-3 criteria diagnose it in a person with headache on 15 or more days per month, taking triptans, opioids, or combination drugs at least 10 days per month, and simple analgesics 15 or more days, for over three months.
The mechanism relates to this article’s topic. In 20 patients with medication overuse headache, platelet levels of anandamide and 2-AG were reduced similarly as in chronic migraine, associated with lowered serotonin (Rossi et al., European Journal of Clinical Pharmacology, 2008). This is biologically interesting but does not change management.
Management involves withdrawal of overused drug and introduction of prophylaxis, usually under medical supervision, as first days can be difficult. Adding CBD to daily acute drugs does not solve the problem and may mask it: improved well-being without reducing days with acute drug maintains the mechanism.
A simple self-test: count days per month you take any analgesic or triptan. If more than ten, priority is doctor visit, not supplement choice. This one number says more about prognosis than the whole rest of the text.
Does CBD help in menstrual migraine?
There is no data on this, though it is a subtype worth separate attention. Pure menstrual migraine affects about 1 percent of women, and migraine associated with menstruation 6 to 7 percent. Attacks in this subtype usually occur without aura, are stronger, longer, and harder to treat than others (Maasumi et al., Headache, 2017).
This difference is due to estrogen level drop around menstruation. Hence the popular speculation: since estrogens also affect the endocannabinoid system, cannabidiol should help more here than in other subtypes. This is reasoning, not study result. No one has tested it in women with this diagnosis, and individual links in this chain are poorly documented in humans.
What has documented efficacy in this subtype: triptans for attack, with best data for several molecules in the group, and short-term perimenstrual prophylaxis started a few days before expected attack. A 2017 review also warns of a trap easily forgotten: some antiepileptic drugs used in migraine prophylaxis reduce hormonal contraceptive effectiveness.
The practical conclusion is simple. If your attacks align with your cycle, this is diagnostic information worth bringing to your doctor on paper. It changes treatment choice much more than oil selection, as it opens options unavailable in migraine without this pattern.
What has stronger evidence in migraine prophylaxis than CBD?
Several things, and this is practically the most important part of the article. Magnesium has randomized double-blind placebo-controlled studies, and oral magnesium for headaches has been included in several national and international guidelines based on this (Maier et al., Nutrients, 2020). This is a level of evidence CBD lacks in migraine.
Riboflavin (vitamin B2) has a meta-analysis of 12 clinical studies with 749 participants, showing a reduction of attacks by 1.39 per month and shortening duration, dose-dependent up to 400 mg daily (Amini et al., Journal of Research in Medical Sciences, 2026). Heterogeneity was high, so read cautiously, but this is still a different league than case series.
Among drugs, anti-CGRP antibodies and oral gepants have phase 2 and 3 studies; four antibodies and three gepants are approved for migraine treatment by the US FDA (Cohen et al., BioDrugs, 2022). Perimenstrual migraine resistant to standard prophylaxis has short-term prophylaxis options described in a separate review (Maasumi et al., Headache, 2017).
This is not to discourage trying CBD. It is about order. If you have migraine and have not tried any option with documented efficacy, starting with a product without evidence is a costly detour.
How to check what is really in CBD oil?
By certificate of analysis for a specific batch, not by label. A study published in JAMA compared label declarations on internet-purchased CBD extracts with lab analysis and found labels often inconsistent with content (Bonn-Miller et al., JAMA, 2017). This was the US market years ago, but the mechanism has not changed anywhere.
The certificate should state measured cannabinoid content in milligrams per milliliter, THC content, pesticide residues, heavy metals, residual solvents, and batch number matching the bottle. A document without batch number describes some oil, not necessarily the one you hold.
The second thing to check is arithmetic. A 5 percent oil contains 500 mg cannabidiol in a 10 ml bottle, 10 percent oil 1,000 mg, and 20 percent oil 2,000 mg. The declared percent refers to concentration in fluid, not dose per drop, and this is the most common source of counting errors.
The third warning sign is the product description itself. If the seller provides a ready dosing scheme for migraine or cites “clinical studies confirming efficacy,” you are dealing with content unsupported by literature. An honest description states how much substance is in the bottle and where the raw material comes from, not what it cures.
u Bucha’s store you will find hemp oils with certificates of analysis in the oils category. More about reading composition and differences between variants is in the guide CBD oils, everything you want to know.
How to plan your own trial and how to recognize no effect?
Set evaluation criteria before the first dose, or you will assess your mood, not the preparation effect. Migraine prophylaxis studies usually measure one thing: average number of attacks per month before and after treatment. The same counter suits a self-conducted trial and is memory-resistant.
Start with a month of observation without changes. Note attack date, duration, intensity on a 0 to 10 scale, accompanying symptoms, and every day you took acute medication. The last column is most important, as days with acute drug determine medication overuse headache risk and whether supplements are worth discussing.
Then change one thing at a time. If you start CBD, magnesium, and new sleep pattern simultaneously, after two months you will learn nothing about any of them. The same mistake is made by guide authors proposing five preparations at once and promising efficacy assessment after a month.
Record decision date and stick to it. After eight weeks, compare attack number with baseline month. If the counter is unchanged, that is the answer, and money is better spent on options with stronger foundations. Increasing dose just in case has no support, as no dose-response relationship for cannabidiol in migraine exists.
What is known today about CBD and migraine?
In summary: cannabidiol alone has no evidence of efficacy in migraine, and the only randomized study testing it showed no superiority over placebo. The endocannabinoid thread in trigeminal pain is real and well described but concerns a pharmacological target, not efficacy of a specific store product.
Remember three things from this text. First, if you read about a “CBD dosing protocol in migraine,” you are dealing with invented content, as such data do not exist. Second, interaction with amitriptyline was measured, so talking to your doctor when on prophylaxis is not a formality. Third, magnesium and riboflavin have stronger bases in migraine prophylaxis and at lower cost than CBD.
If you want to try cannabidiol anyway, do it as an experiment, not a hope purchase. Set in advance when you evaluate effect, count headache days before and during, do not change other treatment elements simultaneously. If after eight weeks headache days do not change, that is the answer.
Sleep disorders often accompany migraine as a separate problem and may be confused with preparation effect. We write about them in the text on how cannabis affects sleep. The full offer of hemp oils with certificates of analysis is in the oils category.
Frequently Asked Questions
Does CBD work for migraine?
There is no evidence for this. In the first randomized cannabis study in acute migraine attack, the CBD-dominant arm provided relief after two hours in 53 percent of attacks versus 47 percent with placebo, and the difference was not statistically significant (Schuster et al., Headache, 2026). Only the combination of THC with CBD showed superiority over placebo.
How much CBD should be taken for migraine?
No one has established this. There is no study from which an oral CBD dose for migraine could be derived, so ready-made dosing protocols are invented. Numbers from studies come from other indications: 25 to 175 mg per day in a series of 72 anxiety cases and 10 to 20 mg per kilogram in four trials on drug-resistant epilepsy.
Can CBD be combined with triptans?
No study has been conducted on this combination, so the answer is based solely on pharmacology. CBD inhibits several cytochrome P450 isoenzymes, and some triptans are metabolized by them. A clinically documented example concerns amitriptyline: 30 mg of CBD increased its plasma concentration in healthy volunteers. Consult such a combination with your attending physician.
Does CBD help with migraine aura?
There is no data from human studies. The hypothesis is based on animal models of cortical spreading depolarization and reviews of the endocannabinoid system in trigeminal pain (Greco et al., Frontiers in Neuroscience, 2018). No clinical study has measured the effect of CBD alone on aura duration or severity.
Does CBD oil work faster than a tablet?
A review of CBD pharmacokinetics in humans showed that data are too scarce to provide absolute bioavailability after oral or sublingual administration (Millar et al., Frontiers in Pharmacology, 2018). The only measured value, 31 percent, concerned smoking. Popular numbers about sublingual bioavailability of 13 to 19 percent do not come from this review.
Can CBD worsen headache?
A meta-analysis of four studies involving 269 healthy adults showed significantly more frequent diarrhea after CBD and a statistically non-significant trend toward more frequent headache (Sawaira et al., Annals of Medicine and Surgery, 2026). A separate risk is medication overuse headache if CBD is added to daily acute medications.
When does migraine require urgent medical visit?
When the pain appears suddenly and is the worst in life, when accompanied by fever with neck stiffness, neurological deficit, optic nerve swelling, or if it occurred after head trauma. A list of such signals is collected in the SNNOOP10 checklist (Do et al., Neurology, 2019). Then diagnostics are needed, not supplementation.
What is the difference between full-spectrum oil and isolate in the context of migraine?
No one has compared these two variants in a clinical study for migraine, so claims of superiority of one are marketing. The only randomized result concerned vaporized flower and showed that superiority over placebo was only given by the combination of THC with CBD, not cannabidiol alone (Schuster et al., Headache, 2026).
This article is for informational and educational purposes and does not constitute medical advice. Before starting cannabis or CBD for therapeutic purposes, consult a doctor, especially if you take other medications, are pregnant, or breastfeeding.
Author: Michał Waluk · Published: 2026-05-04 · Updated: 2026-09-22