CBD and addiction and intoxication: what do studies say
Does CBD cause addiction and intoxication? Results from studies by Babalonis 2017, Schoedel 2018, and Devinsky 2017, drug test risk, and EFSA safety assessment 2026.
In therapeutic doses, studies do not show the potential for abuse with cannabidiol. The signal only appears at single doses of 1500 and 4500 mg, and even then it is weaker than for alprazolam at a dose of 2 mg. The question 'does CBD cause addiction' has been circulating in Polish internet for years, and answers circulate along with numbers that no one verifies. This text starts from something different: from what can be read in specific studies with their methodology, number of participants, and results, including uncomfortable results. You will see here two experimental studies on the potential for abuse, data from a clinical study on epilepsy, epidemiological data on tetrahydrocannabinol itself, and the latest European safety assessment of cannabidiol. You will also see which popular claims we removed from this article because their sources could not be verified, and why specifically those. This arrangement has one advantage: it allows us to separate the question of addiction, which studies answer quite consistently, from questions about long-term safety and product quality, for which the answers are not reassuring at all.
KEY INFORMATION
- In the Babalonis 2017 study, oral cannabidiol at doses of 200, 400, and 800 mg did not signal potential for abuse in 31 frequent marijuana users; the results were at placebo levels across all measured scales.
- In the Schoedel 2018 study, a therapeutic dose of 750 mg did not differ from placebo, while doses of 1500 and 4500 mg yielded significantly higher results than placebo, although the average differences were less than 10 points on the scale compared to over 18 points for alprazolam and dronabinol.
- Tetrahydrocannabinol is a different substance with different risks: the cumulative probability of transitioning from use to addiction was 8.9% for cannabis compared to 67.5% for nicotine (Lopez-Quintero 2011).
- Full-spectrum products with trace THC could yield a positive urine test, while pure cannabidiol practically did not (Spindle 2020).
- The safety of cannabidiol cannot be established in individuals under 25 years of age, in pregnant and breastfeeding women, and in individuals taking medications (EFSA 2026).
The short answer regarding the criteria for diagnosis: there is no basis to speak of addiction. DSM-5 requires at least two out of eleven criteria within a year, including cravings, loss of control, tolerance, and withdrawal syndrome. For cannabidiol itself, neither withdrawal syndrome nor tolerance development has been described. A full breakdown of all criteria is in the later part of the text, and below is a summary of two studies on which this answer is based.
| Element | Babalonis 2017 | Schoedel 2018 |
|---|---|---|
| Dawki kannabidiolu | 0, 200, 400 i 800 mg doustnie | 750, 1500 i 4500 mg jednorazowo |
| Number of participants | 31 | 43 w fazie leczenia, 35 w analizie |
| Population | healthy, frequent marijuana users | recreational users of many substances |
| Komparator | smoked marijuana with THC content of 0.01% and 5.3-5.8% | alprazolam 2 mg oraz dronabinol 10 i 30 mg |
| Wynik wobec placebo | cannabidiol did not differ from placebo | signal only at 1500 and 4500 mg |
| Wynik wobec komparatora | active marijuana produced effects associated with abuse, cannabidiol did not | weaker than alprazolam and dronabinol |
What is the difference between CBD and THC at the receptor level?
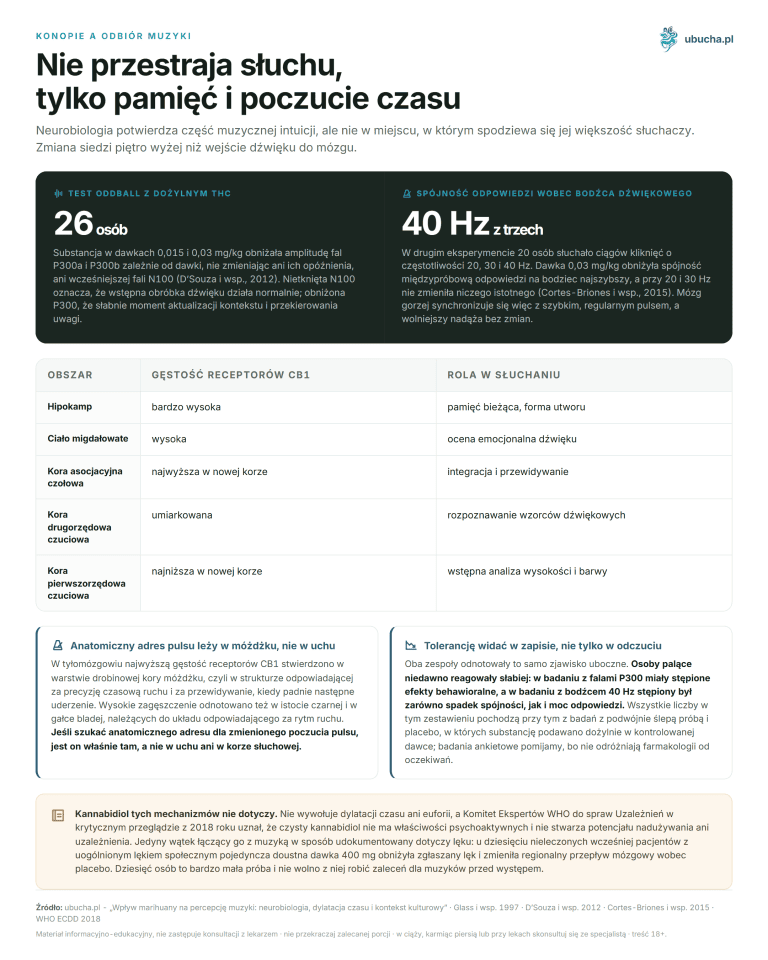
The difference comes down to how both molecules interact with the cannabinoid receptor CB1. Tetrahydrocannabinol is a partial agonist of the CB1 and CB2 receptors, and the responses it elicits depend on the level of receptor expression and the efficiency of signal transmission. Cannabidiol behaves oppositely: in cells and tissues expressing these receptors, it unexpectedly exhibits high efficacy as an antagonist of their agonists (British Journal of Pharmacology, Pertwee 2008).
The mechanism of this action was described in more detail a few years later. In cells expressing the CB1 receptor, cannabidiol reduced the efficacy and potency of two agonists, namely 2-arachidonoylglycerol and tetrahydrocannabinol, on pathways dependent on phospholipase C beta 3 and ERK1/2 kinases. It also limited the recruitment of arrestin 2 to the receptor, thereby preventing its internalization. The authors described cannabidiol as a non-competitive negative allosteric modulator of the CB1 receptor (British Journal of Pharmacology, Laprairie 2015).
It should be noted that this was work on cell models, not on humans. The authors themselves state that allosteric modulation along with actions independent of CB1 receptors may explain the observed effects of cannabidiol in the body. This is a more cautious formulation than the popular slogan that "CBD blocks the effects of THC."
The practical conclusion is clear. A substance that does not activate the CB1 receptor but weakens the signal of its agonists has no means to induce a state of intoxication in the same mechanism as tetrahydrocannabinol. The pharmacological difference between cannabinoids and their acid forms is described in more detail in our entry on destylacie konopnym i izolacie.
How often does THC use lead to addiction?
Here, epidemiological data is needed, not pharmacology. In an analysis of data from the American population study NESARC, individuals who had ever used nicotine (15,918 individuals), alcohol (28,907), cannabis (7,389), or cocaine (2,259) were included. The cumulative probability of transitioning from use to addiction was 67.5% for nicotine, 22.7% for alcohol, 20.9% for cocaine, and 8.9% for cannabis (Drug and Alcohol Dependence, Lopez-Quintero 2011).
This same work provides something that is often overlooked in popular summaries: half of the cases of cannabis addiction appeared about five years after first use, while for nicotine it was about 27 years, and for alcohol about 13 years. The transition to cannabis addiction occurred faster than for nicotine and alcohol, despite the lower final probability.
These data pertain to cannabis as a recreational drug, meaning material with a predominance of tetrahydrocannabinol, not pure cannabidiol. This material has also changed over time. An analysis of 38,681 samples confiscated in the United States showed an increase in the average THC content from about 4% in 1995 to about 12% in 2014, alongside a decrease in CBD content (Biological Psychiatry, ElSohly 2016).
Conclusions from studies on recreational cannabis do not automatically transfer to products containing cannabidiol, and this works both ways. We discuss the impact of THC-predominant cannabis in more detail in our text on the impact of marijuana on mental health..
How is the potential for abuse measured?
Without this question, the two most important studies on this topic are read intuitively. Assessing the potential for abuse in humans is a separate, formalized procedure, not merely an observation of whether someone reaches for the substance again. The reason for conducting it in the case of cannabidiol was its legal status: the substance was listed in the first schedule of the American Controlled Substances Act, yet there were no well-controlled data on its potential for abuse (Drug and Alcohol Dependence, Babalonis 2017).
The design of such a study looks similar every time. Participants in a crossover and double-blind design are given the substance being studied, a placebo, and at least one positive control, which is a drug with known abuse potential; the Schoedel 2018 study additionally used a double-masked form of the drug. If the positive control does not differ from placebo, the study is invalid because it lacks sensitivity.
The primary endpoint is the maximum effect on a visual-analog scale of drug preference. Alongside this, overall preference, declared willingness to take the substance again, positive and negative effects, and similarity to known substances are measured. Cognitive and psychomotor functions are assessed separately, in the Schoedel 2018 study using a divided attention test, the Hopkins verbal learning test, and a symbol substitution test.
The method has clear boundaries. It measures a single dose in volunteers selected to be sensitive to the effects of psychoactive substances, rather than the course of several months of use in the general population. It answers the question, "does this substance signal abuse in laboratory conditions?", rather than the question, "what happens after a year of daily use?".
What did the Babalonis 2017 study show?
This is the first controlled study of the abuse potential of pure cannabidiol in humans. The study included 31 healthy, frequent marijuana users. Participants received oral cannabidiol in doses of 0, 200, 400, and 800 mg, administered alone and in combination with smoked marijuana containing THC at 0.01% or 5.3-5.8%. Each participant underwent one combination of doses during eight weekly outpatient sessions (Drug and Alcohol Dependence, Babalonis 2017).
The result was unequivocal in both directions. Active marijuana consistently produced subjective effects associated with abuse, including the feeling of intoxication, at a significance level below 0.05. Cannabidiol in all measured parameters behaved like a placebo, with a significance level above 0.05. The authors concluded that at the doses studied, cannabidiol did not show any signals of abuse potential.
It is important to clarify the version that circulates on Polish websites. The Babalonis study did not include eight individuals, did not use doses of 750, 1500, and 4500 mg, nor did it compare cannabidiol with alprazolam and dronabinol. These elements belong to another, later study described in the next section. Confusing the designs of both studies is one of the most commonly repeated mistakes on this topic.
The limitation of this work is equally significant. It was a secondary analysis of data collected to study the interactions between cannabidiol and marijuana, based on a sample of 31 individuals, and concerned doses up to 800 mg. What happens at doses many times higher is only addressed in a subsequent study.
What did the Schoedel 2018 study show and what did it not show?
This study was designed to assess the abuse potential of a purified oral solution of cannabidiol, as adverse effects on the central nervous system had been reported in phase three studies on childhood epilepsy. Single doses of cannabidiol at 750, 1500, and 4500 mg were compared with alprazolam at 2 mg, dronabinol at doses of 10 and 30 mg, and with placebo, in recreational users of multiple substances (Epilepsy and Behavior, Schoedel 2018).
Out of 95 qualified individuals, 43 entered the treatment phase, and 35 were included in the pharmacodynamic analysis. Alprazolam and dronabinol produced significantly higher maximum scores on the drug liking scale than placebo, confirming the methodological validity of the study. For cannabidiol at a dose of 750 mg, the difference from placebo was not statistically significant.
And here begins the part that disappears in popular summaries. For doses of 1500 mg and 4500 mg, the result differed from placebo in a statistically significant way, with p values of 0.04 and 0.002. However, the authors noted that the mean differences were less than 10 points on the visual-analog scale, while for positive controls they exceeded 18 points. Thus, the authors' conclusion is precise: the therapeutic dose of 750 mg showed a significantly low potential for abuse, while high and supra-therapeutic doses produced detectable subjective effects, significantly weaker than those of alprazolam and dronabinol.
The study also assessed cognitive functions using a divided attention test, the Hopkins verbal learning test, and a symbol substitution test. Unlike alprazolam, cannabidiol did not show a noticeable impact on these measures. Most adverse effects were mild or moderate in severity, and no serious events or deaths were reported.
What is known from clinical studies on Epidiolex?
The most frequently cited study is a trial involving children and young adults with Dravet syndrome. 120 participants with drug-resistant epilepsy were randomly assigned to receive an oral solution of cannabidiol at a dose of 20 mg per kilogram of body weight per day or to placebo, as an adjunct therapy to standard antiepileptic treatment. The treatment period lasted 14 weeks, following a four-week baseline phase (New England Journal of Medicine, Devinsky 2017).
The median monthly seizure frequency decreased from 12.4 to 5.9 in the cannabidiol group compared to a decrease from 14.9 to 14.1 in the placebo group. At least a fifty percent reduction in seizures was achieved by 43% of participants compared to 27% on placebo, but this difference did not reach statistical significance (p equals 0.08). 5% were seizure-free compared to 0%, and here too significance was not achieved.
However, for the topic of this article, the part regarding safety is more important, and it is not exclusively optimistic. Diarrhea, vomiting, fatigue, fever, drowsiness, and abnormal liver function tests occurred more frequently than in the placebo group. More individuals withdrew from the cannabidiol group than from the placebo group. The authors concluded that cannabidiol provided greater seizure reduction than placebo and was associated with more frequent adverse effects.
This study did not include tens of thousands of patient-years of exposure or observations longer than a year, although such statements circulate on Polish websites along with its number. It involved 120 individuals over 14 weeks. Statements about long-term exposure were removed from this article because they do not originate from this work.
How much cannabidiol actually enters the bloodstream?
This question lies at the heart of the entire discussion about doses, and the answer is surprisingly sparse. A systematic review of the pharmacokinetics of cannabidiol in humans searched 792 publications and found 24 that provided pharmacokinetic parameters in humans at all. This is little for a substance used widely (Frontiers in Pharmacology, Millar 2018).
Absolute bioavailability was measured only for the inhalation route and was found to be 31%. For other routes of administration, no study has undertaken such measurement, even though intravenous formulations, without which it cannot be performed, were available. Therefore, all tables circulating on the internet comparing oral, sublingual, and inhalation bioavailability are based on something that has not been measured.
What does this review reliably provide? A half-life of 1.4 to 10.9 hours after oral mucosal spray, from 2 to 5 days after chronic oral administration, 24 hours after intravenous administration, and 31 hours after smoking. The maximum concentration is reached within 0 to 4 hours, faster after inhalation than after oral administration, and the area under the curve and maximum concentration increase with dose.
Another practically significant observation is that the maximum concentration increases after a meal and in fat-based formulations. Thus, the same number of milligrams on the label results in different exposure when taken on an empty stomach and after eating. The authors of the review summarize that data is lacking, and the available data can be inconsistent, and that solid data for different product forms are still needed.
Does cannabidiol interact with medications?
This is a real clinical problem and it has nothing to do with addiction. The review of clinical and animal data states outright that the effect of cannabidiol on liver enzymes and drug transporters requires further research, as this substance is sometimes used as an adjunct therapy to other treatments (Cannabis and Cannabinoid Research, Iffland 2017).
The same review confirms the favorable adverse effect profile of cannabidiol itself compared to drugs used in epilepsy and psychotic disorders. Fatigue, diarrhea, and changes in appetite and body weight were the most commonly reported. The authors also note that some toxicological parameters remain unstudied, including the effect of cannabidiol on hormones.
The picture from the clinical study confirms this. In the trial on Dravet syndrome, abnormal liver function tests occurred more frequently in the cannabidiol group than in the placebo group, and treatment was conducted as an adjunct to standard antiepileptic therapy (Devinsky 2017). This is not a phenomenon caused by the substance itself in isolation from the rest of the treatment.
The European assessment puts it most sharply: studies in humans have indicated the hepatotoxic potential of cannabidiol, especially when used concurrently with other medications, and for this reason, safety cannot be established in individuals taking medications (EFSA 2026). The statement "cannabidiol is not addictive", even when kept within its scope, does not answer the question of whether it can be safely combined with one's own pharmacotherapy.
Does CBD meet the criteria for addiction according to DSM-5?
The DSM-5 classification defines substance use disorder by meeting at least two of eleven criteria within a twelve-month period. Among them are loss of control over quantity, compulsive substance seeking, increased tolerance, withdrawal symptoms, and neglect of responsibilities (American Psychiatric Association, DSM-5).
The studies of abuse potential described above measure only one fragment of this picture: the subjective liking of the substance and the desire to take it again. This is standard methodology used in drug assessment, but it does not replace long-term observation. The data we have comes from single doses in adult volunteers and from a several-week clinical study in children.
So what do we not know? We do not have studies that have tracked individuals taking cannabidiol at consumer doses over the years concerning the eleven DSM-5 criteria. The review of clinical and animal data states directly that there is a lack of studies with a larger number of participants and a longer duration of chronic administration (Cannabis and Cannabinoid Research, Iffland 2017).
There is also a distinction that is easy to overlook in casual conversation. Getting used to an evening ritual and losing control over quantity are two different phenomena, and the diagnostic criteria require the latter. Regularity of use of anything, from coffee to supplements, does not meet the definition of a disorder until compulsion and harm arise. However, this distinction is not an alibi: it only means that the question of addiction must be asked precisely, and not that the answer is predetermined.
The honest answer is: available studies have not detected a signal of abuse potential at therapeutic doses, and at supra-therapeutic doses, they detected subjective effects weaker than those associated with benzodiazepines. This is not the same as evidence that long-term use does not lead to any dependency pattern, as such a study simply does not exist.
What is the difference between tolerance and addiction?
These are two distinct phenomena that can coexist but are not identical. Tolerance is a decrease in the body's response to a repeated dose, requiring an increase in dosage to achieve the same effect. Addiction is a pattern of compulsive use despite harm, as described in diagnostic criteria. The former is a pharmacological phenomenon, while the latter is clinical-behavioral.
Classical receptor tolerance involves desensitization or internalization of the receptor after chronic stimulation. In the case of cannabidiol, a mechanism has been described that works in the opposite direction: this molecule limits the recruitment of arrestin 2 to the CB1 receptor and prevents its internalization (Laprairie 2015). This is an observation from cell models, not from clinical observations.
The popular phenomenon of "reverse tolerance" found online, which refers to the alleged decrease in effective dose after several weeks of use, has no confirmation in the peer-reviewed literature that was accessible while writing this text. In the previous version of the article, it was cited, leading to a work on a completely different topic. Therefore, we leave the phenomenon itself as a user report, without supporting it with a source that does not exist.
The same applies to withdrawal syndrome. The absence of reports on withdrawal symptoms is not the same as a studied absence of such symptoms. In the study on Dravet syndrome, withdrawal syndrome was not reported, but the study lasted 14 weeks and was not designed to look for it (Devinsky 2017).
Can full-spectrum oil cause intoxication or give a positive test result?
These two questions have different answers, and mixing them is a source of considerable misunderstanding. The answer to the second question has been measured. In a study involving six healthy adults, oral and vaporized cannabidiol at a dose of 100 mg, vaporized cannabis with a predominance of cannabidiol (100 mg CBD and 3.7 mg delta-9-THC), and placebo were compared, collecting urine samples for five days after administration (Journal of Analytical Toxicology, Spindle 2020).
After administering pure cannabidiol, only 1 out of 218 samples tested positive in the screening at a threshold of 20 ng/ml, and none exceeded the confirmatory threshold of 15 ng/ml. After inhalation of cannabis with a predominance of cannabidiol, nine samples were positive at the threshold of 20 ng/ml, two at the threshold of 50 ng/ml, and four were confirmed by LC-MS-MS above 15 ng/ml. The authors conclude that acute administration of pure cannabidiol will not yield a positive result according to current guidelines, but products containing delta-9-THC may.
However, this work does not answer the question of intoxication. The detectability of a metabolite in urine and the psychoactive effect are two different things: the analytical threshold can be many times lower than the dose that causes any sensation. In the previous version of this article, a specific number of milligrams was stated as the psychoactive threshold for THC, supported by a source whose content cannot be read today. We removed it instead of repeating it.
For individuals subjected to testing at work or in sports, the practical conclusion is one: it is the content of delta-9-THC in the product that matters, not the declaration of cannabidiol on the label. We expand on this topic in a separate text about CBD and drug tests at work, behind the wheel, and in sports..
Why does this topic raise so many controversies?
A significant part of the confusion can be explained by the discrepancy between what is studied in the laboratory and what the consumer buys in the store. Pharmacological studies are conducted on a purified substance with a known concentration. The market provides products whose composition may differ from what is declared, and this is not a supposition but a result of measurement.
In the analysis of fourteen commercial cannabidiol oils available in European countries, nine samples had concentrations significantly deviating from the declared amount, while five were within reasonable limits. The authors pointed out the lack of clear regulation of oil products with cannabidiol in EU law as the reason for this state and explicitly stated that it leaves consumers without quality guarantees (Molecules, Pavlovic 2018).
The implication for the discussion about intoxication is direct. If a product claiming to be free of tetrahydrocannabinol actually contains it, the user may experience an effect they did not expect and attribute it to cannabidiol. Researchers are studying one substance, while the consumer describes the effects of a different mixture.
A similar labeling audit was previously conducted in the American market (JAMA, Bonn-Miller 2017). In the previous version of this article, specific percentages of incorrectly labeled products were attributed to it. Since this publication does not have an available abstract or open full text, the numbers could not be confirmed at the source and were removed. The fact remains that such an audit was conducted.
What do people using CBD experience in practice?
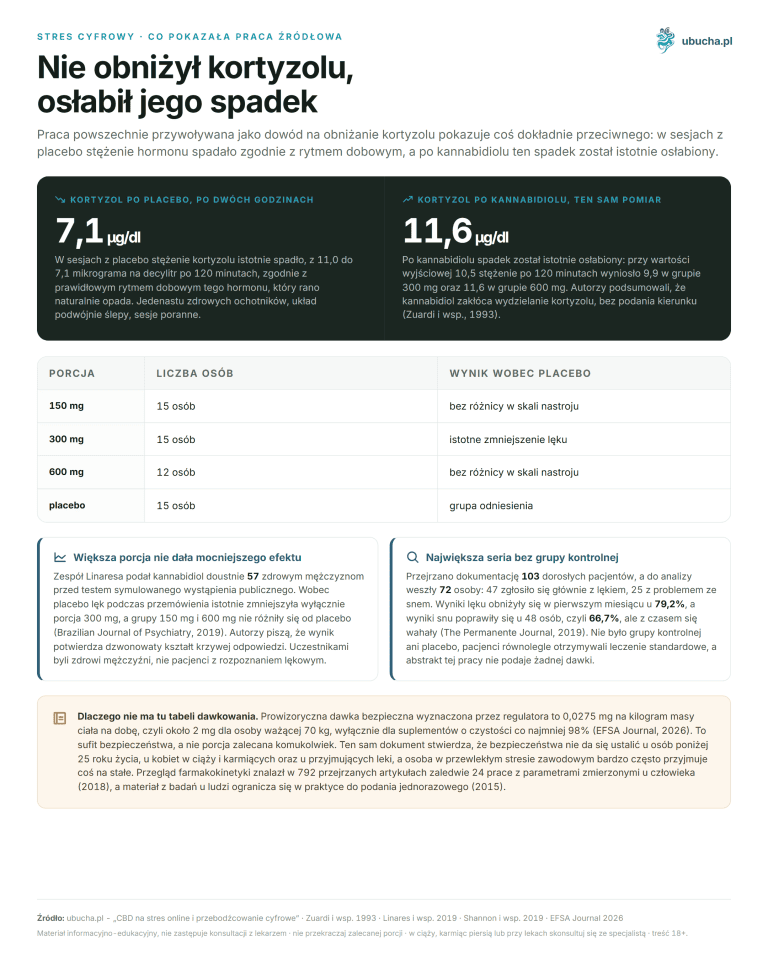
The most frequently cited description of patient experiences is a retrospective case series from a psychiatric clinic. Documentation of 103 adult patients was reviewed, and the final sample included 72 individuals primarily reporting anxiety (47 individuals) or poor sleep (25 individuals). Results were assessed using validated tools before and after the administration of cannabidiol (The Permanente Journal, Shannon 2019).
Anxiety scores decreased in the first month for 57 patients, or 79.2%, and remained at a reduced level throughout the observation period. Sleep scores improved in the first month for 48 patients, or 66.7%, but fluctuated over time. Cannabidiol was well tolerated by all patients except for three.
The authors themselves cautiously state the conclusions: cannabidiol may provide benefits in anxiety disorders, and controlled clinical trials are needed. This is a case series without a control group, so it does not separate the effect of the substance from the effect of contact with a physician and from the natural course of symptoms.
A broader review confirms this limitation. Preclinical data strongly support the anxiolytic action of cannabidiol, while evidence in humans is limited to single-dose administration, and there are few studies in clinical populations (Neurotherapeutics, Blessing 2015). The feeling of calm described by users fits into this picture, but it is not the same as a proven therapeutic effect.
What does the latest European safety assessment say?
It is clearly more cautious than most texts circulating in Polish internet. The EFSA panel on nutrition and novel foods updated its position on the safety of cannabidiol as a novel food in 2026, including a review of animal studies and human research published up to June 2024 (EFSA Journal, 2026).
The panel derived a provisional safe dose of 0.0275 mg per kilogram of body weight per day using the benchmark dose method, which is about 2 mg per day for a person weighing 70 kg, applying an uncertainty factor of 400. This is a safety ceiling, not a recommendation or a dose to be measured. It applies only to supplements with a purity of cannabidiol of at least 98%, without nanoparticles, with a safe production process, and excluded genotoxicity.
The gaps indicated in the 2022 position have not been closed. Animal studies have shown consistent liver toxicity, while human studies indicated potential hepatotoxicity, especially with concurrent use of medications. Cannabidiol crosses the placenta and accumulates systemically, and long-term sex-dependent neurodevelopmental effects have been noted after prenatal exposure. Changes in thyroid hormone levels and adrenal histopathology have also been observed, while immunotoxicity has not been studied at all.
The safety of cannabidiol cannot be established in individuals under 25 years of age, in pregnant and breastfeeding women, and in individuals taking medications simultaneously. (EFSA 2026). This statement concerns a large portion of individuals interested in the topic of this article and cannot be reconciled with the claim that cannabidiol is safe for everyone.
Why do we not refer to the WHO report from 2018 here?
Because it was not possible to verify it at the source, and the article based on a document that the author did not reach is worth as much as its weakest link. The address under which the body of Polish texts on cannabis cites a critical review of cannabidiol prepared for the Expert Committee on Addiction does not currently reference that document. The same dead link has been found in dozens of articles on this blog and is being removed from them.
With this link traveled one specific sentence: that cannabidiol is well tolerated in doses up to 1500 mg per day. This sentence functioned as information about safety, and often directly as encouragement to increase the dose. In light of the provisional safe dose derived by EFSA, which is about 2 mg per day for a person weighing 70 kg, this is a discrepancy of hundreds of times.
This does not mean that the document does not exist or that it said something contrary. It means that we could not read it, so we do not base our claims on it. The number 1500 mg appears rightly in another part of this text: as one of the doses tested in the Schoedel 2018 study, where it yielded a significantly different result from placebo. This is a description of the experiment, not a guideline for the reader.
The same principle applied to several other sentences. Sales data from the store presented as statistics, the names of committee experts whose participation could not be confirmed, and the percentages of adverse effects attributed to a document that was not read were removed from this article. We discuss the question of addiction itself in the text. whether CBD is addictive.
What does this mean for the reader?
First of all, cannabidiol and tetrahydrocannabinol are not the same conversation. The former acts on the CB1 receptor as a negative allosteric modulator in cell models, while the latter acts as a partial agonist responsible for the psychoactive effect. Data on the potential for addiction, which is 8.9% cumulative probability, pertains to cannabis as a recreational drug, not cannabidiol products.
Secondly, two experimental studies on the potential for abuse yielded consistent but not identical results. At doses up to 800 mg, cannabidiol behaved like a placebo in all measures. At 1500 and 4500 mg, subjective effects were detectable, although significantly weaker than after alprazolam and dronabinol. The claim that cannabidiol 'does not differ from placebo at any dose' is an oversimplification in light of the second of these studies.
Thirdly, practical risk does not lie where it is usually sought. Real problems include the detectability of delta-9-THC in urine testing after full-spectrum products, discrepancies between labels and contents, and interactions with medications. None of these constitute addiction, but each can cost the reader more than the hypothesis they are asking about.
Fourthly, the lack of evidence for addiction is not evidence of safety for everyone. The safety of cannabidiol cannot be established for individuals under 25 years of age, for pregnant and breastfeeding women, and for those taking medications. If you belong to any of these groups, the conversation about dosage is a conversation with a doctor, not with an article.
Frequently Asked Questions
Does CBD cause addiction?
Available studies did not detect a signal of potential abuse at doses up to 800 mg, where cannabidiol behaved like a placebo in 31 frequent marijuana users (Babalonis 2017). However, there are no studies tracking individuals using cannabidiol over years for DSM-5 criteria.
Can you get intoxicated from CBD?
Cannabidiol does not activate the CB1 receptor like tetrahydrocannabinol but acts as a non-competitive negative allosteric modulator of this receptor in cell models (Laprairie 2015). In tissues expressing CB1 and CB2 receptors, it behaves like an antagonist of their agonists (Pertwee 2008).
Is a dose of 1500 mg of CBD safe?
This statement circulates without a verifiable source. In the Schoedel 2018 study, a dose of 1500 mg resulted in a significantly different outcome from placebo on the scale of drug preference. The EFSA panel derived a provisional safe dose of about 2 mg per day for a person weighing 70 kg (EFSA 2026).
Will CBD affect the results of a drug test?
After pure cannabidiol, only 1 out of 218 urine samples tested positive in screening, and none exceeded the confirmatory threshold. After vaporizing cannabis with a CBD predominance containing 3.7 mg of delta-9-THC, nine samples were positive, and four were confirmed (Spindle 2020).
Can you build tolerance to CBD?
There is a lack of studies that would verify this. In cell models, cannabidiol limits the internalization of the CB1 receptor, meaning it acts oppositely to substances that cause classical receptor tolerance (Laprairie 2015). The popular phenomenon of 'reverse tolerance' has no confirmation in the peer-reviewed literature.
What did the study on Epidiolex in children show?
In a trial involving 120 individuals with Dravet syndrome, the median number of seizures dropped from 12.4 to 5.9 per month compared to a decrease from 14.9 to 14.1 on placebo, with a dose of 20 mg/kg/day over 14 weeks. Diarrhea, vomiting, drowsiness, and abnormal liver tests were more frequent (Devinsky 2017).
Why do CBD products have such varying effects?
Because the composition can differ from what is declared. In an analysis of fourteen commercial cannabidiol oils from the European market, nine samples had concentrations significantly deviating from the declarations, and the authors pointed to the lack of uniform regulation as the cause (Pavlovic 2018).
Who should not use cannabidiol?
The EFSA panel stated that the safety of cannabidiol cannot be established in individuals under 25 years of age, in pregnant and breastfeeding women, and in individuals taking medications simultaneously. In these groups, the decision to use it should be made with a doctor, not independently (EFSA 2026).
This article is for informational and educational purposes only and does not constitute medical advice. Before starting to use hemp or CBD for therapeutic purposes, consult your doctor, especially if you are taking other medications, are pregnant, or breastfeeding.
Author: Michał Waluk · Opublikowano: 2026-05-11 · Aktualizacja: 2026-08-24