
Hemp and sleep: how CBD and CBN affect insomnia
CBD, CBN, and sleep without marketing: what polysomnography has shown, why the myth of sleep-inducing CBN is not supported by data, how to choose a product, and when to see a doctor.
Half of adult Poles report sleep disturbances, and among women, the percentage reaches 58.9% (Nowicki et al., Psychiatria Polska, 2016). The market for natural solutions has been growing faster than the evidence base for years, and the loudest slogan of the last decade is: CBN is the sleep cannabinoid. It sells well. The problem is that the first study with polysomnography that tested this slogan was published only in 2026, and its main endpoint was a tie with placebo. CBD has better scientific press, just not the kind suggested by product descriptions. Below you will find what can be defended by data: the architecture of sleep, the role of the endocannabinoid system, numbers from studies, how to choose a product, and the moment when the oil stops being the answer.
KEY INFORMATION
• In the first study of CBN with polysomnography, neither 30 mg nor 300 mg shortened wakefulness at night (Lavender et al., Journal of Sleep Research, 2026).
• A typical sleep product contains 5-10 mg of CBN, which is a fraction of the dose at which anything moved.
• The work of Shannon et al. (2019) is a series of cases without a control group, and sleep improvement varied over time.
• The first treatment for chronic insomnia remains cognitive-behavioral therapy CBT-I.
Do cannabis products really help with falling asleep?
They help some people, and rather indirectly than directly. Cannabidiol reduces tension and anxiety that keep a person alert, making it easier to fall asleep. It does not act like a sleeping pill, does not turn off consciousness, and there is no evidence that it restores normal sleep architecture.
Separating these two things changes expectations. A sleeping pill forces sleep. Cannabis at most removes the obstacle that stood between you and sleep, so if your insomnia does not stem from anxiety, racing thoughts, or pain, you will probably feel nothing. This also explains the range of opinions: two people take the same oil, and one talks about a breakthrough, while the other about wasted money.
The division into primary and secondary insomnia is useful here. Primary insomnia has no external cause and persists on its own, driven by the fear of another sleepless night. Secondary insomnia accompanies something else: chronic pain, anxiety disorders, post-traumatic stress. Cannabidiol has a chance to work primarily in the latter situation, as there is indeed something to calm down.
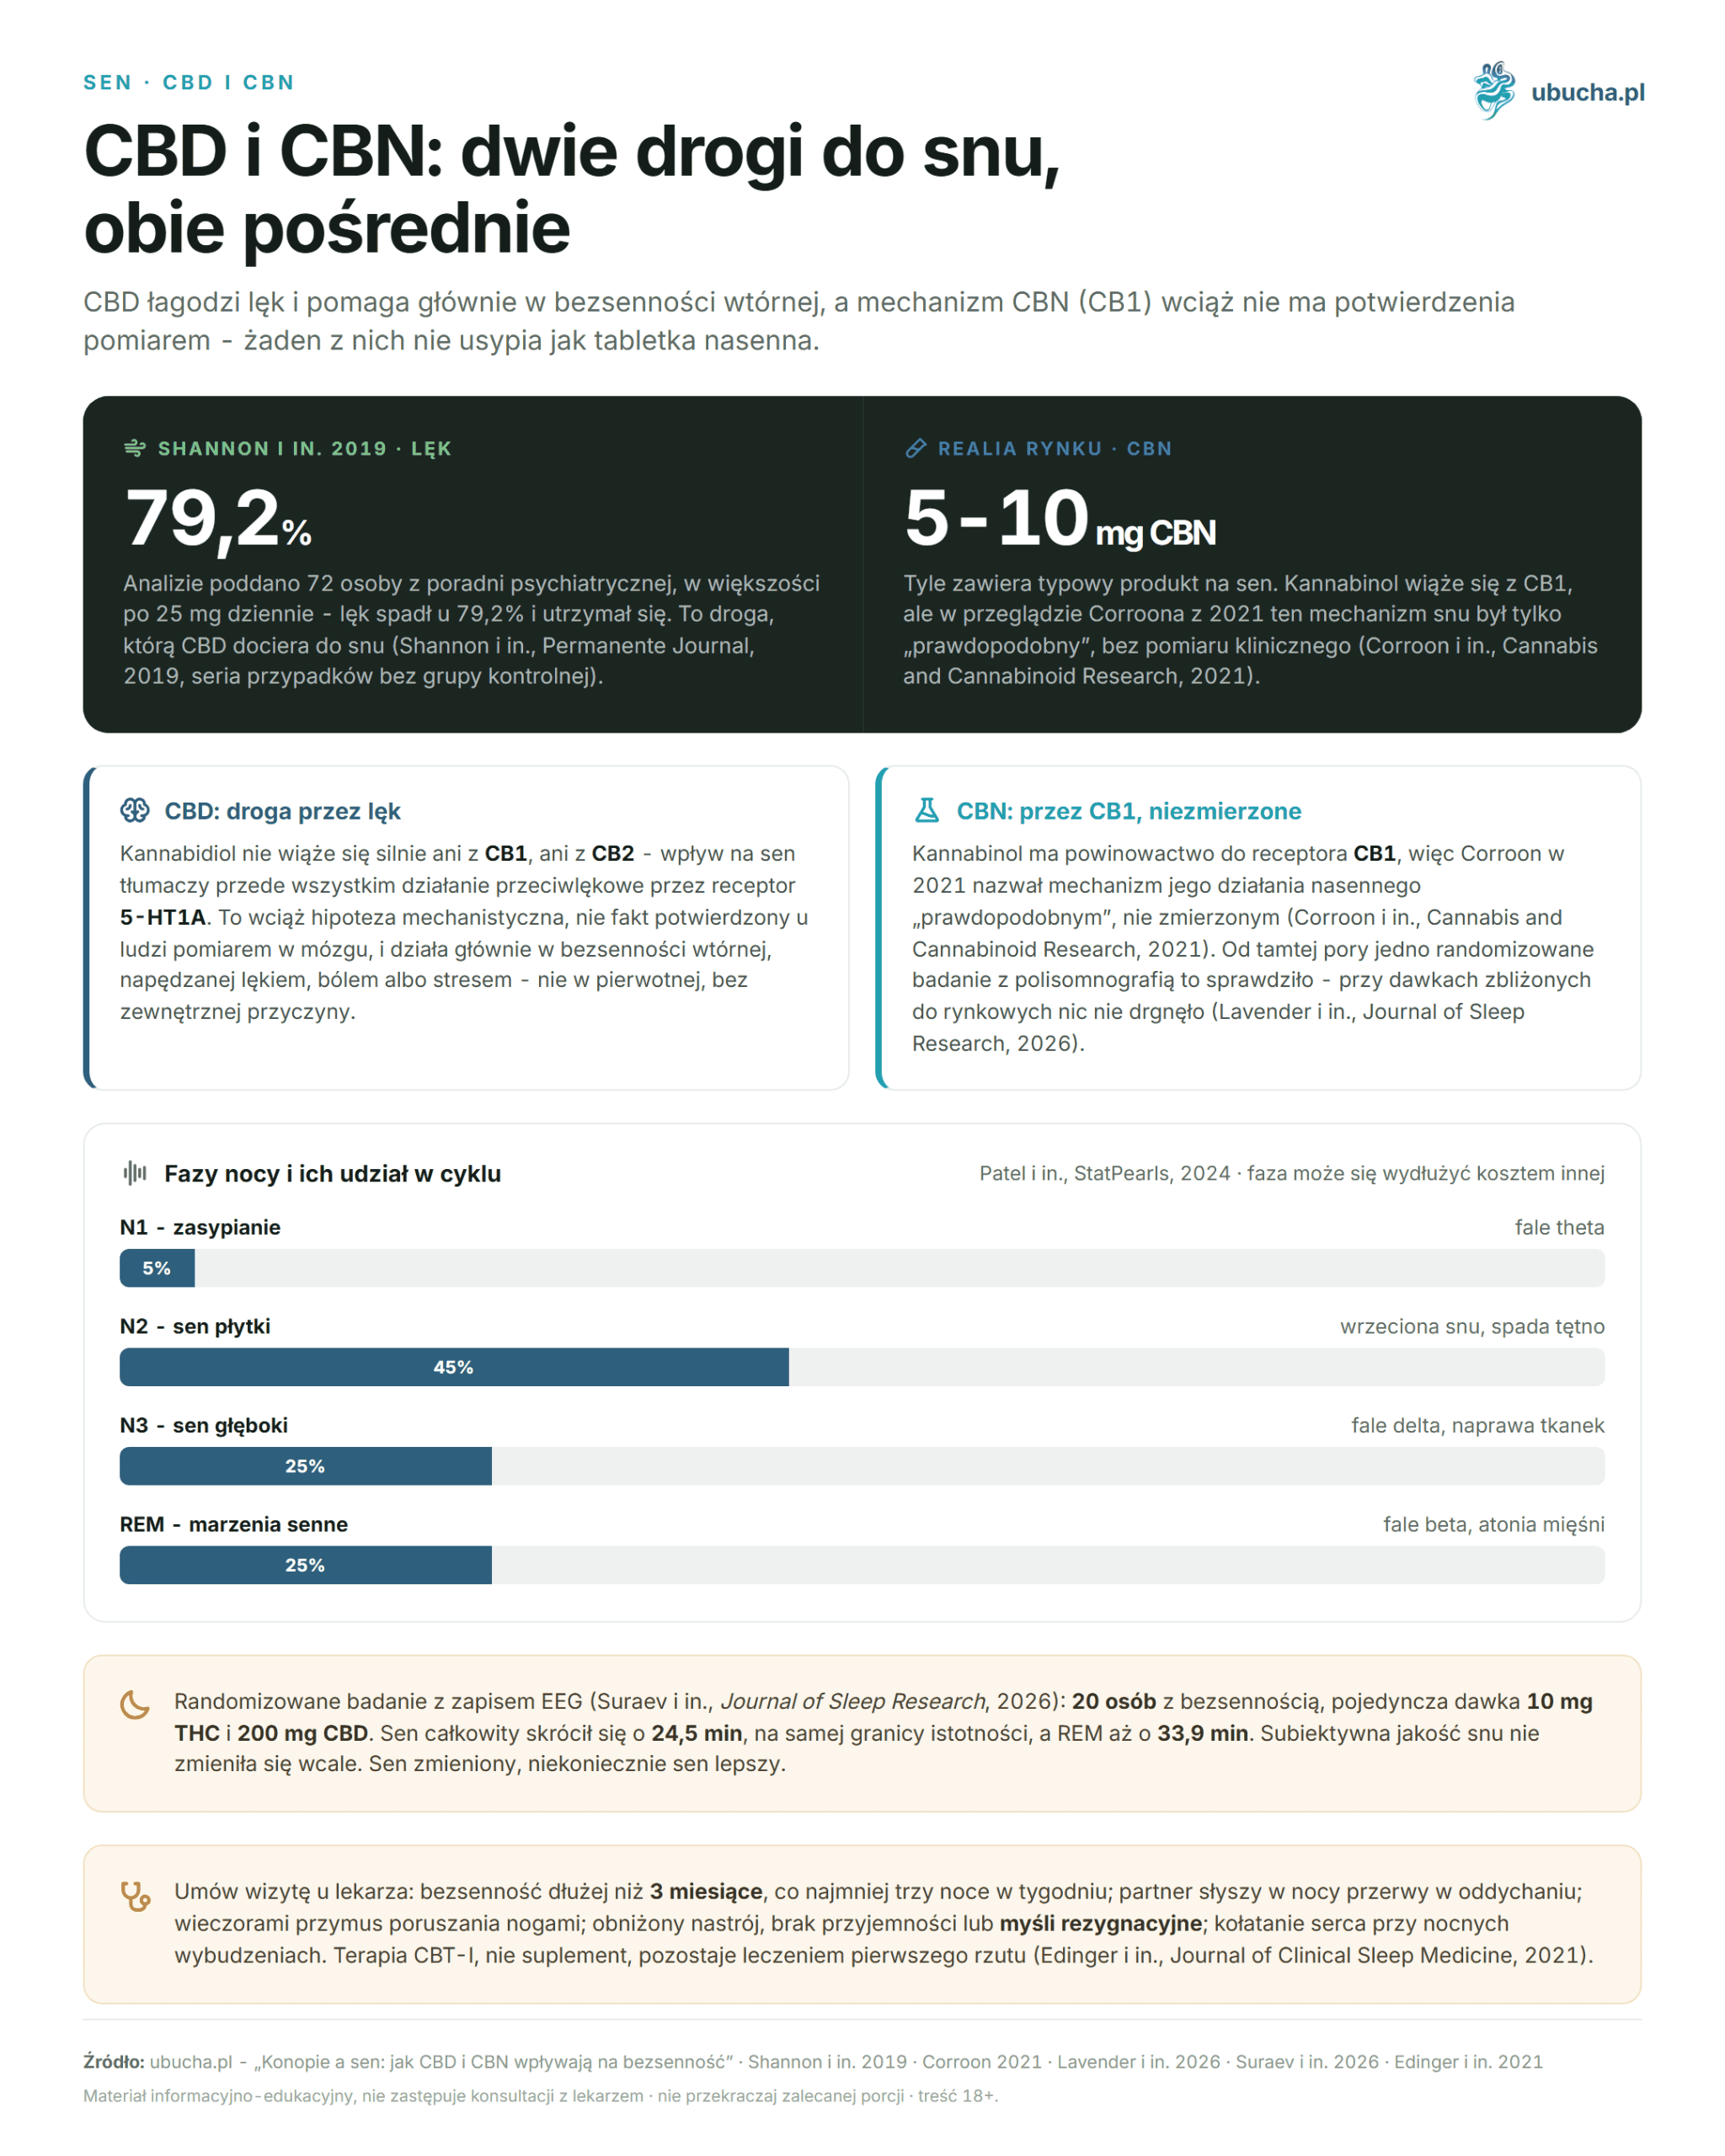
The situation with CBN is different because there is not even anything to defend. The Corroon review (Cannabis and Cannabinoid Research, 2021) searched the literature with one question: is there a clinical study linking cannabinol to sleep, based on polysomnography or at least on a validated questionnaire? The author reviewed 99 abstracts and found no such study. He noted that products sold for sleep usually contain 5 mg of CBN or less, and the available studies on humans date back to the 1970s and 1980s.
Our observation from the store: questions about CBN usually arise after encountering advertising, not after reading a study. Unlike with CBD, where people come with a specific problem, most often with evening tension. This is a good test of intentions: if a product sells you a molecule instead of a solution to a problem, it's worth asking what that promise is based on.
What does a night consist of and why does sleep architecture matter?
An adult's night consists of 4 to 5 cycles of about 90 to 110 minutes each, with phases N1, N2, N3, and REM occurring throughout. About 75% of sleep occurs in NREM phases (Patel et al., StatPearls, 2024). The feeling of being well-rested depends on their ratio, not just the number of hours.
Therefore, the question 'how much did I sleep' can be misleading. You can lie in bed for eight hours and wake up exhausted if the sleep was fragmented by awakenings or lacked deep phases. The opposite can also happen: six hours with preserved structure can restore better than eight hours of shallow sleep interrupted every few minutes.
The phases do not distribute evenly throughout the night. Deep sleep dominates in the first two cycles, while REM takes up more space in the morning. Someone who goes to bed at three and wakes up at seven loses not just one quarter of sleep but almost the entire REM phase. The same principle applies when the morning alarm is set two hours ahead.
| Phase | Participation in the night | Zapis EEG | What happens |
|---|---|---|---|
| N1 | about 5% | fale theta | transition from wakefulness, lasts 1-5 minutes |
| N2 | about 45% | wrzeciona snu, kompleksy K | heart rate and body temperature drop, memory consolidation occurs |
| N3 | about 25% | fale delta | tissue repair, muscle and bone rebuilding, immune system functioning |
| REM | about 25% | fale beta | dreaming, muscle atonia, processing emotions |
This table will be useful shortly when researching cannabinoids. The substance may prolong one phase at the expense of another and not necessarily improve the night, although the statistics will show a "change in sleep." The American Academy of Sleep Medicine, together with the Sleep Research Society, recommends that adults get at least 7 hours of sleep per night (Watson et al., Sleep, 2015), ale ta liczba ma sens dopiero razem z proporcjami z tabeli.
How does the endocannabinoid system regulate sleep and wakefulness?
It regulates it indirectly and less effectively than product descriptions suggest. The review by Babson et al. (Current Psychiatry Reports, 2017) cautiously summarizes studies on cannabis and sleep: cannabidiol has preliminary potential in insomnia, THC shortens the time to fall asleep, but with prolonged use, it can worsen sleep quality, and the overall results are inconsistent.
The system itself also has its own circadian rhythm, but it runs in a different direction than most guides repeat. The popular version says that anandamide increases in the evening and induces sleep. Measurements show something opposite. Vaughn et al. (British Journal of Pharmacology, 2010) measured the concentration of anandamide in the plasma of healthy volunteers and found that upon waking, it is three times higher than just before falling asleep. Sleep deprivation disrupts this rhythm. Anandamide thus appears to be more of a morning molecule than an evening one.
This does not mean that the endocannabinoid system has nothing to do with sleep. It only means that its relationship with the circadian rhythm is bidirectional and poorly studied in humans, and simple stories about a natural sleep hormone simplify it to the point of untruth.
Cannabidiol in this system does not behave like THC. It does not bind strongly to either CB1 or CB2, and its effect on sleep is mainly explained by its anxiolytic action through the serotonin receptor 5-HT1A. This is still a mechanistic hypothesis, not a fact confirmed by measurement in the brain.
Cannabinol behaves differently: it has an affinity for the CB1 receptor, so Corroon calls the mechanism of its sleep-inducing action probable. Probable, however, is not the same as measured, and Corroon himself recommends that future studies use doses much higher than those in products sold for sleep. If you want to trace the entire mechanics of this system, we have described it separately in introduction to the endocannabinoid system.
What do studies really show about CBD and sleep?
They show a signal, but weaker and less certain than advertising suggests. The most frequently cited work by Shannon et al. (Permanente Journal, 2019) is a retrospective case series from a psychiatric clinic, without randomization and without a control group. The authors themselves write that the improvement in sleep varied over time.
It is worth understanding what this means in practice. A doctor reviewed the records of 103 patients, and 72 individuals who received cannabidiol alongside their existing treatment were included in the analysis, predominantly at 25 mg per day. Anxiety scores decreased in 79.2% and remained so, sleep scores improved in 66.7% in the first month, but then fluctuated. No one compared these individuals with a placebo group, there was no blinding, and a patient who comes for help and receives it usually feels better in the following month regardless of the preparation. Such a setup does not distinguish the action of the substance from the natural course of the problem.
| Study | Kto i ile | Method | Outcome |
|---|---|---|---|
| Carlini and Cunha, 1981 | 15 people with insomnia, 40, 80, and 160 mg | comparison with placebo and 5 mg of nitrazepam | longer sleep only after 160 mg, fewer dream memories after each dose |
| Shannon et al., 2019 | 72 patients in the clinic, mostly 25 mg per day | case series, without a control group | improvement in 66.7% in the first month, then the result fluctuated |
| Babson i in., 2017 | literature review | synteza narracyjna | preliminary signal for CBD, overall results are inconsistent |
| Suraev i in., 2026 | 20 people with insomnia, 10 mg THC and 200 mg CBD | randomizacja, polisomnografia z EEG | sleep shorter by 24.5 min, REM shorter by 33.9 min |
Carlini and Cunha (Journal of Clinical Pharmacology, 1981) compared three doses of cannabidiol with placebo and nitrazepam in 15 people with insomnia. Only those taking 160 mg slept longer. The last line is the most interesting and least convenient. In a pilot randomized study (Suraev et al., Journal of Sleep Research, 2026) a single dose of THC with cannabidiol shortened total sleep by 24.5 minutes, right on the edge of significance, clearly suppressed REM phase, and extended the time to its onset by over an hour. The subjective quality of sleep did not change at all. This is altered sleep, not necessarily better sleep.
Where did the myth of CBN as the sleep cannabinoid come from?
From one old paper read on the packaging and from an anecdote about old cannabis. Cannabinol is formed when THC oxidizes under the influence of light, heat, and oxygen, so aging flowers have more of it. Smokers said that such material induces sleep, and attributed it to the new molecule.
A study that has served as evidence for half a century says otherwise. Karniol et al. (Pharmacology, 1975) administered placebo, 50 mg CBN, 25 mg THC, and a mixture of both substances to five volunteers. After THC alone, the participants described themselves as dazed and drowsy. After CBN alone, at a dose ten times higher than in today's gummies, they reported no such effect at all. Drowsiness only intensified when combined with THC, meaning there was something to intensify.
Marketing took this statement about enhancement, cut off the condition, and turned CBN into a sleep aid. Corroon describes this mechanism directly and advises consumers to be skeptical of manufacturers' claims.
This was compounded by a common chemical misunderstanding. Cured cannabis does not change solely into CBN. It loses volatile terpenes and transforms some acidic forms of cannabinoids, so its action profile differs from fresh material on several levels at once. Attributing the entire difference to a single measurable molecule was a convenient shortcut, not a conclusion from the experiment.
A more sensible candidate for the cause of drowsiness from old cannabis is terpenes. Russo (British Journal of Pharmacology, 2011) described the entourage effect, where the terpene profile modifies the action of cannabinoids, and myrcene and linalool have long been considered calming components. However, the evidence remains preclinical: Chen et al. (Pharmaceuticals, 2024) demonstrated the sedative effect of beta-myrcene from lavender oil in mice, not in humans. What this chemistry does in practice, we elaborated on in the text about it, what are cannabis terpenes.
Did CBN perform better than placebo in the polysomnography study?
At the most important endpoint, no. The CUPID study (Lavender et al., Journal of Sleep Research, 2026) involved 20 adults diagnosed with insomnia and compared one dose of 30 mg CBN, one dose of 300 mg CBN, and placebo in a crossover design, with a full polysomnographic recording.
The primary endpoint was wakefulness after sleep onset, which is the sum of minutes spent awake in the middle of the night. CBN did not change it. A few additional indicators shifted at the highest dose, and this is precisely the part that manufacturers are already starting to quote out of context.
| Endpoint | Wynik wobec placebo |
|---|---|
| Wakefulness after sleep onset (primary endpoint) | no difference: 300 mg minus 6.3 min (p = 0.29), 30 mg minus 4.0 min (p = 0.50) |
| Czas zasypiania | shorter, but only after 300 mg (p = 0.004) |
| Faza N2 | longer, only after 300 mg (p = 0.03) |
| Subjective sleep quality | better, only after 300 mg (p = 0.005) |
| Awakening index in EEG | lower, only after 300 mg (p = 0.02) |
| Adverse events | 247 mild and moderate across all arms |
A set of these numbers with the label of any sleep gummy. The dose at which anything moved was 300 mg. Products declare 5 or 10 mg, which is thirty to sixty times less, and the 30 mg dose, closest to market realities, did not move anything. Moreover, it was one overnight stay, twenty people, and a study whose authors themselves write about the need for larger and longer trials.
An honest conclusion, therefore, sounds ambiguous and must be left as such. CBN is not a molecule without action, as something did happen in the EEG recording at a dose tens of times higher than the market dose. It is also not a sleep aid in the sense in which it is sold by labels, as the most important measurement came out to zero, and at real doses, nothing came out. Until multi-week studies appear, that’s all that can be said.
In what form and at what time should CBD be taken for sleep?
The form and timing can be described by data, but the amount cannot. There is no dose confirmed by research for insomnia, and the review by Larsen and Shahin (Journal of Clinical Medicine Research, 2020) gathered 25 studies involving 927 adults and found that the form, dose, and administration schedule varied among them enough that they do not combine into a single threshold of effectiveness. Ask your doctor how much to take, not an article.
However, there is an upper limit worth knowing. The EFSA panel calculated a provisional safe dose of cannabidiol in 2026 at 0.0275 mg per kilogram of body weight per day, which is about 2 mg daily for a person weighing 70 kg (EFSA, 2026). It was derived using the benchmark dose method with an uncertainty factor of 400 and applies only to supplements with a cannabidiol purity of at least 98%, without nanoparticles. The same document states explicitly that the safety of cannabidiol cannot be established in individuals under 25 years of age, in pregnant and breastfeeding women, and in individuals taking medications.
The biggest mistake in evaluating a product is testing it on a whim. Those who reach for oil solely after a bad night assess it at the worst possible moment and usually deem it ineffective. A consistent time and a full two to three weeks of observation give this product a chance that a single dose never will. The form, in turn, determines when the substance will start to work and how long it will remain in the body.
| Form | Onset of action | When to take it |
|---|---|---|
| Sublingual oil | 15 do 45 minut | 30 do 60 minut przed snem |
| Capsules and jellies | 60 do 120 minut | 1,5 do 2 godzin przed snem |
| Vaporization | 5 do 10 minut | works briefly, rarely effective in the evening |
The systematic pharmacokinetic review by Millar et al. (Frontiers in Pharmacology, 2018) indicates the time to maximum concentration from 0 to 4 hours and notes that a meal and a fat carrier raise this peak. Absolute oral bioavailability in humans has never been measured directly. The practical conclusion is straightforward: take the product with fat and always at the same time.
What else helps with sleep: melatonin, magnesium, or L-theanine?
Each of them has evidence, though more modest than the packaging suggests. Melatonin shortens the time to fall asleep by an average of 7 minutes and extends sleep by 8 minutes in a meta-analysis of 19 studies involving 1683 participants (Ferracioli-Oda et al., PLOS ONE, 2013). It is a chronobiological tool, not a sleeping aid.
The scale of this effect can be surprising. Seven minutes of faster sleep onset is a real statistical change and something that most people will not notice at all. Melatonin works best where the problem is a shifted clock, such as with time zone changes and shift work, rather than classic insomnia.
| Agent | What the data showed | Quality of evidence |
|---|---|---|
| Melatonin | falling asleep 7 minutes faster, sleep lasting 8 minutes longer | meta-analysis of 19 randomized studies |
| Magnez doustnie | falling asleep 17.4 minutes faster in seniors | 3 small studies, GRADE assessment low and very low |
| L-teanina 200 mg | better PSQI results for sleep onset and sleep disturbances after 4 weeks | one crossover study, 30 participants |
| Terpeny lawendy | reduction in sleep latency in the insomnia model | only animal studies |
Two things from this table are worth remembering. First, magnesium has a seemingly stronger result than melatonin, but it is based on three small trials with a moderate to high risk of systematic error, so the authors of the review (Mah and Pitre, BMC Complementary Medicine and Therapies, 2021) themselves describe the quality of the literature as insufficient. Second, L-theanine improved sleep only after four weeks of daily use (Hidese et al., Nutrients, 2019), not after the first capsule. Evening herbs, such as lemon balm and hops, work on a similar logic of a repeatable ritual. You will find them in the category teas and infusions.
Why does CBT-I outperform supplements and when should you see a doctor?
Because it addresses the cause, not the symptom, and as the only method has first-line treatment status. The guidelines from the American Academy of Sleep Medicine (Edinger et al., Journal of Clinical Sleep Medicine, 2021) recommend multi-component cognitive-behavioral therapy for insomnia in adults with a strong recommendation strength.
CBT-I typically involves 5 to 8 sessions, during which you learn stimulus control, time restriction in bed, relaxation techniques, and verification of sleep beliefs. It sounds less appealing than a drop of oil and requires a few uncomfortable weeks, but it is the only intervention with a lasting effect after treatment ends. A supplement works only as long as you take it.
Sleep hygiene is a prerequisite, not a therapy in itself, and the same guidelines advise against using it as the only component of treatment. Maintain a consistent wake-up time even on weekends, darken the bedroom to zero, lower the temperature to around 18°C, eliminate caffeine in the afternoon, and reserve the bed solely for sleep and sex. Alcohol is the biggest deceiver here: it speeds up falling asleep and disrupts the second half of the night.
However, there are situations where further experimentation with supplements delays diagnosis. Schedule an appointment if any of the following signals appear:
- insomnia lasts longer than 3 months and occurs at least three nights a week;
- your partner hears pauses in your breathing at night, and you wake up with a headache and daytime drowsiness;
- in the evenings, you feel an urge to move your legs, which only goes away after getting up;
- insomnia is accompanied by a low mood, lack of pleasure, or feelings of resignation;
- night awakenings are accompanied by heart palpitations and weight loss.
The prevalence of insomnia as a disorder among adults ranges from 10 to 16% (Spiegelhalder et al., Nature Reviews Disease Primers, 2026), so it is not a rarity that requires shame before a doctor. We have described more over-the-counter methods in the text about natural ways to sleep without pills.
Are CBD and CBN legal in Poland?
Hemp is legal, and the boundary is defined by the THC content in the plant. The law defines it as Cannabis sativa L., in which the sum of delta-9-THC and tetrahydrocannabinolic acid in flowering or fruiting tops, from which the resin has not been removed, does not exceed 0.3% when calculated on a dry weight basis, rounded to one decimal place.
This distinction has practical significance because the laboratory counts the sum of two compounds, not just delta-9-THC, and the result of the test depends on this. The basis is Article 4 point 5 of the Act of July 29, 2005 on counteracting drug addiction (t.j. Dz.U. 2023 poz. 1939), as amended by the Act of March 24, 2022 (Dz.U. 2022 poz. 763), effective from May 7, 2022. Previously, the national threshold was 0.2%. It corresponds to the EU threshold, but it does not imply that: these are two separate regulations with the same numerical value.
Cannabinol is not named in the regulation of the Minister of Health on the lists of controlled substances (t.j. Dz.U. 2024 poz. 1139); cannabidiol is also not mentioned there. The legality of a specific product is therefore determined by the THC content in the raw material from which it was made, not by the cannabinoid name on the label. THC itself remains available only by prescription Rpw, as a pharmaceutical raw material; this was enabled by the amendment of July 7, 2017 (Dz.U. 2017 poz. 1458), effective from November 1, 2017. Possession without a prescription is punishable, which must be remembered when purchasing from foreign mail-order stores. We expanded on this topic in the article about medical marijuana and insomnia.
How to check what is really in the bottle?
Legality says nothing about content. In an analysis of 84 extracts purchased online, only 30.95% had a label consistent with the actual cannabidiol content, 42.85% contained more than declared, and THC was detected in 21.4% of samples (Bonn-Miller et al., JAMA, 2017). Therefore, before purchasing, check four things: the current laboratory test report with a cannabinoid profile and tests for heavy metals and pesticides, the declared THC content below the threshold, the extraction method using carbon dioxide or ethanol, and finally, dark glass with a readable expiration date.
A certificate in itself guarantees nothing if you don't read it. Check the date, as reports from two years ago describe a different batch of raw material, and the name of the laboratory, as tests conducted in the manufacturer's own facility carry different weight than external analysis. The batch number on the report should match the number on the packaging you hold.
A separate matter is medications. Cannabidiol inhibits the enzymes CYP3A4, CYP2C9, and CYP2C19, through which most prescription drugs are metabolized, and a systematic review by Nachnani et al. (Frontiers in Pharmacology, 2024) gathered 31 documented cases of altered pharmacokinetics. Exercise the greatest caution with warfarin, clobazam, valproate, Z-drugs, and statins.
Frequently Asked Questions
Does CBD make you sleepy like a sleeping pill?
No. Cannabidiol does not turn off consciousness; it only reduces tension and anxiety that make it difficult to fall asleep. In a series of cases by Shannon et al. (Permanente Journal, 2019), sleep outcomes improved in 66.7% of patients in the first month, but varied from month to month, and the study did not have a control group.
Is CBN really a sleep cannabinoid?
The data does not support this. The Corroona review (2021) found no clinical studies on CBN with polysomnography. The first such study, CUPID (Lavender et al., 2026), did not show a reduction in wakefulness at night, neither after 30 mg nor after 300 mg of CBN. The slogan comes from marketing, not from research.
Jaka proporcja CBD do CBN na sen ma sens?
No ratio has been confirmed by research. The market ratios of 3:1 or 1:1 are product decisions, not test results. The only CBN dose with a signal in polysomnography is 300 mg, which is 30 to 60 times more than in a typical gummy. Ratios currently lack data support.
How long before sleep should I take CBD?
Sublingual oil 30 to 60 minutes before sleep, capsules and gummies 1.5 to 2 hours earlier. The pharmacokinetic review by Millar et al. (Frontiers in Pharmacology, 2018) states that the time to maximum concentration ranges from 0 to 4 hours, and fat in the meal raises this peak. Assess the effect after 2 to 3 weeks.
Can I combine CBD with melatonin and magnesium?
Decide on each such combination with your doctor if you are taking anything by prescription. Melatonin resets the biological clock, magnesium and L-theanine calm, and cannabidiol reduces anxiety. Special caution applies to sleep and anxiolytic medications, as CBD inhibits the enzymes CYP3A4, CYP2C9, and CYP2C19 (Nachnani et al., 2024).
Does CBD cause addiction?
The critical review by WHO ECDD from 2018 found no psychoactive properties or potential for abuse and dependence in cannabidiol, and the committee recommended that pure CBD not be subject to international control. However, the dose is not neutral: EFSA in 2026 stated that the safety of CBD cannot be established for individuals taking medications.
Can CBN cause a positive drug test result?
Cannabinol itself usually does not, as screening tests detect THC metabolites. The risk arises from the product background: in a JAMA analysis (Bonn-Miller et al., 2017), THC was detected in 21.4% of 84 tested extracts. Professional drivers should choose isolate or broad-spectrum with laboratory testing.
Can I give CBD to a child with insomnia?
Not without a doctor's decision. In children, cannabidiol is used as a registered medication only for drug-resistant epilepsy types Dravet and Lennox-Gastaut. EFSA states explicitly that the safety of cannabidiol cannot be established below 25 years of age, and insomnia in a child requires pediatric diagnostics.
If after reading you want to try an evening routine, discuss it with your doctor, and then start with one product at a time and give it two weeks. In the store, you will find hemp oils, jelly candy and dried hemp for vaporization and infusions.
This article is for informational and educational purposes only and does not constitute medical advice. Before starting to use hemp or CBD for therapeutic purposes, consult your doctor, especially if you are taking other medications, are pregnant, or breastfeeding.
Author: Michał Waluk · Opublikowano: 2026-05-11 · Aktualizacja: 2026-08-11