
CBD for stress online and digital overstimulation 2026
Screen overstimulation, stress axis, and cannabidiol: we check what the source works confirm, what is a myth, and why we do not provide a dosage in milligrams.
A notification at seven in the morning, three messaging apps by noon, and in the evening another message that could have waited until tomorrow. An increasing number of people working at screens are looking for a way to step back from this cycle through cannabidiol. This text examines how justified this is. We have gone through all the citations from the previous version of the article and removed every number that is not confirmed by the source work, and one assertion turned out to be reversed: the work commonly cited as evidence for lowering cortisol shows something exactly opposite. Below you will find what remains after this verification, along with an explanation of why there is no dosing table or a day-by-day implementation plan here. There are fewer numbers than the first version promised, but each comes from a work that can be opened and read in full.
KEY INFORMATION
- In the 1993 study, cannabidiol did not lower cortisol, but weakened its natural morning drop, meaning the concentration remained higher than after placebo (Brazilian Journal of Medical and Biological Research, 1993).
- In the randomized study involving 57 healthy men, anxiety during performance was reduced only by a dose of 300 mg; 150 mg and 600 mg did not differ from placebo (Brazilian Journal of Psychiatry, 2019).
- The most frequently cited clinical series included 72 adults, and anxiety results decreased in 79.2% of them in the first month. Its abstract does not provide any dosage (The Permanente Journal, 2019).
- The provisional safe dose set by the regulator is 0.0275 mg per kilogram of body weight per day, which is about 2 mg for a person weighing 70 kg (EFSA Journal, 2026).
- The safety of cannabidiol cannot be established in individuals under 25 years of age, in pregnant and breastfeeding women, and in those taking medications.
What is digital overstimulation?
This is a common term for a state in which the nervous system receives more stimuli than it can process, with the sources of these stimuli being screens and notifications. It is not a disease or medical diagnosis, but a description of everyday experience.
It is worth stating right away what you will not find in this text. The previous version of this article provided several striking statistics: how many adults experience physical symptoms of technological stress, how many notifications a remote worker receives daily, what percentage meets the criteria for adjustment disorder. None of these numbers could be confirmed in the document to which the citation led, and some references pointed to the home pages of journals instead of specific works. We removed them all.
What remains is a description that everyone will recognize without statistics: tense shoulders, scattered attention, difficulty falling asleep despite fatigue, irritability after working hours, a feeling that the mind is still working on a task even though the laptop is closed. This is a sufficient reason to seek something. The question is whether that something could be cannabidiol, and this question can be answered much more cautiously than most product descriptions do. So we will start with physiology, which can be described without any marketing, and only then will we check where in this physiology cannabidiol actually appears.
What does chronic stress do to the body?
It activates the hypothalamic-pituitary-adrenal axis, briefly the HPA axis, and with prolonged action, it does not allow it to return to its baseline state. The textbook description of the stress response physiology leads this pathway step by step (StatPearls, aktualizacja 2024).
The hypothalamus releases corticotropin-releasing hormone, abbreviated as CRH, which acts on two receptors: CRH-R1 and CRH-R2. The signal reaches the pituitary gland, which releases adrenocorticotropic hormone, and this hormone stimulates the adrenal cortex to secrete cortisol. Cortisol then does exactly what it is meant to do: it releases catecholamines, inhibits insulin, and makes energy reserves available. For half an hour, this is a beneficial response.
The problem is the duration of exposure, not the response itself. The same description indicates that exposure to chronic stressors leads to maladaptive responses, among which it lists depression, anxiety, cognitive impairment, and heart disease. Hence the sensibility of asking about pharmacological support, but also its limit: an intervention that does not reduce the number of stimuli acts on the effect, not the cause. Separately, we have gathered a review of supplements taken for stress and cortisol, where we posed the same question regarding other ingredients. Before we move on, it is worth remembering one distinction. Cortisol is not a harmful hormone that needs to be eliminated, but a hormone with a clear daily rhythm, which is high in the morning and should drop in the evening. The problem is flattening this rhythm, not the mere presence of the hormone, and this difference will prove significant when assessing the only study that measured this hormone after cannabidiol.
Is digital stress different from any other?
Physiologically, no. The stress axis does not recognize whether the signal came from a communicator or from a car breakdown, and it triggers the same cascade of corticoliberin, corticotropin, and cortisol (StatPearls, aktualizacja 2024).
The difference lies elsewhere, in the frequency and in the fact that the signal comes when there is no way to respond with action. The textbook description emphasizes that the stress response is adaptive when it is short and harmful when it becomes chronic. A notification at twenty-two mobilizes the body for effort that has nowhere to be discharged, and it does this several times a day.
However, it must be said honestly that we did not find a study that measured cortisol separately in individuals exposed to screen overload and compared them with a control group. The circulating interests on this topic in industry materials led to the main pages of journals rather than to specific studies. Therefore, conclusions about digital stress today rely on the general physiology of chronic stress, not on separate evidence. This difference is significant when someone sells a product described as intended specifically for overstimulation from screens.
Does cannabidiol lower cortisol?
No, and the study most often cited to justify this shows the opposite. It is the work of Zuardi and colleagues from 1993, and it is worth describing it in detail because its results are often misrepresented in industry summaries.
Eleven healthy volunteers received either a placebo or cannabidiol orally in a dose of 300 mg for seven individuals or 600 mg for four. Sessions took place in the morning, and blood was drawn from 35 minutes before administration to 180 minutes after. Prolactin and growth hormone levels did not change after either placebo or the preparation (Brazilian Journal of Medical and Biological Research, 1993).
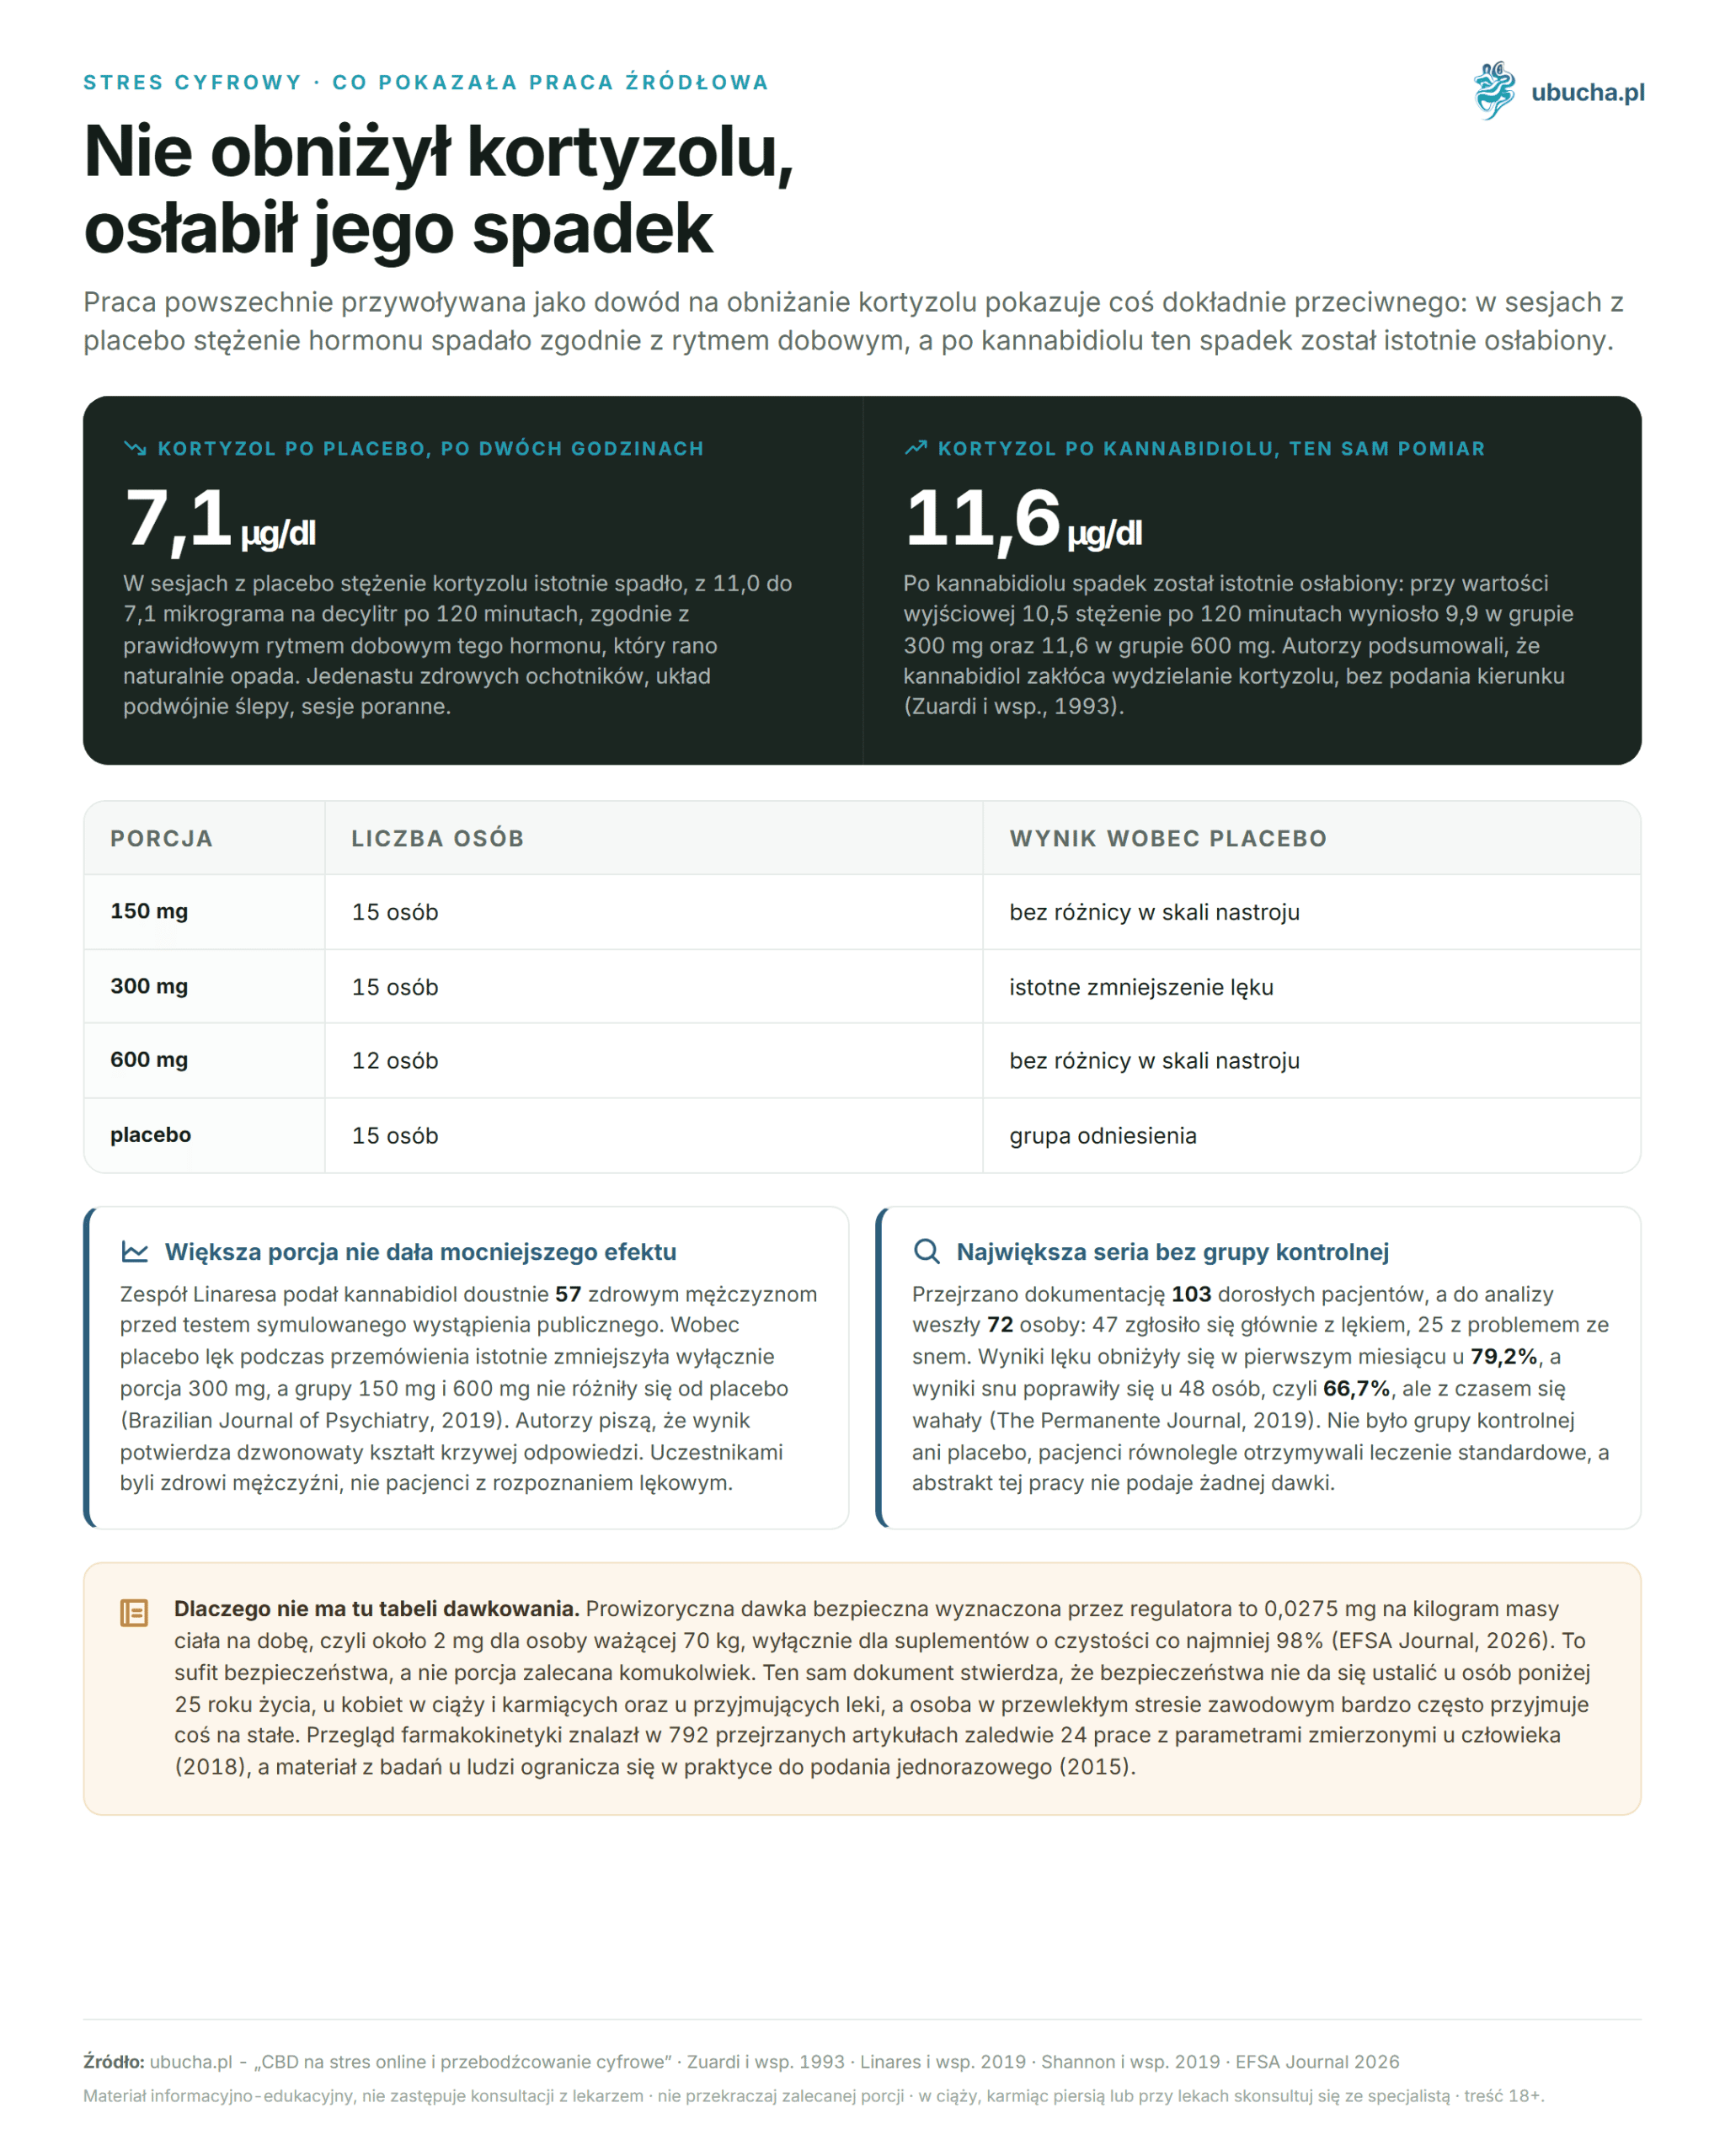
Cortisol behaved differently. In sessions with placebo, its concentration significantly decreased from 11.0 to 7.1 micrograms per deciliter after 120 minutes, in accordance with the normal daily rhythm of this hormone, which naturally declines in the morning. After cannabidiol, this decline was significantly weakened: with a baseline value of 10.5, the concentration after 120 minutes was 9.9 in the 300 mg group and 11.6 in the 600 mg group. The authors concluded that cannabidiol disrupts cortisol secretion and noted a sedative effect in self-assessment scales. Therefore, the statement about lowering cortisol, repeated in product descriptions, is a complete reversal of the results of this study.
Where this reversal comes from can only be speculated. The authors' conclusion speaks of disruption in hormone secretion without specifying the direction, and such a statement is close to adding a more commercially convenient direction. It is also worth noting what this study did not measure. There was neither a stressor nor individuals in chronic tension, nor administration longer than a single dose. Eleven volunteers, morning session, three hours of observation. Inferring from this about the evening cortisol of a person tired from a day in front of a screen goes far beyond the scope of the study.
How does cannabidiol affect anxiety?
Through several pathways, the best described being the serotonin receptor 5-HT1A. A review of mechanisms from 2012 indicates that the acute anxiolytic effect and the antidepressant-like effect primarily rely on facilitating transmission through this receptor.
This occurs in brain areas responsible for defensive reactions: in the dorsal periaqueductal gray, in the bed nucleus of the stria terminalis, and in the medial prefrontal cortex. Other effects may depend on the enhancement of anandamide transmission, and the activation of TRPV1 channels helps explain the bell-shaped curve of the response observed with this relationship (Philosophical Transactions of the Royal Society B, 2012).
The authors of the review emphasize a point that gets lost in simplifications: the mechanism is not one but depends on which response is being measured. They also list a long list of pathways whose involvement has not yet been studied, from the inhibition of adenosine reuptake to action on PPAR-gamma receptors. The practical consequence is that a product description reducing the entire action to one receptor simplifies the picture to the point of falsehood. For the reader, what matters more is that the described effects pertain to defensive reactions, meaning what happens after a stimulus, not the number of stimuli.
Has this been confirmed in studies with humans?
Yes, though in a narrow scope and with a single dose. The most frequently cited study is by Bergamaschi and colleagues from 2011, conducted on patients with generalized social anxiety who had never been treated for it before.
Twenty-four patients were randomly assigned to two groups: twelve received 600 mg of cannabidiol, and twelve received placebo, one and a half hours before a simulated public speaking test. Separately, twelve healthy volunteers underwent the same test without any preparation. The visual analog scale of mood, scale of negative self-statements, and measures of blood pressure, heart rate, and skin conductance were assessed (Neuropsychopharmacology, 2011).
Compared to placebo, the preparation significantly reduced anxiety, cognitive function impairment, and discomfort during the speech. The intensity of negative thoughts about oneself, which increased in the placebo group during the test, almost disappeared in the active group, and in most measured dimensions, the active group did not differ from healthy volunteers. However, it should be added what is not included in this work: no brain imaging studies were conducted, although statements about changes in neuroimaging are sometimes attached to it. We removed them along with the entire paragraph that relied on it.
Does a larger dose provide a stronger effect?
No, and this is one of the better-documented surprises on this topic. The Linares team administered cannabidiol orally to 57 healthy men before a simulated public speaking test in a double-blind setup in 2019.
Participants were assigned to four groups: 150 mg for 15 individuals, 300 mg for 15 individuals, 600 mg for 12 individuals, and placebo for 15 individuals. Compared to placebo, anxiety during the speech was significantly reduced only by the 300 mg dose. The 150 mg and 600 mg groups did not differ from placebo in mood scale (Brazilian Journal of Psychiatry, 2019). The authors write that the result confirms the bell-shaped curve of the response known from animal studies and call for rigorous determination of optimal doses.
Two things in this description require careful attention, as they circulate in a distorted form. First, the study did not include a 900 mg dose, although such a number is sometimes attributed to it. Second, the participants were healthy men, not patients with an anxiety diagnosis. The conclusion for someone seeking help with occupational stress remains the same: since the response does not increase with the amount, adding more drops after an unsuccessful attempt is not a strategy supported by this study.
What did the largest clinical series show?
Improvement in anxiety in four out of five patients, but in a setup that does not allow for cause and effect conclusions. This refers to the retrospective case series by Shannon and colleagues from 2019, conducted in a psychiatric outpatient clinic.
Monthly documentation of 103 adult patients was reviewed, and 72 individuals were included in the analysis: 47 presented mainly with anxiety, 25 with sleep problems. Anxiety scores decreased in the first month for 57 individuals, or 79.2%, and remained reduced throughout the observation period. Sleep scores improved for 48 individuals, or 66.7%, but fluctuated over time. The preparation was well tolerated by all patients except for three (The Permanente Journal, 2019).
The limitations are significant, and the authors themselves list them. There was no control or placebo group, patients were concurrently receiving standard treatment, and the work ends with a call for controlled studies. Separately, it is worth noting something that lives a life of its own on the internet: the abstract of this work does not provide any dosage. The milligram range attributed to it in hundreds of guides does not come from its summary, and we do not have access to the full text, so we do not repeat it.
Why don't we provide the dosage in milligrams?
Because there is no number that could be honestly provided to a person we do not know. Providing a dose would be a recommendation, and a recommendation requires safety data, which simply does not exist for the internet reader.
The European regulator updated its position on cannabidiol as a novel food in 2026. Using the benchmark dose method, with an uncertainty factor of 400, a provisional safe dose of 0.0275 mg per kilogram of body weight per day was derived, which is about 2 mg per day for a person weighing 70 kg. This number pertains only to supplements with a purity of cannabidiol of at least 98%, without nanoparticles (EFSA Journal, 2026). This is a safety ceiling, not a recommended dose for anyone.
This same document states explicitly that the safety of cannabidiol cannot be established in individuals under 25 years of age, in pregnant and breastfeeding women, and in individuals taking medications. Note who the last category describes. A person in chronic occupational stress often takes something regularly: an antidepressant, a blood pressure pill, a thyroid preparation. Precisely for them, the regulator cannot determine a safe amount, and this is the reason why instead of a dosage table, there is a referral to a doctor or pharmacist.
What is the endocannabinoid system?
It is an internal regulatory system encompassing cannabinoid receptors, their natural lipid ligands, and the enzymes that break down these ligands. A comprehensive review describes it as a target for pharmacotherapy in an increasing number of disease states (Pharmacological Reviews, 2006).
The list of these conditions is long and includes mood and anxiety disorders, Parkinson's disease and Huntington's disease, neuropathic pain, multiple sclerosis, hypertension, glaucoma, and metabolic syndrome. The authors note that the psychoactive properties of substances stimulating the CB1 receptor have been an obstacle to the development of cannabinoid drugs, but this problem may be circumvented by an indirect approach that involves blocking the breakdown or transport of endocannabinoids.
The conclusion drawn from the topic of this article is less promising than the typical marketing formula about restoring balance. The endocannabinoid system is a promising target for medications, not a system that can be recharged with a bottle of supplements. The review discusses compounds that modulate this system in preclinical studies and clinical trials, not the everyday use of edibles by healthy individuals. It's important to keep this distinction in mind when reading product descriptions. The review is from 2006, and its authors predicted that the increasing number of preclinical studies and clinical trials would lead to new treatment methods. Twenty years later, most of these predictions are still waiting to be fulfilled.
How long does it take to assess the effect?
Certainly not sooner than a week, and there is simply a lack of reliable answers to this question. A systematic review of pharmacokinetics in humans found only 24 articles with parameters measured in humans among 792 reviewed articles (Frontiers in Pharmacology, 2018).
These studies indicate that the maximum concentration appears between zero and four hours after administration, faster after inhalation than orally, and increases after meals and in fat-based preparations. The half-life after chronic oral administration ranges from two to five days, meaning that a substance taken daily accumulates before reaching a steady state. The authors conclude with a note about the lack of data and discrepancies between studies.
The second limitation is even more serious. The review of evidence in anxiety disorders states that the material from studies in humans is practically limited to single doses, and few trials have been conducted with chronic administration (Neurotherapeutics, 2015). In other words: we know something about how cannabidiol works for a single public speaking event, but very little about what it does after six weeks of daily use. Any implementation plan laid out over weeks exceeds what has been studied today.
What are the side effects and interactions?
The most commonly reported are fatigue, diarrhea, and changes in appetite and body weight. A safety review lists these, covering clinical trials mostly conducted in epilepsy and psychotic disorders, where the doses used are much higher than in supplements (Cannabis and Cannabinoid Research, 2017).
However, the section on interactions is more serious. A review of the pharmacokinetics and pharmacodynamics of cannabinoids indicates that they are metabolized in the liver, so inhibition or stimulation of enzymes and transport proteins is possible, which alters the concentrations of other medications. An example described is the inhibition of clobazam metabolism. Co-administration with substances that inhibit the central nervous system compounds their effects, and combining with sympathomimetic drugs carries cardiovascular risks (British Journal of Clinical Pharmacology, 2018).
Additionally, there are signals gathered by the regulator. Animal studies have shown consistent liver toxicity, and data from human studies indicate potential hepatotoxicity, especially with the concurrent use of other medications. Gastrointestinal symptoms have been reported with larger doses, and data on neurological and psychiatric safety have been deemed insufficient for assessment (EFSA Journal, 2026). If you are taking anything regularly, discussing it with a doctor or pharmacist is a requirement, not a polite suggestion.
Does cannabidiol affect alertness at work?
It can have a sedative effect, and this effect was noted in a study that is often cited elsewhere as evidence of stress reduction. In a cortisol study from 1993, participants reported sedative effects after cannabidiol in self-assessment scales (Brazilian Journal of Medical and Biological Research, 1993).
This is confirmed by the list of the most common side effects from the safety review, where fatigue ranks first (Cannabis and Cannabinoid Research, 2017). There is also a pharmacological warning: co-administration with other substances that inhibit the central nervous system compounds the effects of both, and older individuals are more susceptible to adverse effects (British Journal of Clinical Pharmacology, 2018). A person reaching for a product in the middle of the workday should be aware of this before sitting behind the wheel or engaging in tasks that require attention.
However, the picture is not clear-cut, as in situations of high stress, the opposite effect has been measured. In a study on social anxiety, the group receiving the product had less cognitive impairment during a speech than the placebo group (Neuropsychopharmacology, 2011). This is not a contradiction, but rather two different situations: under strong arousal, reducing tension helps perform a task, while on a calm workday, the same reduction may manifest as drowsiness. The only sensible practical conclusion is: try it for the first time not on a day when you are driving or operating machinery.
What won't cannabidiol do?
It will not change the number of stimuli, and those are the cause of the described problem. All the studies discussed above concern the body's reaction to a stimulus, never its removal.
It will not make up for sleep debt, replace discussions about work-time boundaries, or cure anxiety disorders or depression. It's worth recalling how narrow the evidence base is: data in humans concern almost exclusively single doses, and there are few trials in clinical populations (Neurotherapeutics, 2015). A study on a single public speaking event does not provide any certain conclusions about half a year of working in a team where everything is urgent.
There is one more thing worth knowing when planning an evening. The cortisol study from 1993 noted a sedative effect after cannabidiol in self-assessment scales, while simultaneously weakening the morning cortisol drop (Brazilian Journal of Medical and Biological Research, 1993). These two effects do not fit into a simple story about calming the stress axis, and no one has yet connected them into a coherent model. It is more honest to say that the impact of cannabidiol on hormonal regulation remains unclear than to attach a convenient interpretation to it.
What should be changed in evening screen use?
Start with the light source, as there is an experiment with humans and hormonal measurement. Researchers compared reading on a light-emitting device with reading a printed book in the hours leading up to sleep.
Participants reading from a backlit screen took longer to fall asleep, were less sleepy in the evening, secreted less melatonin, had a later circadian clock, and were less rested the next morning than when reading paper (PNAS, 2015). The authors remind us that in a representative survey among 1508 adult Americans, 90% reported using some form of electronics at least a few nights a week within an hour before going to bed.
This is an intervention with no cost and no adverse effects, and its effect has been demonstrated in controlled conditions, which cannot be said for any supplement for digital stress. Additionally, there is an hour after which work emails are not checked, and notifications are turned off at night. If evening relaxation is what you are looking for, it is also worth checking the text about kannabidiolu na sen bez melatoniny. The order matters because a supplement added to a bright evening works against something that could be turned off.
What hasn't been investigated at all in this matter?
Surprisingly much, and it's worth knowing this before spending money. The gaps are pointed out by the authors of the reviews themselves, in summaries that disappear first in commercial abstracts.
The pharmacokinetic review found parameters measured in humans in only 24 out of 792 reviewed articles and concludes with a statement about the lack of data and discrepancies between studies (Frontiers in Pharmacology, 2018). The review of evidence in anxiety disorders states that the material in humans is practically limited to a single administration (Neurotherapeutics, 2015). The safety review mentions among the gaps the impact on hormonal balance, which has not been studied, and the need for larger trials with longer administration (Cannabis and Cannabinoid Research, 2017).
The regulator speaks most sharply about this. In an assessment from 2026, the panel noted that many new studies have methodological limitations: non-standardized protocols, short duration, and concurrent medication use by participants. It also pointed out that immunotoxicity has not been studied at all, despite the fact that cannabidiol interacts with immune pathways, and there is too little data on neurological and psychiatric safety to evaluate it (EFSA Journal, 2026). This set of statements does not mean that the product is harmful. It means that we do not know what we usually expect to know about something taken daily for many months.
When is a specialist needed?
When symptoms cease to be a reaction to a difficult period and become a permanent state. The boundary is not defined by any percentage from the report, but by the picture you see in yourself over the months.
Signals that it is worth making an appointment with a psychologist, psychotherapist, or psychiatrist are well known in clinical practice: anxiety persisting continuously for many months despite lifestyle changes, waking up after a few hours of sleep with intense anxiety, panic attacks with heart palpitations and shortness of breath, loss of the ability to enjoy things that used to bring joy, thoughts of resignation, withdrawal from social contacts. None of these are indications to increase the supplement dosage.
Physiological foundations explain why it is not worth delaying this. Chronic activation of the stress axis leads to maladaptive responses, among which depression, anxiety, and cognitive impairment are mentioned (StatPearls, update 2024). The longer it lasts, the more needs to be made up later. If you are simultaneously looking for other paths of support, we have described them separately adaptogens and their impact on the nervous system, with the same caveat as here: this is a supplement, not a treatment. There is one more reason not to postpone such a conversation. A product taken on your own can mask the intensification of symptoms for several months enough to make a visit seem unnecessary, while doing nothing about the cause. The time that passes then is the only resource that cannot be regained later.
Which statements did not withstand scrutiny?
Five, and all belong to the most commonly repeated in descriptions of stress products. We list them below along with what the referenced work says about this.
| Statement from marketing materials | What the source work says |
|---|---|
| cannabidiol lowers cortisol | weakens its natural morning drop, so the concentration remains higher than after placebo (Zuardi 1993) |
| the stronger the stress, the larger the dose | the effect was demonstrated only for 300 mg, while 150 mg and 600 mg did not differ from placebo (Linares 2019) |
| the clinical series from 2019 establishes a dosing range | its abstract does not provide any dosage (Shannon 2019) |
| safe up to 1500 mg per day | the provisional safety ceiling is about 2 mg per day for a person weighing 70 kg (EFSA 2026) |
| sublingual bioavailability is several percent | in humans, it was measured only after smoking, where it amounted to 31% (Millar 2018) |
They have one thing in common: none of these statements can be found in the work referenced by the citation. For the reader, this provides a hint worth more than any of the above numbers. If a product description provides a study result, check if the link leads to a specific work, not to the journal's homepage or a press release. This one action catches most of the distortions we have removed from this text.
Frequently Asked Questions
What is digital overstimulation?
This is a common term for a state in which the nervous system receives more stimuli from screens and notifications than it can process. It is not a medical diagnosis. Typical symptoms include tension in the neck and shoulders, scattered attention, difficulty falling asleep despite fatigue, and irritability after working hours.
Does cannabidiol lower cortisol?
No. The study justifying this shows the opposite. After cannabidiol, the natural morning drop in cortisol was significantly weakened, meaning the concentration remained higher than after placebo (Brazilian Journal of Medical and Biological Research, 1993). The authors summarized that the substance disrupts the secretion of this hormone.
What is a safe starting dose?
We do not provide such a number. The European regulator has only derived a provisional safety ceiling, about 2 mg per day for a person weighing 70 kg, and noted that for people taking medications, safety cannot be established (EFSA Journal, 2026).
Does a larger dose work stronger?
No. In a randomized study of 57 healthy men, anxiety during performance was reduced only by the 300 mg dose, while 150 mg and 600 mg did not differ from placebo (Brazilian Journal of Psychiatry, 2019). The response curve is bell-shaped, not a simple upward line.
How long does it take to see the effect?
The maximum concentration occurs between zero and four hours after administration (Frontiers in Pharmacology, 2018), but very little is known about its effects with daily use, as studies in humans almost exclusively concern single doses (Neurotherapeutics, 2015).
Can cannabidiol replace digital hygiene?
No. The effects described in studies relate to the body's response to a stimulus, not the number of stimuli. The evening cessation of screen exposure has a documented impact on falling asleep and melatonin secretion (PNAS, 2015), and nothing can replace that.
Can it be combined with medications?
Not without consultation. It is metabolized in the liver and can alter the concentrations of other medications, as exemplified by clobazam, and it has additive effects with substances that inhibit the central nervous system (British Journal of Clinical Pharmacology, 2018).
Can it be used daily for months?
It is unknown, as there are almost no such studies. Few trials with chronic administration have been conducted (Neurotherapeutics, 2015), and there is also a lack of larger and longer trials (Cannabis and Cannabinoid Research, 2017). The regulator also indicates signals of liver toxicity.
What does this mean for someone working at a screen?
That cannabidiol is, in this situation, a tool of uncertain strength with well-documented limitations, not a solution to information overload. The strongest data pertains to a single dose before a stressful situation (Neuropsychopharmacology, 2011), and not daily use by someone under chronic stress.
Along the way, two assertions on which the earlier version of this guide was based have collapsed. Cannabidiol does not lower cortisol in the way that commercial materials describe, as the source study shows a weakening of its natural decline. There is also no established daily dose for a healthy person, and the only number set by the regulator is a safety ceiling placed very low.
The practical order of actions is therefore the opposite of what most advertisements suggest. First, an hour after which notifications are turned off, and an evening without a backlit screen, as this is the only intervention from this set confirmed by experiment. Then a conversation with a doctor or pharmacist, especially if you are taking anything on a regular basis. Only at the end, if after this conversation you still want to try, the choice of a product with the oils category, fully aware of how thin the evidence base is on which you are relying.
This article is for informational and educational purposes only and does not constitute medical advice. Before starting to use hemp or CBD for therapeutic purposes, consult your doctor, especially if you are taking other medications, are pregnant, or breastfeeding.
Author: Michał Waluk · Opublikowano: 2026-05-11 · Aktualizacja: 2026-08-10